CBFA2T3 / Transcriptional corepressor CBFA2T3 · IHC design guide

Design Immunohistochemistry for CBFA2T3

Plan CBFA2T3 staining in paraffin sections around its general nuclear tissue pattern (HPA tissue IHC). Start with the catalog antibody’s IHC dilution of 1:100–1:300 (datasheet), and interpret staining alongside the reported low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
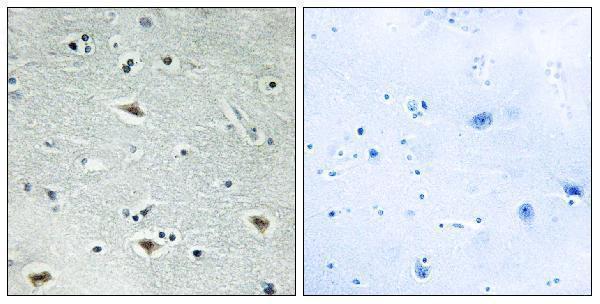
Immunohistochemistry protocol sheet for CBFA2T3 (IHC for CBFA2T3): expected localisation General nuclear tissue staining (HPA tissue IHC), antibody A30478, validated IHC image, and IHC protocol steps
Printable CBFA2T3 IHC protocol sheet — expected localisation General nuclear tissue staining (HPA tissue IHC), antibody A30478, controls and protocol steps. Open the full CBFA2T3 IHC guide →

CBFA2T3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear tissue staining (HPA tissue IHC)
Staining pattern Nuclear staining across diverse tissue cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Antibody staining has low consistency with RNA expression (HPA tissue IHC)
Regulation RNA enhanced in brain, lymphoid tissue, pancreas (HPA RNA)
Isoform / epitope 4 isoforms; epitope coverage is unreported (UniProt; datasheet)
Section 1

Recommended CBFA2T3 IHC & IF Protocols

The catalog antibody protocol is paired with published CBFA2T3 IHC methods for osteosarcoma and cutaneous T-cell lymphoma tissue (PMC4467124; PMC7002219).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A30478)
FixationImage fixative and duration unreported (datasheet A30478); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CBFA2T3, 1:100 - 1:300 (datasheet A30478)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCBFA2T3-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min (page retrieval); citrate pH 6.0 is a published alternative (PMC4467124).
Section 2

What Is the Expected CBFA2T3 Staining Pattern?

CBFA2T3 should stain predominantly in nuclei, consistent with its transcriptional corepressor role and lack of a transmembrane segment (UniProt O75081: function, subcellular location and topology). HPA describes general nuclear tissue expression and reports high staining in several cell populations, including adipocytes, respiratory epithelial cells, glial cells and Purkinje cells (HPA: tissue IHC). Its tissue IHC reliability is Approved, with low consistency between staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Distinct nuclear staining in adipocytes, respiratory epithelial cells, glial cells or Purkinje cells.This fits the reported compartment and examples of high tissue staining (HPA: general nuclear expression; High in these cell populations). Compare nuclei with the counterstain and score the relevant cell population separately (general IHC practice).
Predominantly cytoplasmic or cell-surface staining with little nuclear signal.The pattern conflicts with HPA's general nuclear IHC profile and nucleoplasmic IF localization (HPA: tissue IHC; subcellular ICC-IF). UniProt also lists a Golgi membrane location, so a limited extranuclear signal cannot be classified from compartment alone (UniProt O75081: subcellular location).
Strong signal in cells whose identity or staining pattern differs from the HPA examples.The listed HPA cells are examples, not an exhaustive positive or negative cell list (HPA: tissue IHC positive list; no negative list supplied). Confirm cell identity and nuclear localization; cross-reactivity or endogenous detection activity is possible if staining persists in appropriate controls (general IHC practice).
Diffuse color across tissue, including spaces or structures without discernible nuclei.This cannot be scored as the reported nuclear pattern (HPA: general nuclear expression). Nonspecific reagent binding, insufficient washing or endogenous enzyme activity can produce chromogenic background; interpret it against a matched control (general IHC practice).
No nuclear signal in a section expected to contain an HPA high-staining population.Check that the relevant cells are present before calling the run negative (HPA: High in listed cell populations). A missing signal can also reflect assay performance; HPA's Approved rating and low staining–RNA consistency do not guarantee a positive result in every specimen (HPA: reliability).
💡Expected CBFA2T3 appearanceA convincing positive result is discernible nuclear chromogen in identifiable cells from an HPA high-staining population; diffuse tissue color or dominant cell-surface staining does not match that reported pattern (HPA: tissue IHC; UniProt O75081: topology).
How each factor affects the staining
Compartment and topologyPrioritize nuclear signal (HPA: general nuclear expression). UniProt also records nucleolar, nucleoplasmic and Golgi membrane locations, while listing no transmembrane segment; the record does not define how often each appears in paraffin IHC (UniProt O75081: subcellular location and topology).
Choice of reference cellsAdipocytes, respiratory epithelial cells, glial cells and Purkinje cells are among the reported High populations (HPA: tissue IHC). A tissue-wide positive or negative call can obscure differences between cell populations (general IHC practice).
Strength of supporting evidenceHPA rates tissue IHC Approved but notes low consistency with RNA expression; HPA065890 is IHC Approved (HPA: reliability; antibody validation). Treat staining intensity as an observation for the tested specimen, not a fixed threshold inferred from the High label (HPA: tissue IHC).
Isoforms and epitope coverageFour isoforms are listed (UniProt O75081: isoforms). No antibody epitope or isoform coverage is supplied, so differences between specimens cannot be assigned to an isoform from this evidence.
IF/ICC: where should signal appear?HPA reports enhanced nucleoplasmic localization in ICC-IF and lists images from MCF-7, SiHa and U2OS (HPA: subcellular ICC-IF). This supports an IF localization comparison, but does not supply an IF protocol or establish the chromogenic IHC signal intensity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No stain in an expected positive cell population.The relevant cells may be absent, or the IHC run may have failed (HPA: High in listed cell populations; general IHC practice).Verify cell identity and section quality, then check the IHC-validated antibody's supplied conditions and run controls. Review retrieval and detection as general IHC variables; target-specific fixation sensitivity is unreported in the supplied sources.
Signal is mainly outside nuclei.The result differs from HPA's general nuclear IHC profile; UniProt also permits a Golgi membrane location (HPA: tissue IHC; UniProt O75081: subcellular location).Compare with the counterstain, check a reference positive population and assess localization in replicate sections (general IHC practice). Do not assign a specific organelle from chromogen alone.
Unexpected cells appear strongly positive.The HPA examples are incomplete as a cell atlas for this assay; cross-reactivity or endogenous detection activity may also contribute (HPA: supplied positive and negative lists; general IHC practice).Confirm cell identity and nuclear signal, then examine a control lacking primary antibody and an appropriate positive control (general IHC practice).
Diffuse brown background obscures nuclei.Nonspecific binding, residual detection reagent or endogenous peroxidase can contribute to chromogenic background (general IHC practice).Inspect the control lacking primary antibody; review blocking, washing and endogenous peroxidase control within the established IHC workflow (general IHC practice).
Staining is weak or varies across sections.The supplied evidence does not identify a CBFA2T3-specific cause; HPA reports low consistency between antibody staining and RNA expression (HPA: reliability).Compare like cell populations and matched controls, and document localization separately from intensity (general IHC practice). Avoid inferring CBFA2T3 abundance from RNA alone (HPA: reliability).

Sample controls for CBFA2T3 IHC & IF

🧪Run bronchus first: respiratory epithelial cells should show strong staining (HPA: High in bronchus respiratory epithelial cells). HPA detects CBFA2T3 in all 45 scored tissues, so use no-primary and isotype controls for the negative comparison; any unstained cells on the bronchus slide should show only background chromogen and should not be treated as validated target-negative cells (HPA: no negative tissue listed).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: CBFA2T3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CBFA2T3 in MCF-7, SiHa, U2OS, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and an isotype control matched to the primary antibody’s host species and clonality; use knockout material or peptide competition as a biological specificity control (catalog antibody A30478 caption: peptide-blocked brain section). For chromogenic bronchus IHC, quench endogenous peroxidase and inspect the no-primary slide for tissue background (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval dependency are unreported in the supplied evidence; optimize retrieval empirically for the paraffin-section assay (catalog antibody A30478 caption: paraffin-embedded brain tissue). The selected caption does not state a fixative, and the evidence does not establish whether frozen sections or IF are easier (catalog antibody A30478 caption: fixative unreported). For bronchus, distinguish epithelial staining from chromogen trapped in airway mucus (HPA: High in bronchus respiratory epithelial cells; standard IHC practice).

HPA tissue IHC evidence for CBFA2T3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CBFA2T3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CBFA2T3 IHC Tips

Troubleshoot chromogenic CBFA2T3 staining in paraffin sections by checking retrieval, nuclear localisation, controls and cell-specific scoring.

How should I retrieve CBFA2T3 in paraffin sections when nuclear staining is weak?
Start with Tris-EDTA pH 9.0 heat-induced retrieval at 95–98 °C for 20 min (page retrieval rule: nuclear antigen). Allow sections to cool in retrieval buffer before washing, and process control and test sections together so heating differences do not masquerade as biological variation (standard IHC practice). Assess staining in intact nuclei against the expected general nuclear pattern (HPA tissue IHC: general nuclear expression). If signal remains weak, vary retrieval time on adjacent sections while holding antibody concentration and detection constant (standard IHC optimisation). The selected A30478 paraffin-tissue caption reports peptide blocking but gives no retrieval conditions (A30478 tissue-IHC caption).
Could fixation explain weak or uneven CBFA2T3 staining?
Target-specific fixation sensitivity is unknown because no CBFA2T3 fixation comparison is supplied, and the selected paraffin-tissue caption does not state its fixative (A30478 tissue-IHC caption). Record the fixative, time before fixation, fixation duration and section age for each specimen before comparing staining (standard IHC practice). Compare adjacent sections from similarly processed blocks under the same retrieval and detection conditions to isolate a processing effect (standard IHC practice). In a controlled optimisation, change only 1 preparation variable at a time and assess nuclear signal alongside morphology (standard IHC practice; HPA tissue IHC: general nuclear expression). Do not assign fixation as the cause from staining intensity alone.
Which compartments should count as plausible CBFA2T3 staining?
Prioritise staining within intact nuclei because tissue IHC shows general nuclear expression and cell imaging enhances the nucleoplasm (HPA tissue IHC; HPA subcellular). Nucleolar staining can also be biologically plausible, and UniProt lists a Golgi membrane location for CBFA2T3 (UniProt O75081: subcellular location). Treat a solely diffuse cytoplasmic DAB deposit cautiously, since it does not match the predominant nuclear observations (HPA tissue IHC; HPA subcellular). Review the counterstain and morphology at the same focus before assigning a compartment (standard IHC practice). Score nuclear and nonnuclear signals separately, using the same compartment rules across specimens (standard IHC quantification practice).
Can this stain distinguish CBFA2T3 isoforms or modified protein?
Do not assign an IHC signal to one splice form without an epitope map: UniProt lists 4 CBFA2T3 isoforms, but the selected caption does not identify the antibody epitope (UniProt O75081: isoforms; A30478 tissue-IHC caption). Its peptide-blocked image supports competition by the immunising peptide under that image condition, without establishing which isoforms are recognised (A30478 tissue-IHC caption). CBFA2T3 includes a TAFH region at residues 171–266 and reported phosphorylation sites, so epitope position could affect interpretation of variant or modification studies (UniProt O75081: domains and modified residues). Map the antibody sequence against each isoform before making isoform-specific claims (standard antibody validation practice).
How can IF help check an ambiguous chromogenic CBFA2T3 pattern?
Use IF on a separately optimised section to ask whether CBFA2T3 signal overlaps nuclei and an independently validated marker for the expected cell type; HPA reports high staining in caudate glial cells (HPA tissue IHC). Choose a far-red fluorophore when tissue autofluorescence obscures shorter wavelengths, and include single-stain and unstained controls for multiplex interpretation (standard IF practice). After fixation, use a mild permeabilisation condition to access intracellular nuclear epitopes; UniProt reports no CBFA2T3 transmembrane segment (standard IF practice; UniProt O75081: topology and location). Judge IF localisation against enhanced nucleoplasmic staining observed in cell imaging, without treating it as validation of a particular paraffin-section workflow (HPA subcellular).
What should I check when CBFA2T3 DAB staining looks diffuse?
First compare intact nuclei with surrounding tissue: a broad nonnuclear deposit conflicts with the general nuclear tissue pattern (HPA tissue IHC). Inspect a no-primary control for detection-system background, and compare the peptide-blocked image only as a control for that selected A30478 staining condition (standard IHC practice; A30478 tissue-IHC caption). Apply a peroxidase block before HRP and DAB detection, and use an appropriate protein block to reduce nonspecific binding (standard chromogenic IHC practice). Titrate the primary antibody and shorten DAB development separately if staining obscures the counterstain (standard IHC optimisation). Keep retrieval, incubation and development conditions matched across comparisons (standard IHC practice).
How should I quantify CBFA2T3 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and nuclear compartment before reviewing group labels, consistent with the reported general nuclear pattern (HPA tissue IHC; standard scoring practice). For each region, report the percentage of positive nuclei and intensity classes, or calculate a nuclear H-score from intensity-weighted percentages on a 0–300 scale (standard IHC scoring practice). Normalise positive counts to the number of intact nuclei in the same annotated cell population, or report density per mm² of evaluable tissue (standard IHC scoring practice). Exclude folds, edges and necrotic areas by a prespecified rule (standard IHC scoring practice). Keep thresholds, counterstain and imaging settings consistent across slides (standard IHC quantification practice).
When is an apparent CBFA2T3-positive area convincing?
A convincing result places signal in morphologically intact nuclei within the assessed cell population, matching the general nuclear tissue profile and enhanced nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). Check whether the sampled cells are plausible for the tissue: HPA reports high staining in caudate glial cells and cerebellar Purkinje cells, among other cell types (HPA tissue IHC). Discount staining concentrated at section edges, folds or necrotic areas, and investigate signal in the no-primary control for endogenous enzyme or detection background (standard IHC practice). Treat intensity differences cautiously because HPA rates its tissue staining Approved while reporting low consistency with RNA expression (HPA tissue IHC: reliability).
Boster reagents

Best CBFA2T3 / Transcriptional corepressor CBFA2T3 IHC Antibodies

The catalog antibody A30478 has a paraffin-section human brain IHC image (IHC image caption); IF and ICC are listed applications, and human and mouse are listed reactivities (catalog: A30478).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human brain tissue, using MTG16 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-MTG16 Antibody
Cat # A30478

A30478 will render with an IHC image of paraffin-embedded human brain tissue and a peptide-blocked comparison (IHC image caption: A30478). IF and ICC are listed applications, but no IF image is supplied; human and mouse are listed reactivities (catalog: A30478).

Which to pick: Choose A30478 for paraffin-section tissue IHC based on its human brain image; the fixative is unreported (IHC image caption: A30478). For IF/ICC, A30478 is the listed option, with a 1:50 IF dilution, though no IF image is supplied (catalog: A30478). For human or mouse work, A30478 is listed as reactive with both species and is rabbit polyclonal; the supplied IHC image shows human tissue only (catalog and IHC image caption: A30478).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75081 (MTG16_HUMAN, Transcriptional corepressor CBFA2T3).
  2. Human Protein Atlas. CBFA2T3 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CBFA2T3 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. CBFA2T3 antibody validation summary (3 antibodies).
  5. miR-27a and miR-27a* contribute to metastatic properties of osteosarcoma cells. Oncotarget 2015 — PMC4467124.
  6. Colony-Stimulating Factor 1 Receptor (CSF1R) Activates AKT/mTOR Signaling and Promotes T-Cell Lymphoma Viability. Clinical cancer research : an official journal of the American Association for Cancer Research 2020 — PMC7002219.
  7. Failure of human rhombic lip differentiation underlies medulloblastoma formation. Nature 2022 — PMC10026724.
  8. The Transcription Co-Repressors MTG8 and MTG16 Regulate Exit of Intestinal Stem Cells From Their Niche and Differentiation Into Enterocyte vs Secretory Lineages. Gastroenterology 2020 — PMC7607384.
  9. PubMed PMID:9596646 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:9790752 — UniProt-cited evidence.