CBR1 / Carbonyl reductase [NADPH] 1 · IHC design guide

Design Immunohistochemistry for CBR1

Plan chromogenic CBR1 IHC in paraffin sections using the expected cytoplasmic pattern (HPA tissue IHC). This guide covers fixation, controls, and interpretation of cell-type differences in staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CBR1 (IHC for CBR1): expected localisation Cytoplasm (HPA tissue IHC), antibody M02825-3, validated IHC image, and IHC protocol steps
Printable CBR1 IHC protocol sheet — expected localisation Cytoplasm (HPA tissue IHC), antibody M02825-3, controls and protocol steps. Open the full CBR1 IHC guide →

CBR1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasm (HPA tissue IHC)
Staining pattern Cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M02825-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Fallopian tube+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Bronchial epithelium stains high; alveolar cells are undetected (HPA tissue IHC)
Regulation Expression varies by tissue and cell type (HPA tissue IHC)
Isoform / epitope 2 isoforms; antibody epitope coverage is unspecified (UniProt)
Section 1

Recommended CBR1 IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 heat retrieval (datasheet M02825-3). Four published CBR1 IHC protocols provide additional staining conditions (cited PMC articles).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet M02825-3)
FixationImage fixative and duration unreported (datasheet M02825-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M02825-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02825-3)
Primary antibodyRabbit monoclonal (clone 30C98) anti-CBR1, 1:50-1:200 (datasheet M02825-3)
Primary incubationOvernight at 4 °C (datasheet M02825-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M02825-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCBR1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 retrieval for the catalog antibody (datasheet M02825-3); use a published alternative when following that article’s antibody protocol.
Section 2

What Is the Expected CBR1 Staining Pattern?

Expect cytoplasmic CBR1 staining in most tissues, with strong staining in selected glandular, epithelial, myoepithelial and glial cells (HPA: tissue IHC). CBR1 is annotated as cytoplasmic, with no transmembrane segment or signal peptide (UniProt P16152). Interpret intensity by cell type: HPA reports both strongly stained cells and cells where staining was not detected, and rates agreement between antibody staining and RNA expression as medium (HPA: Enhanced tissue reliability).

What am I looking at on my slide?
Clear cytoplasmic staining in colon or duodenal glandular cells, or bronchial respiratory epithelial cells.This matches cells scored High in tissue IHC (HPA: High in colon and duodenum glandular cells; High in bronchial respiratory epithelial cells). Judge the pattern within the named cell population; an unstained neighboring population does not, by itself, invalidate the result (HPA: cell-specific tissue IHC observations).
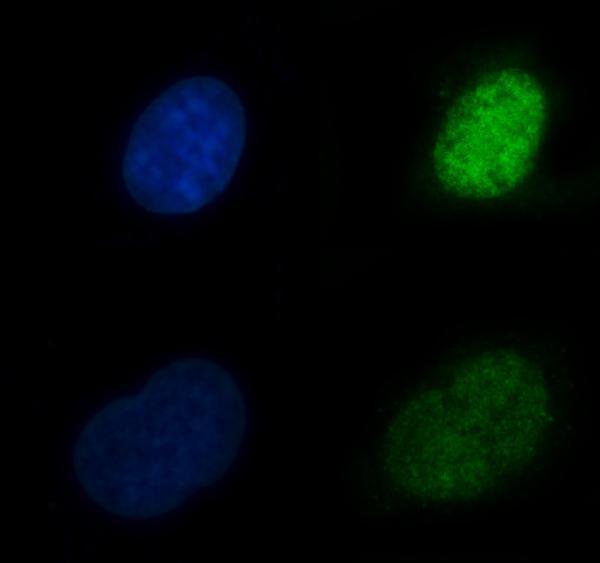
Predominantly nuclear staining with little cytoplasmic signal in a paraffin tissue section.This departs from the cytoplasmic tissue IHC profile (HPA: cytoplasmic expression in most tissues; UniProt P16152: Cytoplasm). Check controls and staining conditions before calling it specific. Nuclear signal is reported in ICC-IF, so compartment findings from the two applications should be assessed separately (HPA: approved nucleoplasm location in ICC-IF).
Strong signal in a cell population scored Not detected by HPA, such as lung alveolar cells.Treat the result as unexpected and assess antibody specificity and endogenous detection activity; it is not proof of either cause (HPA: Not detected in lung alveolar cells; general IHC practice). Compare the named cell type, since staining elsewhere in the same tissue cannot settle that discrepancy (HPA: cell-specific tissue IHC observations).
Diffuse staining across cells and surrounding tissue, with poor separation of cytoplasm from background.The pattern is difficult to score against HPA's cell-specific cytoplasmic profile (HPA: tissue IHC profile). Review blocking, washes, detection background and a no-primary control as general IHC practice. Background alone does not establish where CBR1 is expressed.
No signal in an expected positive population, such as adrenal glandular cells.An absent result in cells scored High warrants a run and reagent check (HPA: High in adrenal glandular cells). Confirm that the target cells are present, then review antibody and detection performance with appropriate controls (general IHC practice). The supplied sources do not identify a CBR1-specific cause of signal loss.
💡Expected CBR1 appearanceCall a convincing IHC positive a clearly resolved cytoplasmic signal in a cell population scored High, such as colon glandular cells (HPA: tissue IHC); uniform haze or signal confined to an unexpected cell type is suspect (general IHC practice).
How each factor affects the staining
Cell type and tissueCBR1 is cytoplasmic in most tissues, but intensity varies by population (HPA: tissue IHC profile). HPA scores breast myoepithelial and cortical glial cells High, while heart cardiomyocytes and skeletal muscle myocytes are Not detected (HPA: tissue IHC). Use the identified cells when comparing slides.
IF/ICC question: Is nuclear staining expected?Yes, in the separate ICC-IF evidence: nucleoplasm is the approved main location and cytosol an additional supported location (HPA: subcellular ICC-IF). This does not replace the cytoplasmic expectation for paraffin tissue IHC (HPA: tissue IHC profile).
Antibody validationTwo listed antibodies have Enhanced IHC validation, while one has Uncertain ICC validation (HPA: HPA018433 and CAB034291 IHC; HPA018433 ICC). Tissue reliability still reports medium agreement with RNA expression (HPA: Enhanced reliability description). Keep those qualifications when interpreting an unusual pattern.
Protein features and missing assay evidenceCBR1 has no annotated transmembrane segment or signal peptide and has 2 isoforms (UniProt P16152). The supplied sources do not map an antibody epitope to an isoform or report target-specific fixation sensitivity; neither feature supports predicting an isoform-specific stain or a fixation effect.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells are blank.The run may have failed, or the sampled section may lack the intended cells; the sources do not identify a CBR1-specific cause (HPA: High in adrenal glandular cells; general IHC practice).Locate the named cells on the counterstained section and check antibody and detection controls. Review retrieval and dilution against the validated IHC procedure as general IHC practice; no CBR1-specific retrieval condition or dilution is supplied.
The whole section is brown, including tissue without a clear cellular pattern.Non-specific detection or endogenous chromogenic activity may obscure the expected cytoplasmic pattern (general IHC practice; HPA: tissue IHC profile).Examine a no-primary control, check endogenous enzyme blocking where applicable, and review blocking and washes (general IHC practice). Interpret CBR1 only after cytoplasmic signal separates from background.
Nuclei stain more strongly than cytoplasm in tissue IHC.The result conflicts with the usual tissue IHC profile, although ICC-IF reports nucleoplasm as its main location (HPA: tissue IHC; HPA: subcellular ICC-IF).Check the no-primary control and whether expected positive cell types also show cytoplasmic signal (general IHC practice; HPA: tissue IHC). Report the compartment discrepancy rather than using the ICC-IF result alone to validate the tissue stain.
Cells scored Not detected show strong chromogenic signal.Cross-reactivity or endogenous detection activity is possible, but the observation alone cannot distinguish them (HPA: Not detected in lung alveolar cells; general IHC practice).Verify cell identity, inspect a no-primary control and compare the same run with a named High population (HPA: tissue IHC; general IHC practice). Record any persistent mismatch as unresolved.
One field appears negative while another is strongly positive.The fields may contain different cell populations; HPA reports staining at the cell-type level (HPA: tissue IHC).Score the named cells separately. For example, compare glandular cells with glandular cells when using colon as a High reference (HPA: High in colon glandular cells).
A faint signal is hard to call positive.Some populations are reported at lower intensity, and tissue IHC has medium agreement with RNA expression (HPA: Low in lymph node non-germinal center cells; HPA: Enhanced reliability description).Compare cytoplasmic contrast with background and with a High reference population on a controlled run (HPA: tissue IHC; general IHC practice). Record an equivocal result when cells cannot be separated reliably from background.

Sample controls for CBR1 IHC & IF

🧪Run adrenal gland first: glandular cells should stain (HPA: High in adrenal gland glandular cells). Use fallopian tube glandular cells as the negative tissue (HPA: Not detected); on the adrenal slide, assess adjacent nonglandular cells for background signal, without assuming they are CBR1-negative because HPA provides no internal-negative cell annotation.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Fallopian tube (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CBR1 in A-431, A-549, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and species- and immunoglobulin-class-matched rabbit IgG controls (selected-SKU caption: rabbit primary antibody), plus a CBR1 knockout or validated peptide-block control for specificity. Quench endogenous peroxidase and check background in adrenal sections before interpreting HRP/DAB staining (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 was used, but whether CBR1 staining requires retrieval is unreported (selected-SKU caption: EDTA heat retrieval). The evidence does not establish whether frozen sections or IF are easier; endogenous peroxidase can create background in adrenal HRP/DAB sections (standard IHC practice).

HPA tissue IHC evidence for CBR1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Myoepithelial cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Lung Alveolar cells Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CBR1 IHC Tips

Troubleshoot CBR1 staining in paraffin sections by checking retrieval, cellular distribution, controls, and scoring before interpreting chromogenic signal.

How should I adjust antigen retrieval when CBR1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M02825-3). The selected tissue image used that buffer before 10% goat-serum blocking and 1:50 primary incubation overnight at 4°C (caption M02825-3). If staining is weak, compare shorter and longer heating intervals on adjacent sections while keeping antibody dilution and DAB development constant; reject conditions that damage morphology. CBR1 is annotated as cytoplasmic and has no transmembrane segment (UniProt P16152), so assess whether retrieval improves cellular staining without producing diffuse background. Include a no-primary control alongside each retrieval condition to identify staining caused by the detection workflow.
Could fixation explain variable CBR1 staining between paraffin blocks?
CBR1-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not report a fixative (caption M02825-3). Record the fixative, fixation duration, tissue thickness, and processing history for each block before comparing staining intensity. For troubleshooting, stain sections from consistently processed blocks together, using heat-mediated EDTA retrieval at pH 8.0 and the same detection settings (datasheet M02825-3). Compare preserved morphology and signal in the expected cell population, rather than treating stronger DAB alone as better staining. If fixation histories differ, report that limitation when interpreting differences; neither tissue staining patterns nor CBR1 topology establishes a fixation effect.
Should nuclear CBR1 staining be considered specific in IHC?
Evaluate nuclear staining cautiously because the localisation evidence differs: UniProt annotates CBR1 in the cytoplasm (UniProt P16152), while HPA reports nucleoplasm as its main ICC/IF location and cytosol as an additional location (HPA subcellular). HPA tissue IHC describes cytoplasmic expression in most tissues (HPA tissue IHC). Check whether nuclear DAB persists in a no-primary control, tracks section edges, or accompanies diffuse staining across unrelated cell types. Score cytoplasmic and nuclear signal separately in clearly identified cells, using the same thresholds across sections. Report the compartment and assay rather than assuming that an ICC/IF localisation validates nuclear chromogenic staining.
Can this IHC antibody distinguish CBR1 isoforms or modified epitopes?
Do not assign isoform-specific staining without an antibody epitope or isoform-validation result: CBR1 has 2 annotated isoforms (UniProt P16152), and the supplied IHC caption does not map the epitope (caption M02825-3). UniProt lists modifications including residues 2, 30, and 239 (UniProt P16152). Those annotations alone cannot establish whether processing, retrieval, or a modification changes antibody binding. If an apparent cell-specific pattern matters, seek an independently mapped antibody or orthogonal expression evidence before attributing it to an isoform. Keep retrieval, antibody dilution, and DAB development matched when comparing sections so technical differences do not masquerade as epitope differences.
How can IF help assess CBR1 localisation alongside a cell-type marker?
For a separate IF/ICC experiment, pair CBR1 with a validated marker for the cell population of interest; HPA reports high CBR1 staining in glial cells of the caudate and cerebral cortex (HPA tissue IHC). Choose spectrally separated fluorophores and consider a far-red CBR1 channel if the specimen has strong short-wavelength autofluorescence. Use controlled permeabilisation to give antibodies access to cytosolic and nucleoplasmic epitopes: CBR1 has no transmembrane segment (UniProt P16152), and HPA reports both locations in ICC/IF (HPA subcellular). Acquire single-stain and no-primary controls to check bleed-through and background. Document IF fixation separately; the paraffin IHC caption does not state its fixative (caption M02825-3).
What causes widespread brown staining in a CBR1 IHC section?
First compare a no-primary section with the stained section under identical DAB development to identify background from detection chemistry. The selected image used a peroxidase-conjugated secondary and DAB (caption M02825-3); include an endogenous-peroxidase block as a general chromogenic IHC step, particularly when cellular granules stain without a coherent pattern. Check whether 10% goat-serum blocking and 1:50 primary incubation overnight at 4°C are being reproduced before changing antibody concentration (caption M02825-3). Shorten DAB development or improve washing if background rises in both expected and unexpected regions. Compare results with the predominantly cytoplasmic tissue pattern reported for CBR1 (HPA tissue IHC).
How should CBR1 staining be scored across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because HPA describes cytoplasmic expression in most tissues (HPA tissue IHC) and reports different staining levels across cell types (HPA tissue IHC). For DAB, record the percentage of positive target cells and staining intensity using a prespecified scale; an H-score can combine intensity and percentage on a 0–300 scale (standard IHC scoring). Normalize counts or positive area to the number of evaluable target cells or tissue area in mm², as appropriate to the question. Exclude folds, edges, and necrotic regions using the same rules for every section. Keep retrieval, imaging, and DAB development consistent across the comparison.
How can I distinguish true CBR1 staining from artefact?
Look for reproducible cellular staining in an anatomically identified population, with a clean no-primary control and preserved tissue morphology. HPA reports high staining in colon glandular cells and no detected staining in heart-muscle cardiomyocytes (HPA tissue IHC), offering contrasting reference patterns when those specimens are available. CBR1 is annotated as cytoplasmic (UniProt P16152), although HPA also reports nucleoplasmic ICC/IF localisation (HPA subcellular); document the observed compartment rather than treating all brown signal as equivalent. Discount signal confined to section edges, necrosis, or regions with endogenous peroxidase activity until controls resolve it. Interpret unexpected cell or compartment patterns with independent evidence before assigning them to CBR1.
Boster reagents

Best CBR1 / Carbonyl reductase [NADPH] 1 IHC Antibodies

The catalog antibodies have human paraffin-section IHC images (M02825-3 and A02825-1 IHC captions). A02825-1 also has an A549 IF image and lists human, mouse, and rat reactivity (A02825-1 IF caption; catalog reactivity).

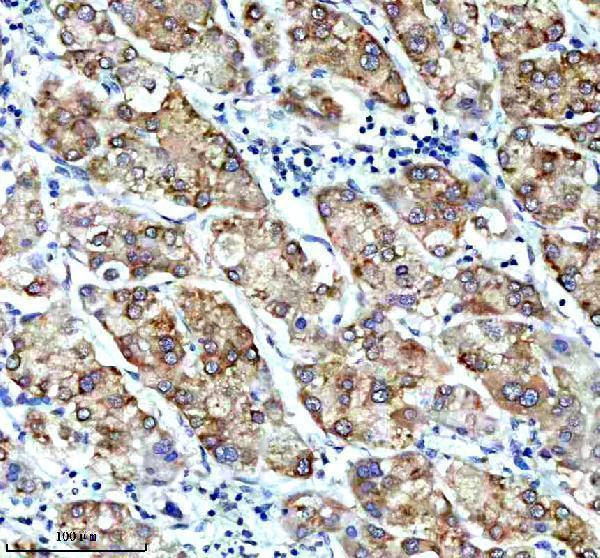
Real IHC data IHC analysis of CBR1 using anti-CBR1 antibody (M02825-3). CBR1 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-CBR1 Antibody (M02825-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CBR1 Rabbit Monoclonal Antibody
Cat # M02825-3
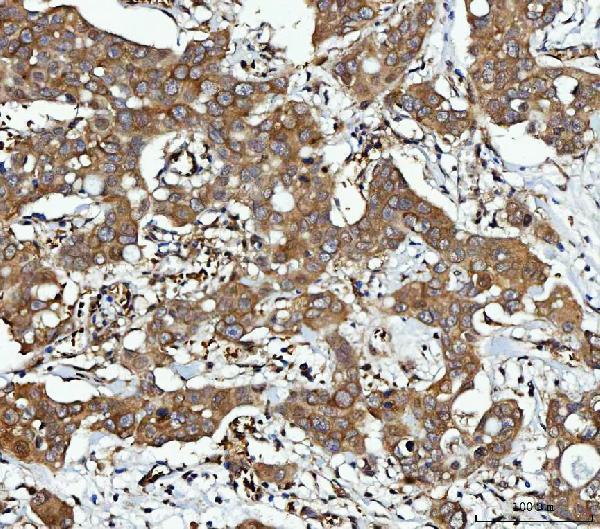
Real IHC data IHC analysis of CBR1 using anti-CBR1 antibody (A02825-1). CBR1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-CBR1 Antibody (A02825-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CBR1 ® Antibody
Cat # A02825-1

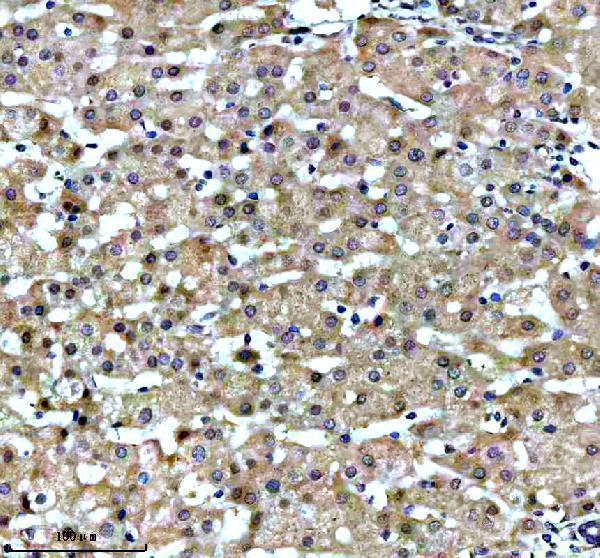
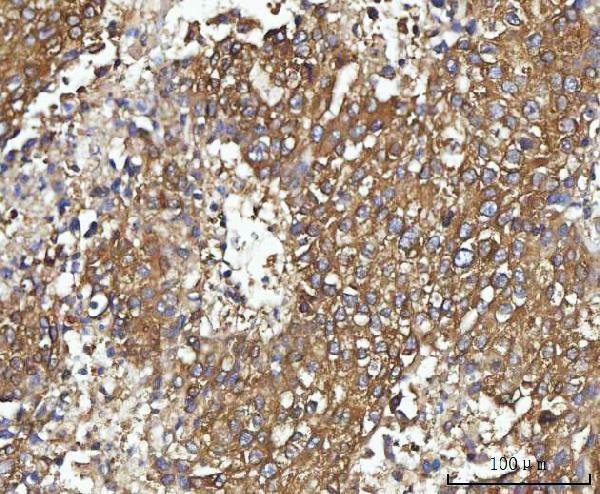
M02825-3 has IHC images of human liver cancer and liver paraffin sections; its listed reactivity is human (M02825-3 IHC captions; catalog reactivity). A02825-1 has IHC images of human breast, liver, lung, and rectal cancer paraffin sections, plus an IF image of A549 cells (A02825-1 image captions).

Which to pick: For human tissue IHC, M02825-3 offers a rabbit monoclonal with a human liver cancer paraffin-section image using EDTA retrieval at pH 8.0 and primary antibody at 1:50; the fixative is unreported (M02825-3 catalog clone and reactivity; M02825-3 IHC caption). For IF/ICC, A02825-1 has an A549 cell IF image using 5 μg/mL primary antibody, while M02825-3 lists IF/ICC without an IF image (A02825-1 IF caption; M02825-3 catalog applications and image alts). For mouse or rat work, A02825-1 lists reactivity with both species, but its supplied IHC images show human tissue (A02825-1 catalog reactivity; A02825-1 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P16152 (CBR1_HUMAN, Carbonyl reductase [NADPH] 1).
  2. Human Protein Atlas. CBR1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CBR1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. CBR1 antibody validation summary (2 antibodies).
  5. Upregulation of Carbonyl Reductase 1 by Nrf2 as a Potential Therapeutic Intervention for Ischemia/ Reperfusion Injury during Liver Transplantation. Molecules and cells 2019 — PMC6776159.
  6. Maternal 25-Hydroxyvitamin D Deficiency Promoted Metabolic Syndrome and Downregulated Nrf2/CBR1 Pathway in Offspring. Frontiers in pharmacology 2020 — PMC7058637.
  7. Decreased carbonyl reductase 1 expression promotes tumor growth via epithelial mesenchymal transition in uterine cervical squamous cell carcinomas. Reproductive medicine and biology 2018 — PMC5902461.
  8. Low carbonyl reductase 1 expression is associated with poor prognosis in patients with oral squamous cell carcinoma. Molecular and clinical oncology 2018 — PMC5795658.
  9. PubMed PMID:3141401 — UniProt-cited evidence.
  10. PubMed PMID:2182121 — UniProt-cited evidence.
  11. PubMed PMID:1921984 — UniProt-cited evidence.