This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section CBX3 IHC around its ubiquitous nuclear staining pattern (HPA tissue IHC). Use the catalog antibody’s 0.5–1 μg/mL IHC dilution as a starting range (datasheet A01142), and compare nuclear staining across cells within each section (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclei across tissues (HPA tissue IHC) | |
| Staining pattern | Ubiquitous nuclear staining across cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6 HIER, heat-mediated (datasheet A01142) | |
| Positive control | Lung+4 more · see all | |
| Negative control | None in HPA (detected in all 44 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Ubiquitous nuclear signal limits unstained-cell controls (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | No isoforms annotated; chain spans residues 2–183 (UniProt) |
The catalog antibody’s IHC protocol (datasheet A01142) is accompanied by published CBX3 tissue protocols (PMC6540543; PMC5920882; PMC8357267).
| Sample | Paraffin-embedded human mammary cancer tissue; fixative not specified (datasheet A01142) |
| Fixation | Image fixative and duration unreported (datasheet A01142); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6, 20 min (datasheet A01142) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A01142) |
| Primary antibody | Rabbit anti-CBX3, 0.5-1μg/ml (datasheet A01142) |
| Primary incubation | Overnight at 4 °C (datasheet A01142) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A01142) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CBX3-positive staining in alveolar cells type I of lung (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control. |
CBX3 should appear predominantly in nuclei across many cell types, consistent with the HPA description of ubiquitous nuclear expression and supported tissue IHC reliability (HPA: tissue IHC). It is a nuclear protein with no transmembrane segment (UniProt Q13185: subcellular location and topology). For a clear positive reference, examine alveolar type I cells, cytotrophoblasts, melanocytes, or pachytene spermatocytes, each reported with high staining (HPA: tissue IHC).
| Distinct nuclear chromogen in an expected cell population, with interpretable tissue structure and limited staining outside nuclei. | This fits CBX3 localisation (UniProt Q13185: nucleus; HPA: ubiquitous nuclear expression). Compare intensity within identified cells: HPA reports high staining in lung alveolar type I cells and placental cytotrophoblasts, but low staining in liver hepatocytes. Those categories describe observed patterns, not universal cutoffs for every section (HPA: tissue IHC). |
| Predominantly cytoplasmic, membranous, or extracellular deposit while the expected nuclei remain unstained. | That compartment conflicts with the supported nuclear pattern (UniProt Q13185: nucleus; HPA: tissue IHC). Treat it as a suspect IHC result and check morphology and detection controls (general IHC practice). UniProt notes possible association with microtubules and mitotic poles during mitosis; that potential does not establish diffuse cytoplasmic staining as the expected tissue pattern (UniProt Q13185: subcellular location). |
| Strong staining appears selectively in an unexpected cell population, while an expected high-staining population is weak or absent. | Check cell identification and controls before interpreting the selective signal; cross-reactivity or endogenous detection activity are possibilities (general IHC practice). CBX3 is described as ubiquitously nuclear, so signal in another cell type alone does not prove a false positive, and the supplied HPA profile provides no negative tissue reference (HPA: tissue IHC). |
| Brown haze covers several tissue compartments or obscures the boundary between nuclei and surrounding tissue. | Diffuse background prevents a confident nuclear localisation call. Review the detection-only control and staining development, then reassess individual nuclei on the same section (general IHC practice). HPA's supported reliability describes agreement between antibody staining and RNA expression data; it does not validate an uninterpretable slide (HPA: tissue IHC reliability). |
| No nuclear signal is visible in a suitable section containing an expected high-staining population. | Consider a technical failure before concluding that CBX3 is absent: HPA reports high staining in alveolar type I cells, cytotrophoblasts, melanocytes, and pachytene spermatocytes (HPA: tissue IHC). Confirm the relevant cells are present, then review the IHC workflow and controls (general IHC practice). One failed section cannot overturn the reported tissue pattern. |
| Tissue and cell selection (HPA: tissue IHC) | Choose an identifiable high-staining population for the positive reference: lung alveolar type I cells, placental cytotrophoblasts, skin melanocytes, or testicular pachytene spermatocytes (HPA: tissue IHC). Hepatocytes and skeletal myocytes are reported low, not negative; weak staining there does not establish assay failure (HPA: tissue IHC). |
| Compartment and chromatin context (UniProt Q13185; HPA: subcellular ICC-IF) | Score nuclei rather than a membrane or secreted compartment: UniProt places CBX3 in the nucleus and reports no transmembrane segment. UniProt says it associates with euchromatin and is largely excluded from constitutive heterochromatin; HPA ICC-IF supports mainly nucleoplasmic localisation with additional nuclear bodies. Nuclear bodies are an IF observation, not a required chromogenic IHC feature. |
| Antibody evidence (HPA: antibody validation) | HPA lists IHC support for both HPA004902 and CAB001973, and ICC support for HPA004902; no ICC status is supplied for CAB001973 (HPA: antibody validation). This supports the listed applications but does not establish identical staining with every antibody or guarantee performance under a different IHC workflow (general IHC practice). |
| Protein annotation limits (UniProt Q13185) | UniProt reports no isoforms, signal peptide, propeptide, or glycosylation sites, and identifies a chain spanning residues 2–183 (UniProt Q13185: processing and isoforms). These annotations provide no evidence for a shed staining compartment or an isoform-specific tissue pattern. The supplied record does not locate the antibody epitope or establish CBX3-specific fixation or retrieval sensitivity. |
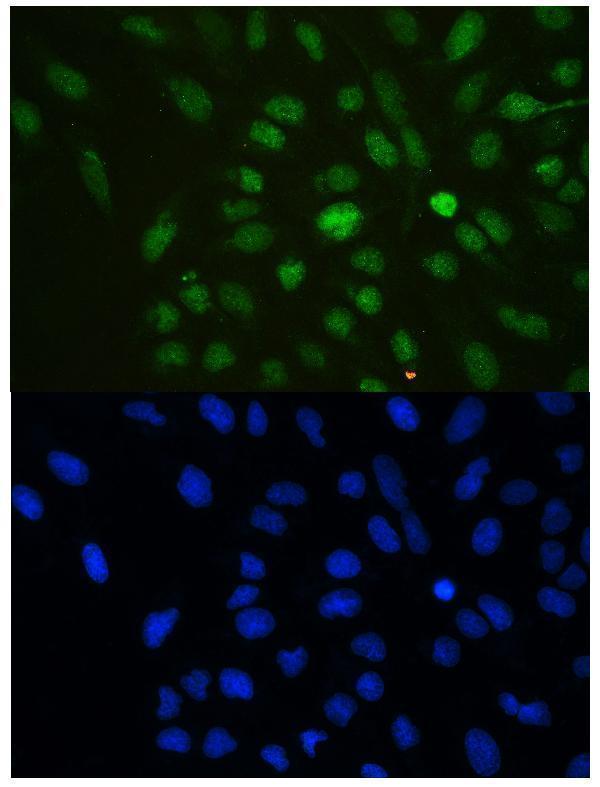
| IF/ICC Q: What localisation should a separate IF/ICC guide assess? (HPA: subcellular ICC-IF) | A: Mainly nucleoplasmic signal, with additional nuclear bodies, is supported by HPA ICC-IF images from A-431, U-251MG, and U2OS cells (HPA: subcellular ICC-IF). This is a localisation comparison for the separate IF/ICC application; it does not supply an IF protocol or change the nuclear IHC scoring criterion. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells lack nuclear chromogen. | The high-staining population may be absent from the section, or an IHC step may have failed (HPA: tissue IHC; general IHC practice). | Identify the cells on a counterstained section, then check the positive control, antibody preparation, retrieval record, and detection steps (general IHC practice). No CBX3-specific retrieval condition or fixation effect is supplied. |
| Signal is mainly outside nuclei. | The observed compartment disagrees with the nuclear pattern; nonspecific staining or a detection artifact is possible (UniProt Q13185: nucleus; HPA: tissue IHC; general IHC practice). | Recheck cell boundaries and the detection-only control, then assess whether nuclear staining is independently visible (general IHC practice). Do not score the nonnuclear deposit as CBX3 solely because it is intense. |
| Brown deposit appears when primary antibody is omitted. | Endogenous activity or another detection-system contribution is possible (general IHC practice). | Address the source indicated by the detection-only control, then repeat the comparison with the same tissue type (general IHC practice). HPA tissue staining levels do not identify the source of that deposit. |
| Diffuse background makes nuclei hard to distinguish. | Excess background or overdevelopment may obscure the expected nuclear pattern (general IHC practice; UniProt Q13185: nucleus). | Review blocking, washing, antibody dilution, and chromogen development under the chosen IHC workflow; compare controls before assigning nuclear scores (general IHC practice). The supplied evidence specifies no dilution or development time. |
| A low-staining tissue appears negative or much brighter than expected. | Low is an HPA staining category, not a formal negative control; technical background or cell identification may affect the comparison (HPA: tissue IHC; general IHC practice). | Compare identified cells with an HPA high-staining population on a suitable control section and review background controls (HPA: tissue IHC; general IHC practice). Avoid calling the tissue CBX3-negative or the brighter result specific from intensity alone. |
| Fine nuclear bodies seen by IF/ICC cannot be resolved in chromogenic IHC. | HPA reports nuclear bodies as an additional ICC-IF location, while its tissue IHC profile describes ubiquitous nuclear expression (HPA: subcellular ICC-IF; HPA: tissue IHC). | Score the predominant nuclear IHC pattern in identifiable cells; reserve assessment of nuclear bodies for the separate IF/ICC guide (HPA: tissue IHC; HPA: subcellular ICC-IF). |


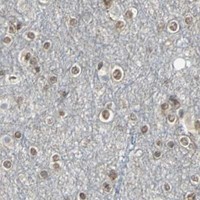
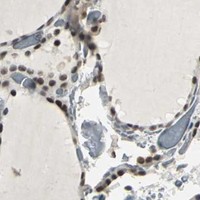
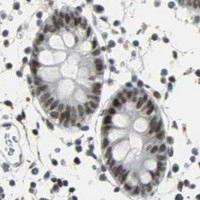
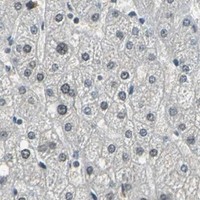


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Lung | Alveolar cells type I | High | Protein (IHC) | HPA → |
| Placenta | Cytotrophoblasts | High | Protein (IHC) | HPA → |
| Skin | Melanocytes | High | Protein (IHC) | HPA → |
| Testis | Pachytene spermatocytes | High | Protein (IHC) | HPA → |
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: CBX3 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot CBX3 staining in paraffin sections by checking nuclear localisation, the documented retrieval conditions, and controls before comparing chromogenic signal across samples.
A01142 has pictured IHC results in human, mouse and rat paraffin sections, plus an IF result in U20S cells (A01142 image captions).
The rendered SKU is A01142; its IHC captions show human mammary and rectal cancer and mouse and rat small intestine in paraffin sections (A01142 IHC captions). Its IF caption shows U20S cells, and the catalog lists Human, Mouse and Rat reactivity (A01142 IF caption; catalog reactivity).
Which to pick: Choose A01142 for tissue IHC and pictured cross-species examples: its captions document paraffin sections from Human, Mouse and Rat, but do not report the fixative (A01142 IHC captions). Choose A01142 for IF/ICC because its application list includes both and its IF caption shows U20S cells (A01142 catalog applications; IF caption). M01142-1 is a rabbit monoclonal listed for IHC and Human, Mouse and Rat reactivity, but has no supplied IHC image caption (M01142-1 catalog).