CBX5 / Chromobox protein homolog 5 · IHC design guide

Design Immunohistochemistry for CBX5

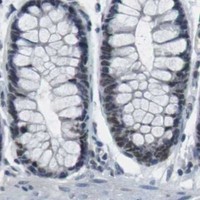
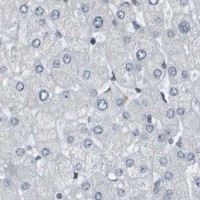
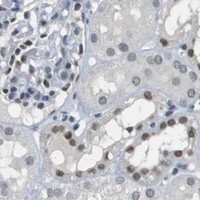
CBX5 shows nuclear staining in most tissues by IHC (HPA tissue IHC). This guide helps plan paraffin-section staining with the IHC-validated antibody and select tissue controls using the reported cell-specific staining pattern (datasheet M02780-2; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CBX5 (IHC for CBX5): expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody M02780-2, validated IHC image, and IHC protocol steps
Printable CBX5 IHC protocol sheet — expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody M02780-2, controls and protocol steps. Open the full CBX5 IHC guide →

CBX5 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in most tissues (HPA tissue IHC)
Staining pattern Nuclear staining across varied tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M02780-2)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Heart muscle+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Cardiomyocytes lack detectable staining (HPA tissue IHC)
Regulation H3Y41ph excludes chromatin binding (UniProt)
Isoform / epitope No annotated isoforms; one chain spans aa 1–191 (UniProt)
Section 1

Recommended CBX5 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: M02780-2) with published CBX5 chromogenic IHC protocols (PMC3419921; PMC12450695).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet M02780-2)
FixationImage fixative and duration unreported (datasheet M02780-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M02780-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02780-2)
Primary antibodyMouse monoclonal (clone 8G6) anti-CBX5, 2μg/ml (datasheet M02780-2)
Primary incubationOvernight at 4 °C (datasheet M02780-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet M02780-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCBX5-positive staining in cells in molecular layer of cerebellum (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: M02780-2); the lung cancer study used 1× Trilogy in water (PMC3419921).
Section 2

What Is the Expected CBX5 Staining Pattern?

CBX5 should appear chiefly in nuclei, consistent with its chromatin and centromere associations and lack of a transmembrane segment (UniProt P45973). In paraffin-section IHC, expect staining in many tissues, including neuronal cells in cerebral cortex and cytotrophoblasts in placenta (HPA tissue IHC: High). HPA describes nuclear expression in most tissues but rates agreement between staining and RNA expression as medium (HPA tissue IHC: Enhanced reliability).

What am I looking at on my slide?
Distinct nuclear chromogen in cerebral cortex neuronal cells or placental cytotrophoblasts, with limited surrounding color.This fits CBX5 localization (UniProt P45973: nucleus and chromatin) and the High staining recorded for those specific cells (HPA tissue IHC). Judge cell identity and nuclear placement together; staining elsewhere in the section does not establish that these reference populations stained.
Predominantly cytoplasmic or membranous color, while nuclei remain clear.That compartment conflicts with the expected nuclear pattern (UniProt P45973; HPA tissue IHC: nuclear expression in most tissues). Treat it as a possible staining or interpretation artifact. Examine a known-positive cell population and a no-primary control before calling the cytoplasmic color CBX5.
Strong color in cardiomyocytes or skeletal-muscle myocytes.HPA records CBX5 as Not detected in those named cell types (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity, especially if nuclei are not clearly stained. These are cell-specific observations; they do not declare every cell in heart or skeletal muscle negative.
Diffuse color across stroma, lumina, or nuclei and cytoplasm alike, obscuring cell borders.A uniform haze is difficult to score as CBX5 because the reference distribution is nuclear (HPA tissue IHC; UniProt P45973). Background from detection reagents or inadequate washing is a general IHC possibility; compare no-primary and positive-control sections before assigning a biological pattern.
No nuclear signal in the expected cells of a known-positive control section.Absent staining in cerebral cortex neuronal cells or placental cytotrophoblasts disagrees with their High HPA observations (HPA tissue IHC). First assess section quality, antibody and detection performance, and whether those exact cells are present; a failed control cannot support a negative result in the test section.
💡Expected CBX5 appearanceCall a result positive when discernible nuclear chromogen occurs in the relevant cells, such as High-staining cerebral cortex neuronal cells or placental cytotrophoblasts (HPA tissue IHC; UniProt P45973: nucleus); cytoplasmic-only color or broad haze is suspect against that reference pattern.
How each factor affects the staining
Nuclear and chromatin associationCBX5 is a heterochromatin component and is reported at centromeric and pericentromeric regions (UniProt P45973). Nuclear staining is therefore the primary compartment check. A paraffin-section chromogenic result need not resolve individual centromeres to be consistent with this localization.
Cell-specific reference intensityHPA reports High staining in cerebellar molecular-layer cells, hippocampal glial cells, gallbladder glandular cells, and parathyroid glandular cells; prostate glandular cells are Low (HPA tissue IHC). Compare the same cell type when choosing controls or interpreting apparent intensity differences.
Strength of antibody evidenceHPA lists CAB017548 as IHC Enhanced; HPA016699 has no listed IHC status (HPA antibodies). The tissue profile also has Enhanced reliability, described as medium staining-to-RNA consistency (HPA tissue IHC). Keep those two evidence labels distinct when judging an unexpected pattern.
Protein architectureThe supplied record describes a single 1–191 chain, no signal peptide, no transmembrane segment, and no annotated isoforms (UniProt P45973). Those annotations support a nuclear, intracellular interpretation; they provide no basis for predicting a secreted, shed, or membrane staining pattern.
IF/ICC Q: Where should signal appear?A: In the nucleoplasm (HPA subcellular ICC-IF: enhanced main location). UniProt also places CBX5 in the nucleus and on chromosomes, including centromeres (UniProt P45973). This is an IF/ICC localization check, not an additional IHC protocol or a claim that every nucleus must stain equally.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive nuclei are blank.The run may have failed, or the expected cells may be missing from the examined area; HPA reports those cells as High (HPA tissue IHC).Locate the named positive cell population, then check antibody preparation, detection reagents, and run controls. Review antigen-retrieval and dilution records as general IHC workflow checks; no CBX5-specific retrieval condition is supplied.
Chromogen is mainly outside nuclei.The compartment disagrees with CBX5's nuclear localization (UniProt P45973; HPA tissue IHC). Off-target staining or background is possible.Compare a no-primary section and the same run's positive section. Confirm that counterstained nuclei are identifiable before scoring localization; adjust general blocking or washing only if the controls implicate background.
Cardiomyocytes stain strongly.HPA records cardiomyocytes as Not detected (HPA tissue IHC); antibody cross-reactivity or endogenous chromogenic activity is possible.Check nuclear placement and a no-primary control. If using enzyme detection, evaluate its endogenous-activity control and blocking step as general IHC practice before accepting this as CBX5 staining.
Diffuse color masks tissue detail.A broad haze prevents assessment of the nuclear reference pattern (HPA tissue IHC; UniProt P45973). Detection background is a general IHC possibility.Inspect no-primary and reagent controls, then review wash and blocking steps. Reassess only where nuclei and cell boundaries can be distinguished.
A low-expression reference cell looks negative.HPA rates prostate glandular cells Low, whereas parathyroid glandular cells are High (HPA tissue IHC).Use a named high-staining population to verify the run first. Score the low-staining population against its own reference and background; avoid treating every faint nucleus as a technical failure.
An unfamiliar tissue shows patchy nuclear staining.HPA's profile is cell-specific and has medium staining-to-RNA consistency (HPA tissue IHC: Enhanced reliability); the supplied record does not establish the expected intensity for every cell.Identify and score the stained cell populations separately. Compare them with the supplied HPA cell-level examples, and report unsupported populations as observations rather than assigning a reference intensity.

Sample controls for CBX5 IHC & IF

🧪Run cerebral cortex first and expect neuronal nuclei to stain (HPA: High in cerebral cortex neuronal cells; UniProt P45973: nuclear localization). Run skeletal muscle as the negative tissue, where myocytes are not detected (HPA: Not detected in skeletal muscle myocytes); on the cortex slide, unstained nuclei can serve as local background comparators, but HPA does not identify a specific negative cortical cell type (HPA: High in neuronal cells).
Positive control tissue: Cerebellum (Cells in molecular layer, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CBX5 in U-251MG, U2OS, A-431, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a concentration-matched mouse IgG isotype control for the captioned mouse primary, and a CBX5 knockout specimen if available (M02780-2 caption: mouse primary; standard IHC practice). For chromogenic brain sections, check endogenous peroxidase and biotin background because the caption uses biotin-based detection with DAB; for IF, check tissue autofluorescence (M02780-2 caption: biotinylated secondary, SABC and DAB; standard IHC/IF practice).
⚠️Feasibility: A CBX5-specific fixation window or fixation effect is unreported, and the selected M02780-2 paraffin-section caption does not state the fixative (M02780-2 caption). The caption uses heat retrieval in EDTA at pH 8.0 for rat brain, but does not establish that this retrieval is required for human cerebral cortex (M02780-2 caption; HPA: High in cerebral cortex neuronal cells). Frozen-section ease cannot be ranked from the supplied evidence; ICC-IF shows nucleoplasmic localization, while brain lipofuscin, if present, can complicate chromogenic or fluorescent scoring (HPA subcellular: nucleoplasm; standard histology practice).

HPA tissue IHC evidence for CBX5

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Hippocampus Glial cells High Protein (IHC) HPA →
Parathyroid gland Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Soft tissue Chondrocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CBX5 IHC Tips

Troubleshoot CBX5 staining in paraffin sections by checking nuclear localisation, retrieval, detection background and cell type before comparing chromogenic signal across specimens.

What retrieval should I start with for CBX5 in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M02780-2). The rat brain example used this retrieval before overnight incubation at 4°C with 2 μg/ml catalog antibody (datasheet M02780-2). If nuclear staining is weak, vary heating duration on matched sections while keeping antibody concentration and chromogenic detection constant; the caption does not specify a heating duration (datasheet M02780-2). Check that improved signal remains nuclear, since CBX5 is associated with nuclear heterochromatin and chromosomes (UniProt P45973). Excessive heating can damage section morphology, making apparent gains in staining difficult to interpret (standard IHC practice).
Could fixation explain weak or uneven CBX5 staining?
The paraffin-section rat brain caption does not state its fixative, so target-specific CBX5 sensitivity to fixation is unknown (datasheet M02780-2). Record the fixative and fixation duration for each specimen, then compare matched sections processed with the same EDTA pH 8.0 retrieval and detection conditions (datasheet M02780-2; standard IHC practice). Evaluate nuclear staining alongside preserved tissue morphology, because uneven processing can complicate interpretation of chromogenic sections (standard IHC practice). The presence of nuclear staining across many tissues in an independent atlas does not establish how this catalog antibody responds to a particular fixative (HPA tissue IHC).
Where should convincing CBX5 staining appear in tissue?
Score CBX5 primarily within nuclei: it is a nuclear and chromosome-associated protein, including at centromeric and pericentromeric heterochromatin (UniProt P45973). Nuclear expression across most tissues is also reported by tissue IHC, while cell-based imaging identifies the nucleoplasm (HPA tissue IHC; HPA subcellular). Inspect the counterstain and DAB signal at high magnification to decide whether staining follows individual nuclei rather than tissue edges or extracellular material (standard IHC practice). During mitosis, chromosome-associated signal can differ from the interphase nuclear pattern, so record mitotic cells separately when assessing unusual staining (UniProt P45973). Predominantly diffuse cytoplasmic signal warrants a background check (UniProt P45973; standard IHC practice).
How can epitope accessibility affect CBX5 IHC?
The supplied record lists 0 alternative isoforms and a 1–191 chain, so an isoform switch is not an evidenced explanation for discordant staining (UniProt P45973). CBX5 contains a chromodomain at residues 20–78 and a chromoshadow domain at 121–179, but the catalog antibody’s recognized epitope is not specified here (UniProt P45973; datasheet M02780-2). Reported modifications include N-terminal phosphoserines and acetyllysine 40; their effect on this antibody’s binding has not been established (UniProt P45973; datasheet M02780-2). When staining differs between specimens, first compare retrieval, morphology and nuclear signal under identical conditions before attributing the difference to epitope masking (standard IHC practice).
How should I compare CBX5 fluorescence with chromogenic IHC?
Use IF/ICC as a separate validation context when comparing it with this paraffin-section, chromogenic IHC workflow (datasheet M02780-2). For a multiplex experiment, pair CBX5 with a cell-type marker relevant to the specimen; neuronal cells in cerebral cortex are reported as high for CBX5 by tissue IHC (HPA tissue IHC). Choose spectrally separated fluorophores and inspect unstained tissue for autofluorescence before interpreting overlap (standard IF practice). Because CBX5 is nuclear and has no transmembrane segment, permeabilisation must allow antibody access to the nucleus; assess whether the resulting fluorescence follows nuclei rather than tissue background (UniProt P45973; standard IF practice).
What should I check when DAB obscures CBX5 nuclei?
The documented chromogenic example uses a biotinylated secondary antibody, a streptavidin-biotin complex and DAB (datasheet M02780-2). Check a no-primary section to locate detection-system background, and include a peroxidase block when using DAB-based detection (standard IHC practice). If staining persists in the no-primary section, investigate endogenous enzyme activity and background associated with the biotin-based system before adjusting CBX5 antibody concentration (standard IHC practice; datasheet M02780-2). The documented primary concentration is 2 μg/ml after a 10% goat-serum block; compare any concentration changes on matched sections while preserving nuclear morphology (datasheet M02780-2; standard IHC practice).
How should I quantify CBX5 across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, then measure the percentage of nuclei with CBX5 signal and nuclear staining intensity (standard IHC practice; UniProt P45973). An H-score can combine intensity classes 0–3 with their percentages, giving a possible range of 0–300 (standard IHC practice). Normalize positive-cell counts to the total evaluable nuclei in the same region, or report positive nuclei per mm² when area is the comparison unit (standard IHC practice). Keep retrieval, DAB development, counterstain and image settings consistent across specimens, and exclude damaged or poorly preserved areas from scoring (standard IHC practice).
How can I distinguish true CBX5 staining from artefact?
A credible CBX5-positive cell has signal aligned with its nucleus, consistent with nuclear expression and chromosome association (HPA tissue IHC; UniProt P45973). Check the cell type as well as the compartment: cerebral cortical neuronal cells are reported high, whereas heart-muscle cardiomyocytes are reported not detected in the atlas (HPA tissue IHC). Treat staining concentrated at section edges, in necrotic areas or outside nuclei cautiously, and compare it with a no-primary control for detection background (standard IHC practice). Residual DAB signal after omitting the primary antibody points toward detection artefact, including endogenous enzyme activity, rather than confirmed CBX5 expression (standard IHC practice).
Boster reagents

Best CBX5 / Chromobox protein homolog 5 IHC Antibodies

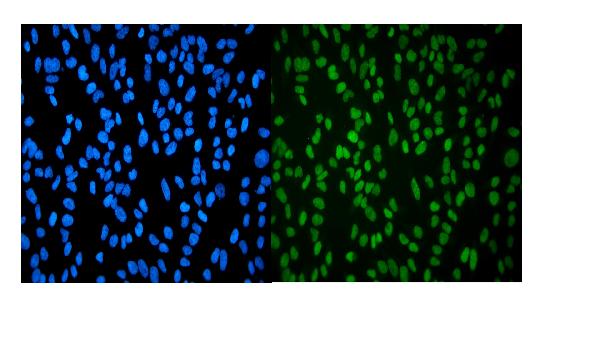
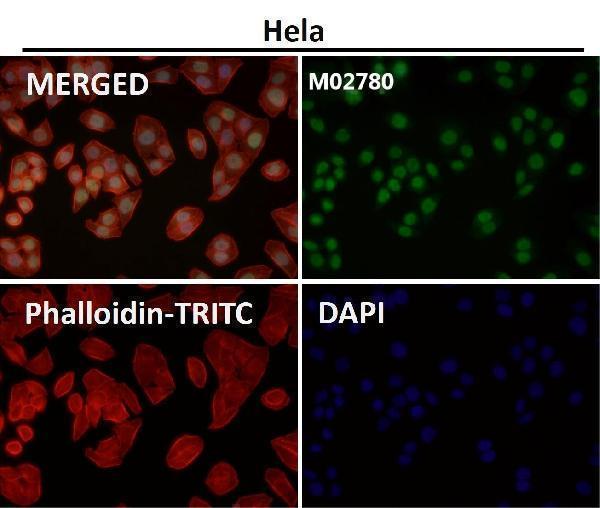
Anti-CBX5 antibodies have IHC images from human, mouse, and rat tissues (catalog IHC captions), plus IF images from HeLa and A549 cells (catalog IF captions).

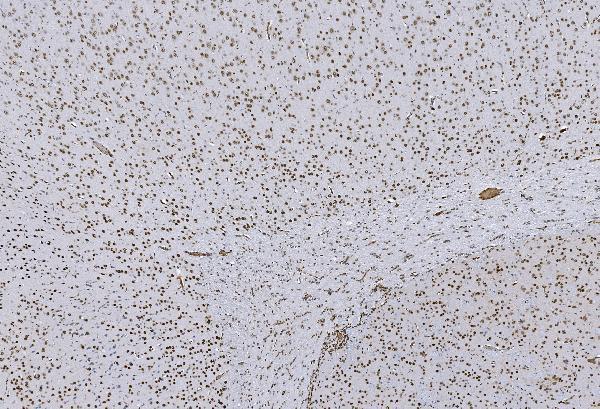
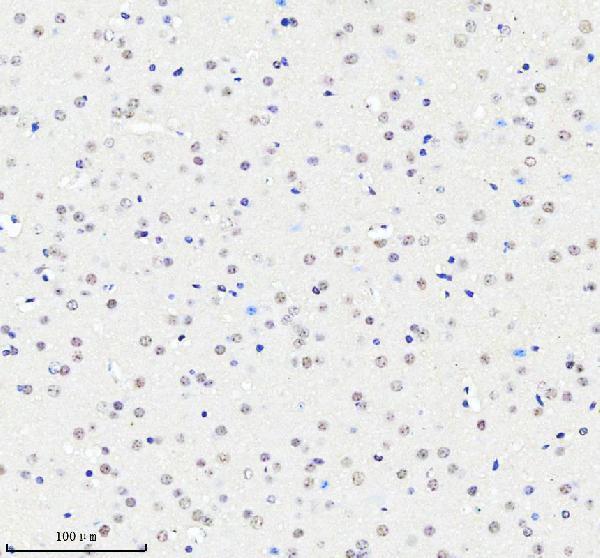
Real IHC data IHC analysis of HP1 alpha/CBX5 using anti-HP1 alpha/CBX5 antibody (M02780-2). HP1 alpha/CBX5 was detected in paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml mouse anti-HP1 alpha/CBX5 Antibody (M02780-2) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-HP1 alpha/CBX5 Antibody ® (monoclonal, 8G6)
Cat # M02780-2
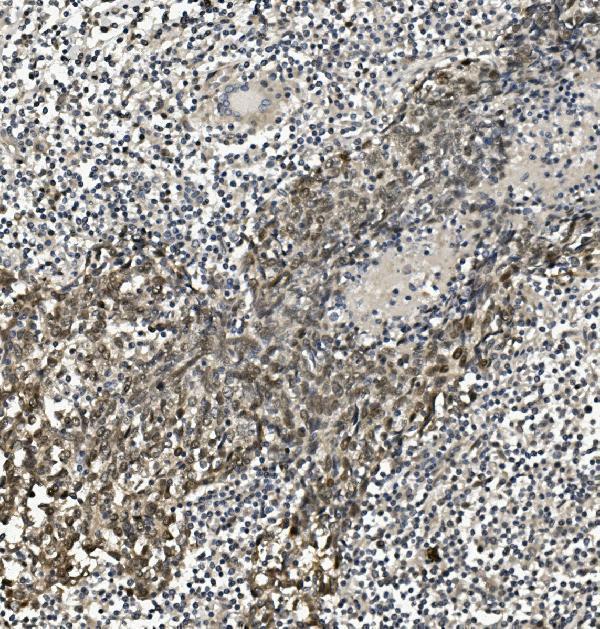
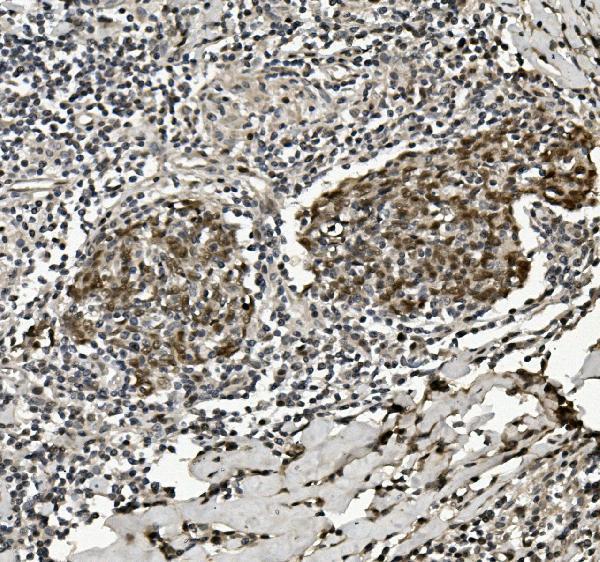
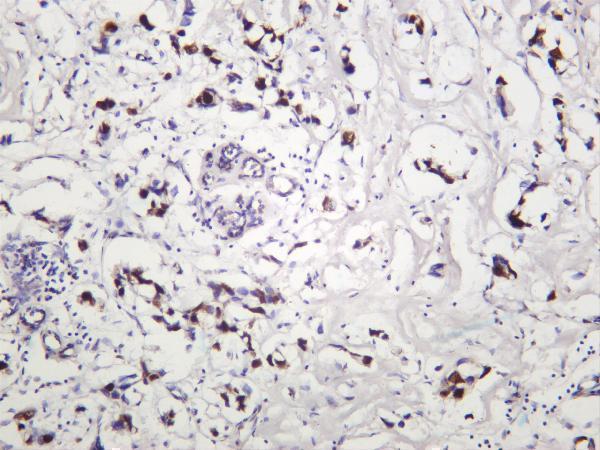
Real IHC data IHC analysis of HP1 alpha/CBX5 using anti-HP1 alpha/CBX5 antibody (A02780-3). HP1 alpha/CBX5 was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-HP1 alpha/CBX5 Antibody (A02780-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-HP1 alpha/CBX5 Antibody ®
Cat # A02780-3
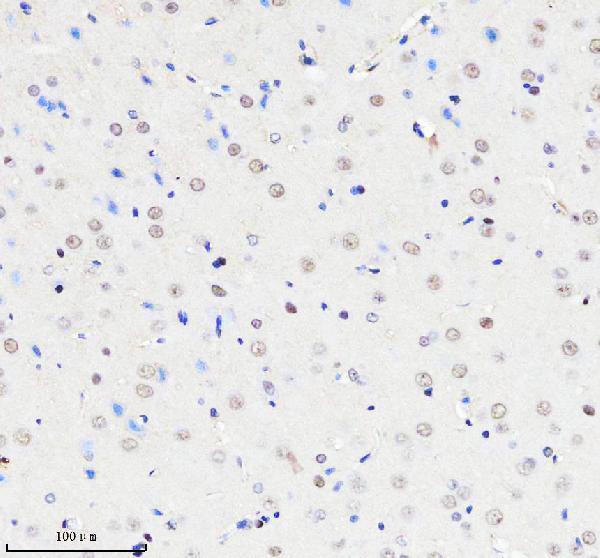
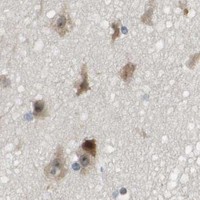
Real IHC data IHC analysis of CBX5 using anti-CBX5 antibody (M02780). CBX5 was detected in a paraffin-embedded section of mouse brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-CBX5 Antibody (M02780) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-HP1 alpha CBX5 Rabbit Monoclonal Antibody
Cat # M02780
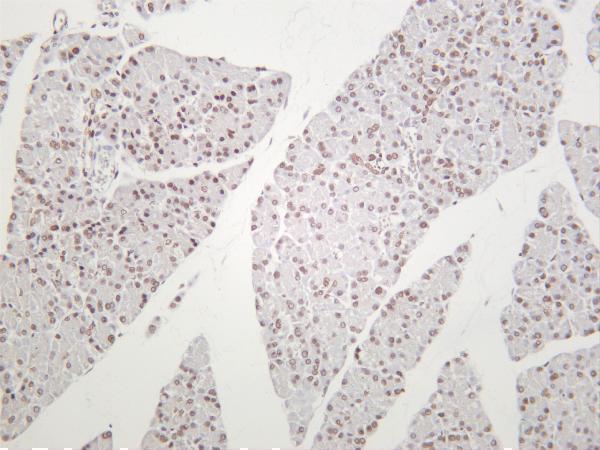
Real IHC data Rat pancreas was stained with anti-HP1α rabbit antibody
Anti-HP1α Rabbit Monoclonal Antibody
Cat # M02780-3

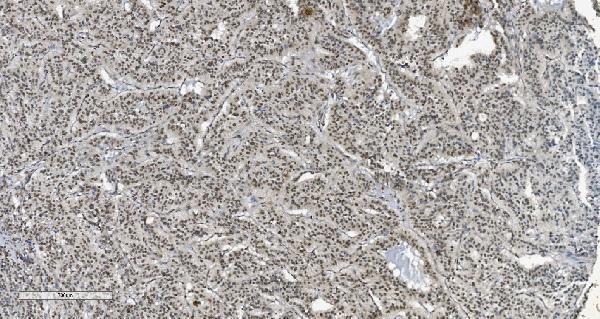
M02780-2 shows IHC in rat brain and human adrenocortical adenoma, ovarian serous adenocarcinoma, and breast cancer; A02780-3 shows IHC in human lung and mammary cancers and mouse intestine (catalog IHC captions). M02780 shows IHC in mouse and rat brain, while M02780-3 shows staining in rat and mouse pancreas and human breast carcinoma (catalog IHC captions).

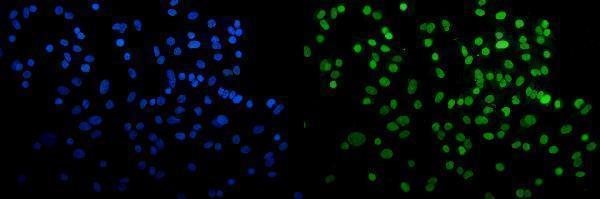
Which to pick: For human tissue IHC, choose A02780-3: its paraffin-section captions document EDTA pH 8.0 retrieval and 1 μg/ml primary antibody (A02780-3 IHC captions). For IF/ICC, choose M02780-2: its applications include both, and its A549 cell IF caption documents 5 μg/ml primary antibody and DAPI counterstaining (M02780-2 catalog applications; M02780-2 IF caption). For tissue IHC across human, mouse, and rat samples, consider M02780-3: its captions show staining in all three species, but do not report the fixative or section processing (M02780-3 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P45973 (CBX5_HUMAN, Chromobox protein homolog 5).
  2. Human Protein Atlas. CBX5 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CBX5 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. CBX5 antibody validation summary (2 antibodies).
  5. Psychological Stress Associated Bile Acid Reprogramming Promotes Hepatocellular Carcinoma Progression. Advanced science (Weinheim, Baden-Wurttemberg, Germany) 2026 — PMC13355934.
  6. Acquired temozolomide resistance in MGMT-deficient glioblastoma cells is associated with regulation of DNA repair by DHC2. Brain : a journal of neurology 2019 — PMC6658867.
  7. Network biology of tumor stem-like cells identified a regulatory role of CBX5 in lung cancer. Scientific reports 2012 — PMC3419921.
  8. Identification of MAEA protein as a potential target for chemoresistance in osteosarcoma using bioinformatics and proteomic analysis. Frontiers in oncology 2025 — PMC12450695.
  9. PubMed PMID:8505380 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.