This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
This guide uses the reported cytoplasmic tissue profile to plan chromogenic CCL17 IHC and select controls (HPA tissue IHC). The catalog antibody is validated for human IHC-P (datasheet: A02036); interpret staining with the uncertainty associated with a secreted protein in mind (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in most tissues and immune cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02036) | |
| Caveat | Secretion can separate tissue staining from RNA location (HPA tissue IHC) | |
| Regulation | Induced in stimulated PBMCs (UniProt) | |
| Isoform / epitope | No isoforms; 24–94 is secreted, with no cytoplasmic tail (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by published CCL17 IHC protocols for renal and lung tissue (PMC5299767; PMC3665443; PMC2741459).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A02036); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CCL17, 1:100–1:500 starting range (standard) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CCL17-positive staining in glandular cells of appendix (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues and in immune cells. No signal in the no-primary control. |
CCL17 is a secreted chemokine with no transmembrane segment (UniProt Q92583). In tissue IHC, HPA reports predominantly cytoplasmic staining across many tissues and immune cells, including medium staining in appendix glandular cells and bone marrow hematopoietic cells (HPA tissue IHC). Treat this as a provisional pattern: HPA rates the tissue result and the listed antibody CAB002583 as Uncertain (HPA tissue IHC; HPA antibodies).
| Cytoplasmic staining in appendix glandular cells or bone marrow hematopoietic cells, around the reported medium level (HPA tissue IHC). | This resembles the observed CCL17 tissue pattern (HPA tissue IHC). Compare the stained cells with tissue architecture and a matched control section (general IHC practice). The match supports interpretation, but does not establish antibody specificity: the tissue result and CAB002583 IHC validation are Uncertain (HPA tissue IHC; HPA antibodies). |
| Strong, sharply nuclear or continuous cell-surface staining dominates, with little cytoplasmic signal. | A dominant nuclear or membrane pattern differs from HPA's cytoplasmic tissue profile (HPA tissue IHC). CCL17 is secreted and lacks a transmembrane segment, so continuous membrane staining is not the expected intrinsic localization (UniProt Q92583). Review controls and detection conditions before assigning this signal to CCL17 (general IHC practice). |
| Prominent staining appears in adipocytes or soft-tissue fibroblasts while expected cell types are weak (HPA tissue IHC). | HPA reports CCL17 as not detected in those cell types, making the result discordant with its tissue observations (HPA tissue IHC). Cross-reactivity or endogenous detection activity are possibilities to check with appropriate controls (general IHC practice). An HPA negative observation is not proof that expression is impossible (HPA tissue IHC: Uncertain). |
| Color spreads broadly across the section without a clear cell-associated pattern. | Diffuse background cannot be scored as the reported cytoplasmic cell staining (HPA tissue IHC). Because CCL17 is secreted, extracellular material may complicate localization, but diffuse color alone cannot identify its source (UniProt Q92583; general IHC practice). Check background controls, blocking, washes and detection conditions (general IHC practice). |
| No signal appears in appendix glandular cells or bone marrow hematopoietic cells (HPA tissue IHC). | Both are reported at medium intensity, so absence warrants a control and workflow review (HPA tissue IHC; general IHC practice). Check whether the section contains the relevant cells and whether detection worked (general IHC practice). These tissues are reference examples, not guaranteed positives, given the Uncertain HPA assessment (HPA tissue IHC). |
| Secretion and compartment (UniProt Q92583; HPA tissue IHC) | CCL17 is secreted and has no transmembrane segment (UniProt Q92583), while HPA describes cytoplasmic tissue staining (HPA tissue IHC). Read cytoplasmic signal as an observed staining pattern, not proof that all CCL17 remains inside the producing cell (UniProt Q92583; HPA tissue IHC). |
| Processing and epitope interpretation (UniProt Q92583) | UniProt annotates a signal peptide at residues 1–23 and a mature chain at 24–94 (UniProt Q92583). The payload gives no antibody epitope, so peptide processing cannot predict whether CAB002583 detects precursor, mature secreted protein, or both (UniProt Q92583; HPA antibodies). |
| Tissue distribution and confidence (UniProt Q92583; HPA tissue IHC) | UniProt reports constitutive thymus expression and stimulated, but not resting, peripheral blood mononuclear cell expression (UniProt Q92583). HPA reports broad cytoplasmic tissue staining yet flags secreted-protein RNA/protein location differences and a transcript discrepancy (HPA tissue IHC). Interpret tissue comparisons with those limitations visible (HPA tissue IHC). |
| IHC antibody evidence (HPA antibodies; HPA tissue IHC) | The only listed antibody, CAB002583, has Uncertain IHC validation; the tissue profile is also Uncertain (HPA antibodies; HPA tissue IHC). A plausible compartment or tissue match alone therefore cannot settle specificity (HPA antibodies; HPA tissue IHC). |
| IF/ICC: what pattern is established? (HPA subcellular) | HPA calls CCL17 secreted but provides no main ICC/IF location or cell-line images (HPA subcellular). There is no image-backed intracellular IF pattern to prescribe here; assess any IF result against controls and the secreted nature of the target (HPA subcellular; UniProt Q92583; general IF practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in an HPA medium-positive tissue example (HPA tissue IHC). | The sampled section may lack the reported cells, or the IHC detection workflow may have failed (general IHC practice). | Confirm cell identity and tissue integrity, then inspect matched positive and detection controls before changing conditions (general IHC practice); HPA's examples remain provisional (HPA tissue IHC: Uncertain). |
| Signal is strong in adipocytes or soft-tissue fibroblasts (HPA tissue IHC). | These cells were not detected in the HPA profile; cross-reactivity or endogenous detection activity may contribute (HPA tissue IHC; general IHC practice). | Compare with a no-primary control and the expected cells in the same run; assess any residual detection signal before scoring CCL17 (general IHC practice). |
| A broad wash of chromogen obscures individual cells. | Background from blocking, washes or detection can obscure the reported cytoplasmic pattern (general IHC practice; HPA tissue IHC). | Inspect the no-primary control and optimize general blocking, wash and detection conditions; score only interpretable cellular staining (general IHC practice). |
| The dominant signal is nuclear or forms a continuous membrane outline. | This differs from HPA's cytoplasmic tissue profile and from CCL17's secreted, non-transmembrane annotation (HPA tissue IHC; UniProt Q92583). | Check control sections and review antibody and detection specificity before assigning that compartment to CCL17 (general IHC practice). |
| Two tissue samples show different intensities. | Expression can vary by tissue and cell state: HPA lists medium and undetected examples, and UniProt distinguishes stimulated from resting blood mononuclear cells (HPA tissue IHC; UniProt Q92583). | Compare the same cell type and scoring criteria across sections; record the tissue context and retain HPA's Uncertain reliability caveat (general IHC practice; HPA tissue IHC). |
| An IF/ICC image appears to show a precise organelle location. | HPA provides no ICC/IF images or main intracellular location for CCL17; it describes the protein as secreted (HPA subcellular). | Treat the organelle assignment as unverified, check IF controls and report only the observed distribution until independent evidence supports a location (HPA subcellular; general IF practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Secreted protein, tissue location of RNA and protein is expected to differ. Caution, Splice and/or transcript discrepancy exists.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Soft tissue | Fibroblasts | Not detected | Protein (IHC) | HPA → |
| Spleen | Cells in red pulp | Not detected | Protein (IHC) | HPA → |
| Vagina | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot CCL17 chromogenic IHC by separating retrieval and staining problems from the interpretation of a secreted chemokine (UniProt Q92583).
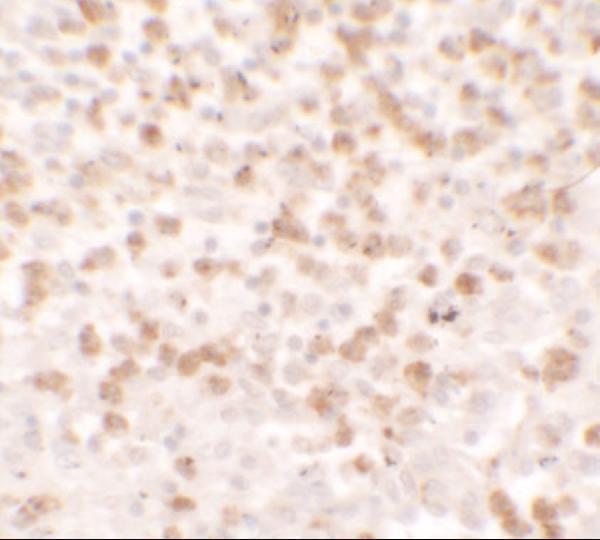
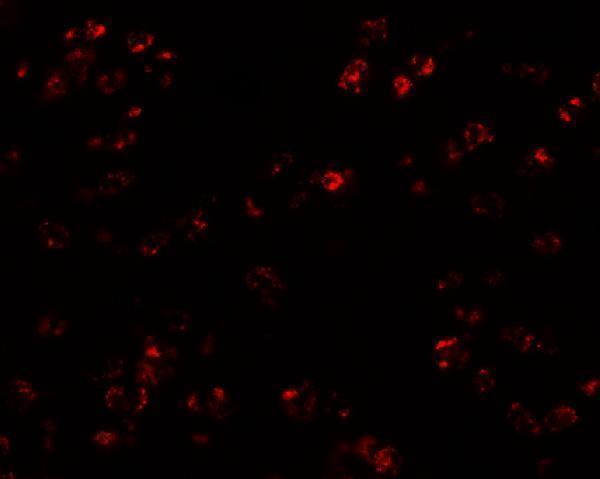
A02036 has human spleen IHC and IF images (catalog image captions); its listed reactivity includes human, mouse, and rat (catalog reactivity).
A02036 has an IHC image of human spleen at 5 μg/ml (catalog IHC caption). A02036 also has an IF image of human spleen at 20 μg/ml (catalog IF caption).
Which to pick: For tissue IHC, choose A02036: IHC-P is listed (catalog applications), and its IHC image shows human spleen at 5 μg/ml (catalog IHC caption); the caption does not report the fixative (catalog IHC caption). For IF, choose A02036 based on its human spleen image (catalog IF caption); ICC validation is unreported (catalog applications). For mouse or rat work, A02036 lists both species (catalog reactivity), but the supplied IHC and IF images show human tissue only (catalog image captions); it is rabbit hosted, with clonality unreported (catalog payload).