CDC123 / Translation initiation factor eIF2 assembly protein · IHC design guide

Design Immunohistochemistry for CDC123

Plan CDC123 IHC-P around cytoplasmic staining, with alveolar or pancreatic exocrine cells as positive controls (HPA tissue IHC). Titrate the catalog antibody within 2–5 μg/mL (datasheet A08251-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CDC123 (IHC for CDC123): expected localisation General cytoplasmic staining (HPA tissue IHC), antibody A08251-2, validated IHC image, and IHC protocol steps
Printable CDC123 IHC protocol sheet — expected localisation General cytoplasmic staining (HPA tissue IHC), antibody A08251-2, controls and protocol steps. Open the full CDC123 IHC guide →

CDC123 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in alveolar and exocrine glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08251-2)
Positive control ⓘ Lung+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
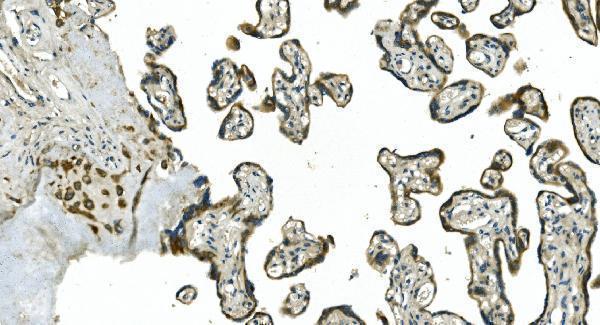
Caveat Placenta staining may differ from HPA-negative trophoblasts (datasheet A08251-2 IHC; HPA tissue IHC)
Regulation No specific expression regulator reported (UniProt)
Isoform / epitope No isoforms or processing annotated; epitope position unknown (UniProt)
Section 1

Recommended CDC123 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A08251-2) with a published human fetal lung IHC protocol (PMC4966770).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human ovarian cancer tissue; fixative not specified (datasheet A08251-2)
FixationImage fixative and duration unreported (datasheet A08251-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08251-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08251-2)
Primary antibodyRabbit anti-CDC123, 2-5μg/ml (datasheet A08251-2)
Primary incubationOvernight at 4 °C (datasheet A08251-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A08251-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCDC123-positive staining in alveolar cells of lung (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A08251-2); the published protocol used steamer citrate pH 6.0 (PMC4966770).
Section 2

What Is the Expected CDC123 Staining Pattern?

CDC123 is cytoplasmic in the UniProt record and has no transmembrane segment (UniProt O75794: subcellular location and topology). In tissue IHC, expect general cytoplasmic staining, with High staining reported in lung alveolar cells and pancreatic exocrine glandular cells (HPA: tissue IHC). HPA rates the tissue staining Approved, with medium consistency between staining and RNA expression; interpret individual slides in that context (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining in lung alveolar cells or pancreatic exocrine glandular cells.This matches the reported High staining in those cell types (HPA: tissue IHC). Compare signal within the identified cells, since adjacent cell types need not share their staining level (standard IHC interpretation).
Predominantly nuclear or Golgi-like staining with little cytoplasmic signal in a tissue section.This diverges from the general tissue IHC profile (HPA: general cytoplasmic expression). Review morphology, counterstain and controls before calling it an artefact: nucleoplasm and Golgi are approved ICC-IF locations (HPA: subcellular ICC-IF).
Strong staining in adipocytes, smooth muscle cells or ovarian stromal cells.Those specific cells are listed as Not detected in tissue IHC (HPA: tissue IHC). Check cell identification and a no-primary control; cross-reactivity or endogenous detection activity may explain unexpected chromogen (standard IHC practice).
Diffuse chromogen across cells and tissue spaces, obscuring cell boundaries.This cannot establish CDC123 localisation. Review the no-primary control, blocking, primary antibody concentration and detection development (standard IHC practice); retain the HPA cytoplasmic pattern as the comparison (HPA: tissue IHC).
No staining in lung alveolar cells or pancreatic exocrine glandular cells.An absent signal conflicts with their reported High staining (HPA: tissue IHC). Verify that the relevant cells are present, then assess the catalog antibody and IHC detection workflow with appropriate controls (standard IHC practice).
💡Expected CDC123 appearanceCall positive tissue IHC when High cytoplasmic signal identifies lung alveolar or pancreatic exocrine glandular cells (HPA: tissue IHC); diffuse background or strong signal in HPA Not detected cell types warrants investigation before scoring.
How each factor affects the staining
Tissue and cell choiceHPA reports High staining in lung alveolar and pancreatic exocrine glandular cells, but Not detected in adipocytes and smooth muscle cells (HPA: tissue IHC). Assess the named cells rather than assigning one expected level to an entire section.
Antibody validationBoth listed antibodies are Approved for IHC; HPA037830 is also Approved for ICC (HPA: antibodies). The supplied record does not assign either an Enhanced IHC rating, so approval alone does not establish independent reproduction of every observed pattern.
Cellular compartmentThe tissue profile is generally cytoplasmic (HPA: tissue IHC; UniProt O75794: cytoplasm). ICC-IF additionally places CDC123 in nucleoplasm and Golgi, with cytosol as an additional location (HPA: subcellular ICC-IF). Interpret each application against its own evidence.
Processing and topologyUniProt lists one chain spanning residues 1–336, no signal peptide or propeptide, and no transmembrane segment (UniProt O75794: processing and topology). These annotations support an intracellular expectation; they do not predict staining strength or retrieval conditions.
Antigen retrieval in IHC-PUse the catalog antibody's IHC-P procedure as the starting point for retrieval and dilution (standard IHC practice). Neither supplied source establishes a CDC123-specific retrieval requirement or fixation sensitivity, so compare trial conditions using tissue and reagent controls.
IF/ICC Q&A: what pattern should I expect?Expect approved nucleoplasm and Golgi localisation, with additional cytosol signal (HPA: subcellular ICC-IF). That observation comes from ICC-IF images in A-431, U-251MG and U2OS (HPA: subcellular ICC-IF); it does not replace the tissue IHC profile.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive cells are unstained.The slide conflicts with High staining reported for lung alveolar or pancreatic exocrine cells (HPA: tissue IHC); the immediate cause is undetermined.Confirm cell identity and tissue preservation, then check catalog antibody dilution, retrieval and detection with positive and no-primary controls (standard IHC practice).
All compartments show a uniform haze.Nonspecific binding or excessive detection development can obscure localisation (standard IHC practice).Inspect the no-primary control; adjust blocking, primary concentration, washing or development as indicated by the control (standard IHC practice).
Strong signal appears in HPA Not detected cell types.Misidentified cells, cross-reactivity or endogenous enzyme activity are possibilities (HPA: tissue IHC; standard IHC practice).Recheck morphology and compare with a no-primary control; if using enzyme detection, assess endogenous activity before scoring the signal (standard IHC practice).
Nuclear staining dominates tissue IHC.It differs from the general cytoplasmic tissue profile, although nucleoplasm is an approved ICC-IF location (HPA: tissue IHC; HPA: subcellular ICC-IF).Review counterstain, cell boundaries and reagent controls; describe the observed compartment separately from the expected tissue IHC pattern (standard IHC interpretation).
A negative ovarian stromal result seems inconsistent with UniProt expression.UniProt reports expression in ovary without specifying stromal cells, whereas HPA lists ovarian stromal cells as Not detected by IHC (UniProt O75794: tissue specificity; HPA: tissue IHC).Score the identified stromal cells against the cell-specific HPA observation; do not treat organ-level expression as proof that each ovarian cell type must stain.
Signal varies between sections or runs.Cell composition or workflow variation can change the observed field (standard IHC practice); HPA reports medium consistency between staining and RNA data (HPA: tissue IHC reliability).Compare the same identified cell types across sections, record retrieval and detection conditions, and interpret weak differences alongside controls (standard IHC practice).

Sample controls for CDC123 IHC & IF

🧪Run pancreas first: exocrine glandular cells should stain (HPA: High in pancreatic exocrine glandular cells). Use adipose tissue as the negative tissue: adipocytes are listed as not detected (HPA: Not detected in adipocytes); on the pancreas slide, compare stained exocrine cells with any cells that remain unstained, without treating a particular pancreatic cell type as a validated internal negative.
Positive control tissue: Lung (Alveolar cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CDC123 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (approved), Golgi apparatus (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a concentration-matched rabbit IgG isotype control, and CDC123-knockout material or a validated peptide-block control (selected-SKU caption: rabbit primary; standard IHC practice). For pancreatic chromogenic IHC, quench endogenous peroxidase and check for endogenous biotin when using the caption’s streptavidin–biotin detection system (selected-SKU caption: SABC with DAB; standard IHC practice).
⚠️Feasibility: The selected-SKU paraffin-section caption reports heat retrieval in EDTA at pH 8.0, but leaves the fixative unreported; no target-specific fixation window or fixation effect is supplied (selected-SKU tissue-IHC caption). That caption supports a retrieved paraffin-section starting point, while the evidence does not establish whether frozen sections or IF are easier (selected-SKU tissue-IHC caption; HPA: ICC-IF images). In pancreas, endogenous biotin can complicate the reported streptavidin–biotin method, so assess background with the controls above (selected-SKU caption: SABC detection; standard IHC practice).

HPA tissue IHC evidence for CDC123

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Alveolar cells High Protein (IHC) HPA →
Pancreas Exocrine glandular cells High Protein (IHC) HPA →
Skin Keratinocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Placenta Trophoblastic cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced CDC123 IHC Tips

Troubleshoot CDC123 chromogenic IHC in paraffin sections using the selected antibody image, protein annotations, and tissue staining patterns.

Which antigen retrieval should I use when CDC123 staining is weak in paraffin sections?
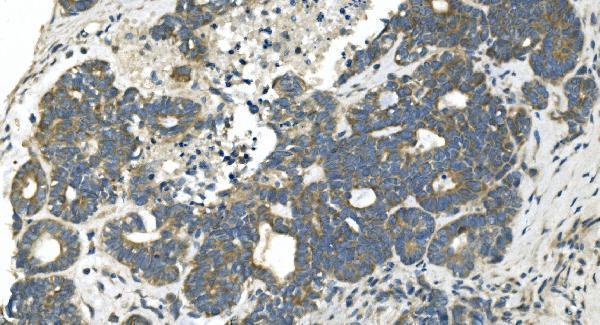
Use heat-mediated antigen retrieval in EDTA at pH 8.0 for CDC123 paraffin-section IHC (datasheet A08251-2). The selected ovarian cancer image used that retrieval before incubation with 2 μg/mL catalog antibody overnight at 4°C (datasheet A08251-2). If staining remains weak, compare retrieval duration across matched sections while keeping antibody concentration, detection, and development time constant (standard IHC practice). Include a positive control with an expected staining pattern, such as lung alveolar cells, alongside each condition (HPA tissue IHC: High in lung alveolar cells). Judge improvement by cleaner cellular staining as well as signal intensity, since excessive heating can damage tissue morphology (standard IHC practice).
Could fixation explain weak or uneven CDC123 staining?
The selected paraffin-section caption does not report a fixative, so target-specific CDC123 fixation sensitivity is unknown (datasheet A08251-2). Record the fixative, fixation duration, section thickness, and storage conditions for each specimen before comparing staining runs (standard IHC practice). If fixation histories differ, test matched sections with the same pH 8.0 EDTA retrieval and 2 μg/mL antibody condition used in the selected image (datasheet A08251-2). Assess tissue preservation and the distribution of signal within cells, rather than treating any intensity difference as proof of a CDC123-specific fixation effect (standard IHC practice). Use an expected positive tissue in each run to help identify processing or detection failures (HPA tissue IHC: High in pancreas exocrine glandular cells).
How should I assess CDC123 staining outside the cytoplasm?
For paraffin-section IHC, begin by assessing cytoplasmic staining, because the tissue profile reports general cytoplasmic expression (HPA tissue IHC). Interpret nuclear or perinuclear staining cautiously: the subcellular IF record reports approved nucleoplasmic and Golgi locations, with additional cytosolic localisation (HPA subcellular). CDC123 also lacks an annotated transmembrane segment, so a crisp plasma-membrane-only rim is unexpected from its protein annotation (UniProt O75794 topology). Compare each compartment with adjacent cells and a positive control processed in the same run (standard IHC practice). If an unusual compartment persists, confirm it with a separate validated antibody or orthogonal assay before assigning biological meaning (standard IHC practice).
Could isoforms or epitope accessibility explain variable CDC123 staining?
UniProt lists 0 annotated CDC123 isoforms and a single 1–336 chain, so annotated splice isoforms do not explain staining differences (UniProt O75794 isoforms and processing). The record notes phosphoserine at residue 60, but its effect on binding cannot be inferred without the catalog antibody’s epitope (UniProt O75794 modified residues; datasheet A08251-2: epitope not stated). CDC123 interacts with EIF2S3 through its C-terminus, which makes epitope position relevant if that region is recognized (UniProt O75794 subunit). Compare the same specimens under matched retrieval and detection conditions before attributing a difference to masking (standard IHC practice). If available, confirm discordant patterns with an antibody recognizing a documented, distinct epitope (standard IHC practice).
How can IF help assess a disputed CDC123 IHC pattern?
Use IF as a separate localisation check, pairing CDC123 with a marker for the cell type implicated by the IHC result (standard IF practice). For example, lung alveolar cells and pancreas exocrine glandular cells have high tissue IHC staining, so choose a cell-type marker appropriate to the specimen under study (HPA tissue IHC). Select spectrally separated fluorophores and inspect an unstained section to distinguish signal from tissue autofluorescence (standard IF practice). Permeabilise for access to intracellular epitopes: CDC123 has no transmembrane segment, while IF annotations include nucleoplasm, Golgi apparatus, and cytosol (UniProt O75794 topology; HPA subcellular). Keep antibody and single-channel controls when judging colocalisation, especially near bright tissue structures (standard IF practice).
What should I check when CDC123 DAB staining is diffuse?
The selected image used 10% goat serum blocking, a biotinylated goat anti-rabbit secondary, a streptavidin–biotin complex, and DAB (datasheet A08251-2). In a repeat run, include a no-primary control and review endogenous peroxidase blocking, washes, and DAB development time to locate procedural background (standard IHC practice). Because the documented detection system uses biotin, assess endogenous biotin as a possible source when control sections stain (datasheet A08251-2; standard IHC practice). Compare suspected background with cellular cytoplasmic staining expected in tissue IHC, rather than calling every diffuse deposit CDC123-positive (HPA tissue IHC: general cytoplasmic expression). Keep illumination and image settings consistent across controls and test sections (standard IHC practice).
How should I quantify CDC123 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since tissue IHC reports general cytoplasmic expression while subcellular IF also reports nucleoplasmic and Golgi localisation (HPA tissue IHC; HPA subcellular). For a cellular readout, report the percentage of positive cells and an H-score based on the proportions at intensity grades 0–3 (standard IHC practice). For spatial questions, report positive-cell density per mm² of viable tissue, excluding folds and necrosis (standard IHC practice). Normalise counts to the same eligible cell population or viable tissue area across specimens, and use identical thresholds and DAB development conditions (standard IHC practice). Report compartment scores separately rather than merging nuclear and cytoplasmic signals (standard IHC practice).
When is an unexpected CDC123-positive area likely to be artefact?
CDC123 tissue IHC shows general cytoplasmic expression, and the protein lacks an annotated transmembrane segment; an isolated sharp membrane rim therefore warrants verification (HPA tissue IHC; UniProt O75794 topology). Check whether staining follows viable cells and their expected compartments rather than section edges, folds, or necrotic debris (standard IHC practice). Compare the suspect area with a no-primary control to assess nonspecific detection or endogenous enzyme activity (standard IHC practice). Cell identity matters: ovarian stroma cells were not detected in the HPA profile, whereas the selected catalog image shows staining in human ovarian cancer tissue (HPA tissue IHC; datasheet A08251-2). Reproduce an unexpected pattern in separately processed sections before interpreting it biologically (standard IHC practice).
Boster reagents

Best CDC123 / Translation initiation factor eIF2 assembly protein IHC Antibodies

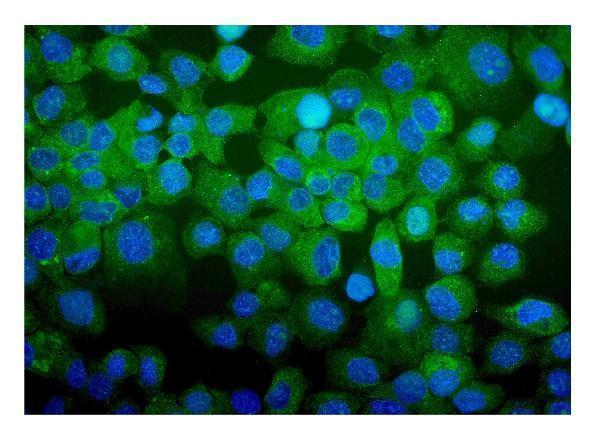
A08251-2 has documented CDC123 IHC in human paraffin tissue sections and IF/ICC in A431 cells (catalog: IHC/IF image captions).

Real IHC data IHC analysis of CDC123 using anti-CDC123 antibody (A08251-2). CDC123 was detected in paraffin-embedded section of human ovarian cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-CDC123 Antibody (A08251-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-CDC123 Antibody ®
Cat # A08251-2

A08251-2 is listed for human IHC, with images from paraffin sections of ovarian cancer, placenta, appendicitis, and bladder cancer tissue (catalog: applications, reactivity, IHC image captions). The same SKU has an IF image from A431 cells (catalog: IF image caption).

Which to pick: Choose A08251-2 for human paraffin-section IHC; its IHC caption documents EDTA retrieval at pH 8.0 and 2 μg/mL antibody, but does not report the tissue fixative (catalog: IHC image caption). For IF/ICC, A08251-2 has an A431 cell image using 5 μg/mL antibody (catalog: IF image caption). No cross-species option is documented, and clonality is unspecified (catalog: Human reactivity; clone field unreported).

Each figure is that product's own IHC / IF validation image from its datasheet.