This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Use cerebellar synaptic glomeruli as a high-staining reference and cortical neurons as a medium-staining comparison for CDH7 IHC (HPA tissue IHC). Score neuronal cytoplasm and processes (HPA tissue IHC), consider the membrane annotation separately (UniProt), and include specificity controls because presumed off-target binding was observed (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Neuronal cytoplasm and processes (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in CNS neurons and processes (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Cerebellum+2 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target binding can complicate scoring (HPA tissue IHC) | |
| Regulation | Regulation not annotated (UniProt) | |
| Isoform / epitope | No isoforms annotated; check extracellular vs cytoplasmic epitope (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet) is accompanied by one published cerebral cortex IHC protocol (PMC13343476).
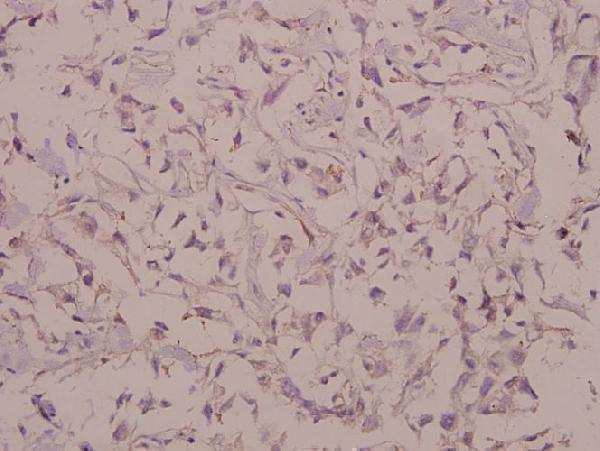
| Sample | Paraffin-embedded human colorectal carcinoma tissue; fixative not specified (datasheet A10388-1) |
| Fixation | Image fixative and duration unreported (datasheet A10388-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CDH7, 1:50-1:200 (datasheet A10388-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CDH7-positive staining in synaptic glomeruli - core of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in neuronal cells and processes in CNS. No signal in the no-primary control. |
CDH7 is a cell-membrane protein with an extracellular region at residues 28–607 and a cytoplasmic region at 629–785 (UniProt Q9ULB5 topology). In tissue IHC, expect staining in CNS neuronal cells and processes, strongest in cerebellar synaptic glomeruli cores (HPA: tissue IHC). HPA rates the tissue pattern Supported, reports medium agreement with RNA data, and notes that presumed off-target staining was disregarded (HPA: reliability).
| Strong staining in cerebellar synaptic glomeruli cores, with neuronal and process-associated staining in CNS sections. | This matches the highest reported tissue signal and the described CNS pattern (HPA: High in cerebellar synaptic glomeruli cores; cytoplasmic expression in neuronal cells and processes). Score the stained structures, since a tissue-level positive call alone can hide which cells carry the signal. |
| Cerebral cortical neuronal cells stain moderately; hippocampal neuronal cells stain weakly. | The difference is consistent with the reported levels (HPA: Medium in cerebral cortical neuronal cells; Low in hippocampal neuronal cells). Compare each region with its own expected cell pattern; a weak hippocampal result should not be judged against the cerebellar core intensity. |
| The dominant signal is nuclear or confined to an unexpected compartment, without the expected neuronal or process pattern. | Treat this as a possible staining artefact or nonspecific signal: CDH7 is assigned to the cell membrane (UniProt Q9ULB5 topology), while HPA describes cytoplasmic staining in CNS neuronal cells and processes (HPA: tissue IHC). Recheck the cell pattern before scoring it as CDH7. |
| Strong staining appears in cells reported as unstained, such as adipocytes or adrenal glandular cells. | This raises possible cross-reactivity or endogenous chromogenic detection activity (HPA: Not detected in adipocytes and adrenal glandular cells; standard IHC practice). HPA reports presumed off-target binding in its tissue assessment (HPA: reliability); the unexpected signal alone cannot identify its cause. |
| No staining appears in the cerebellar synaptic glomeruli cores of an otherwise interpretable section. | A missing signal in this reported high-expression structure makes the run inconclusive for a negative CDH7 call (HPA: High in cerebellar synaptic glomeruli cores). Check the antibody and detection workflow with a known-positive section before interpreting weaker tissues. |
| Cell location and slide appearance | CDH7 has one transmembrane segment at 608–628 (UniProt Q9ULB5 topology). HPA nevertheless describes cytoplasmic staining in CNS neuronal cells and processes (HPA: tissue IHC). Interpret the observed neuronal pattern alongside the membrane assignment; the two sources do not establish a required sharp membrane outline in paraffin sections. |
| Tissue and cell choice | Cerebellar synaptic glomeruli cores provide a reported high-signal reference; cerebral cortical neuronal cells and late spermatids are reported at medium levels (HPA: tissue IHC). Adipocytes and adrenal glandular cells are reported as not detected (HPA: tissue IHC). Use the named cells when assessing controls. |
| Confidence in an unexpected signal | The tissue pattern is Supported, with medium agreement between staining and RNA expression, and presumed off-target binding was disregarded (HPA: reliability). An unexpected positive needs review against cell identity and controls; Supported does not establish that every stained structure is specific. |
| Processing and epitope position | UniProt lists a signal peptide at 1–27, a propeptide at 28–47, and a mature chain at 48–785 (UniProt Q9ULB5 processing). These boundaries matter when an antibody's epitope is known. No epitope position is supplied here, so they cannot predict this antibody's staining outcome. |
| IF/ICC Q&A: should IF show the same pattern? | A membrane-associated signal is compatible with the HPA subcellular summary (HPA: Membrane; UniProt Q9ULB5 topology). HPA supplies no ICC-IF cell images or main-location assignment, and lists no ICC validation for HPA061419 (HPA: subcellular and antibody records). Use the separate IF/ICC guide for that application. |
| Situation | Likely cause | Next action |
|---|---|---|
| The cerebellar positive control shows no signal. | The expected high-signal structure is absent from the readout (HPA: High in cerebellar synaptic glomeruli cores); the source record does not identify a CDH7-specific technical cause. | Confirm that the synaptic glomeruli cores are present, then check antibody, retrieval and detection steps against the IHC-validated antibody's instructions (standard IHC practice). Repeat with a known-positive section before calling study sections negative. |
| Signal is uniformly weak across expected positive structures. | The expected levels differ by structure (HPA: High in cerebellar cores; Medium in cortical neurons; Low in hippocampal neurons). Uniform weakness may reflect a run-level issue, but these records do not assign it to fixation or retrieval. | Review section quality and the antibody's documented IHC conditions; adjust retrieval or antibody concentration only within a controlled optimisation series (standard IHC practice). Judge improvement first in the reported high-signal structure. |
| Adipocytes or adrenal glandular cells stain strongly. | Those cells are reported as not detected (HPA: tissue IHC). Nonspecific antibody binding or endogenous detection activity are possible explanations (standard IHC practice), and HPA notes disregarded presumed off-target staining (HPA: reliability). | Compare a no-primary control and the known-positive neuronal pattern; check the appropriate endogenous-activity block for the chromogenic detection system (standard IHC practice). Do not score the unexpected cells as CDH7 solely from color. |
| Brown precipitate spreads across tissue or outside recognizable cells. | A diffuse deposit does not match the reported neuronal and process-associated distribution (HPA: tissue IHC). Excess chromogen development, inadequate washing or background from detection reagents are general IHC possibilities (standard IHC practice). | Inspect the no-primary control, washes and chromogen development time, then repeat with the documented detection workflow (standard IHC practice). Assess localization only after tissue-wide background is reduced. |
| Nuclear staining dominates while neuronal processes lack signal. | A nuclear-dominant pattern conflicts with the membrane topology and observed CNS pattern (UniProt Q9ULB5 topology; HPA: tissue IHC). This supports suspicion of an artefact, without identifying its precise source. | Check the no-primary control and review the counterstain and detection signal separately (standard IHC practice). Reassess only if the expected neuronal or process pattern becomes distinguishable. |
| IF/ICC gives a pattern that seems unlike the IHC result. | The HPA subcellular summary says Membrane, but provides no ICC-IF images or main-location assignment; HPA061419 has no listed ICC validation (HPA: subcellular and antibody records). The tissue IHC observations alone cannot validate an IF pattern. | Evaluate IF/ICC with its own controls and application-specific guidance (standard IF practice). Keep the paraffin IHC interpretation anchored to the reported tissue cells and staining levels (HPA: tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebellum | Synaptic glomeruli - core | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Testis | Elongated or late spermatids | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot CDH7 staining in paraffin sections by checking retrieval, compartment, tissue context, and controls before scoring chromogenic signal.
CDH7 IHC has a paraffin-section image from human colorectal carcinoma (A10388-1 image caption); both antibodies list Human, Mouse and Rat reactivity (catalog), while A10388 lists IF without an image (catalog).
A10388-1 is the card that will render: its IHC image shows paraffin-embedded human colorectal carcinoma at 1:50 (A10388-1 image caption). It lists IHC and Human, Mouse and Rat reactivity (A10388-1 catalog); the caption does not report the fixative (A10388-1 image caption).
Which to pick: Choose A10388-1 for tissue IHC when a matching paraffin-section image is useful; its caption identifies a polyclonal antibody and human colorectal carcinoma, but does not report the fixative (A10388-1 image caption). For IF/ICC planning, A10388 lists IF at 1:200–1:1000, though no IF image is supplied (A10388 catalog). Both list Human, Mouse and Rat reactivity for cross-species work; A10388-1 lists IHC at 1:50–1:200, while A10388 lists IHC at 1:100–1:300 (catalog).