CDKN1C / Cyclin-dependent kinase inhibitor 1C · IHC design guide

Design Immunohistochemistry for CDKN1C

Plan CDKN1C paraffin-section IHC around nuclear tissue staining (HPA tissue IHC). Use glomerular, pancreatic endocrine or decidual cells as positive controls (HPA tissue IHC), and compare nuclear signal with a negative control (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CDKN1C (IHC for CDKN1C): expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody A01244-2, validated IHC image, and IHC protocol steps
Printable CDKN1C IHC protocol sheet — expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody A01244-2, controls and protocol steps. Open the full CDKN1C IHC guide →

CDKN1C Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in several tissues (HPA tissue IHC)
Staining pattern Nuclear staining in glomerular, endocrine and decidual cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01244-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Lung alveolar cells have no detectable staining (HPA tissue IHC)
Regulation Expression varies by cell type (HPA tissue IHC)
Isoform / epitope 2 isoforms, Long and Short; epitope coverage unknown (UniProt)
Section 1

Recommended CDKN1C IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol (datasheet: EDTA pH 8.0 retrieval). Two published CDKN1C IHC protocols provide additional conditions for breast cancer and mouse fetal sections (PMC2323395; PMC4786089).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human esophageal squamous carcinoma tissue; fixative not specified (datasheet A01244-2)
FixationImage fixative and duration unreported (datasheet A01244-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01244-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01244-2)
Primary antibodyRabbit anti-CDKN1C, 2 μg/ml (datasheet A01244-2)
Primary incubationOvernight at 4 °C (datasheet A01244-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01244-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCDKN1C-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in several tissues. No signal in the no-primary control.
💡Decision noteTry EDTA pH 8.0 first with the catalog antibody (datasheet: EDTA pH 8.0 HIER). The published citrate retrieval conditions used different primary antibodies (PMC2323395; PMC4786089).
Section 2

What Is the Expected CDKN1C Staining Pattern?

CDKN1C is a nuclear, non-membrane protein (UniProt P49918: nucleus; no transmembrane segment). In paraffin-section IHC, expect nuclear staining in selected cells, including glomerular cells, pancreatic endocrine cells, placental decidual cells and adrenal glandular cells (HPA: High in each). HPA describes nuclear expression across several tissues, with Enhanced IHC reliability and medium consistency between antibody staining and RNA expression (HPA: tissue IHC).

What am I looking at on my slide?
Distinct nuclear stain in glomerular cells, pancreatic endocrine cells, decidual cells or adrenal glandular cells.This matches HPA’s High staining in those cell populations and its overall nuclear IHC profile (HPA: tissue IHC). Score the identified cells and their nuclei; a whole-section average can hide the expected cell-specific pattern (general IHC practice).
Predominantly cytoplasmic or membrane-like stain, with little convincing nuclear signal.That conflicts with the expected nuclear IHC pattern and the absence of a transmembrane segment (HPA: tissue IHC; UniProt P49918 topology). Review morphology and staining controls before interpreting it as CDKN1C. HPA reports additional cytosol localization in ICC-IF, which does not establish a cytoplasmic IHC pattern (HPA: subcellular).
Strong signal in adipocytes, lung alveolar cells or lymph-node germinal center cells.HPA reports CDKN1C as Not detected in those particular cell populations (HPA: tissue IHC). Check cell identification, antibody-dependent cross-reactivity and endogenous detection activity (general IHC practice). A positive signal in another cell population from the same tissue is a separate observation.
Diffuse stain across nuclei, cytoplasm and tissue spaces, without clear cell boundaries.A diffuse field does not reproduce the reported cell-selective nuclear pattern (HPA: tissue IHC). Possible general IHC causes include excess antibody or detection reagent, inadequate washing and endogenous chromogen-generating activity; compare no-primary and detection controls before assigning target expression (general IHC practice).
No nuclear stain in an otherwise interpretable section of kidney glomeruli or pancreatic endocrine tissue.HPA reports High staining in those specified cells (HPA: tissue IHC), so first confirm that the relevant cells are present. If they are, review the IHC-validated antibody and run controls through the same staining workflow; an unstained slide alone cannot distinguish absent antigen from assay failure (general IHC practice).
💡Expected CDKN1C appearanceCall a convincing positive result cell-selective nuclear chromogen in HPA High populations such as glomerular or pancreatic endocrine cells; diffuse tissue-wide color or staining confined to an unexpected compartment is suspect (HPA: tissue IHC; UniProt P49918: nucleus).
How each factor affects the staining
Cell population and tissue choice (HPA: tissue IHC).High staining is reported in adrenal glandular, glomerular, pancreatic endocrine and decidual cells; Medium staining is reported in selected marrow, brain and duodenal cells (HPA: tissue IHC). Assess the named population within a section rather than treating every cell in a positive tissue as positive (general IHC practice).
IHC evidence strength (HPA: tissue IHC; HPA: antibody HPA002924).The tissue profile reports Enhanced reliability but only medium consistency with RNA expression; the listed rabbit polyclonal antibody has Enhanced IHC validation (HPA: tissue IHC; HPA: antibody HPA002924). Treat unexpected results as requiring controls and cell-level review, rather than assuming either the slide or the reference is definitive.
Isoforms and processing (UniProt P49918).UniProt lists 2 isoforms, Long and Short, and a chain spanning residues 1–316, with no signal peptide or propeptide (UniProt P49918). These facts do not identify an antibody epitope or establish an isoform-specific IHC pattern; do not assign staining differences to an isoform without additional evidence.
IF/ICC: Where should CDKN1C appear? (HPA: subcellular).Mainly in nucleoplasm and nuclear bodies, with additional cytosol localization reported in ICC-IF images from HeLa, SiHa and U2OS cells (HPA: subcellular). This answers the localization question for IF/ICC; the paraffin-section IHC interpretation here follows the tissue IHC nuclear profile (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A proposed positive-control section appears entirely negative.The expected cell population may be absent from the sampled area, or the staining run may have failed (HPA: tissue IHC; general IHC practice).Confirm glomerular, pancreatic endocrine, decidual or adrenal glandular cells in the section, then compare a same-run positive control and detection controls (HPA: High in those cells; general IHC practice).
Only weak staining is visible in a chosen tissue.The sampled cells may normally show Medium or Low staining rather than High staining (HPA: tissue IHC). Tissue-level RNA enrichment does not guarantee strong IHC signal in each cell (HPA: tissue IHC).Identify and score the relevant cell type; compare with a reported High population processed in the same run before adjusting the general IHC workflow (HPA: tissue IHC; general IHC practice).
Brown color persists where the primary antibody was omitted.The signal can arise from the detection system or endogenous tissue activity rather than primary-antibody binding (general chromogenic IHC practice).Check the no-primary control and the detection system’s blocking steps; interpret CDKN1C only where nuclear signal exceeds that control (general chromogenic IHC practice; UniProt P49918: nucleus).
Unexpected cytoplasmic or membrane-like staining dominates.The pattern disagrees with nuclear tissue IHC localization; membrane localization is unsupported by the UniProt topology record (HPA: tissue IHC; UniProt P49918 topology).Verify cell morphology and compare controls and an HPA High nuclear population. Do not transfer the additional cytosol observation from ICC-IF directly to paraffin IHC (HPA: subcellular; HPA: tissue IHC).
Signal appears strong in an HPA Not detected cell population.Possible explanations include cell misidentification, cross-reactivity or endogenous detection activity; the HPA entry applies to the named cells, not automatically to the entire organ (HPA: tissue IHC; general IHC practice).Recheck the stained cell type against the corresponding HPA tissue entry and inspect no-primary and positive controls before calling the finding CDKN1C expression (HPA: tissue IHC; general IHC practice).
A run gives widespread haze that obscures nuclear scoring.Excess staining reagent or insufficient washing can raise background in chromogenic IHC (general IHC practice).Compare no-primary controls, review reagent concentration and wash steps, and repeat with a controlled adjustment if needed; judge success by restored cell-selective nuclear staining (general IHC practice; HPA: tissue IHC).

Sample controls for CDKN1C IHC & IF

🧪Run adrenal gland first and score its glandular cells, which are High for CDKN1C (HPA: High in adrenal gland glandular cells). Run adipose tissue as the biological negative because adipocytes are Not detected (HPA: Not detected in adipocytes); on the adrenal slide, nonglandular cells should be assessed for background staining rather than assumed to be CDKN1C-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
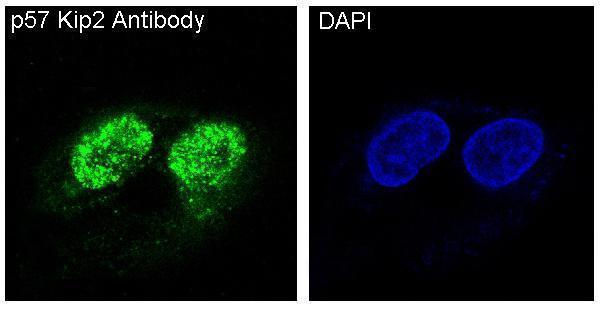
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CDKN1C in HeLa, SiHa, U2OS, with annotated localisation: Nucleoplasm (approved), Nuclear bodies (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a rabbit IgG isotype control matched to the catalog antibody’s clonality if known (caption: rabbit primary antibody). Use CDKN1C-knockout material as a target-specific negative where available; quench endogenous peroxidase and check endogenous biotin when using the caption’s biotin–SABC/DAB detection (caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected A01244-2 paraffin-section caption does not state the fixative. The caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required (caption: EDTA heat retrieval); whether frozen sections or IF are easier is unreported, although HPA documents ICC-IF images in HeLa, SiHa and U2OS with mainly nucleoplasmic and nuclear-body localisation (HPA: subcellular). For adrenal gland, assess peroxidase and biotin background under the selected detection method; no adrenal-specific artefact is reported in the supplied evidence (caption: biotin–SABC/DAB detection).

HPA tissue IHC evidence for CDKN1C

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Kidney Cells in glomeruli High Protein (IHC) HPA →
Pancreas Pancreatic endocrine cells High Protein (IHC) HPA →
Placenta Decidual cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Endometrium Cells in endometrial stroma Not detected Protein (IHC) HPA →
Section 3

Advanced CDKN1C IHC Tips

Troubleshoot CDKN1C staining in paraffin sections by checking retrieval, nuclear localisation, cell type and detection controls before comparing signal across samples.

What retrieval should I try when nuclear CDKN1C staining is weak?
Start with heat-mediated EDTA pH 8.0 antigen retrieval for paraffin-section chromogenic IHC (datasheet A01244-2). The selected antibody image used that retrieval method before overnight incubation at 4°C with 2 μg/ml primary antibody (datasheet A01244-2). When comparing weak sections, hold retrieval conditions constant and include a tissue and cell population with documented nuclear CDKN1C staining, such as pancreatic endocrine cells (HPA: High in pancreatic endocrine cells; standard IHC practice). If staining remains weak, adjust heating duration in a small series while checking morphology and background, because excessive retrieval can damage sections (standard IHC practice).
Can I attribute weak CDKN1C staining to the fixation method?
The selected paraffin-section image does not report its fixative, so target-specific fixation sensitivity cannot be determined from it (datasheet A01244-2: fixative not stated). Record the fixative, fixation duration, processing history and section age for each specimen before comparing staining results (standard IHC practice). Compare affected sections with similarly processed controls using the documented EDTA pH 8.0 retrieval and 2 μg/ml primary concentration (datasheet A01244-2; standard IHC practice). If staining varies with processing history, test matched specimens where available; the result establishes a local workflow effect without assigning a CDKN1C-specific fixation mechanism (standard IHC practice).
How should I assess cytoplasmic staining when CDKN1C is expected in nuclei?
Prioritise nuclear staining in paraffin sections because CDKN1C is annotated as nuclear and tissue IHC shows nuclear expression in several tissues (UniProt P49918: nucleus; HPA: tissue IHC profile). Nuclear bodies and nucleoplasm are approved main locations, while cytosol is an additional approved location in subcellular imaging (HPA: subcellular localisation). Therefore, isolated cytoplasmic DAB without convincing nuclear staining needs confirmation using a control population such as glomerular cells, reported as High (HPA: kidney glomerular cells; standard IHC practice). Check that the counterstain resolves individual nuclei, and compare the suspect pattern with omission and detection controls before scoring it as CDKN1C (standard IHC practice).
Could isoforms or modified residues explain inconsistent CDKN1C staining?
CDKN1C has 2 annotated isoforms, Long and Short, but the supplied antibody evidence does not map its epitope or establish recognition of both (UniProt P49918: isoforms; datasheet A01244-2: epitope not supplied). The protein has no annotated transmembrane segment, so a membrane-only staining pattern is inconsistent with its recorded topology (UniProt P49918: topology). Annotated modifications include methylarginine at residue 107 and phosphoserine at residue 268; their effects on this antibody's tissue staining are unknown (UniProt P49918: modified residues; datasheet A01244-2: epitope not supplied). If isoform recognition matters, obtain epitope documentation and compare appropriate controls before attributing staining differences to splicing or modification (standard IHC practice).
How can I check CDKN1C localisation in a multiplex IF experiment?
For a separate IF experiment, pair CDKN1C with an independently validated marker of the expected cell population, such as pancreatic endocrine cells, which show High tissue staining (HPA: pancreatic endocrine cells; standard IF practice). CDKN1C is intracellular with nuclear main locations and no transmembrane segment, so use permeabilisation adequate for nuclear antigen access while preserving cell structure (HPA: subcellular localisation; UniProt P49918: topology; standard IF practice). Choose spectrally separated fluorophores after inspecting unstained tissue autofluorescence, and include single-label controls to assess bleed-through (standard IF practice). Score nuclear signal alongside the cell marker; IF staining conditions cannot be inferred from the paraffin-section chromogenic caption (datasheet A01244-2: IHC image; standard IF practice).
What should I investigate when DAB background obscures CDKN1C nuclei?
Inspect a no-primary control and the tissue edges first to separate diffuse detection background from cell-associated nuclear staining (standard IHC practice; UniProt P49918: nucleus). The selected workflow used 10% goat serum blocking, a biotinylated secondary, streptavidin–biotin detection and DAB (datasheet A01244-2). Apply an endogenous peroxidase block as a general DAB workflow step, and check whether the biotin-based system contributes background in a detection-only control (standard IHC practice; datasheet A01244-2: detection system). If background persists, optimise washing and antibody concentration against a documented nuclear-positive population while keeping exposure and development comparable across sections (standard IHC practice; HPA: tissue IHC profile).
How should I quantify CDKN1C across sections with different cell composition? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and score nuclear staining, consistent with the reported tissue pattern, before comparing samples (HPA: tissue IHC profile; standard IHC practice). Report the percentage of positive nuclei or an H-score from 0–300, with fixed intensity thresholds and the number of eligible cells (standard IHC practice). If using positive-cell density per mm², specify whether the denominator is the whole tissue area or a defined compartment, and report cellularity alongside it (standard IHC practice). Normalise comparisons to the same cell type, region, section criteria and detection settings; mixed-cell averages can obscure differences in CDKN1C staining (standard IHC practice).
When is apparent CDKN1C positivity more likely to be artefact?
A convincing result places signal in identifiable nuclei of an appropriate cell population, consistent with CDKN1C's nuclear annotation and tissue IHC profile (UniProt P49918: nucleus; HPA: tissue IHC profile). For comparison, glomerular cells and decidual cells have reported High staining, whereas adipocytes are reported as not detected (HPA: kidney, placenta and adipose tissue). Treat edge-only staining, necrotic regions, diffuse DAB deposits or signal reproduced in a no-primary control as suspect, and check endogenous peroxidase activity where relevant (standard IHC practice). Cytoplasmic signal alone is inconclusive: cytosol is an additional approved location, but nuclear localisation should also be assessed in the scored cells (HPA: subcellular localisation; standard IHC practice).
Boster reagents

Best CDKN1C / Cyclin-dependent kinase inhibitor 1C IHC Antibodies

Explore anti-CDKN1C antibodies with IHC images from human and rat paraffin sections and an IF image from HeLa cells (catalog: IHC and IF image captions).

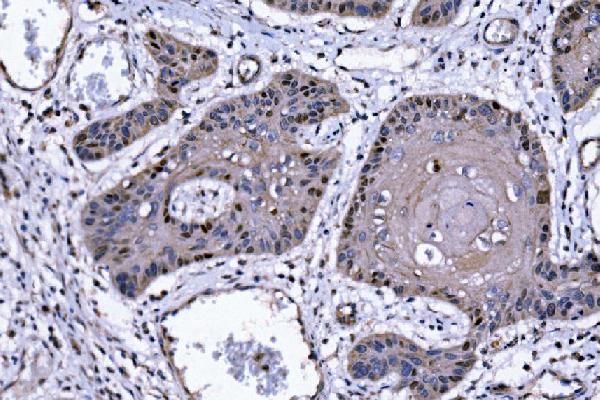
Real IHC data IHC analysis of p57 Kip2/CDKN1C using anti-p57 Kip2/CDKN1C antibody (A01244-2). p57 Kip2/CDKN1C was detected in a paraffin-embedded section of human esophageal squamous carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-p57 Kip2/CDKN1C Antibody (A01244-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-p57 Kip2/CDKN1C Antibody ®
Cat # A01244-2
Real IHC data Immunohistochemical analysis of paraffin-embedded Human thyroid cancer, using the Antibody at 1:50 dilution.
Anti-p57 Kip2 Rabbit Monoclonal Antibody
Cat # M01244-2
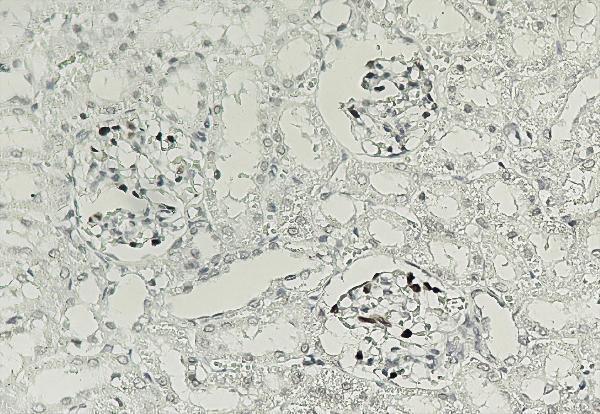
Real IHC data Human kidney tissue was stained with anti-p57kip2 rabbit Antibody
Anti-p57kip2 Rabbit Monoclonal Antibody
Cat # M01244-3

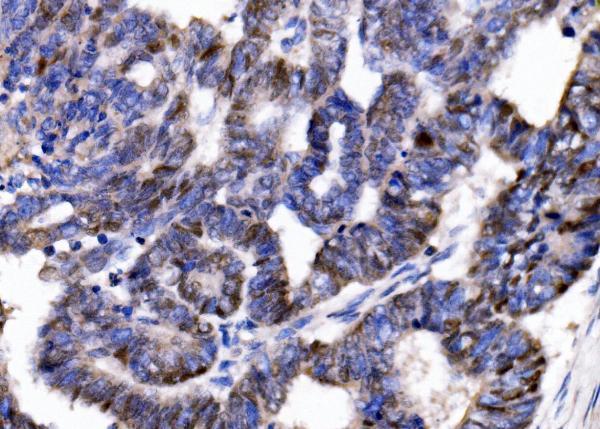
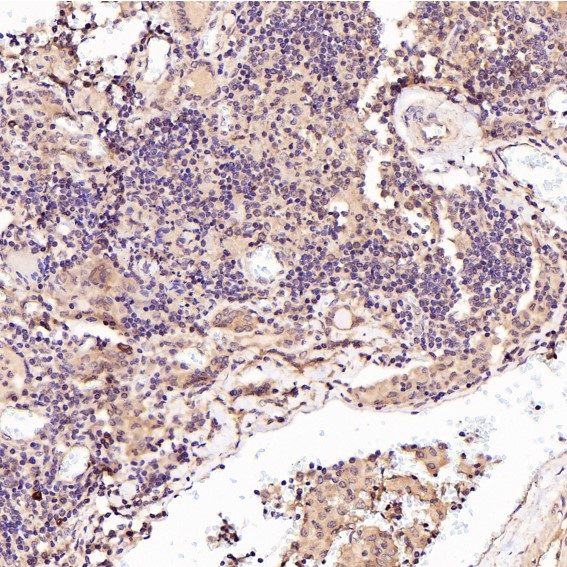
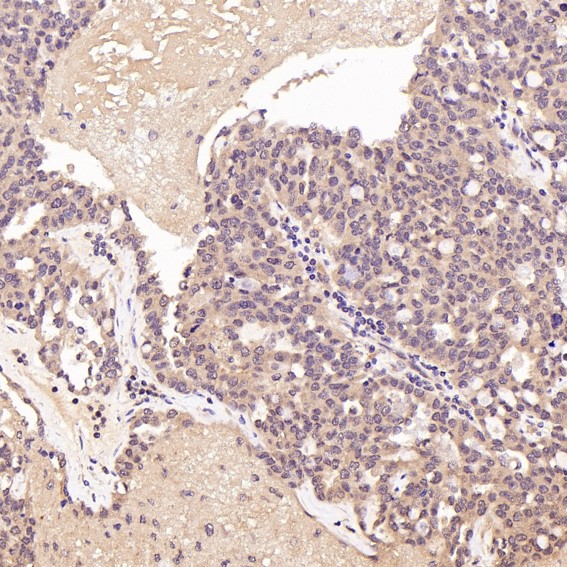
A01244-2 shows IHC in human esophageal squamous carcinoma and rat kidney paraffin sections (A01244-2: IHC captions); M01244-2 shows IHC in human thyroid cancer paraffin sections and IF in HeLa cells (M01244-2: IHC and IF captions). M01244-3 shows IHC staining in human kidney tissue (M01244-3: IHC caption).

Which to pick: For paraffin-section IHC with a documented workflow, choose A01244-2: its caption specifies EDTA retrieval at pH 8.0, 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and DAB detection (A01244-2: IHC caption). For IF/ICC, choose rabbit monoclonal M01244-2, which lists both applications and shows IF in HeLa cells (M01244-2: catalog applications, clone and IF caption). For human, mouse or rat IHC, A01244-2 and M01244-2 list all three species, while M01244-3 lists human only (catalog: reactivity); the IHC captions describe paraffin sections or tissue staining but do not report a fixative (catalog: IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P49918 (CDN1C_HUMAN, Cyclin-dependent kinase inhibitor 1C).
  2. Human Protein Atlas. CDKN1C tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CDKN1C subcellular location (ICC-IF): Mainly localized to the nucleoplasm and nuclear bodies. In addition localized to the cytosol..
  4. Human Protein Atlas. CDKN1C antibody validation summary (1 antibodies).
  5. CDKN1C/p57kip2 is a candidate tumor suppressor gene in human breast cancer. BMC cancer 2008 — PMC2323395.
  6. Cdkn1c Boosts the Development of Brown Adipose Tissue in a Murine Model of Silver Russell Syndrome. PLoS genetics 2016 — PMC4786089.
  7. Relationship of DNA methylation to mutational changes and transcriptional organization in fusion-positive and fusion-negative rhabdomyosarcoma. International journal of cancer 2019 — PMC7415348.
  8. Mutations in the PCNA-binding domain of CDKN1C cause IMAGe syndrome. Nature genetics 2012 — PMC3386373.
  9. PubMed PMID:7729684 — UniProt-cited evidence.
  10. PubMed PMID:8640800 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.