This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan CEP70 paraffin-section IHC around its cytoplasmic tissue staining (HPA tissue IHC). The catalog antibody has an IHC dilution range of 1:100–1:300 (datasheet A10748-1); compare sections with consistent fixation and appropriate negative controls (standard IHC practice).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC); centrosomal localization (UniProt) | |
| Staining pattern | Cytoplasmic staining across diverse tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 8.0 HIER, heat-mediated (datasheet A10748-1) | |
| Positive control | Caudate+4 more · see all | |
| Negative control | Adipose tissue+1 more · see all |
| Fixation | Keep fixation consistent between sections (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA expression show medium consistency (HPA tissue IHC) | |
| Regulation | No expression regulation annotated (UniProt) | |
| Isoform / epitope | 5 isoforms; verify epitope coverage across variants (UniProt) |
The catalog antibody protocol (datasheet: A10748-1) is accompanied by one published CEP70 IHC protocol for pancreatic tissues (PMC4759539: Immunohistochemistry).
| Sample | Paraffin-embedded Human brain tissue; fixative not specified (datasheet A10748-1) |
| Fixation | Image fixative and duration unreported (datasheet A10748-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 8.0 (datasheet A10748-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CEP70, 1:100-1:300 (datasheet A10748-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CEP70-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
CEP70 is a centrosome-associated cytoplasmic protein with no transmembrane segment (UniProt Q8NHQ1: location and topology). In paraffin-section IHC, expect predominantly cytoplasmic staining across many cell types (HPA tissue IHC: ubiquitous cytoplasmic expression; reliability Enhanced). High staining is reported in neuronal cells, Purkinje cells, kidney tubules and several other specified cell populations (HPA tissue IHC: High).
| Cytoplasmic signal in kidney tubular cells, with weaker signal in some surrounding cells. | This fits a reported high-staining population within a broadly cytoplasmic tissue profile (HPA tissue IHC: kidney tubular cells High; ubiquitous cytoplasmic expression). Judge intensity by cell type and local background; a centrosomal focus may be too small to resolve confidently in chromogenic sections (UniProt Q8NHQ1: centrosome localisation; general IHC practice). |
| Strong, exclusively nuclear chromogen with little cytoplasmic signal. | Treat this as discordant with the tissue IHC profile and investigate staining artefact (HPA tissue IHC: ubiquitous cytoplasmic expression; general IHC practice). HPA also reports uncertain nucleoplasmic localisation by ICC-IF, so nuclear signal alone cannot settle whether an IF observation is specific (HPA subcellular: nucleoplasm uncertain). |
| Prominent staining in adipocytes or liver cholangiocytes. | These particular cell populations were reported as not detected (HPA tissue IHC: adipocytes and cholangiocytes Not detected). Recheck cell identification, background and detection controls before assigning CEP70 positivity; cross-reactivity or endogenous detection activity is possible, but the HPA examples do not make either tissue universally negative (general IHC practice; HPA tissue IHC: specified cells Not detected). |
| Diffuse chromogen obscures cell borders or appears similarly in tissue and control sections. | A uniform haze cannot establish the expected cellular distribution (HPA tissue IHC: cytoplasmic profile; general IHC practice). Inspect a section processed without primary antibody and assess blocking, washing and detection chemistry; the pattern may reflect nonspecific binding or endogenous activity (general IHC practice). |
| No convincing signal in kidney tubular cells or cerebellar Purkinje cells. | Both are reported high-staining populations, so absent signal warrants a run-level check (HPA tissue IHC: kidney tubular cells and Purkinje cells High). Review tissue identity, the antibody's IHC validation, detection controls and the recorded retrieval procedure before interpreting a specimen as negative (HPA antibodies: IHC Enhanced; general IHC practice). |
| Cell population and tissue | The profile is broadly cytoplasmic, yet staining levels differ by cell population (HPA tissue IHC: ubiquitous cytoplasmic expression; specified High, Low and Not detected cells). Compare equivalent cells rather than treating every part of a section as an equal-intensity reference (general IHC practice). |
| Subcellular scale | CEP70 is reported at the centrosome and mitotic spindle poles (UniProt Q8NHQ1: subcellular location). A discrete centrosomal dot may be difficult to distinguish from chromogenic background, so cytoplasmic distribution and cell identity remain useful IHC checks (general IHC practice). |
| Antibody evidence and isoforms | Two listed rabbit polyclonal antibodies have Enhanced IHC status, while their ICC status is Uncertain (HPA antibodies: HPA036941 and HPA036942). Five isoforms are listed, but the payload gives no epitope or isoform-coverage data; do not infer that either antibody detects every isoform (UniProt Q8NHQ1: five isoforms; HPA antibodies). |
| IF/ICC Q: what localisation should be expected? | A: HPA reports primary cilium and basal body localisation as approved, centrosome as supported, and nucleoplasm and cytosol as uncertain (HPA subcellular: ICC-IF). Interpret IF/ICC on its own evidence; those location labels do not establish an IHC-P staining pattern (HPA subcellular: ICC-IF; HPA tissue IHC: cytoplasmic profile). |
| Retrieval and processing evidence | No target-specific fixation or antigen-retrieval effect is supplied; tissue intensity and the lack of a transmembrane segment cannot predict either effect (HPA tissue IHC: staining levels; UniProt Q8NHQ1: topology). Record the actual retrieval conditions when comparing IHC runs (general IHC practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected high-staining cells are blank. | A failed staining run, incorrect tissue identification or unsuitable antibody conditions may explain absent signal (HPA tissue IHC: specified High populations; general IHC practice). | Verify the cell population and include a known positive section; review the IHC-validated antibody's documented conditions, retrieval record and detection controls before calling the test section negative (HPA antibodies: IHC Enhanced; general IHC practice). |
| Every compartment shows similar brown haze. | Nonspecific antibody binding or detection background can conceal the reported cytoplasmic pattern (HPA tissue IHC: cytoplasmic expression; general IHC practice). | Compare with a no-primary control; check blocking, wash steps and detection chemistry, then reassess cellular localisation in the cleared section (general IHC practice). |
| Adipocytes or cholangiocytes stain more strongly than nearby expected cells. | Cell misidentification, cross-reactivity or endogenous detection activity is possible (HPA tissue IHC: adipocytes and cholangiocytes Not detected; general IHC practice). | Confirm morphology and compare a no-primary control with an HPA high-staining cell population. Treat these reported negatives as cell-specific reference observations, not absolute negative-tissue controls (HPA tissue IHC: specified Not detected and High populations; general IHC practice). |
| Signal appears only nuclear. | This differs from the reported tissue IHC profile; uncertain nucleoplasmic ICC-IF localisation does not validate nuclear-only chromogenic staining (HPA tissue IHC: cytoplasmic expression; HPA subcellular: nucleoplasm uncertain). | Inspect background controls and compare the same run with a high-staining tissue population. Report the discordance if it persists rather than scoring it as the expected IHC result (HPA tissue IHC: specified High populations; general IHC practice). |
| Signal varies markedly between sections or runs. | Section quality, retrieval execution or detection variation can change an IHC readout (general IHC practice); no CEP70-specific fixation sensitivity is established by the supplied sources. | Compare matched cell populations and a common positive control across runs, then review the recorded processing and detection steps (HPA tissue IHC: cell-specific levels; general IHC practice). |
| ICC-IF puncta seem inconsistent with diffuse IHC staining. | The assays resolve different spatial detail, while HPA assigns different confidence levels to its ICC-IF locations (HPA subcellular: location labels; general IHC practice). | Assess each assay against its own reported pattern: cytoplasmic tissue IHC and the qualified ciliary, centrosomal, basal-body, cytosolic and nucleoplasmic ICC-IF observations (HPA tissue IHC: cytoplasmic expression; HPA subcellular: ICC-IF). |
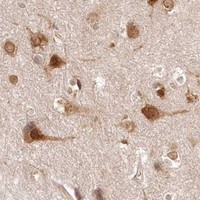

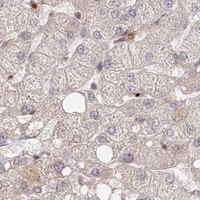


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Pancreas | Exocrine glandular cells | High | Protein (IHC) | HPA → |
Troubleshoot CEP70 staining in paraffin sections by checking retrieval, controls, cellular distribution and scoring before interpreting weak or diffuse signal.
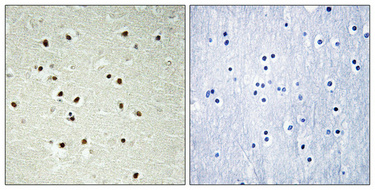
A10748-1 has a human brain paraffin-section IHC image (IHC image caption); IF is listed without an image (catalog: applications and image data). Human and Monkey reactivity is listed (catalog: reactivity).
A10748-1 has an IHC image from paraffin-embedded human brain, with a peptide-preabsorbed control (IHC image caption). The same SKU lists IF as an application and Human and Monkey reactivity, but provides no IF image (catalog: applications, reactivity, and image data).
Which to pick: Choose A10748-1 for tissue IHC when using paraffin sections: its human brain image documents that preparation and 1:100 antibody dilution with Tris-EDTA pH 8.0 retrieval; the fixative is unreported (IHC image caption). For IF, A10748-1 lists 1:50, but IF/ICC sample validation is unreported (catalog: IF dilution and image data). For cross-species work, A10748-1 lists Human and Monkey reactivity, while its IHC image documents only human tissue; the host is rabbit and clonality is unreported (catalog: reactivity, host, and clone; IHC image caption).