CHCHD2 / Coiled-coil-helix-coiled-coil-helix domain-containing protein 2 · IHC design guide

Design Immunohistochemistry for CHCHD2

Plan CHCHD2 paraffin IHC using the catalog antibody’s documented 1:200 incubation (datasheet A06266-1). Compare granular cytoplasmic staining in high-staining glandular or neuronal cells with smooth muscle, where staining was not detected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CHCHD2 (IHC for CHCHD2): expected localisation Observed tissue: granular cytoplasm (HPA tissue IHC); molecular location: mainly mitochondrial intermembrane space (UniProt), antibody A06266-1, validated IHC image, and IHC protocol steps
Printable CHCHD2 IHC protocol sheet — expected localisation Observed tissue: granular cytoplasm (HPA tissue IHC); molecular location: mainly mitochondrial intermembrane space (UniProt), antibody A06266-1, controls and protocol steps. Open the full CHCHD2 IHC guide →

CHCHD2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Observed tissue: granular cytoplasm (HPA tissue IHC); molecular location: mainly mitochondrial intermembrane space (UniProt)
Staining pattern Granular cytoplasm in glandular, neuronal and squamous cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06266-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Smooth muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show medium consistency (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No annotated isoforms or processing; one 1–151 chain (UniProt)
Section 1

Recommended CHCHD2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A06266-1) is accompanied by three published CHCHD2 IHC methods (PMC6975173; PMC6313053; PMC7020603).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A06266-1)
FixationImage fixative and duration unreported (datasheet A06266-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06266-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06266-1)
Primary antibodyRabbit anti-CHCHD2, 1:50 recommended; image 1:200 (datasheet A06266-1)
Primary incubationOvernight at 4 °C (datasheet A06266-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06266-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCHCHD2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A06266-1); the included articles do not specify retrieval conditions for CHCHD2 IHC (PMC6975173; PMC6313053; PMC7020603).
Section 2

What Is the Expected CHCHD2 Staining Pattern?

CHCHD2 is mainly mitochondrial, in the intermembrane space, with nuclear localisation also reported; it has no transmembrane segment (UniProt Q9Y6H1). In paraffin-section IHC, expect granular cytoplasmic staining, especially in the glandular and neuronal cell populations scored High by HPA (HPA: tissue IHC). HPA rates its tissue staining Approved, with medium consistency between staining and RNA expression; interpret a new antibody or tissue result in that context (HPA: tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in adrenal, appendix, colon, duodenum or endometrial glandular cells, or caudate or cortical neurons (HPA: High in these cells).This fits the observed tissue pattern and the mainly mitochondrial localisation (HPA: granular cytoplasmic IHC; UniProt Q9Y6H1). Compare the signal with nearby morphology and controls before scoring it as CHCHD2.
Predominantly nuclear, membrane-rim or uniformly diffuse staining replaces the granular cytoplasmic pattern (HPA: tissue IHC).Treat this as a pattern mismatch and investigate staining artefact or nonspecific binding. Nuclear localisation is annotated, so nuclear signal alone cannot establish an artefact; HPA's tissue IHC profile is the comparator (UniProt Q9Y6H1; HPA: tissue IHC).
Strong staining appears in smooth muscle cells, which HPA scored Not detected (HPA: smooth muscle IHC).Check for cross-reactivity or endogenous detection activity, especially if controls show the same colour. A single discordant section does not establish either cause; HPA's designation is an observed reference pattern (HPA: smooth muscle IHC; general IHC practice).
Colour is widespread across cells, extracellular areas and the blank-slide region, obscuring granules.Diffuse background prevents a reliable compartment call. Review blocking, washing and detection controls under general IHC practice; the expected reference is granular cytoplasmic staining (HPA: tissue IHC).
No staining is seen in a section expected to contain HPA High glandular cells or neurons (HPA: tissue IHC).Treat the result as inconclusive until tissue identity and an independent positive control are checked. Review retrieval and antibody-detection steps using the antibody's validated IHC-P instructions; HPA staining does not establish CHCHD2-specific retrieval requirements (HPA: tissue IHC; general IHC practice).
💡Expected CHCHD2 appearanceCall a positive IHC result when identifiable glandular cells or neurons show convincing granular cytoplasmic signal at the expected HPA High sites (HPA: tissue IHC); broad diffuse colour or strong signal in HPA Not detected smooth muscle warrants investigation, rather than automatic CHCHD2 scoring (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Cell population and tissueUse cell identity when judging intensity: HPA reports High staining in specified glandular cells and neurons, Low staining in hippocampal neurons and adipocytes, and Not detected in smooth muscle cells (HPA: tissue IHC). Low is a reference observation, not a universal negative control.
Compartment and molecular locationHPA describes granular cytoplasmic tissue staining, while UniProt places CHCHD2 mainly in the mitochondrial intermembrane space and also annotates the nucleus (HPA: tissue IHC; UniProt Q9Y6H1). Chromogenic granules support a compatible pattern; they do not resolve the intermembrane space.
Strength of tissue-pattern evidenceHPA marks tissue IHC Approved but reports medium consistency between staining and RNA expression (HPA: tissue IHC). The supplied antibody records list HPA027407 and HPA052510 as IHC Approved; neither designation makes every signal in another assay or tissue specific (HPA: antibody validation).
IF/ICC Q&A: what pattern supports the localisation call?Mitochondrial localisation in an IF/ICC comparison is consistent with HPA's supported mitochondrial assignment (HPA: subcellular ICC-IF). IF/ICC has its own guide; that result can support localisation but does not substitute for interpreting cell populations on an IHC section.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-reference glandular cells or neurons show no usable signal (HPA: tissue IHC).The section may lack the expected cell population, or the IHC run may have lost signal; the supplied sources give no CHCHD2-specific fixation sensitivity (HPA: tissue IHC; general IHC practice).Confirm morphology and run a known-positive section. Check retrieval, primary-antibody use and detection against the catalog antibody's IHC-P instructions; avoid inferring a CHCHD2-specific fixation effect.
The whole section is brown or otherwise diffusely coloured, including areas without the expected granular pattern (HPA: tissue IHC).Nonspecific binding, inadequate washing or detection background can obscure compartment-specific staining (general IHC practice).Inspect a no-primary control and review blocking, washes and detection reagents. Score CHCHD2 only where cell-associated granules can be distinguished from background (HPA: granular cytoplasmic IHC; general IHC practice).
Smooth muscle cells stain strongly despite the HPA Not detected reference (HPA: smooth muscle IHC).Cross-reactivity or endogenous detection activity is possible; the observed colour alone cannot distinguish them (general IHC practice).Compare a no-primary control and the expected positive cell population on the same run. If enzyme-based detection is used, check its endogenous-activity control before assigning CHCHD2 specificity (general IHC practice).
Predominantly nuclear signal appears while the expected cytoplasmic granules are weak (HPA: tissue IHC).The tissue pattern is discordant with HPA's general granular cytoplasmic IHC profile, although UniProt also annotates nuclear CHCHD2 (HPA: tissue IHC; UniProt Q9Y6H1).Document both compartments separately and compare a known-positive section and controls. Do not use the nuclear annotation alone to accept a predominantly nuclear IHC pattern as specific.
Signal is much weaker in hippocampal neurons or adipocytes than in High-reference cells (HPA: tissue IHC).HPA scored these populations Low, so the difference may reflect the observed tissue distribution rather than a failed run (HPA: tissue IHC).Judge run performance in a matched HPA High cell population before changing staining conditions. Record weak signal as such rather than reclassifying these cells as universally negative (HPA: tissue IHC).
An IF/ICC result appears mitochondrial, but paraffin-section IHC lacks interpretable granules (HPA: subcellular ICC-IF; HPA: tissue IHC).The assays answer related localisation questions under different preparations; mitochondrial IF/ICC does not establish that this IHC section worked (HPA: subcellular ICC-IF; general IHC practice).Use the IHC controls and expected tissue cell populations to assess this section. Refer to the separate IF/ICC guide for that assay; do not transfer an IF/ICC protocol to IHC-P.

Sample controls for CHCHD2 IHC & IF

🧪Run colon first: glandular cells should stain strongly (HPA: High in colon glandular cells). Run smooth muscle as the negative tissue (HPA: Not detected in smooth muscle cells); on the colon slide, use adjacent nonglandular cells as a provisional background reference and confirm any apparent absence of staining with controls (HPA: High is specified for glandular cells only).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Smooth muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CHCHD2 in A-431, U-251MG, U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (caption: rabbit primary and anti-rabbit secondary; standard IHC practice). Use CHCHD2 knockout material as a biological negative, and quench endogenous peroxidase before DAB detection in colon tissue (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence; the selected A06266-1 tissue-IHC caption does not state a fixative. The caption reports heat retrieval in EDTA at pH 8.0 and a 1:200 primary dilution overnight at 4°C, but does not establish whether retrieval is required (caption: A06266-1 tissue IHC). Frozen-section or IF/ICC ease relative to this paraffin IHC workflow is unreported; in colon, endogenous peroxidase can produce misleading DAB signal (standard IHC practice).

HPA tissue IHC evidence for CHCHD2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced CHCHD2 IHC Tips

Troubleshoot CHCHD2 staining by checking retrieval, compartment, tissue context and controls before interpreting chromogenic signal.

Which retrieval conditions should I start with for CHCHD2 paraffin-section IHC?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A06266-1). The catalog antibody produced a paraffin-section staining example after this retrieval, followed by 1:200 primary antibody overnight at 4°C (datasheet A06266-1). If staining is weak, compare retrieval heating times on matched sections while keeping the buffer, detection system and exposure to DAB constant (standard IHC practice). Include a section processed without primary antibody to identify detection background (standard IHC practice). Assess whether the expected granular cytoplasmic pattern improves without a parallel rise in diffuse staining (HPA tissue IHC: granular cytoplasmic profile).
How should I troubleshoot weak staining when the tissue fixative is unknown?
The selected paraffin-section caption does not state a fixative, so CHCHD2-specific fixation sensitivity is unknown (datasheet A06266-1: fixative unreported). Record the fixative and processing history for each specimen, then compare matched sections processed with the same EDTA pH 8.0 retrieval and 1:200 antibody dilution (datasheet A06266-1; standard IHC practice). Use a consistently positive control section in each run to distinguish specimen variation from a staining-run failure (standard IHC practice). Check tissue preservation and staining at cut edges before changing detection conditions (standard IHC practice). Neither the tissue staining profile nor mitochondrial location establishes a CHCHD2-specific fixation effect (HPA tissue IHC; UniProt Q9Y6H1).
Should CHCHD2 appear nuclear or cytoplasmic in chromogenic sections?
Expect predominantly granular cytoplasmic staining in tissue sections (HPA tissue IHC: general granular cytoplasmic expression). CHCHD2 is mainly in the mitochondrial intermembrane space, although a nuclear location is also reported (UniProt Q9Y6H1); mitochondrial localisation is supported by cell imaging (HPA subcellular). At the resolution of routine chromogenic IHC, score a granular cytoplasmic pattern before interpreting isolated nuclear DAB as specific (standard IHC practice; HPA tissue IHC). Compare the same cell type across a 1:200 primary-antibody section and a no-primary control processed together (datasheet A06266-1; standard IHC practice). If nuclear staining persists alone, seek independent antibody or compartment evidence before assigning it to CHCHD2 (standard IHC practice).
Could an isoform or hidden epitope explain inconsistent CHCHD2 staining?
The supplied record lists a single 151-residue chain and no annotated isoforms, signal peptide, propeptide, glycosylation sites or modified residues (UniProt Q9Y6H1). Its CHCH domain spans residues 111–151, and no transmembrane segment is annotated (UniProt Q9Y6H1). The antibody epitope is not supplied, so do not assume that it lies in that domain or that a particular processing event masks it (datasheet A06266-1: epitope unspecified; UniProt Q9Y6H1). Compare matched sections using EDTA pH 8.0 retrieval and the same detection settings before attributing discordance to epitope access (datasheet A06266-1; standard IHC practice). Confirm a persistent discrepancy with an independently validated antibody if available (standard IHC practice).
How can IF help assess a puzzling CHCHD2 IHC pattern?
Use IF/ICC as a complementary localisation check, while keeping the paraffin-section chromogenic result as the IHC readout (standard IHC practice). Multiplex CHCHD2 with a marker for the cell population being assessed and a mitochondrial marker, then examine signal within individual cells (HPA subcellular: supported mitochondrial location; standard IF practice). Choose spectrally separated fluorophores, favoring a far-red channel when tissue autofluorescence obscures shorter wavelengths, and include single-color controls (standard IF practice). CHCHD2 is mainly in the mitochondrial intermembrane space, but the antibody epitope is unspecified; assess permeabilisation for access to the relevant side of the mitochondrial membranes rather than assuming cytosolic access suffices (UniProt Q9Y6H1; datasheet A06266-1: epitope unspecified). Do not transfer fixation conditions from the IHC caption, which reports no fixative (datasheet A06266-1).
What should I change when CHCHD2 DAB staining is diffuse?
First inspect a no-primary section for secondary-reagent binding and endogenous peroxidase signal, using a peroxidase block as part of the general chromogenic workflow (standard IHC practice). Compare the catalog condition of 1:200 primary antibody overnight at 4°C with a more dilute primary on matched sections, holding EDTA pH 8.0 retrieval constant (datasheet A06266-1; standard IHC practice). The illustrated procedure used 10% goat-serum blocking and DAB development, but the caption does not establish those steps as CHCHD2-specific requirements (datasheet A06266-1). Shorten DAB development if control sections darken, and assess background separately from granular cytoplasmic staining (standard IHC practice; HPA tissue IHC).
How should I quantify CHCHD2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring area before reviewing stain intensity, and exclude folds, necrosis and section edges consistently (standard IHC practice). Score the percentage of positive cells and cytoplasmic intensity, or calculate an H-score from 0–300 using percentages at intensities 0–3 (standard IHC practice). For spatial analyses, report positive-cell density per mm² of viable tissue and normalize signal to the number of eligible cells or viable area (standard IHC practice). Keep retrieval at EDTA pH 8.0, primary dilution at 1:200 and DAB development consistent across a comparison batch (datasheet A06266-1; standard IHC practice). Report granular cytoplasmic and nuclear staining separately because the expected tissue profile is granular cytoplasmic (HPA tissue IHC).
How can I distinguish genuine CHCHD2 staining from tissue artefacts?
Treat reproducible granular cytoplasmic staining in the relevant cells as the strongest chromogenic pattern to evaluate (HPA tissue IHC: granular cytoplasmic profile). CHCHD2 is mainly mitochondrial, with nuclear localisation also reported, so an exclusively diffuse nuclear result needs independent support rather than automatic rejection or acceptance (UniProt Q9Y6H1; HPA subcellular). Compare cell identity and compartment with reference patterns: high staining is reported in colon glandular cells, whereas smooth muscle cells are listed as not detected (HPA tissue IHC). Discount signal confined to tissue edges, necrosis or a no-primary section, and check peroxidase blocking when DAB appears in controls (standard IHC practice). HPA rates the tissue staining as Approved with medium RNA consistency, so interpret small intensity differences cautiously (HPA tissue IHC).
Boster reagents

Best CHCHD2 / Coiled-coil-helix-coiled-coil-helix domain-containing protein 2 IHC Antibodies

The catalog antibody has real IHC data from a human lung cancer paraffin section; IF/ICC is listed without an IF image, and human and rat reactivity is listed (IHC caption; catalog applications and reactivity).

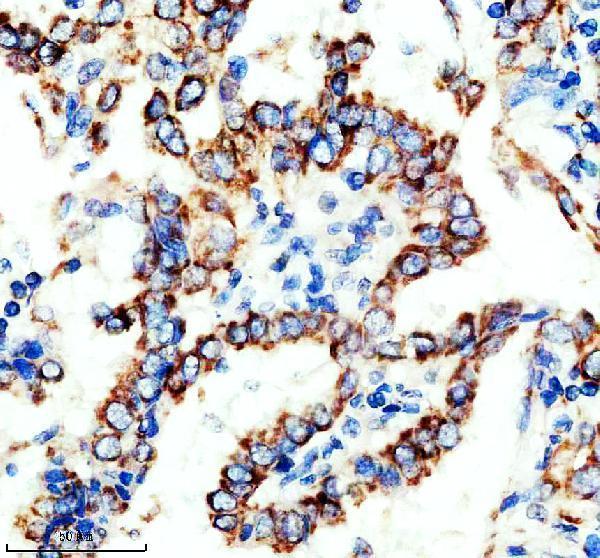
Real IHC data IHC analysis of CHCHD2 using anti-CHCHD2 antibody (A06266-1). CHCHD2 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:200 rabbit anti-CHCHD2 Antibody (A06266-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CHCHD2 Antibody ®
Cat # A06266-1

A06266-1 was demonstrated by chromogenic IHC on a paraffin section of human lung cancer tissue (A06266-1 IHC caption). A06266-1 also lists IF/ICC and human and rat reactivity, but provides no IF image (A06266-1 catalog applications, reactivity, and image records).

Which to pick: Choose A06266-1 for tissue IHC: its caption documents EDTA retrieval at pH 8.0 and antibody at 1:200 on a human lung cancer paraffin section; the fixative is unreported (A06266-1 IHC caption). For IF/ICC, A06266-1 lists those applications and a 1:50 dilution, but has no IF image (A06266-1 catalog applications, IF dilution, and image records). It is a polyclonal option with listed human and rat reactivity; the supplied IHC image documents human tissue only (A06266-1 catalog description, reactivity, and IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y6H1 (CHCH2_HUMAN, Coiled-coil-helix-coiled-coil-helix domain-containing protein 2).
  2. Human Protein Atlas. CHCHD2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CHCHD2 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. CHCHD2 antibody validation summary (2 antibodies).
  5. Neuropathologic description of CHCHD10 mutated amyotrophic lateral sclerosis. Neurology. Genetics 2020 — PMC6975173.
  6. Knockdown of CHCHD2 inhibits migration and angiogenesis of human renal cell carcinoma: A potential molecular marker for treatment of RCC. Oncology letters 2019 — PMC6313053.
  7. CHCHD2 is a potential prognostic factor for NSCLC and is associated with HIF-1a expression. BMC pulmonary medicine 2020 — PMC7020603.
  8. Decoding temporal heterogeneity in NSCLC through machine learning and prognostic model construction. World journal of surgical oncology 2024 — PMC11170806.
  9. PubMed PMID:12853948 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:21269460 — UniProt-cited evidence.