This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic CHD3 IHC in paraffin sections using the catalog antibody at 1:100 as a starting dilution (datasheet: M03200 IHC images). Assess nuclear and cytoplasmic staining, comparing strongly stained urothelial cells in urinary bladder with lower-signal cell populations (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear and cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Nuclear and cytoplasmic staining with variable intensity (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M03200) | |
| Positive control | Cerebral cortex+4 more · see all | |
| Negative control | Appendix+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent (standard IHC practice; not target-specific) | |
| Caveat | Cell-type staining ranges from high to undetected (HPA tissue IHC) | |
| Regulation | Expression regulator not specified (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope coverage is unknown (UniProt) |
The catalog antibody’s IHC-P protocol is followed by one published CHD3 protocol for paraffin sections (PMC3654872).
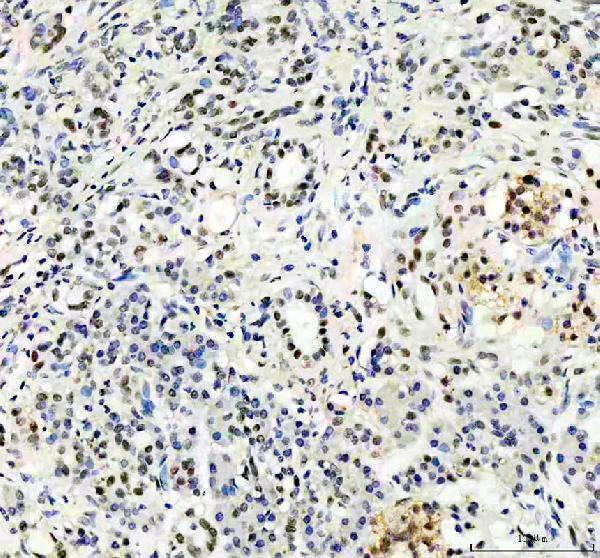
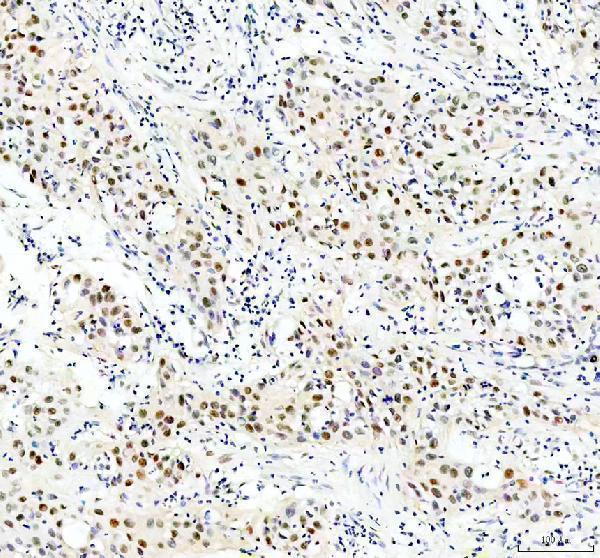
| Sample | Paraffin-embedded human pancrease cancer tissue; fixative not specified (datasheet M03200) |
| Fixation | Image fixative and duration unreported (datasheet M03200); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M03200); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M03200) |
| Primary antibody | Rabbit monoclonal (clone 17C46) anti-CHD3, 1:50-1:200 (datasheet M03200) |
| Primary incubation | Overnight at 4 °C (datasheet M03200) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet M03200) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CHD3-positive staining in neuronal cells of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control. |
CHD3 is a nuclear chromatin remodeler that can also localize to centrosomes (UniProt Q12873: localization and function). In paraffin sections, expect staining in selected neuronal, glandular, endothelial, Sertoli, and urothelial cells, with nuclear and cytoplasmic expression reported across tissues (HPA: tissue IHC, Supported reliability). CHD3 has no transmembrane segment (UniProt Q12873: topology).
| Nuclear staining in cerebral cortex neurons and fallopian tube glandular cells. | This fits the expected compartment and cells: both populations show high CHD3 staining (HPA: tissue IHC). Compare cell types within the section; widespread expression does not mean every cell should stain equally (UniProt Q12873: widely expressed; HPA: tissue IHC). |
| Staining appears only along cell membranes, without a discernible nuclear component. | A membrane-only pattern conflicts with the reported nuclear and cytoplasmic tissue profile and nuclear localization (HPA: tissue IHC; UniProt Q12873: localization). CHD3 has no transmembrane segment (UniProt Q12873: topology). Treat this pattern as suspect until controls support it. |
| Strong signal appears in appendix non-germinal center cells or bone marrow hematopoietic cells. | Those specific populations were not detected in the HPA tissue survey (HPA: tissue IHC). Check for cross-reactivity or endogenous detection activity before interpreting the signal as CHD3; an HPA observation is a reference pattern, not an absolute biological exclusion. |
| A diffuse brown haze obscures both nuclei and tissue boundaries. | When staining lacks recognizable cellular localization, it cannot establish the reported CHD3 pattern (HPA: tissue IHC). Nonspecific antibody binding, residual detection activity, or inadequate washing are general IHC possibilities; inspect a negative reagent control and the counterstain (general IHC practice). |
| There is no signal in a well-preserved cerebral cortex neuronal population. | Neurons were high in the HPA cerebral cortex sample (HPA: tissue IHC). First check the staining run and tissue preservation with appropriate controls (general IHC practice). A negative result in one specimen does not by itself establish CHD3 absence. |
| Cell population and reference tissue | CHD3 is widely expressed, yet HPA staining varies by cell type (UniProt Q12873: tissue specificity; HPA: tissue IHC). High-reference examples include salivary gland glandular cells and bladder urothelial cells; low-reference examples include small-intestine enterocytes and breast glandular cells (HPA: tissue IHC). |
| Antibody evidence | The tissue IHC profile has Supported reliability, with medium consistency between staining and RNA data; HPA043368 is Supported for IHC (HPA: tissue IHC and antibody validation). Interpret an individual stain alongside controls and morphology rather than assuming every reported intensity will reproduce in every specimen (general IHC practice). |
| Subcellular localization | UniProt places CHD3 in nuclei and PML bodies and reports centrosome association; HPA describes general nuclear and cytoplasmic tissue expression (UniProt Q12873: localization; HPA: tissue IHC). Thus cytoplasmic signal alone needs context, while a clean nuclear component is a useful reference. |
| Isoforms and modified residues | UniProt lists three isoforms and multiple phosphorylation sites (UniProt Q12873: isoforms and modified residues). The supplied sources give no epitope map for the catalog antibody, so they do not establish whether isoform choice or phosphorylation changes this IHC stain. |
| Antigen retrieval | Retrieval conditions are a general paraffin-section optimization variable (general IHC practice). Neither supplied source establishes CHD3-specific retrieval sensitivity; compare any candidate condition against the same positive-reference tissue and controls rather than attributing a change to CHD3 chemistry. |
| IF/ICC Q: Where should fluorescence appear? | A: Mainly in nucleoplasm and nucleoli (HPA: ICC-IF, supported); centriolar-satellite localization is uncertain (HPA: ICC-IF). This is an IF localization reference, not an IHC protocol choice. |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in a positive-reference section | A failed reagent or detection step is possible (general IHC practice); neuronal cells in cerebral cortex were high in the HPA survey (HPA: tissue IHC). | Check the run control, reagent sequence, detection chemistry, and counterstained tissue integrity (general IHC practice); repeat with an HPA-high cell population (HPA: tissue IHC). |
| Only cytoplasmic color is visible | HPA reports a cytoplasmic component, but UniProt also places CHD3 in nuclei (HPA: tissue IHC; UniProt Q12873: localization). | Inspect nuclear boundaries and the matched controls before scoring; compare with an HPA-high population for a nuclear component (general IHC practice; HPA: tissue IHC). |
| Every cell stains equally strongly | Uniform signal obscures HPA's cell-type differences and may reflect nonspecific binding or detection background (HPA: tissue IHC; general IHC practice). | Review a negative reagent control and optimize blocking, washing, or detection conditions if background is present (general IHC practice). |
| Brown haze persists outside recognizable cells | Nonspecific binding or residual detection activity can produce poorly localized color (general IHC practice). | Compare with a negative reagent control, then review blocking and wash conditions; score only signal assignable to intact cells (general IHC practice). |
| A presumed negative tissue shows scattered positive cells | HPA 'not detected' entries apply to named populations, not necessarily every cell in an organ (HPA: tissue IHC). | Identify the stained cell type before calling the tissue discordant; compare the same population with its HPA reference and check controls (HPA: tissue IHC; general IHC practice). |
| Signal varies between specimens of the same tissue | HPA rates the tissue IHC evidence Supported with medium staining–RNA consistency, and its reported levels are cell-type specific (HPA: tissue IHC). | Compare matched cell populations and run controls, document staining location and intensity, and avoid assigning a fixation-specific CHD3 effect without evidence (HPA: tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | Low | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Salivary gland | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Non-germinal center cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Duodenum | Endocrine cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot CHD3 staining in paraffin sections by checking retrieval, cell compartment, controls and scoring before interpreting chromogenic signal.
M03200 has IHC images from paraffin sections of human, mouse, and rat tissue (M03200 IHC captions). IF/ICC is listed for both antibodies, but no IF images are supplied (catalog applications and IF images).
M03200 is the only SKU with a rendering card (cards payload). Its IHC captions show paraffin sections of human pancreas and bladder cancer tissue and mouse and rat bladder cancer tissue (M03200 IHC captions).
Which to pick: Choose M03200 for tissue IHC: its own captions document EDTA pH 8 retrieval and 1:100 primary antibody overnight at 4°C on paraffin sections; the fixative is unreported (M03200 IHC captions). For IF/ICC, both rabbit monoclonals are listed at 1:50–1:200, but neither has a supplied IF image (catalog host, applications, IF dilutions, and IF images). Choose M03200 for cross-species work because it lists human, mouse, and rat reactivity, while M03200-1 lists human only (catalog reactivity).