This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan CHKB staining in paraffin sections using the general cytoplasmic pattern reported in tissue IHC (HPA tissue IHC). Pancreatic exocrine cells show high staining (HPA tissue IHC); titrate the IHC-validated antibody within 1:50–1:200 (datasheet: A06297).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in pancreatic exocrine cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Pancreas+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Staining-linked regulation is not reported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unspecified (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet) with a published CHKB protocol for human and mouse colon paraffin sections (PMC9701742).
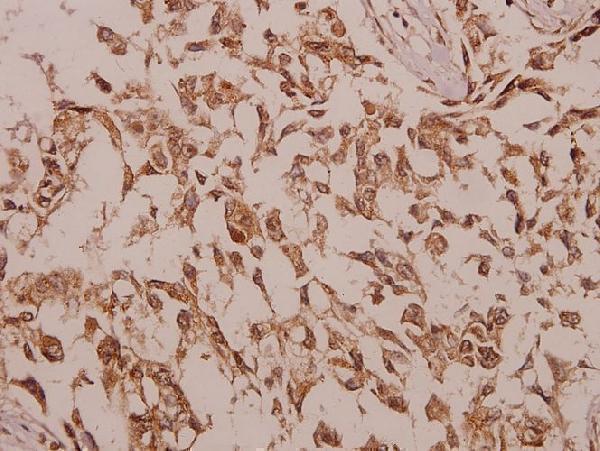
| Sample | Paraffin-embedded human colorectal carcinoma tissue; fixative not specified (datasheet A06297) |
| Fixation | Image fixative and duration unreported (datasheet A06297); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CHKB, 1:50-1:200 (datasheet A06297) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CHKB-positive staining in exocrine glandular cells of pancreas (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
CHKB staining should be predominantly cytoplasmic in paraffin sections (HPA tissue IHC: general cytoplasmic expression). A cytosolic location is also observed by ICC-IF (HPA subcellular: approved cytosol); CHKB has no annotated transmembrane segment (UniProt Q9Y259 topology). Expect stronger staining in pancreatic exocrine glandular cells, placental decidual cells, smooth muscle cells, thyroid glandular cells, and tonsillar non-germinal center cells (HPA tissue IHC: High). The tissue IHC assessment is Approved, with medium consistency between staining and RNA data (HPA tissue IHC).
| Cytoplasmic staining is prominent in pancreatic exocrine glandular cells or thyroid glandular cells. | This fits reported High staining in those cell populations (HPA tissue IHC: High) and the reported cytoplasmic pattern (HPA tissue IHC). Compare the stained cells with tissue morphology before scoring intensity (general IHC practice). |
| Staining is mainly nuclear or sharply restricted to cell membranes. | That compartment differs from the reported cytoplasmic tissue pattern and approved cytosolic ICC-IF location (HPA tissue IHC; HPA subcellular). Treat it as a specificity or detection concern; morphology alone cannot identify its cause (general IHC practice). |
| The darkest signal is confined to a cell type other than the reported High populations. | Check cell identity and tissue context first: CHKB has low RNA tissue specificity, and HPA reports staining in several cell types (HPA tissue IHC). If the pattern remains discordant, assess possible antibody cross-reactivity or endogenous detection activity with appropriate controls (general IHC practice). |
| Chromogen covers multiple compartments or blank regions without clear cellular boundaries. | This diffuse background cannot establish CHKB localization (general IHC practice). Review blocking, reagent carryover, wash quality, and the detection-only control before interpreting faint cytoplasmic color (general IHC practice). |
| A known-positive region shows no visible staining. | Confirm that the section actually contains the reported positive cells; pancreas exocrine glandular cells and smooth muscle cells are High in HPA tissue IHC (HPA tissue IHC: High). If present, check assay controls and detection steps before calling CHKB absent (general IHC practice). |
| Tissue and cell selection | Use named cell populations when judging intensity: pancreatic exocrine glandular, placental decidual, smooth muscle, thyroid glandular, and tonsillar non-germinal center cells are High; adrenal glandular and bone marrow hematopoietic cells are Medium (HPA tissue IHC). HPA lists no negative tissue in this payload (HPA tissue IHC). |
| Strength of pattern evidence | The tissue IHC assessment is Approved but has medium consistency between staining and RNA expression (HPA tissue IHC). Treat a matching slide as supportive evidence, especially when cell identity and controls agree; it is not proof that every stained cell expresses CHKB specifically (general IHC practice). |
| Molecular form and antibody recognition | CHKB has two annotated isoforms and no annotated signal peptide or transmembrane segment (UniProt Q9Y259). The supplied record gives no epitope or isoform-specific antibody recognition data, so the expected stain cannot be assigned to one isoform (UniProt Q9Y259; HPA antibody record). |
| Does IF/ICC change the IHC expectation? | ICC-IF reports approved cytosolic localization in A-431, U-251MG, and U2OS cells (HPA subcellular). This supports a cytoplasmic interpretation of tissue IHC; the separate cell-imaging result supplies no paraffin-section staining intensity or IHC protocol conditions (HPA subcellular; HPA tissue IHC). |
| Chromogenic detection | Endogenous enzyme activity or detection-reagent binding can imitate cellular color in chromogenic IHC (general IHC practice). Use the detection-only control and the chemistry's appropriate blocking step to assess that possibility; the payload reports no CHKB-specific endogenous-activity effect (HPA tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal in pancreatic exocrine glandular cells. | The expected High population may be missing from the evaluated area (HPA tissue IHC: High), or an assay step may have failed (general IHC practice). | Verify morphology and a working positive control, then review the catalog antibody's IHC-P instructions and detection reagents (general IHC practice). |
| Weak staining in a reported High population. | Intensity may reflect tissue sampling or assay conditions; HPA's High label does not define the intensity of every section (HPA tissue IHC; general IHC practice). | Compare matching cell types and controls on the same run; review antibody dilution and antigen retrieval under the validated IHC-P procedure (general IHC practice). |
| Strong nuclear or membrane-only signal. | The compartment conflicts with reported cytoplasmic tissue staining and cytosolic ICC-IF localization (HPA tissue IHC; HPA subcellular). | Check localization against counterstain and cell boundaries; inspect controls and reassess antibody specificity before scoring the signal as CHKB (general IHC practice). |
| Color appears across blank spaces or many unrelated structures. | Diffuse background or detection chemistry may obscure a cellular pattern (general IHC practice). | Review washes, blocking, and detection-only controls; score CHKB only where cell-associated cytoplasmic staining can be distinguished (general IHC practice; HPA tissue IHC). |
| A low-staining cell type appears darker than the reported High cells. | HPA reports low staining in adipocytes and esophageal squamous epithelial cells, versus High staining in several named populations (HPA tissue IHC). | Recheck cell identification, compare an appropriate High reference tissue, and investigate detection background or cross-reactivity if the contrast persists (general IHC practice). |
| Adjacent samples give inconsistent positive-cell counts. | Different proportions of reported positive cell types can change the apparent tissue-wide result (HPA tissue IHC; general IHC practice). | Score the named cell population and its cytoplasmic pattern separately from overall section color; document which regions were evaluated (general IHC practice; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Pancreas | Exocrine glandular cells | High | Protein (IHC) | HPA → |
| Placenta | Decidual cells | High | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | High | Protein (IHC) | HPA → |
| Thyroid gland | Glandular cells | High | Protein (IHC) | HPA → |
| Tonsil | Non-germinal center cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: CHKB is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot CHKB staining in paraffin sections by checking retrieval, cellular pattern, controls, and scoring before interpreting chromogenic signal.
The catalog shows CHKB IHC staining in a paraffin-embedded human colorectal carcinoma section; both antibodies list Human, Mouse and Rat reactivity, and one also lists IF (IHC image caption; catalog applications/reactivity).
The rendered A06297 card shows IHC staining of paraffin-embedded human colorectal carcinoma tissue at 1:50 (A06297 IHC image caption). A06297-1 is listed for IHC and IF in Human, Mouse and Rat, but has no IHC or IF image and will not render as a card (A06297-1 catalog applications/reactivity/image captions; card list).
Which to pick: For tissue IHC, choose A06297: its own image documents paraffin-section staining, while the fixative is unreported (A06297 IHC image caption). For IF, consider A06297-1 because IF is listed; ICC performance and an IF figure are unreported (A06297-1 catalog applications/image captions). Either SKU lists Human, Mouse and Rat reactivity, but the only supplied tissue image is human (catalog reactivity; A06297 IHC image caption).