CHMP2B / Charged multivesicular body protein 2b · IHC design guide

Design Immunohistochemistry for CHMP2B

Plan CHMP2B chromogenic IHC in paraffin sections with a 1:50 catalog antibody dilution (datasheet M01935). Assess cytoplasmic staining in colon glandular cells, bearing in mind that tissue staining reliability is uncertain (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CHMP2B (IHC for CHMP2B): expected localisation Cytoplasmic tissue stain; cytosol and late endosome membrane (HPA tissue IHC; UniProt), antibody M01935, validated IHC image, and IHC protocol steps
Printable CHMP2B IHC protocol sheet — expected localisation Cytoplasmic tissue stain; cytosol and late endosome membrane (HPA tissue IHC; UniProt), antibody M01935, controls and protocol steps. Open the full CHMP2B IHC guide →

CHMP2B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue stain; cytosol and late endosome membrane (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic stain in selected glandular and immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M01935)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Low staining–RNA consistency; tissue pattern is uncertain (HPA tissue IHC)
Regulation Widely expressed (UniProt)
Isoform / epitope 2 isoforms; antibody epitope coverage unspecified (UniProt; datasheet M01935)
Section 1

Recommended CHMP2B IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: M01935) with one published CHMP2B protocol for paraffin-embedded brain sections (PMC3207829).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet M01935)
FixationImage fixative and duration unreported (datasheet M01935); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M01935); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M01935)
Primary antibodyRabbit monoclonal (clone 25C36) anti-CHMP2B, 1:50 (datasheet M01935)
Primary incubationOvernight at 4 °C (datasheet M01935)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M01935)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCHMP2B-positive staining in glandular cells of appendix (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in selected tissues, including immune cells in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: M01935); the published protocol used microwave retrieval in distilled water (PMC3207829).
Section 2

What Is the Expected CHMP2B Staining Pattern?

CHMP2B is annotated in the cytosol and at late endosome membranes, without a transmembrane segment (UniProt Q9UQN3). Expect mainly cytoplasmic staining in selected cells, including kidney tubule cells, hepatocytes and glandular cells (HPA: Medium in each). Treat this as a guide, not a universal tissue rule: HPA rates its tissue IHC profile Uncertain because antibody staining and RNA expression show low consistency (HPA: Uncertain).

What am I looking at on my slide?
Cytoplasmic signal in kidney tubule cells or hepatocytes, with tissue structures clearly resolved.This fits two reported Medium IHC observations (HPA: kidney tubule cells; HPA: hepatocytes) and CHMP2B's cytosolic annotation (UniProt Q9UQN3). Cytoplasmic staining alone does not establish antibody specificity: compare the expected cells with neighboring cells and review controls (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal in the same cells.Nuclear dominance conflicts with the supplied cytosol and late endosome membrane annotations (UniProt Q9UQN3; HPA: Cytosol approved in ICC-IF). Consider detection artefact or nonspecific binding; the unexpected compartment is a reason to investigate, not proof of a specific mechanism (general IHC practice).
Strong staining mainly in a cell population reported as undetected, while expected cells remain unstained.For example, HPA reports adipocytes in adipose tissue as Not detected and kidney tubule cells as Medium (HPA: tissue IHC). Consider cross-reactivity or endogenous detection activity, then check morphology and controls (general IHC practice). HPA's Uncertain reliability means its negative calls are comparison points, not absolute exclusions (HPA: Uncertain).
Diffuse color across cells and surrounding tissue obscures cell boundaries.This cannot establish CHMP2B's cellular location (general IHC practice). Broad background can arise from nonspecific binding, incomplete blocking or endogenous detection activity (general IHC practice). Compare a control lacking primary antibody and inspect whether the color tracks recognizable cells (general IHC practice).
No signal in kidney tubule cells or hepatocytes in a technically readable section.Both cell populations have reported Medium staining, so absence warrants a workflow and antibody check (HPA: kidney; HPA: liver). It does not prove CHMP2B absence: the HPA tissue profile is Uncertain, and the supplied sources give no CHMP2B-specific fixation or retrieval sensitivity (HPA: Uncertain; supplied source scope).
💡Expected CHMP2B appearanceA plausible positive is Medium cytoplasmic staining in kidney tubule cells or hepatocytes (HPA: kidney and liver), while dominant nuclear color or diffuse cell-free color warrants an artefact check (UniProt Q9UQN3; general IHC practice).
How each factor affects the staining
Compartment and topology (UniProt Q9UQN3)CHMP2B is annotated in cytosol and at late endosome membranes, with no transmembrane segment (UniProt Q9UQN3). Interpret cytoplasmic staining in that context; a continuous plasma-membrane outline is not the pattern established by these annotations (UniProt Q9UQN3).
Tissue and antibody evidence (HPA: Uncertain)RNA has low tissue specificity, yet the observed IHC profile is selective and rated Uncertain for low staining–RNA consistency (HPA: tissue IHC). The listed IHC antibody HPA035069 is also rated Uncertain; these observations should not serve as stand-alone specificity validation (HPA: antibody validation).
Isoforms and epitope coverage (UniProt Q9UQN3)UniProt lists 2 isoforms (UniProt Q9UQN3). The supplied evidence does not map an antibody epitope or establish isoform recognition; do not assign differences between tissue sections to a particular isoform from IHC color alone (UniProt Q9UQN3; supplied source scope).
Target-specific retrieval evidence (supplied source scope)No CHMP2B-specific fixation effect or antigen-retrieval condition is supplied (supplied source scope). Retrieval can be assessed with appropriate controls as general IHC practice, without claiming that fixation masks this particular epitope (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
What if expected cytoplasmic cells are blank?Low signal or a failed staining run is possible; HPA reports Medium staining in kidney tubules and hepatocytes but rates the tissue profile Uncertain (HPA: kidney, liver; HPA: Uncertain).Check section integrity, reagent delivery and a suitable positive control; use the catalog antibody's documented IHC-P instructions if available (general IHC practice). Avoid inferring a CHMP2B-specific fixation effect from this result (supplied source scope).
What if nuclei dominate the signal?The pattern disagrees with the cytosolic location approved in HPA ICC-IF and the cytosol annotation in UniProt (HPA: Cytosol approved; UniProt Q9UQN3).Inspect counterstain and chromogen separately, then compare a control lacking primary antibody (general IHC practice). Confirm that apparent nuclear color is signal rather than overlapping cytoplasm before scoring (general IHC practice).
What if unexpected cells stain strongly?Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA reports some cell populations as Not detected, but its overall IHC reliability is Uncertain (HPA: tissue IHC).Identify the stained cells by morphology, compare HPA's cell-specific observations, and examine a control lacking primary antibody (HPA: tissue IHC; general IHC practice). Treat discordance as a validation question, not a definitive negative-cell rule (HPA: Uncertain).
What if color is diffuse or structures disappear?Excess background may reflect nonspecific binding or endogenous detection activity (general IHC practice). Such color cannot be scored reliably as cytoplasmic CHMP2B (general IHC practice).Review blocking, washing and detection controls; adjust these as general IHC workflow variables while preserving interpretable tissue morphology (general IHC practice). Do not use overall darkness as a substitute for cell-level localization (general IHC practice).
What if two tissues show different strengths?Variation is consistent with the reported selected-tissue IHC profile, including Medium kidney tubule and liver hepatocyte staining and Low lung macrophage staining (HPA: tissue IHC).Score each named cell population separately and record intensity with localization (general IHC practice). Because HPA rates the tissue profile Uncertain, corroborate an unexpected biological conclusion before generalizing across tissues (HPA: Uncertain).
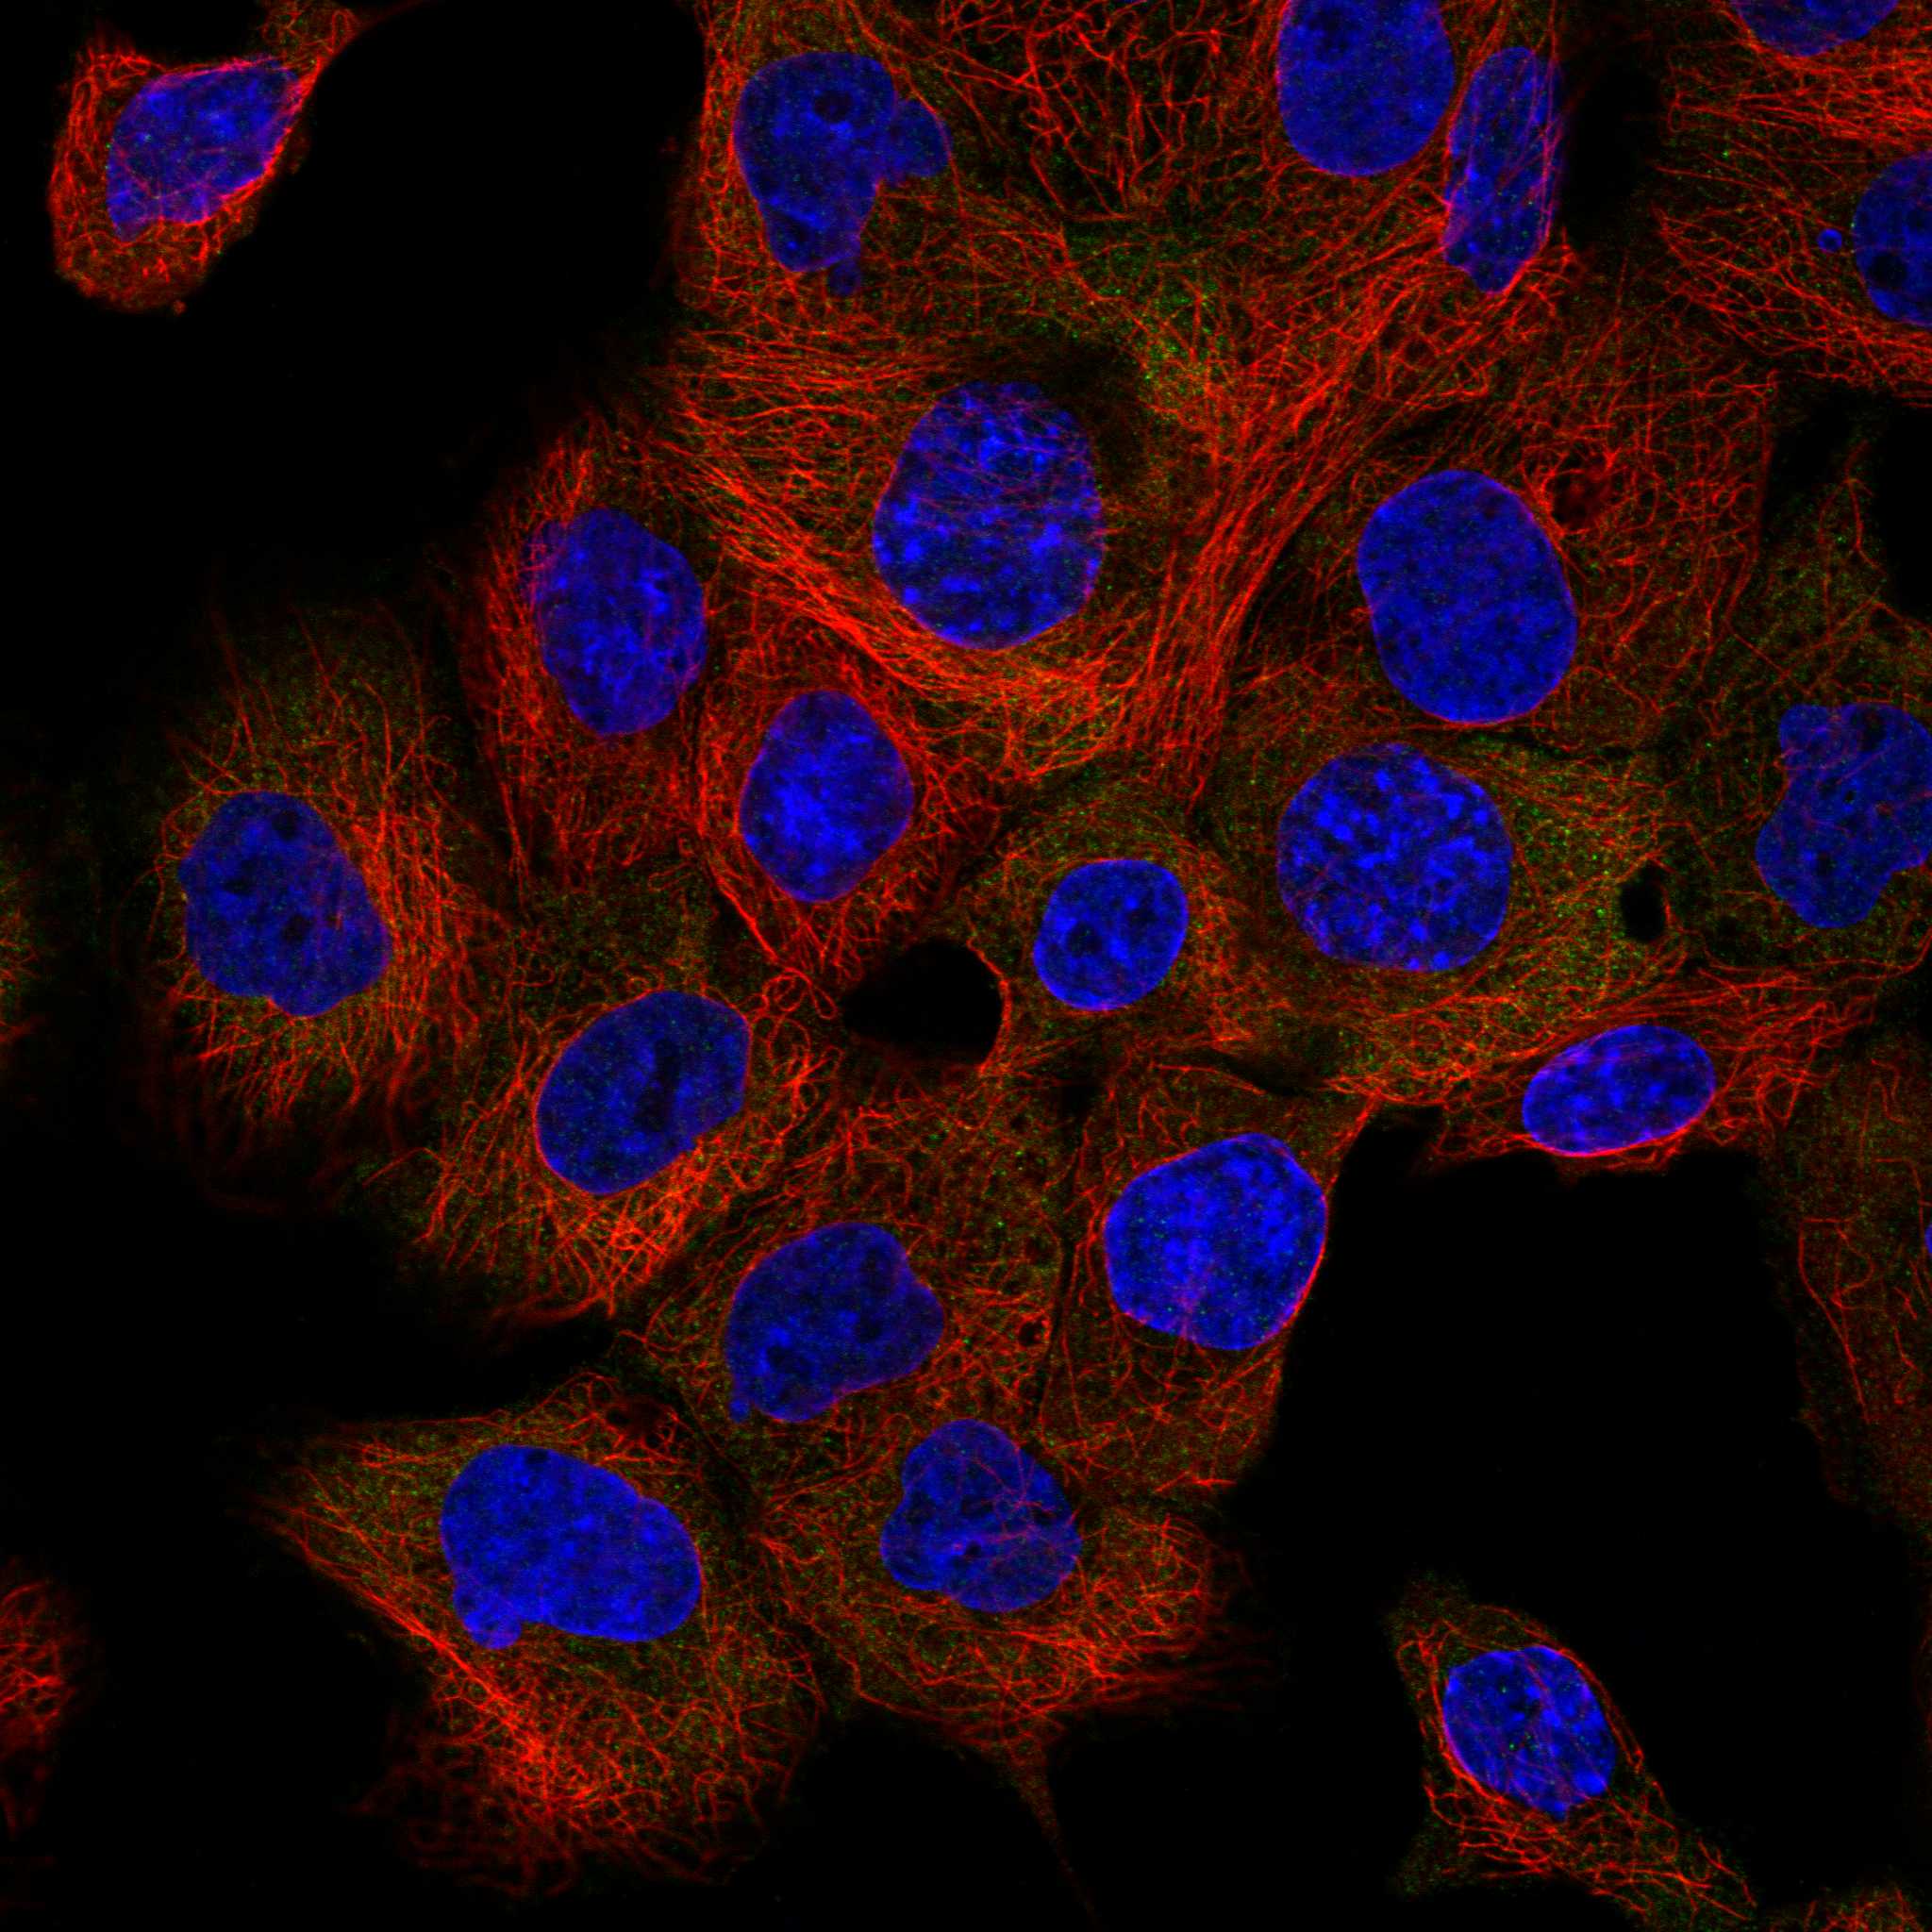
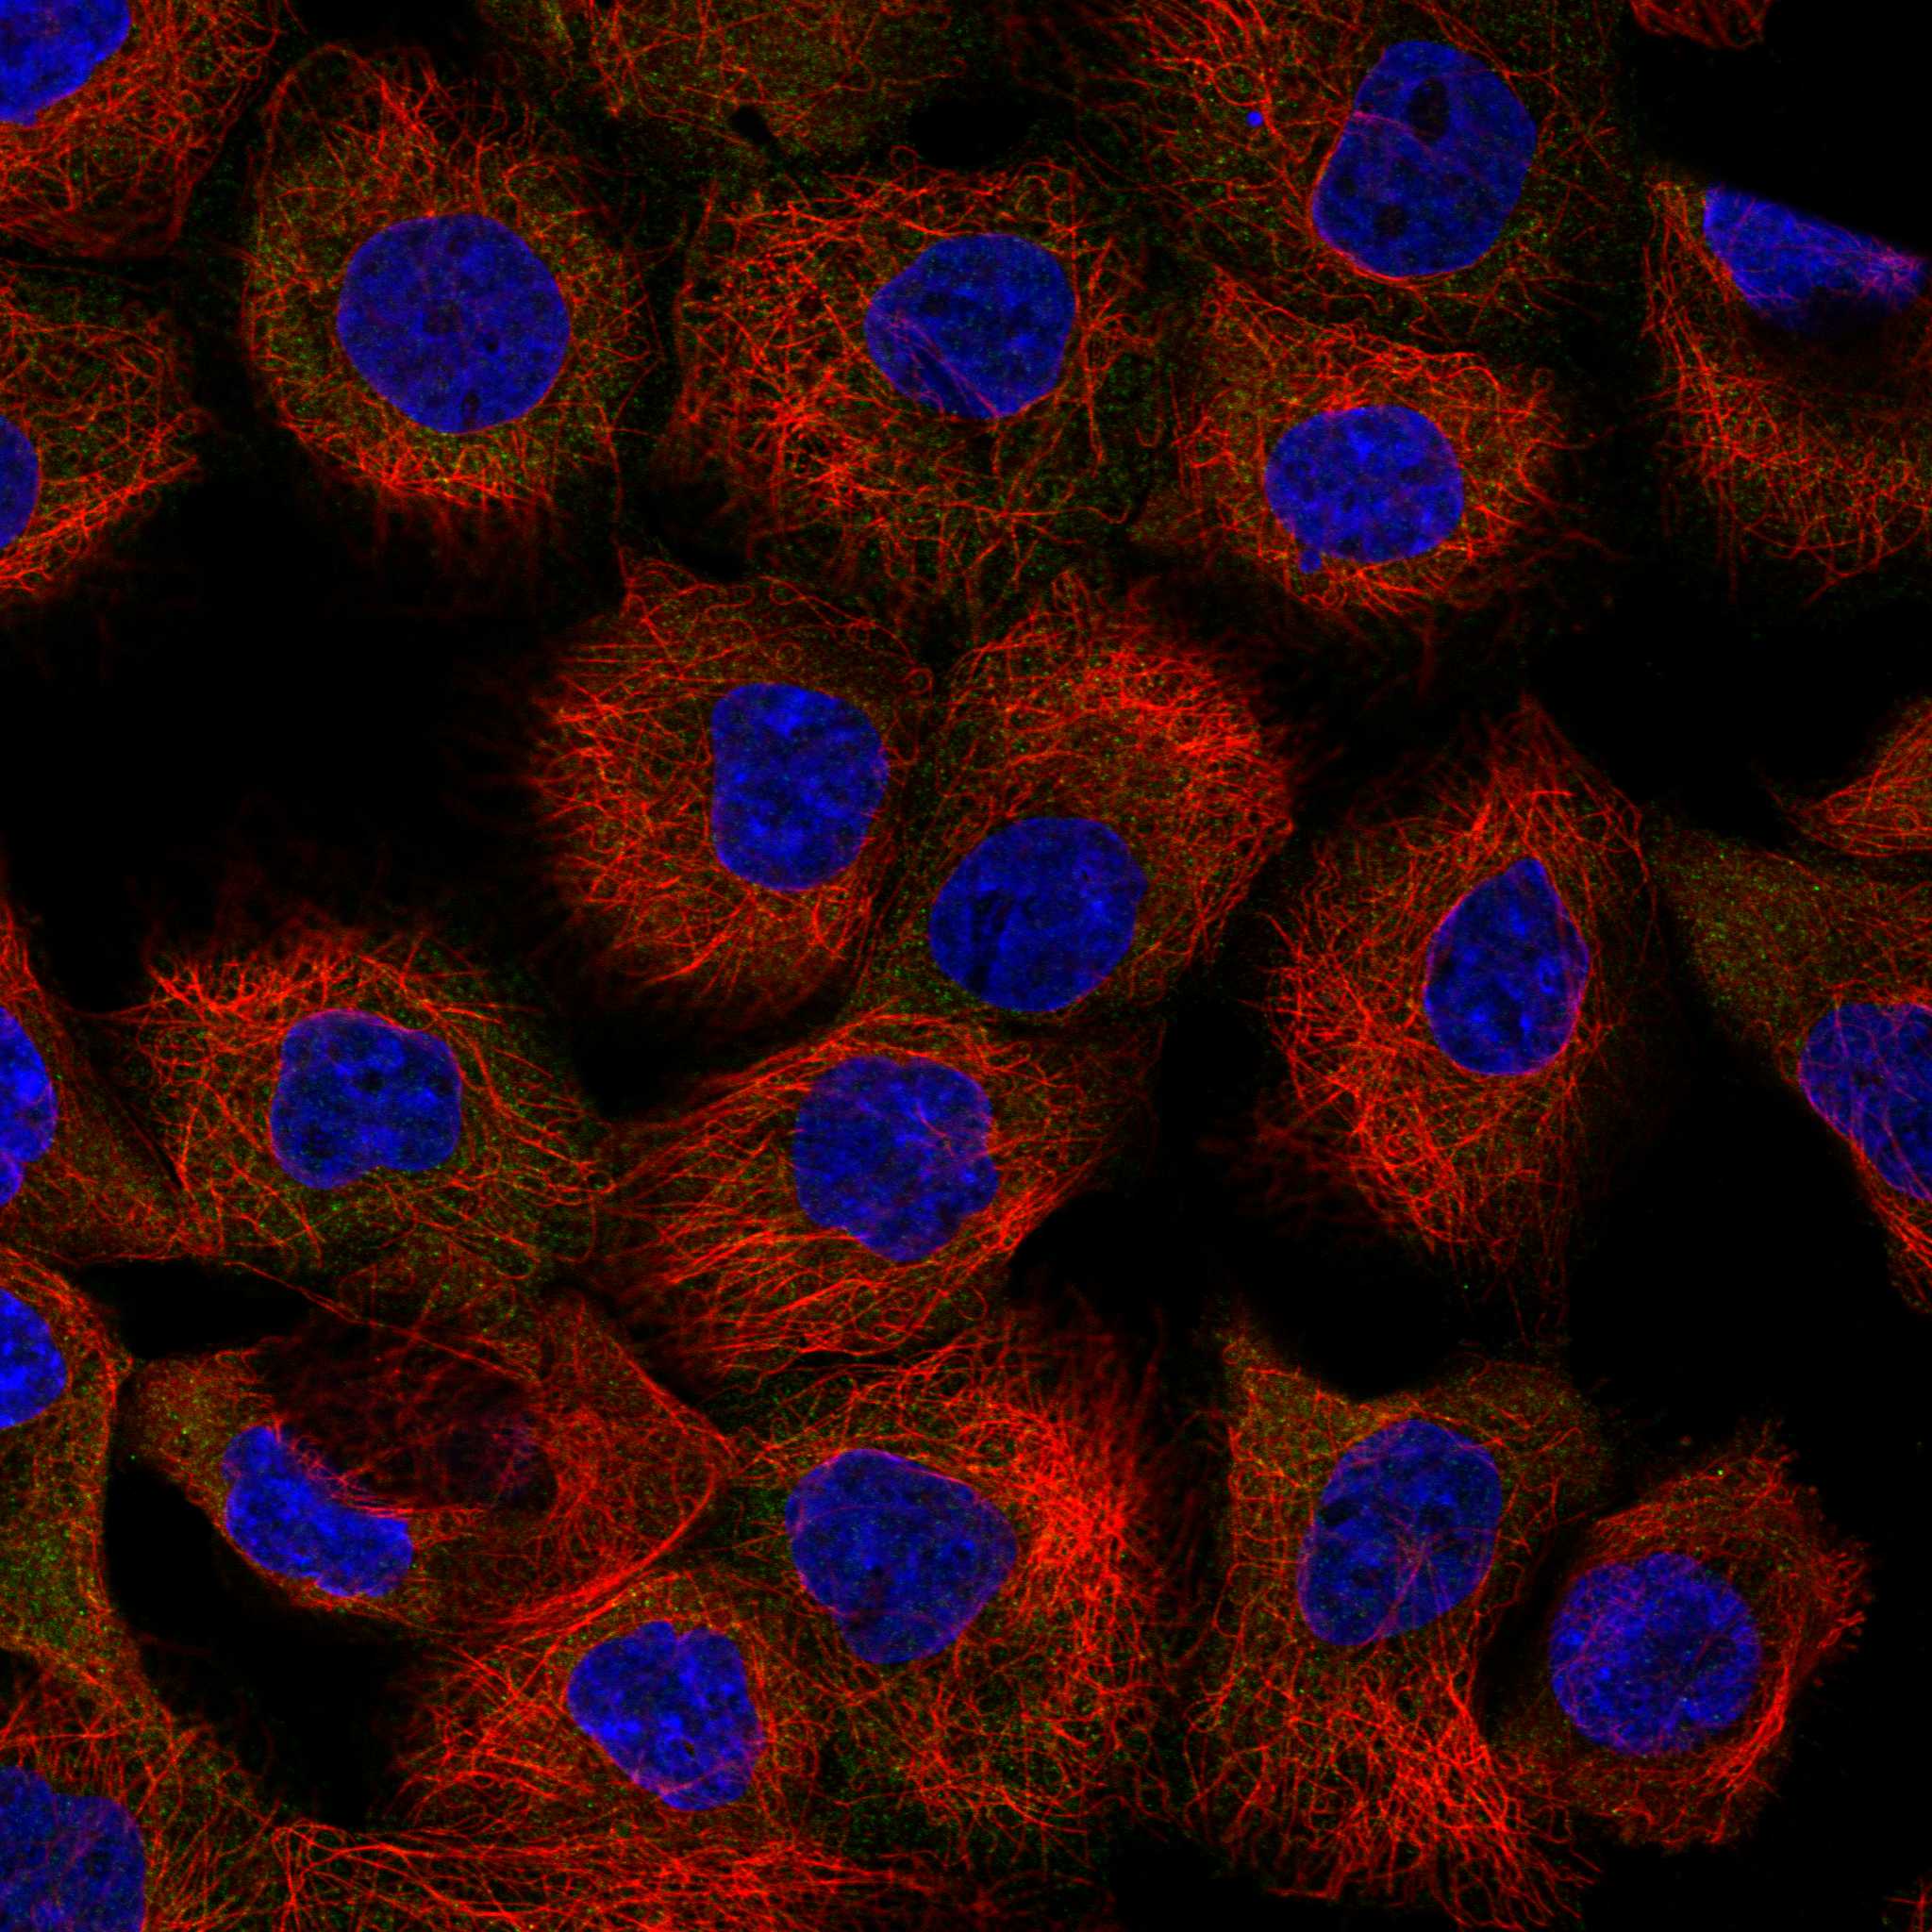
Can I use the same expected pattern for IF/ICC?HPA approves cytosol as the main ICC-IF location; its listed ICC antibody HPA052754 is Supported (HPA: subcellular; HPA: antibody validation). These are ICC-IF observations, not an IHC-P protocol (HPA: antibody validation).Use cytosolic localization as the IF/ICC comparison point and consult the separate IF/ICC guide for that method (HPA: Cytosol approved). Do not transfer IHC-P detection or dilution settings to IF/ICC without method-specific evidence (general IHC/IF practice).

Sample controls for CHMP2B IHC & IF

🧪Run colon first and look for CHMP2B staining in its glandular cells (HPA: Medium in colon glandular cells). Run adipose tissue as a low-signal comparator (HPA: Not detected in adipocytes); on the colon slide, areas without specific staining should show only background chromogen, but do not assume other cell types are true negatives (UniProt Q9UQN3: widely expressed).
Positive control tissue: Appendix (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CHMP2B in A-431, U-251MG, U2OS, NIH 3T3, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls (caption: rabbit primary antibody; standard IHC practice), plus CHMP2B knockout material as a biological negative where available (standard IHC practice). Block endogenous peroxidase and check for nonspecific DAB signal in colon sections (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected M01935 paraffin-section caption does not state a fixative (caption: fixative unreported). The demonstrated IHC procedure uses heat retrieval in EDTA at pH 8.0, followed by primary antibody at 1:50 overnight at 4°C (caption: retrieval and incubation); a retrieval dependency has not been established. ICC/IF images support cytosolic localization, but the supplied evidence does not establish whether frozen sections or IF are easier than paraffin IHC (HPA: cytosol approved; caption: paraffin-section IHC).

HPA tissue IHC evidence for CHMP2B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Colon Glandular cells Medium Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CHMP2B IHC Tips

Troubleshoot CHMP2B staining in paraffin-section chromogenic IHC using the catalog antibody’s documented workflow and compartment-aware controls.

What should I change when CHMP2B staining is weak after antigen retrieval?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet M01935). Check that sections receive consistent heating and cooling, then compare staining with a section processed alongside the documented human colon cancer specimen (datasheet M01935; standard IHC practice). That specimen was stained after 10% goat-serum blocking and 1:50 primary-antibody incubation overnight at 4°C, so changing retrieval and antibody concentration together would obscure the cause of weak signal (datasheet M01935; standard IHC practice). If signal remains weak, trial a longer retrieval interval on matched sections while monitoring tissue damage and background (standard IHC practice).
Could fixation explain variable CHMP2B staining between paraffin sections?
Target-specific sensitivity to fixation is unknown from the supplied evidence (datasheet M01935). The selected image documents a paraffin-embedded human colon cancer section but does not state its fixative, so it cannot establish an optimal fixation condition for CHMP2B (datasheet M01935). Record each specimen’s fixative and fixation duration, then compare matched sections using the same EDTA pH 8.0 retrieval and detection workflow (datasheet M01935; standard IHC practice). Examine morphology alongside signal, since weak staining in a poorly preserved area is difficult to interpret (standard IHC practice). Keep a reference section in each run to distinguish specimen handling from day-to-day staining variation (standard IHC practice).
Is diffuse or punctate cytoplasmic CHMP2B staining expected in IHC?
CHMP2B is annotated in the cytosol and at the late endosome membrane, without a transmembrane segment (UniProt Q9UQN3 localisation and topology). Cytoplasmic staining is therefore compatible with its annotated locations, while small cytoplasmic puncta can be assessed as a possible endosomal pattern rather than assumed to identify individual endosomes (UniProt Q9UQN3 localisation; standard IHC interpretation). HPA describes cytoplasmic expression in selected tissues, but rates its tissue IHC reliability uncertain because antibody staining and RNA expression have low consistency (HPA tissue IHC). Compare the pattern with a negative reagent control and a second validated marker before assigning puncta to an organelle (standard IHC practice). Strong isolated nuclear staining warrants particular scrutiny because the supplied localisation evidence does not identify the nucleus as a main site (UniProt Q9UQN3 localisation; HPA subcellular).
How can isoforms or epitope accessibility affect CHMP2B IHC?
CHMP2B has 2 annotated isoforms and reported modifications at residues 2 and 199 (UniProt Q9UQN3 isoforms and modified residues). The supplied caption does not map the M01935 epitope, so its ability to detect both isoforms or a modified form cannot be established here (datasheet M01935; UniProt Q9UQN3). If specimens disagree, compare matched sections under the same EDTA pH 8.0 retrieval conditions before attributing the difference to an isoform (datasheet M01935; standard IHC practice). An independently validated antibody with a disclosed, nonoverlapping epitope can help investigate that possibility, provided its own paraffin-section performance is established (standard IHC practice). Record antibody identity and retrieval conditions with every comparison (standard IHC practice).
How should I investigate CHMP2B localisation with multiplex IF?
Use multiplex IF as a separate localisation check and pair CHMP2B with a marker identifying the expected cell population, such as a glandular epithelial marker when examining colon glands (HPA tissue IHC: medium in colon glandular cells; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a far-red channel if the tissue has substantial short-wavelength autofluorescence (standard IF practice). CHMP2B is cytosolic and associated with the late endosome membrane, with no transmembrane segment; the antibody’s epitope side is not supplied (UniProt Q9UQN3 localisation and topology; datasheet M01935). Test mild permeabilisation against an otherwise matched condition to allow access to intracellular epitopes without assuming which membrane face this antibody recognises (standard IF practice). Include single-stain controls to assess bleed-through (standard IF practice).
What causes widespread DAB background in CHMP2B tissue sections?
First inspect a section without primary antibody to assess detection-system background independently of CHMP2B binding (standard IHC practice). The documented workflow uses a peroxidase-conjugated secondary antibody and DAB, while a peroxidase block is a general chromogenic IHC step rather than CHMP2B-specific evidence (datasheet M01935; standard IHC practice). Check blocking, washes, and DAB development time on matched sections; the caption reports 10% goat serum, 1:50 primary antibody overnight at 4°C, and secondary incubation for 30 minutes at 37°C (datasheet M01935). If background rises with longer development, shorten the chromogen exposure consistently across the comparison set (standard IHC practice).
How should I quantify CHMP2B staining across IHC specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, then apply the same thresholds and imaging conditions to every section (standard IHC practice). For cytoplasmic CHMP2B, record an H-score from intensity and percentage of positive cells, or report percentage positive cells with intensity categories when that is easier to reproduce (UniProt Q9UQN3 localisation; standard IHC practice). For discrete positive cells, report density per mm² of evaluable tissue and normalise counts to that area, excluding folds, necrosis, and tissue loss (standard IHC practice). Compare like cell populations across specimens because HPA reports medium staining in colon glandular cells but low staining in lung macrophages (HPA tissue IHC). Report background-control results with the scores (standard IHC practice).
How can I distinguish true CHMP2B signal from staining artefacts?
Assess whether staining lies in a plausible cytoplasmic compartment: CHMP2B is annotated in cytosol and at the late endosome membrane, and HPA approves a cytosolic subcellular location (UniProt Q9UQN3 localisation; HPA subcellular). Confirm which cells stain with morphology or a companion cell marker rather than assigning every brown cell to the intended population (standard IHC practice). Discount section-edge intensification, necrotic regions, and signal reproduced in a no-primary control; endogenous peroxidase can contribute to a DAB reaction (standard IHC practice). Interpret apparent tissue differences cautiously because HPA rates its CHMP2B tissue IHC reliability uncertain owing to low agreement between antibody staining and RNA expression (HPA tissue IHC). Recheck unexpected nuclear-dominant patterns with an independent control (UniProt Q9UQN3 localisation; standard IHC practice).
Boster reagents

Best CHMP2B / Charged multivesicular body protein 2b IHC Antibodies

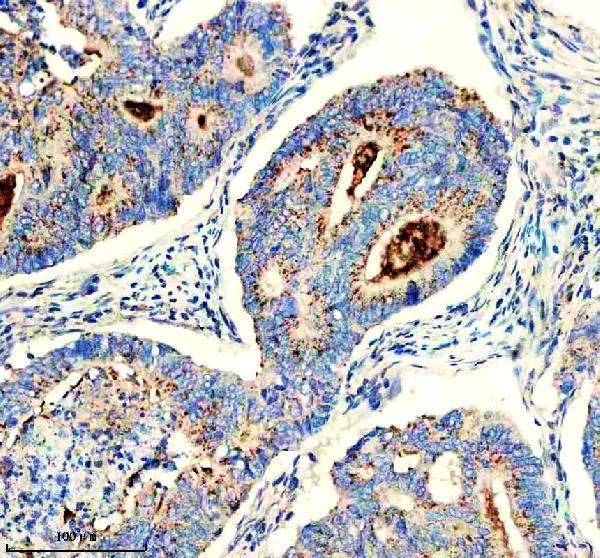
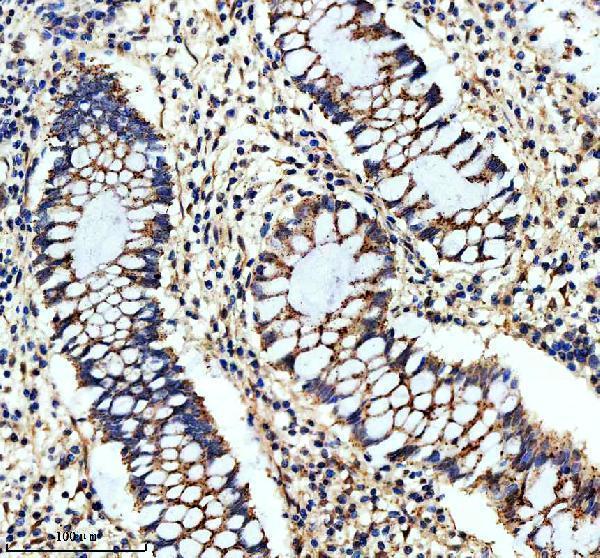
M01935 has human colon and colon cancer paraffin-section IHC images (M01935 IHC captions); its catalog also lists IF/ICC and human, mouse, and rat reactivity (catalog: M01935).

Real IHC data IHC analysis of CHMP2B using anti-CHMP2B antibody (M01935). CHMP2B was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-CHMP2B Antibody (M01935) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CHMP2B Rabbit Monoclonal Antibody
Cat # M01935

M01935 will render with its human colon cancer paraffin-section IHC figure (M01935 IHC caption). A second caption documents human colon paraffin-section IHC, while the catalog lists IF/ICC without an IF image (M01935 IHC captions; catalog: M01935 applications and image alts).

Which to pick: Choose M01935 for tissue IHC: this rabbit monoclonal has human colon and colon cancer paraffin-section captions; neither reports the fixative (catalog: M01935 host/clone; M01935 IHC captions). Choose M01935 for IF/ICC because those applications are listed, although no IF image is supplied (catalog: M01935 applications and image alts). For cross-species work, both M01935 and A01935-1 list human, mouse, and rat reactivity; M01935 also lists IF/ICC, while A01935-1 lists IHC without a supplied IHC image (catalog: M01935 and A01935-1 reactivity, applications, and image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UQN3 (CHM2B_HUMAN, Charged multivesicular body protein 2b).
  2. Human Protein Atlas. CHMP2B tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. CHMP2B subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. CHMP2B antibody validation summary (2 antibodies).
  5. Granulovacuolar degenerations appear in relation to hippocampal phosphorylated tau accumulation in various neurodegenerative disorders. PloS one 2011 — PMC3207829.
  6. Molecular markers for granulovacuolar degeneration are present in rimmed vacuoles. PloS one 2013 — PMC3842945.
  7. Early microgliosis precedes neuronal loss and behavioural impairment in mice with a frontotemporal dementia-causing CHMP2B mutation. Human molecular genetics 2017 — PMC5409096.
  8. Identification of a PANoptosis-related Gene Signature for Predicting the Prognosis, Tumor Microenvironment and Therapy Response in Breast Cancer. Journal of Cancer 2024 — PMC10758028.
  9. PubMed PMID:10810093 — UniProt-cited evidence.
  10. PubMed PMID:11230166 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.