CHUK / Inhibitor of nuclear factor kappa-B kinase subunit alpha · IHC design guide

Design Immunohistochemistry for CHUK

Plan CHUK chromogenic IHC in paraffin sections using the cytoplasmic pattern reported in most cell types (HPA tissue IHC). Interpret nuclear staining in light of CHUK's reported shuttling between cytoplasm and nucleus (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CHUK (IHC for CHUK): expected localisation Cytoplasmic staining in most cell types (HPA tissue IHC), antibody PB9110, validated IHC image, and IHC protocol steps
Printable CHUK IHC protocol sheet — expected localisation Cytoplasmic staining in most cell types (HPA tissue IHC), antibody PB9110, controls and protocol steps. Open the full CHUK IHC guide →

CHUK Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most cell types (HPA tissue IHC)
Staining pattern Most cell types show cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet PB9110)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Nuclear shuttling may change the apparent pattern (UniProt)
Regulation Expression regulation is not specified (UniProt)
Isoform / epitope 0 listed isoforms; one 1–745 chain (UniProt)
Section 1

Recommended CHUK IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet PB9110) with the published CHUK tissue microarray protocol (PMC12647233: IHC methods).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissues; fixative not specified (datasheet PB9110)
FixationImage fixative and duration unreported (datasheet PB9110); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet PB9110)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9110)
Primary antibodyRabbit anti-CHUK, 0.5-1μg/ml (datasheet PB9110)
Primary incubationOvernight at 4 °C (datasheet PB9110)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9110)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCHUK-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most cell types. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate retrieval at pH 6 (datasheet PB9110); the published IHC excerpt gives no retrieval conditions (PMC12647233: IHC methods).
Section 2

What Is the Expected CHUK Staining Pattern?

CHUK should show mainly cytoplasmic staining across many cell types in paraffin-section IHC (HPA tissue IHC: Approved; medium consistency with RNA). Stronger staining is reported in selected epithelial, glandular, hematopoietic and neuronal cells (HPA tissue IHC: High). Nuclear signal can be biologically plausible because CHUK shuttles between cytoplasm and nucleus (UniProt O15111: subcellular location). CHUK has no transmembrane segment, so a membrane-only pattern is unexpected (UniProt O15111: topology).

What am I looking at on my slide?
Cytoplasmic staining in bronchial respiratory epithelium and bone-marrow hematopoietic cells (HPA tissue IHC: High).This matches two reported strong cell populations. Compare staining within identifiable cells, since HPA describes CHUK as cytoplasmic in most cell types (HPA tissue IHC: profile).
Some nuclear staining accompanies a credible cytoplasmic pattern (UniProt O15111: cytoplasm and nucleus).Nuclear CHUK is plausible because it shuttles between compartments; IHC alone does not establish pathway activation (UniProt O15111: subcellular location and function).
Only a crisp plasma-membrane rim or extracellular deposit is visible (UniProt O15111: no transmembrane segment).That distribution conflicts with the reported cytoplasmic IHC profile. Check morphology and control sections before interpreting it as CHUK (HPA tissue IHC: profile; general IHC practice).
Strong staining appears chiefly in adipocytes, soft-tissue fibroblasts or adrenal glandular cells (HPA tissue IHC: Low).These are lower-staining comparators, not proven negatives. An unexpectedly strong pattern raises concern for cross-reactivity or detection background (HPA tissue IHC: Low; general IHC practice).
Diffuse color covers stroma, lumina and cells without a readable intracellular pattern (HPA tissue IHC: cytoplasmic profile).Treat this as background until a cellular pattern emerges with appropriate controls; diffuse color alone cannot identify CHUK-positive cells (general IHC practice).
💡Expected CHUK appearanceCall CHUK positive when identifiable cells show predominantly cytoplasmic staining, potentially strong in the HPA-listed High populations; a membrane-only rim or diffuse deposit is suspect (HPA tissue IHC: profile and High; UniProt O15111: topology).
How each factor affects the staining
Tissue and cell choice (HPA tissue IHC: High and Low).High examples include Purkinje cells, cortical neurons and intestinal glandular cells; adipocytes, soft-tissue fibroblasts and adrenal glandular cells are lower comparators, not negative controls (HPA tissue IHC: High and Low).
Compartment and molecular topology (UniProt O15111: subcellular location and topology).Cytoplasmic and nuclear signal can fit CHUK shuttling. A membrane-restricted result needs scrutiny because CHUK lacks a transmembrane segment (UniProt O15111: topology).
Antibody evidence (HPA antibodies: HPA001402, CAB004240 and CAB018564).All three listed antibodies have Approved IHC status; this should not be described as Enhanced validation or proof that every tissue pattern is specific (HPA antibodies: IHC status; general IHC practice).
Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.The supplied sources do not report how fixation changes CHUK staining. Treat retrieval adjustments as general IHC optimization, not a CHUK-specific requirement (source scope; general IHC practice).
IF/ICC Q: Where is CHUK seen? (HPA subcellular ICC-IF).A: Mainly in nucleoplasm, with additional cytosol signal in the reported ICC-IF observations. That assay-specific pattern does not override the cytoplasmic tissue-IHC profile (HPA subcellular ICC-IF; HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in bronchial respiratory epithelium or bone-marrow hematopoietic cells (HPA tissue IHC: High).A run-level staining failure is possible; HPA High is an observed pattern, not a guarantee for every section (HPA tissue IHC: High; general IHC practice).Inspect tissue preservation and the run controls, then optimize retrieval and catalog-antibody dilution within the IHC workflow (general IHC practice).
Only nuclei stain in tissue IHC, with no discernible cytoplasmic signal (HPA tissue IHC: cytoplasmic profile).Nuclear localization is possible, but an exclusively nuclear tissue pattern differs from HPA's dominant IHC observation (UniProt O15111: nucleus; HPA tissue IHC: profile).Recheck cell boundaries and counterstain, then compare a known High tissue and staining controls before assigning specificity (HPA tissue IHC: High; general IHC practice).
Strong color persists outside cells or in the negative detection control (general IHC practice).Nonspecific reagent binding or endogenous detection activity can produce color without a CHUK-specific pattern (general IHC practice).Review blocking and detection controls, then reduce background before scoring intracellular staining (general IHC practice).
Adipocytes or soft-tissue fibroblasts dominate the positive call (HPA tissue IHC: Low).Their reported staining is Low, so intense signal in these cells warrants scrutiny; Low does not mean absent (HPA tissue IHC: Low).Compare morphology and compartment with a reported High population, and check antibody and detection controls (HPA tissue IHC: High and Low; general IHC practice).
A membrane-only outline is reproducible (UniProt O15111: no transmembrane segment).The pattern conflicts with CHUK topology and the HPA cytoplasmic tissue profile (UniProt O15111: topology; HPA tissue IHC: profile).Examine edge effects and control sections; withhold a CHUK-positive call until intracellular staining is supported (general IHC practice).
IHC cytoplasm and ICC-IF nucleoplasm appear discordant (HPA tissue IHC; HPA subcellular ICC-IF).The supplied datasets report different dominant compartments in different assays; CHUK can shuttle between both (HPA tissue IHC; HPA subcellular ICC-IF; UniProt O15111: subcellular location).Score each assay against its own reported pattern and controls; avoid treating the ICC-IF result as an IHC protocol or scoring rule (HPA tissue IHC; HPA subcellular ICC-IF; general IHC practice).

Sample controls for CHUK IHC & IF

🧪Start with bone marrow; hematopoietic cells should stain (HPA: High in bone marrow hematopoietic cells). HPA detects CHUK in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat any unstained, morphologically intact cells on the positive slide only as internal comparators, not validated CHUK-negative cells (HPA: no negative tissue rows).
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: None in HPA: CHUK is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CHUK in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section, a host- and isotype-matched nonimmune immunoglobulin control, and a CHUK-knockout sample or validated peptide block as a biological specificity control (IHC control practice; selected caption: rabbit anti-IKKA). For bone marrow, quench endogenous peroxidase and check background before interpreting DAB staining (IHC control practice; HPA: bone marrow positive tissue).
⚠️Feasibility: The selected PB9110 paraffin-section caption does not state a fixative, and no target-specific fixation window or fixation effect is reported (selected tissue-IHC caption). That caption uses heat retrieval in citrate buffer at pH 6 for 20 minutes, but does not establish that retrieval is required for every specimen (selected tissue-IHC caption). HPA has ICC-IF images in A-431, U-251MG and U2OS, but the supplied evidence does not establish that IF or frozen sections are easier; bone marrow endogenous peroxidase can complicate chromogenic interpretation (HPA: ICC-IF cell lines; IHC control practice).

HPA tissue IHC evidence for CHUK

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CHUK is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CHUK IHC Tips

Troubleshoot CHUK staining in paraffin section IHC using the PB9110 tissue image and compartment patterns as reference points.

Which retrieval conditions should I start with for CHUK in paraffin sections?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet PB9110). That is the retrieval used for the selected paraffin section image, followed by 1 μg/ml primary antibody overnight at 4°C (datasheet PB9110). If staining is weak, compare a longer citrate heating interval or an alternative retrieval buffer on matched sections, changing one condition at a time (general IHC practice). Keep detection and exposure to DAB consistent across that comparison, and judge improvement in intact cells rather than section edges or damaged areas (general IHC practice).
Could fixation explain weak or uneven CHUK staining?
CHUK-specific fixation sensitivity is unknown from the supplied evidence; the selected tissue image identifies a paraffin section but does not state its fixative (datasheet PB9110). Record fixative, fixation duration and section age before comparing cases, because those variables can alter epitope access in paraffin IHC (general IHC practice). For a controlled pilot, process matched specimens with 10% neutral buffered formalin for 6 and 24 hours, then apply identical citrate retrieval and detection (general IHC practice). Interpret any difference as a result of that local comparison, without assigning it to a known CHUK-specific fixation effect.
How should I assess cytoplasmic and nuclear CHUK staining?
Score cytoplasm and nuclei separately: CHUK shuttles between both compartments (UniProt O15111: subcellular location). Predominantly cytoplasmic tissue staining is consistent with the reported IHC profile, while supported ICC/IF localisation includes nucleoplasm and cytosol (HPA: tissue IHC profile; HPA: subcellular summary). Use a hematoxylin counterstain and compare intact cells at the same magnification before calling a nuclear signal (general IHC practice). If nuclear staining appears only in crushed regions or section margins, review retrieval and DAB development on an adjacent section before interpreting it as redistribution (general IHC practice).
How can epitope biology affect my CHUK IHC result?
Do not attribute contrasting patterns to established CHUK isoforms: none are listed in the supplied record (UniProt O15111: isoforms 0). The protein has no transmembrane segment, so interpret compartment staining without a membrane sidedness model (UniProt O15111: topology). Its kinase domain spans residues 15–302, and reported modifications include Thr23, Ser176, Thr179 and Ser180 (UniProt O15111: domains and modified residues). Because the PB9110 epitope is unspecified here, test retrieval or staining changes empirically; staining alone cannot establish whether a modification altered antibody binding (datasheet PB9110: epitope not stated; general IHC practice).
How should I follow up an IHC pattern with CHUK immunofluorescence?
Treat IF/ICC as a separate assay: the supplied PB9110 image documents chromogenic paraffin section IHC, while HPA reports supported nucleoplasmic and cytosolic ICC/IF localisation (datasheet PB9110; HPA: subcellular summary). Multiplex CHUK with a marker identifying the expected cell type, such as a respiratory epithelial marker when following up bronchus staining (HPA: High in bronchus respiratory epithelial cells; general IF practice). Choose a fluorophore channel with low specimen autofluorescence and compare unstained and secondary-only controls (general IF practice). Because CHUK has no transmembrane segment, optimise a mild permeabilisation pilot, such as 0.1% Triton X-100 for 5 minutes, to access intracellular epitopes (UniProt O15111: topology; general IF practice).
What should I check when CHUK DAB staining looks diffuse?
First compare no-primary and secondary-only controls to separate primary-dependent staining from detection background (general IHC practice). The selected image used 10% goat serum blocking, a biotinylated goat anti-rabbit secondary, an avidin–biotin detection complex and DAB (datasheet PB9110). In that workflow, include a peroxidase block and check endogenous biotin with an appropriate control when diffuse colour persists (general IHC practice). Titrate primary antibody around the documented 1 μg/ml condition and shorten DAB development on matched sections; assess background in tissue-free areas, damaged edges and intact cells separately (datasheet PB9110; general IHC practice).
How should I quantify CHUK staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define cell type and compartment before scoring, because CHUK can occupy cytoplasm and nucleus (UniProt O15111: subcellular location). For each compartment, record percentage of positive cells and intensity grades 0–3, then calculate an H-score from 0–300 using the same thresholds across slides (general IHC practice). If counting positive cells per mm², normalise to analysed viable tissue area and report cell type or region separately (general IHC practice). Keep section thickness, retrieval, DAB development and image settings matched; exclude necrotic and folded areas and record the exclusion rule (general IHC practice).
When is a CHUK-positive IHC signal convincing?
A convincing result stains intact cells in a plausible compartment and recurs across comparable regions, with little signal in no-primary controls (general IHC practice; UniProt O15111: cytoplasm and nucleus). For tissue context, HPA reports high staining in bronchus respiratory epithelial cells and bone marrow hematopoietic cells, but its IHC reliability is Approved with medium RNA–staining consistency (HPA: tissue IHC). Treat isolated nuclear colour at edges, necrotic zones or folds cautiously; check endogenous peroxidase and detection controls before calling those regions positive (general IHC practice). Finally, CHUK abundance or nuclear staining alone does not measure kinase activity or NF-κB pathway activation (UniProt O15111: function; general IHC practice).
Boster reagents

Best CHUK / Inhibitor of nuclear factor kappa-B kinase subunit alpha IHC Antibodies

Anti-CHUK antibodies have IHC images from human lung cancer, mouse kidney, and rat kidney, plus IF/ICC images from Jurkat cells (catalog image captions); listed reactivity covers human, mouse, and rat (catalog reactivity).

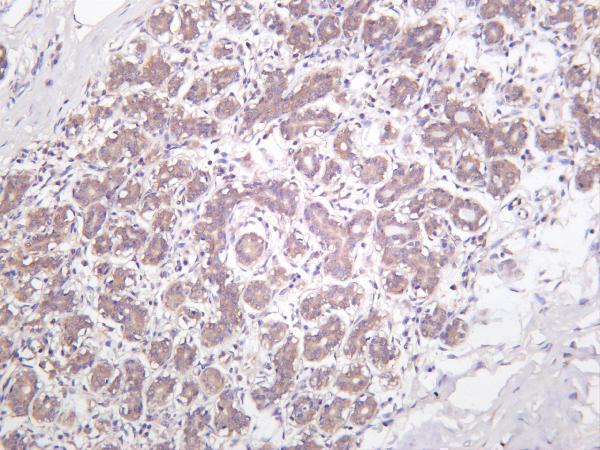
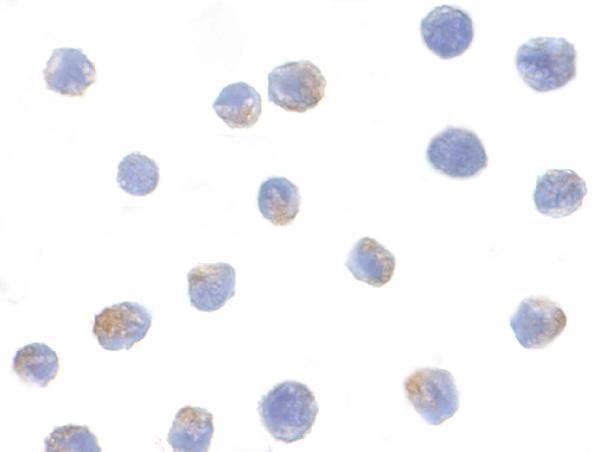
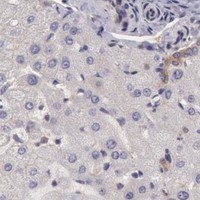
Real IHC data IHC analysis of IKKA using anti-IKKA antibody (PB9110). IKKA was detected in paraffin-embedded section of human lung cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-IKKA Antibody (PB9110) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-IKK alpha/CHUK Antibody ®
Cat # PB9110
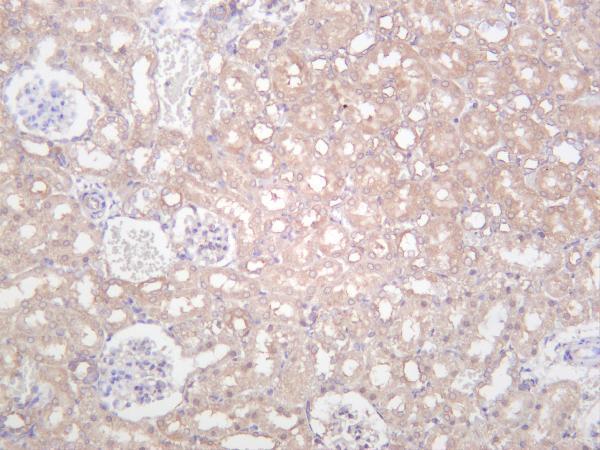
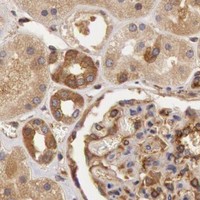
Real IHC data Rat kidney was stained with anti-IKK α rabbit antibody
Anti-IKK α Rabbit Monoclonal Antibody
Cat # M01918-4
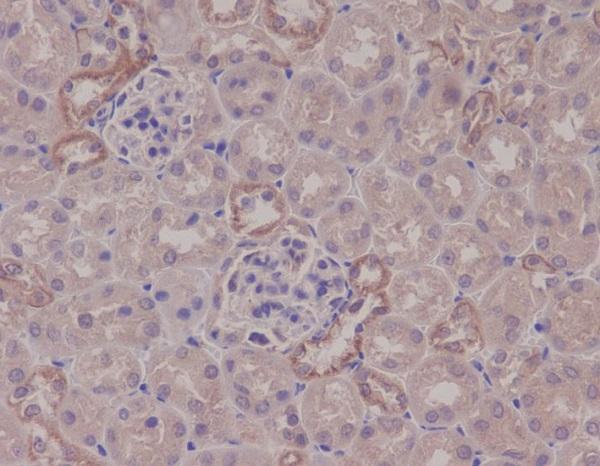
Real IHC data Immunohistochemical analysis of paraffin-embedded mouse kidney, using IKK alpha Antibody.
Anti-IKK alpha CHUK Rabbit Monoclonal Antibody
Cat # M01918-1
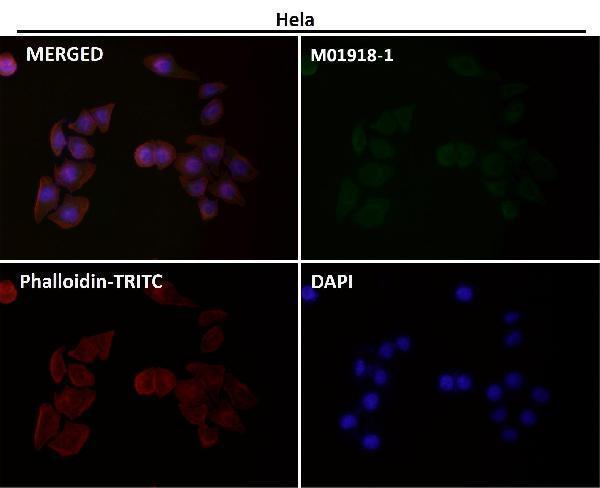
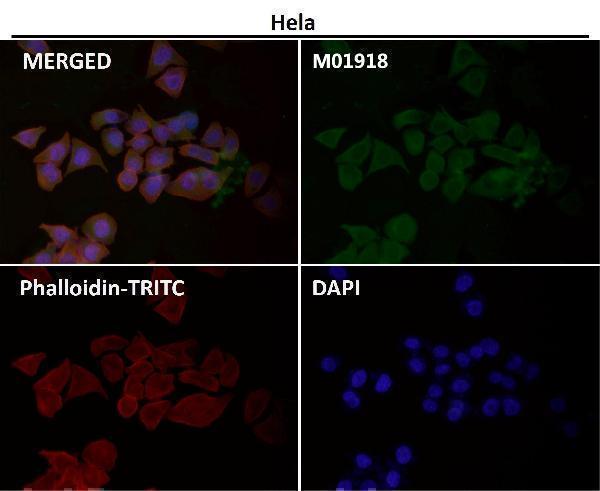
Real IF data Immunocytochemistry of IKK alpha in Jurkat cells with IKK alpha antibody at 1μg/mL.
Anti-IKK alpha CHUK Antibody
Cat # A01918
Real IF data Immunofluorescent analysis using the Antibody at 1:50 dilution.
Anti-IKK alpha+beta CHUK Rabbit Monoclonal Antibody
Cat # M01918

PB9110 shows IHC in human lung cancer paraffin sections (PB9110 image caption); M01918-1 shows IHC in mouse kidney paraffin sections (M01918-1 image caption); M01918-4 shows IHC in rat kidney (M01918-4 image caption). A01918 shows ICC in Jurkat cells (A01918 image caption); M01918 has an IF image with no sample identified (M01918 image caption).

Which to pick: For human tissue IHC, choose PB9110, which has a human paraffin section image and an IHC dilution of 0.5–1 μg/mL (PB9110 image caption; catalog dilution); its fixative is unreported (PB9110 image caption). For IF/ICC, choose A01918 for human Jurkat cells or M01918 for listed human, mouse, and rat reactivity; M01918 recognizes IKK alpha and beta (A01918 image caption; M01918 catalog applications, reactivity, and title). For tissue IHC across listed human, mouse, and rat reactivity, choose monoclonal M01918-4, whose IHC images include rat, mouse, and human tissues; the rat kidney caption does not report processing or fixative (M01918-4 catalog reactivity and description; M01918-4 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O15111 (IKKA_HUMAN, Inhibitor of nuclear factor kappa-B kinase subunit alpha).
  2. Human Protein Atlas. CHUK tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CHUK subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. CHUK antibody validation summary (3 antibodies).
  5. Honokiol inhibits gastric cancer via tumor microenvironment modulation: a bioinformatics and single-cell analysis. Scientific reports 2025 — PMC12647233.
  6. Exome Sequencing of Oral Squamous Cell Carcinoma Reveals Molecular Subgroups and Novel Therapeutic Opportunities. Theranostics 2017 — PMC5399578.
  7. PubMed PMID:9244310 — UniProt-cited evidence.
  8. PubMed PMID:9252186 — UniProt-cited evidence.
  9. PubMed PMID:9346484 — UniProt-cited evidence.