CISD2 / CDGSH iron-sulfur domain-containing protein 2 · IHC design guide

Design Immunohistochemistry for CISD2

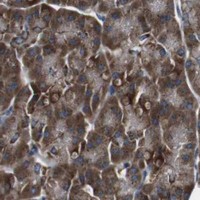
Plan chromogenic CISD2 staining in paraffin sections using the granular cytoplasmic tissue pattern as a reference (HPA tissue IHC). Compare stained glandular cells with adipocytes, where staining was not detected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CISD2 (IHC for CISD2): expected localisation Granular cytoplasm (HPA tissue IHC); ER and outer mitochondrial membrane (UniProt), antibody A06387-1, validated IHC image, and IHC protocol steps
Printable CISD2 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); ER and outer mitochondrial membrane (UniProt), antibody A06387-1, controls and protocol steps. Open the full CISD2 IHC guide →

CISD2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); ER and outer mitochondrial membrane (UniProt)
Staining pattern Granular cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06387-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Adipocytes and vaginal squamous cells: not detected (HPA tissue IHC)
Regulation Stimulus-dependent regulation unreported (UniProt)
Isoform / epitope No annotated isoforms; mature chain spans 2–135 (UniProt)
Section 1

Recommended CISD2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A06387-1) is accompanied by published CISD2 staining protocols for lung, laryngeal, pancreatic and liver cancer tissue (PMC11385248; PMC5008395; PMC7841247; PMC8415543).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A06387-1)
FixationImage fixative and duration unreported (datasheet A06387-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06387-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06387-1)
Primary antibodyRabbit anti-CISD2, 2-5μg/ml (datasheet A06387-1)
Primary incubationOvernight at 4 °C (datasheet A06387-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A06387-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCISD2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Granular cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A06387-1). Published alternatives include heated citrate (PMC11385248; PMC8415543).
Section 2

What Is the Expected CISD2 Staining Pattern?

CISD2 is a membrane protein of the endoplasmic reticulum (ER) and mitochondrial outer membrane, with a transmembrane segment at residues 38–60 (UniProt Q8N5K1 topology). In paraffin IHC, expect granular cytoplasmic staining in many cell types (HPA tissue IHC: profile). HPA rates its tissue staining Approved, with medium consistency against RNA expression and external verification pending (HPA tissue IHC: reliability).

What am I looking at on my slide?
Granular cytoplasmic staining in bronchial respiratory epithelium or appendix glandular cells.This matches the HPA profile; both named cell populations have medium staining (HPA tissue IHC: bronchus, appendix). Assess signal within the named cells and its distribution, rather than treating colour anywhere in the section as a positive result (general IHC interpretation).
Predominantly nuclear staining, with little granular cytoplasmic signal.The predominant compartment conflicts with the HPA tissue pattern and the annotated membrane locations (HPA tissue IHC: profile; UniProt Q8N5K1 subcellular location). Review controls and detection conditions before calling it CISD2; an IHC section alone cannot distinguish ER from nearby mitochondrial membranes (general IHC interpretation).
Strong staining in adipocytes or vaginal squamous epithelial cells.HPA reports CISD2 as not detected in those cell populations (HPA tissue IHC: adipose tissue, vagina). This discrepancy raises concern for nonspecific antibody binding or endogenous detection activity (general IHC practice); it does not establish that every individual cell must lack CISD2.
Broad, smooth colour across cells, stroma or the whole section.A diffuse deposit obscures the expected granular cytoplasmic pattern (HPA tissue IHC: profile). Consider nonspecific binding, residual detection activity or excess chromogen development (general IHC practice). Reassess localisation only after the background is reduced; diffuse colour alone cannot confirm CISD2.
No staining in a section expected to provide a positive reference.Bronchial respiratory epithelium and appendix glandular cells are reported at medium intensity (HPA tissue IHC: bronchus, appendix). If a matched reference also lacks signal, check the IHC workflow before interpreting the study section as negative (general IHC practice). HPA approval does not guarantee staining in every preparation (HPA tissue IHC: reliability).
💡Expected CISD2 appearanceCall a positive result when named cells show discernible granular cytoplasmic staining, typically medium in the cited bronchial or appendix examples; predominantly nuclear or uniform background colour is discordant (HPA tissue IHC: profile, bronchus, appendix; UniProt Q8N5K1 subcellular location).
How each factor affects the staining
Membrane localisation and topologyCISD2 has one transmembrane segment at residues 38–60, with residues 2–37 lumenal and 61–135 cytoplasmic (UniProt Q8N5K1 topology). These annotations guide compartment interpretation; the supplied record does not locate this antibody's epitope.
ER versus mitochondrial interpretationUniProt lists ER and mitochondrial outer membrane; its note reports predominantly ER localisation in one study and predominantly mitochondrial outer membrane in mouse experiments (UniProt Q8N5K1 subcellular location). HPA ICC-IF supports ER localisation (HPA subcellular: supported).
Tissue pattern and validationHPA describes granular cytoplasmic expression in most tissues and low RNA tissue specificity (HPA tissue IHC: profile, RNA specificity). Its IHC result is Approved, with medium RNA concordance and external verification pending (HPA tissue IHC: reliability); HPA015914 is IHC Approved (HPA antibodies).
Processing and modification annotationsUniProt lists no signal peptide, propeptide, annotated glycosylation sites or modified residues for CISD2 (UniProt Q8N5K1 processing, glycosylation, modified residues). Those entries provide no basis for predicting a target-specific fixation or antigen-retrieval effect.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive reference and study section both show no signal.Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.Confirm that the IHC-validated antibody, retrieval conditions and detection reagents were applied as intended; include a documented positive cell population in the next run (general IHC practice; HPA tissue IHC: bronchus, appendix).
Signal is weak in a tissue expected to stain.HPA reports medium staining in its bronchial and appendix examples, but intensity can vary across preparations (HPA tissue IHC: bronchus, appendix; general IHC practice).Compare the expected cell population with a matched positive reference, then review antigen retrieval, primary antibody conditions and chromogen development within the validated IHC workflow (general IHC practice).
Background makes the granular pattern hard to score.Nonspecific binding, endogenous detection activity or excessive chromogen development can add diffuse colour (general IHC practice).Check a no-primary control and the detection blocking step; adjust blocking, washing or development according to the assay controls, then rescore cytoplasmic granules (general IHC practice; HPA tissue IHC: profile).
Nuclear staining dominates.That distribution conflicts with HPA's granular cytoplasmic IHC profile and UniProt's membrane locations (HPA tissue IHC: profile; UniProt Q8N5K1 subcellular location).Review the no-primary control and antibody specificity before reporting a nuclear CISD2 pattern; use the documented cytoplasmic reference for comparison (general IHC practice; HPA tissue IHC: profile).
Adipocytes or vaginal squamous cells stain strongly.The result differs from HPA's not detected observations; nonspecific binding or endogenous detection activity is possible (HPA tissue IHC: adipose tissue, vagina; general IHC practice).Inspect matched negative and no-primary controls, then compare the suspect cells with an HPA-reported positive population before assigning CISD2 positivity (general IHC practice; HPA tissue IHC: bronchus, appendix).
IF/ICC: what localisation should be expected?HPA supports ER localisation in ICC-IF; UniProt also annotates the mitochondrial outer membrane (HPA subcellular: supported; UniProt Q8N5K1 subcellular location).Assess whether fluorescence follows an ER-associated distribution and document any divergent compartment; interpret the IF result within its separate guide (HPA subcellular: supported; general IF interpretation).

Sample controls for CISD2 IHC & IF

🧪Run adrenal gland first; its glandular cells should stain (HPA: Medium in adrenal gland glandular cells). Use adipose tissue adipocytes as the negative tissue comparator (HPA: Not detected in adipocytes); unstained non-glandular cells on the adrenal slide can indicate background, but are not a validated CISD2-negative population.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CISD2 in A-431, U-251MG, U2OS, with annotated localisation: Endoplasmic reticulum (supported) (HPA subcellular).
Technical controls: Include no-primary or secondary-only and host-matched rabbit IgG isotype controls, plus CISD2-knockout tissue or a validated peptide-block control (standard IHC practice; selected caption: rabbit primary antibody). For DAB scoring in adrenal tissue, check endogenous peroxidase and biotin, and distinguish intrinsic pigment from specific staining (standard chromogenic IHC practice; selected caption: biotin-based detection with DAB).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected A06387-1 paraffin-section caption does not report a fixative (selected caption: fixative unreported). Retrieval dependence is unestablished, although that caption uses heat-mediated EDTA at pH 8.0 (selected caption: EDTA retrieval). Frozen sections and IF are not shown to be easier in the supplied evidence; ICC-IF supports endoplasmic reticulum localization, while adrenal pigment and endogenous peroxidase warrant checks during chromogenic scoring (HPA: supported endoplasmic reticulum location; standard IHC practice).

HPA tissue IHC evidence for CISD2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Glial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CISD2 IHC Tips

Troubleshoot CISD2 staining in paraffin sections by checking retrieval, cellular pattern, controls and scoring before interpreting chromogenic signal.

Which retrieval condition should I try first for weak CISD2 staining?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A06387-1). This condition accompanied CISD2 detection in a human lung cancer section, although the caption does not report a fixative (caption A06387-1). Keep section thickness, heating, cooling and detection conditions matched when comparing retrieval runs, so a staining difference is interpretable (standard IHC practice). If signal remains weak, compare a citrate buffer at pH 6.0 as a fallback while retaining the EDTA condition as the reference (standard IHC practice). Judge improvement by cellular pattern as well as intensity, since stronger diffuse staining alone does not establish specificity (HPA tissue IHC; standard IHC practice).
Could fixation explain variable CISD2 staining across paraffin blocks?
Target-specific fixation sensitivity for CISD2 is unknown from the supplied evidence, and the selected tissue-IHC caption does not state its fixative (caption A06387-1). Record the fixative and processing history for each block before comparing signal across specimens (standard IHC practice). Compare sections with matched processing, retrieval and detection conditions to assess whether variation follows preparation rather than the specimen (standard IHC practice). If archived blocks differ in fixation history, include a consistently processed reference section in each run and interpret intensity comparisons cautiously (standard IHC practice). Do not attribute a fixation effect to CISD2 solely from its membrane topology or reported tissue staining (UniProt Q8N5K1 topology; HPA tissue IHC).
What CISD2 staining pattern is plausible in tissue sections?
Expect predominantly granular cytoplasmic staining in tissue IHC, consistent with the reported pattern across most tissues (HPA tissue IHC). CISD2 is annotated at the endoplasmic reticulum membrane and mitochondrial outer membrane, with evidence favoring the endoplasmic reticulum in the cited human study (UniProt Q8N5K1 subcellular location). At the resolution of chromogenic IHC, granular cytoplasmic signal alone cannot establish which organelle contains the antigen (standard IHC practice). Compare the stained cell types and their intracellular pattern with a matched control section before assigning biological meaning (standard IHC practice). A strong isolated nuclear pattern would conflict with the supplied localisation evidence and warrants review of controls and staining conditions (UniProt Q8N5K1 subcellular location; standard IHC practice).
How should CISD2 topology affect interpretation of an antibody epitope?
CISD2 has a transmembrane segment at residues 38–60, with residues 2–37 lumenal and 61–135 cytoplasmic (UniProt Q8N5K1 topology). The supplied record lists no isoforms, glycosylation sites or modified residues, so it provides no basis for an isoform-specific staining claim (UniProt Q8N5K1 record). Check the antibody's documented immunogen or epitope before attributing weak staining to access to one side of the membrane (standard IHC practice). Retrieval can alter epitope accessibility in paraffin sections, so compare controlled retrieval conditions if the documented epitope remains poorly detected (standard IHC practice). Do not infer the antibody's epitope position from the observed chromogenic pattern alone (standard IHC practice).
How can IF help assess an ambiguous CISD2 IHC pattern?
Use IF as a separate localisation check when a granular chromogenic pattern is difficult to assign to cells (HPA tissue IHC; standard IF practice). Multiplex CISD2 with a validated marker for the expected cell type, chosen for the specific tissue under study, and assess overlap at the cell level (standard IF practice). Select fluorophores and controls that distinguish signal from that tissue's autofluorescence, particularly when evaluating punctate cytoplasmic staining (standard IF practice). If the antibody epitope is documented as lumenal or cytoplasmic, optimise permeabilisation for access to that membrane side without assuming an undocumented epitope location (UniProt Q8N5K1 topology; standard IF practice). Compare IF findings with the IHC cellular pattern, recognising that fluorescence overlap alone does not prove molecular interaction (standard IF practice).
How do I distinguish CISD2 signal from chromogenic background?
The selected paraffin-section example used 10% goat serum, 2 µg/mL primary antibody and biotin-based DAB detection (caption A06387-1). When background rises, inspect a no-primary control and compare matched sections before changing antibody concentration or detection conditions (standard IHC practice). Include a peroxidase block for DAB workflows and review endogenous biotin interference when using a biotin-based detection system (standard IHC practice; caption A06387-1). Excessive edge staining, deposits or signal in damaged tissue should be assessed separately from the granular cytoplasmic pattern reported for CISD2 (HPA tissue IHC; standard IHC practice). Adjust blocking, washes or detection exposure one factor at a time while preserving a reference section for comparison (standard IHC practice).
How should CISD2 staining be scored across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and tissue region before measuring CISD2, since staining intensity and the proportion of relevant cells can vary independently (standard IHC practice). For cellular staining, report an H-score from intensity categories and their percentages, or report the percentage of positive cells with the intensity threshold stated (standard IHC practice). If counting stained cells, express density per mm² of viable, evaluable tissue and document excluded necrotic or damaged areas (standard IHC practice). Normalise comparisons to the same cell compartment, section area, imaging settings and reference staining run rather than to whole-section darkness (standard IHC practice). Record cell type alongside score because CISD2 is reported in multiple tissues and cell populations (HPA tissue IHC).
What makes a positive CISD2 IHC result credible?
A credible result shows a reproducible cellular pattern compatible with granular cytoplasmic CISD2 staining and appropriate control behavior (HPA tissue IHC; standard IHC practice). Check whether stained cells fit the sampled tissue: HPA reports medium staining in bronchial respiratory epithelium and no detection in adipocytes, among its surveyed examples (HPA tissue IHC). Predominantly nuclear staining conflicts with the supplied endoplasmic reticulum and mitochondrial outer-membrane localisation and should prompt review (UniProt Q8N5K1 subcellular location; standard IHC practice). Exclude tissue edges, necrosis and endogenous enzyme signal before assigning a positive score (standard IHC practice). Treat tissue-level conclusions cautiously because the HPA tissue-IHC assessment reports medium consistency with RNA expression and awaits external verification (HPA tissue IHC).
Boster reagents

Best CISD2 / CDGSH iron-sulfur domain-containing protein 2 IHC Antibodies

The catalog shows CISD2 IHC in human lung cancer paraffin sections and rat brain (catalog IHC captions), plus IF in human A431 cells and rat brain (catalog IF captions).

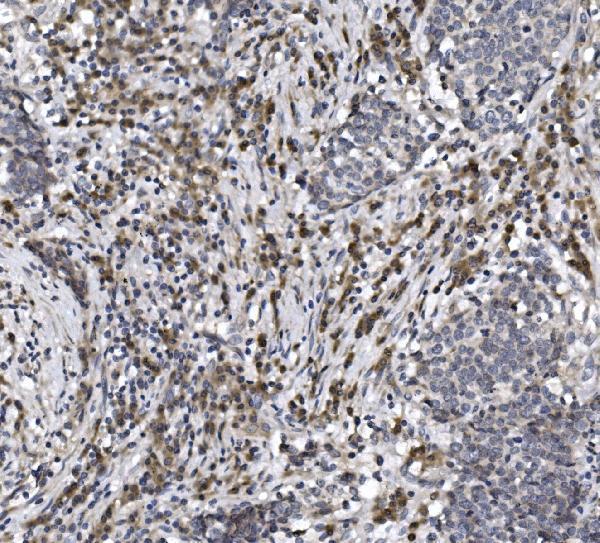
Real IHC data IHC analysis of CISD2 using anti-CISD2 antibody (A06387-1). CISD2 was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-CISD2 Antibody (A06387-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-CISD2 Antibody ®
Cat # A06387-1
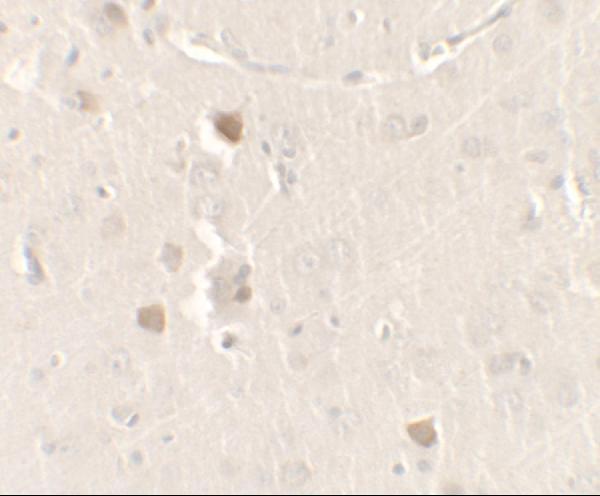
Real IHC data Immunohistochemistry of CISD2 in rat brain tissue with CISD2 antibody at 2.5 μg/ml.
Anti-CISD2 Antibody
Cat # A06387

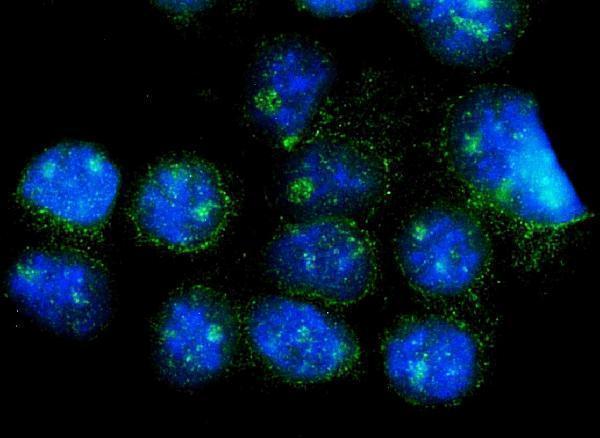
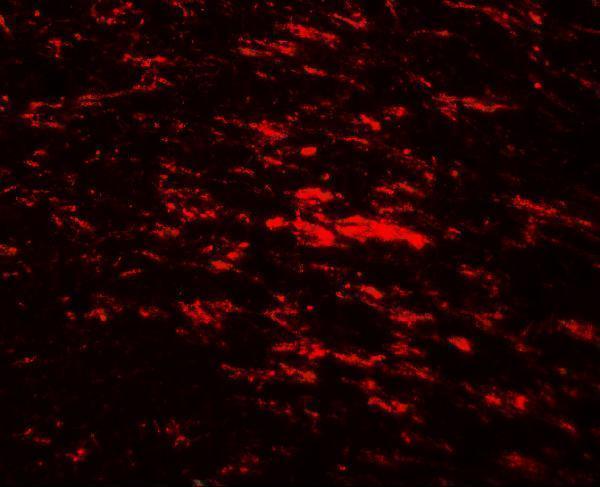
A06387-1 has IHC images from human lung cancer paraffin sections and rat brain, and an ICC/IF image from A431 cells (A06387-1 image captions). A06387 has IHC and IF images from rat brain (A06387 image captions).

Which to pick: For paraffin tissue IHC, A06387-1 provides human lung cancer and rat brain examples with EDTA pH 8 retrieval and 2 μg/ml antibody; A06387 provides a rat brain IHC example at 2.5 μg/ml (respective IHC captions). For IF/ICC, A06387-1 has an A431 cell example at 5 μg/ml, while A06387 has a rat brain IF example at 20 μg/ml (respective IF captions). A06387-1 lists human, monkey, mouse and rat reactivity, compared with human, mouse and rat for A06387 (catalog reactivity); both are rabbit antibodies with clone type unreported (catalog host/clone), and neither IHC caption reports the fixative (catalog IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8N5K1 (CISD2_HUMAN, CDGSH iron-sulfur domain-containing protein 2).
  2. Human Protein Atlas. CISD2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CISD2 subcellular location (ICC-IF): Localized to the endoplasmic reticulum..
  4. Human Protein Atlas. CISD2 antibody validation summary (1 antibodies).
  5. Bioinformatic prediction of miR-320a as a potential negative regulator of CDGSH iron-sulfur domain 2 (CISD2), involved in lung adenocarcinoma bone metastasis via MYC activation, and associated with tumor immune infiltration. Translational cancer research 2024 — PMC11385248.
  6. A novel prognostic score model incorporating CDGSH iron sulfur domain2 (CISD2) predicts risk of disease progression in laryngeal squamous cell carcinoma. Oncotarget 2016 — PMC5008395.
  7. CDGSH Iron Sulfur Domain 2 Activates Proliferation and EMT of Pancreatic Cancer Cells via Wnt/β-Catenin Pathway and Has Prognostic Value in Human Pancreatic Cancer. Oncology research 2017 — PMC7841247.
  8. CISD2 Promotes Resistance to Sorafenib-Induced Ferroptosis by Regulating Autophagy in Hepatocellular Carcinoma. Frontiers in oncology 2021 — PMC8415543.
  9. PubMed PMID:17846994 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:17974005 — UniProt-cited evidence.