CKS2 / Cyclin-dependent kinases regulatory subunit 2 · IHC design guide

Design Immunohistochemistry for CKS2

Plan CKS2 staining in paraffin sections around the nuclear pattern reported in most tissues (HPA tissue IHC). Use the catalog antibody at 1:100–1:300 (datasheet: A08202-1), and interpret staining with the reported cross-gene targeting caution (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CKS2 (IHC for CKS2): expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody A08202-1, validated IHC image, and IHC protocol steps
Printable CKS2 IHC protocol sheet — expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody A08202-1, controls and protocol steps. Open the full CKS2 IHC guide →

CKS2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in most tissues (HPA tissue IHC)
Staining pattern Nuclear signal in cells across most tissues (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining may reflect proteins from more than one gene (HPA tissue IHC)
Regulation Cell-cycle linked; regulation unreported (UniProt)
Isoform / epitope No annotated isoforms; one 1–79 chain (UniProt)
Section 1

Recommended CKS2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by 3 published CKS2 tumor-section protocols (PMC9406629; PMC8806895; PMC6411633).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A08202-1)
FixationImage fixative and duration unreported (datasheet A08202-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CKS2, 1:100 - 1:300 (datasheet A08202-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCKS2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval setting); the glioma protocol offers a 5 min pressure-cooker comparison (PMC8806895).
Section 2

What Is the Expected CKS2 Staining Pattern?

In paraffin-section IHC, expect predominantly nuclear CKS2 staining across most tissues (HPA tissue IHC: nuclear expression in most tissues). High staining is reported in bone marrow hematopoietic cells and several other specified cell types (HPA tissue IHC: High). The HPA tissue profile is Approved but cautions that the antibody targets proteins from more than one gene (HPA tissue IHC: reliability description). CKS2 has no transmembrane segment; UniProt does not assign it a subcellular location (UniProt P33552: topology and subcellular annotation).

What am I looking at on my slide?
Nuclear staining in hematopoietic cells of bone marrow or glandular cells of adrenal gland or appendix.This fits the reported compartment and high-staining cell populations (HPA tissue IHC: nuclear profile; High in these cells). Evaluate the proportion of stained cells and staining intensity within the identified population; a high HPA level is a reference pattern, not a required score for every section (general IHC practice).
Predominantly cytoplasmic or punctate staining, with little nuclear signal, in paraffin-section IHC.This differs from the reported tissue IHC profile (HPA tissue IHC: nuclear expression in most tissues). Check morphology, controls and antibody-specific validation before calling it CKS2: ICC-IF separately reports cytosol and mitochondria as main locations, with a multi-gene targeting caution (HPA subcellular: summary).
Strong staining confined to cells other than the reported high-staining population in a reference tissue.For example, an exclusive nonhematopoietic signal in bone marrow warrants checking cell identity and nonspecific staining (HPA tissue IHC: High in bone marrow hematopoietic cells; general IHC practice). HPA also reports nuclear expression in most tissues, so staining outside a listed high population is not, by itself, proof of cross-reactivity (HPA tissue IHC: profile).
Uniform colour over tissue, extracellular spaces or section edges, obscuring nuclei.This is diffuse background rather than an interpretable nuclear pattern (HPA tissue IHC: nuclear profile). Review primary-antibody concentration, blocking and detection controls; retained endogenous enzyme activity can contribute to chromogenic background (general IHC practice).
No nuclear signal in an otherwise intact bone marrow section.This conflicts with the reported high staining in hematopoietic cells (HPA tissue IHC: High in bone marrow hematopoietic cells). First check that those cells are present and that the run's controls worked; absence of signal alone cannot establish that the sample lacks CKS2 (general IHC practice).
💡Expected CKS2 appearanceCall a paraffin-section result positive when identifiable cells show nuclear staining, especially the reported high-staining hematopoietic cells of bone marrow; broad diffuse colour or an exclusively nonnuclear pattern is suspect (HPA tissue IHC: nuclear profile; High in bone marrow hematopoietic cells; general IHC practice).
How each factor affects the staining
Tissue reference and validationThe tissue profile is Approved but carries a multi-gene targeting caution; the listed high populations are useful reference patterns, not proof of unique CKS2 detection (HPA tissue IHC: reliability description and positive list).
IHC antibody evidenceHPA030762 is IHC Approved, while HPA003424 has ICC Approved status and no listed IHC status (HPA antibodies: validation entries). Do not transfer ICC validation to paraffin-section IHC (general IHC practice).
Topology and processingCKS2 has no transmembrane segment, signal peptide or propeptide; its annotated chain spans residues 1–79 (UniProt P33552: topology and processing). These facts do not establish antigen-retrieval conditions or fixation sensitivity.
Tissue RNA versus protein stainBone marrow and testis are tissue-enhanced at the RNA level; the supplied protein IHC examples report High staining in bone marrow hematopoietic cells, but give no testis cell-level example (HPA tissue IHC: RNA specificity and positive list).
Q: What should IF/ICC show?A: HPA reports mainly cytosol and mitochondria, with additional nucleoplasm and vesicles; this ICC-IF summary also cautions about antibodies targeting multiple genes (HPA subcellular: locations and summary).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Bone marrow reference section is blank.A failed staining run, absent hematopoietic cells or insufficient detection can produce a blank result (general IHC practice).Confirm cell morphology and run controls, then review the antibody's IHC-P instructions and detection reagents (HPA tissue IHC: High in bone marrow hematopoietic cells; general IHC practice).
Staining appears only outside nuclei in tissue IHC.The observed distribution differs from HPA's predominant tissue nuclear pattern; HPA's ICC-IF locations describe a different assay (HPA tissue IHC: profile; HPA subcellular: locations).Check nuclear counterstain, tissue morphology and antibody validation before assigning the signal to CKS2 (general IHC practice).
Unexpected cells stain more strongly than the reported reference population.Cell misidentification, nonspecific binding or endogenous detection activity are possible explanations (general IHC practice).Compare cell types within the same tissue and inspect a primary-omission control; treat an isolated mismatch cautiously because HPA flags multi-gene targeting (HPA tissue IHC: reliability description; general IHC practice).
Brown precipitate or diffuse colour obscures cell boundaries.Excess background may arise from detection chemistry, endogenous peroxidase activity or nonspecific binding (general IHC practice).Inspect a primary-omission control, review blocking and peroxidase quenching, and adjust detection conditions using the antibody's IHC-P instructions (general IHC practice).
Signal is weak but nuclei and tissue architecture remain visible.The available HPA examples show High staining in selected populations; they do not define an intensity cutoff for every specimen (HPA tissue IHC: positive list).Compare the run with a reported high-staining reference tissue and working controls before changing retrieval or primary-antibody conditions (HPA tissue IHC: positive list; general IHC practice).
ICC-IF and paraffin-section IHC appear to disagree.HPA reports mainly cytosol and mitochondria by ICC-IF, versus nuclear expression in most tissues by IHC; both summaries carry specificity cautions (HPA subcellular: summary; HPA tissue IHC: profile and reliability description).Interpret each assay against its own HPA pattern and antibody validation; investigate controls before treating either distribution as definitive (HPA antibodies: validation entries; general IHC practice).

Sample controls for CKS2 IHC & IF

🧪Start with bone marrow: hematopoietic cells should stain (HPA: High in hematopoietic cells). HPA detects CKS2 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect any unstained cells within the positive section to show counterstain only, without assuming a particular cell type is CKS2-negative (HPA: no negative tissue rows).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: CKS2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CKS2 in A-549, PC-3, U2OS, with annotated localisation: Mitochondria (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Run a secondary-only control and an isotype control matched to the primary antibody’s host species and class, using normal IgG if the primary is polyclonal; a peptide-blocked section provides a biological specificity control (A08202-1 caption: peptide-blocked brain section). For chromogenic bone marrow IHC, block endogenous peroxidase and check for residual background in hematopoietic cells (HPA: High in hematopoietic cells).
⚠️Feasibility: No supplied evidence reports a CKS2-specific fixation window or antigen-retrieval dependency; optimize retrieval for the chosen paraffin-section assay. The A08202-1 paraffin brain caption does not report a fixative (A08202-1 caption: fixative unreported). Frozen sections are not assessed here, and IF/ICC cannot be judged easier from the supplied images; interpret its reported cytosol and mitochondria localization cautiously because the HPA summary draws on antibodies targeting proteins from multiple genes (HPA: subcellular summary).

HPA tissue IHC evidence for CKS2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Caution, targets protein from more than one gene. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CKS2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CKS2 IHC Tips

Troubleshoot CKS2 staining in paraffin sections by checking retrieval, compartment, controls and scoring before interpreting chromogenic signal.

How should I retrieve CKS2 antigen when paraffin sections stain weakly?
Start with citrate buffer at pH 6.0 for heat-induced retrieval at 95–98 °C for 20 minutes (page retrieval rule). Let slides cool in buffer, then compare a retrieved section with an otherwise matched no-retrieval section to assess whether retrieval improves signal without damaging tissue (standard IHC practice). Keep section thickness, antibody incubation and chromogen development consistent across that comparison (standard IHC practice). If staining remains weak, test a different retrieval buffer or exposure time as a fallback, using adjacent sections and the same controls (standard IHC practice). Evaluate nuclear and cytoplasmic patterns separately because published CKS2 localisation evidence differs by assay (HPA tissue IHC; HPA subcellular).
Could fixation explain inconsistent CKS2 staining across my paraffin blocks?
Target-specific CKS2 sensitivity to fixative type or fixation duration is unknown from the supplied evidence; the catalog brain image identifies paraffin embedding but does not state its fixative (A08202-1 caption). Record each block’s fixative and fixation interval, then compare sections processed with the same pH 6.0, 20-minute citrate retrieval (page retrieval rule; standard IHC practice). Include a previously staining section in each run to distinguish a block problem from a reagent or detection problem (standard IHC practice). If signal differs, assess morphology and repeat staining under matched conditions before attributing the difference to fixation (standard IHC practice).
Should CKS2 appear in nuclei or cytoplasm in chromogenic tissue IHC?
Nuclear staining is reported across most tissues in the tissue IHC profile, although that profile carries a warning about antibodies targeting proteins from more than one gene (HPA tissue IHC). Cell imaging instead reports mainly cytosol and mitochondria, with additional nucleoplasm and vesicle signal, under the same cross-gene caution (HPA subcellular). Score nuclear and cytoplasmic staining separately, using matched sections and a no-primary control to evaluate diffuse chromogen (standard IHC practice). A purely mitochondrial pattern cannot be established from chromogenic appearance alone; confirm a disputed compartment with an orthogonal assay before assigning it to CKS2 (HPA subcellular; standard IHC practice).
How can I assess whether my antibody recognises the intended CKS2 epitope?
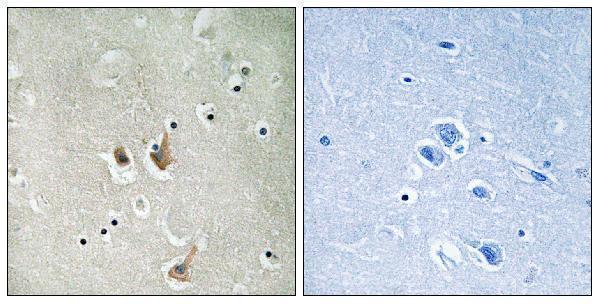
The supplied record lists a single 79-amino-acid chain, no annotated isoforms and no transmembrane segment, so it provides no basis for an isoform-specific staining claim (UniProt P33552 record). It records one example of an N-terminal modified residue, N6-acetyllysine at position 4, without establishing an effect on this antibody’s binding (UniProt P33552 record). The selected catalog image shows peptide-blocked staining in paraffin-embedded human brain, providing a competition control for that image (A08202-1 caption). Compare blocked and unblocked adjacent sections, then seek independent target validation before treating peptide competition as proof that all tissue signal is CKS2-specific (A08202-1 caption; standard IHC practice).
How should I follow up uncertain CKS2 IHC localisation with IF?
Use IF as a separate localisation check: the supplied cell-imaging profile places signal mainly in cytosol and mitochondria, with additional nucleoplasm and vesicles (HPA subcellular). Multiplex CKS2 with a validated marker for the cell population under study, assigning spectrally distinct fluorophores and checking each channel separately (standard IF practice). Select a fluorophore channel after measuring unstained tissue autofluorescence, and include single-stain controls when assessing overlap (standard IF practice). Because the record shows no transmembrane segment, choose permeabilisation for access to intracellular epitopes and verify its effect with matched samples; the supplied evidence does not map this antibody’s epitope (UniProt P33552 record; standard IF practice).
What should I check when CKS2 IHC has widespread brown background?
Inspect a no-primary section before adjusting the CKS2 antibody: residual chromogen or endogenous enzyme activity can create signal without primary antibody binding (standard IHC practice). For peroxidase and DAB detection, include a peroxidase block and compare matched development times; these are general workflow controls, not CKS2-specific validation (standard IHC practice). Optimise protein blocking, wash consistency and a dilution series while keeping the pH 6.0, 20-minute retrieval condition fixed initially (page retrieval rule; standard IHC practice). Distinguish crisp cellular staining from pigment, folds and section edges on the counterstained slide, and review nuclear and cytoplasmic signal separately (standard IHC practice; HPA tissue IHC).
How can I quantify CKS2 staining without confusing expression and tissue composition? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring: the tissue IHC profile reports predominantly nuclear staining, while cell imaging also reports cytoplasmic localisation (HPA tissue IHC; HPA subcellular). For a defined cell population, record percent positive cells and intensity, or calculate an H-score from 0–300 using percentages at intensity grades 0–3 (standard IHC practice). Normalise counts to the number of eligible cells, or report positive-cell density per mm² of evaluable tissue, excluding necrotic and folded areas by a prespecified rule (standard IHC practice). Keep exposure, chromogen development and scoring thresholds consistent across sections, and report nuclear and cytoplasmic results separately (standard IHC practice).
When is CKS2 staining convincing rather than artefactual?
Look for reproducible cellular staining in the prespecified compartment, with low signal in a no-primary control and appropriate morphology on the counterstain (standard IHC practice). Nuclear staining is compatible with the tissue IHC profile, while cytoplasmic signal has support from cell imaging; neither pattern alone establishes antibody specificity (HPA tissue IHC; HPA subcellular). Treat staining confined to tissue edges, folds, necrosis or endogenous-enzyme-rich areas cautiously, especially when the same pattern appears in controls (standard IHC practice). The catalog brain image includes a peptide-blocked comparison, but the tissue profile warns of possible cross-gene recognition; resolve unexpected cell or compartment patterns with an independent target assay (A08202-1 caption; HPA tissue IHC).
Boster reagents

Best CKS2 / Cyclin-dependent kinases regulatory subunit 2 IHC Antibodies

A08202-1 has a human paraffin-section IHC image (catalog: IHC image caption) and is listed for human and mouse IHC, IF, and ICC (catalog: applications and reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human brain tissue, using CKS2 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-CKS2 Antibody
Cat # A08202-1

A08202-1 is listed for human and mouse IHC, IF, and ICC (catalog: applications and reactivity). Its IHC image shows paraffin-embedded human brain with a peptide-blocked comparison (catalog: IHC image caption); no IF image is supplied (catalog: IF image alts).

Which to pick: Choose A08202-1 for paraffin-section tissue IHC: its own image shows paraffin-embedded human brain (catalog: IHC image caption), and its IHC dilution is 1:100–1:300 (catalog: IHC dilution). For IF/ICC, A08202-1 is listed for both applications and is rabbit polyclonal (catalog: applications, host and dilution_raw); its listed IF dilution is 1:50 (catalog: IF dilution). For work involving human and mouse samples, A08202-1 lists both species (catalog: reactivity); the IHC caption does not report the fixative (catalog: IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P33552 (CKS2_HUMAN, Cyclin-dependent kinases regulatory subunit 2).
  2. Human Protein Atlas. CKS2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CKS2 subcellular location (ICC-IF): Mainly localized to the cytosol and mitochondria. In addition localized to the nucleoplasm and vesicles. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. CKS2 antibody validation summary (2 antibodies).
  5. Cyclin-Dependent Kinase Subunit 2 (CKS2) as a Prognostic Marker for Stages I-III Invasive Non-Mucinous Lung Adenocarcinoma and Its Role in Affecting Drug Sensitivity. Cells 2022 — PMC9406629.
  6. CKS2 Overexpression Correlates with Prognosis and Immune Cell Infiltration in Lung Adenocarcinoma: A Comprehensive Study based on Bioinformatics and Experiments. Journal of Cancer 2021 — PMC8558665.
  7. CKS2 (CDC28 protein kinase regulatory subunit 2) is a prognostic biomarker in lower grade glioma: a study based on bioinformatic analysis and immunohistochemistry. Bioengineered 2021 — PMC8806895.
  8. Mitochondrial Function of CKS2 Oncoprotein Links Oxidative Phosphorylation with Cell Division in Chemoradioresistant Cervical Cancer. Neoplasia (New York, N.Y.) 2019 — PMC6411633.
  9. PubMed PMID:2227411 — UniProt-cited evidence.
  10. PubMed PMID:15164053 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.