CMTM4 / CKLF-like MARVEL transmembrane domain-containing protein 4 · IHC design guide

Design Immunohistochemistry for CMTM4

Plan CMTM4 chromogenic IHC in paraffin sections around the reported cytoplasmic and membranous glandular-cell pattern (HPA tissue IHC). Use thyroid or parathyroid glandular cells, where staining is high, as positive controls and interpret unexpected signal in light of reported off-target binding (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CMTM4 (IHC for CMTM4): expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC), antibody A14124, validated IHC image, and IHC protocol steps
Printable CMTM4 IHC protocol sheet — expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC), antibody A14124, controls and protocol steps. Open the full CMTM4 IHC guide →

CMTM4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC)
Staining pattern Glandular cells show cytoplasmic and membranous staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Parathyroid gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A14124)
Caveat Presumed off-target binding has been observed (HPA tissue IHC)
Regulation Staining-linked regulation is unreported (UniProt)
Isoform / epitope 3 isoforms; check extracellular vs cytoplasmic epitope (UniProt)
Section 1

Recommended CMTM4 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published CMTM4 methods for oral, renal, and canine tumor tissues (PMC10869054; PMC4609138; PMC7300202).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A14124)
FixationImage fixative and duration unreported (datasheet A14124); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CMTM4, 1:100 (datasheet A14124)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCMTM4-positive staining in glandular cells of parathyroid gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression, most abundant in thryoid and parathyroid glands. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen retrieval); compare the published retrieval conditions where stated (PMC10869054; PMC7300202).
Section 2

What Is the Expected CMTM4 Staining Pattern?

CMTM4 is a four-pass membrane protein (UniProt Q8IZR5 topology). In paraffin-section IHC, expect cytoplasmic and membranous staining, especially in thyroid and parathyroid glandular cells (HPA: tissue IHC). HPA rates its tissue staining Enhanced, while noting that presumed off-target binding was observed and disregarded (HPA: tissue IHC reliability). Read the pattern by both compartment and cell type.

What am I looking at on my slide?
Strong membranous and cytoplasmic staining in thyroid or parathyroid glandular cells (HPA: High in both).This matches the strongest reported tissue pattern (HPA: tissue IHC). Membrane staining fits the four-pass topology (UniProt Q8IZR5). Cytoplasmic signal is also compatible with the HPA tissue pattern; do not require a membrane-only result.
Predominantly nuclear staining, with little glandular membrane or cytoplasmic signal.A nuclear-dominant pattern does not match the reported tissue pattern or membrane annotation (HPA: tissue IHC; UniProt Q8IZR5). Treat it as suspect and compare antibody-omission and known-positive controls before interpreting it as CMTM4 (general IHC practice).
Strong staining in adipocytes, fibroblasts, or squamous epithelial cells where HPA reports none.HPA reports CMTM4 as Not detected in adipocytes, skin and soft-tissue fibroblasts, and oral or vaginal squamous epithelium (HPA: tissue IHC). Check for antibody cross-reactivity or endogenous detection activity; these are possible explanations, not diagnoses from staining alone (general IHC practice).
Diffuse color across cells and surrounding tissue, obscuring boundaries.This cannot establish the glandular cytoplasmic and membranous pattern (HPA: tissue IHC). Background from detection reagents or inadequate blocking can obscure localization; compare no-primary and detection controls, then adjust the affected step (general IHC practice).
No staining in thyroid or parathyroid glandular cells despite an intact section.This conflicts with the High staining reported for those cells (HPA: tissue IHC). First verify that the detection system and tissue control worked; then review the antibody's IHC-P instructions, including its specified retrieval and dilution, before calling the sample negative (general IHC practice).
💡Expected CMTM4 appearanceCall a positive result when thyroid or parathyroid glandular cells show strong cytoplasmic and membranous staining (HPA: High; tissue IHC); dominant nuclear staining or strong signal in HPA Not detected cell types is suspect and needs controls (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Membrane topology (UniProt Q8IZR5)Four transmembrane segments support a membrane-associated interpretation (UniProt Q8IZR5 topology). They do not require an exclusively surface-outlined chromogenic pattern: HPA reports both cytoplasmic and membranous tissue staining (HPA: tissue IHC).
IF/ICC Q: Where does CMTM4 localize?A: HPA approves plasma membrane, Golgi apparatus, and vesicle localization in ICC-IF (HPA: subcellular). This supports intracellular signal as plausible, while tissue IHC should be judged against its own cytoplasmic and membranous pattern (HPA: tissue IHC).
Three annotated isoforms (UniProt Q8IZR5)UniProt lists isoforms 1, 2, and 3 (UniProt Q8IZR5). The supplied evidence does not map an IHC antibody epitope to them; do not infer isoform-specific staining or use a missing signal to assign an isoform.
Tissue evidence differs by sourceUniProt describes high expression in testis and prostate (UniProt Q8IZR5 tissue specificity), whereas HPA's strongest listed IHC staining is in thyroid and parathyroid glandular cells (HPA: High). Use the HPA cell-level IHC observations to choose slide controls.
Validation has a defined limitTwo listed antibodies have Enhanced IHC status (HPA: HPA014704 and HPA023890). HPA also notes presumed off-target binding that was disregarded (HPA: tissue IHC reliability); Enhanced supports the reported pattern but does not make every stained cell specific.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive glandular cells are blank.The result disagrees with High thyroid and parathyroid glandular staining (HPA: tissue IHC); a failed detection step or unsuitable assay settings are possibilities (general IHC practice).Run a known-positive section and detection control, then follow the catalog antibody's IHC-P instructions for retrieval and dilution; change one assay variable at a time (general IHC practice).
Only nuclei stain.Nuclear-dominant signal diverges from HPA's cytoplasmic and membranous tissue pattern and UniProt's membrane annotation (HPA: tissue IHC; UniProt Q8IZR5).Review a known-positive glandular section alongside a no-primary control; withhold a CMTM4-positive call until the expected compartments are demonstrable (general IHC practice).
Adipocytes or listed squamous cells stain strongly.These cell types are Not detected in the supplied HPA tissue observations (HPA: tissue IHC). Cross-reactivity or endogenous detection activity may account for the discordance (general IHC practice).Compare the cell-specific pattern with a no-primary and appropriate detection control; investigate persistent primary-dependent staining before scoring those cells as positive (general IHC practice).
Diffuse color hides glandular cell boundaries.Diffuse background prevents assessment of HPA's reported cytoplasmic and membranous pattern (HPA: tissue IHC); blocking or detection background may contribute (general IHC practice).Inspect no-primary controls and review blocking, washing, and detection conditions; score localization only when cell boundaries and compartments can be resolved (general IHC practice).
Cytoplasmic staining appears without a crisp cell-surface rim.The pattern can still align with HPA's cytoplasmic and membranous tissue description; ICC-IF also places CMTM4 in Golgi apparatus and vesicles (HPA: tissue IHC; HPA: subcellular).Assess the stained cell type and distribution against the thyroid or parathyroid glandular reference pattern; avoid rejecting a result solely for lacking a sharp rim (HPA: tissue IHC).
Two antibody results disagree in the same cell type.HPA lists two Enhanced IHC antibodies, yet records presumed off-target binding in its tissue assessment (HPA: HPA014704 and HPA023890; tissue IHC reliability).Compare compartments and known-positive and Not detected cell types on matched sections; use the discordance as a reason to investigate specificity before assigning a CMTM4 score (HPA: tissue IHC; general IHC practice).

Sample controls for CMTM4 IHC & IF

🧪Run parathyroid gland first and look for staining in its glandular cells (HPA: High in parathyroid glandular cells); use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes). On the parathyroid slide, compare adjacent nonglandular cells for background chromogen and intact nuclear counterstain, without assuming they are validated CMTM4-negative cells (HPA: parathyroid glandular cells High).
Positive control tissue: Parathyroid gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CMTM4 in A-431, U-251MG, U2OS, with annotated localisation: Golgi apparatus (approved), Vesicles (approved), Plasma membrane (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, an irrelevant immunoglobulin control matched to the primary antibody’s host species and clonality, and a cognate-peptide block as a specificity check (A14124 tissue-IHC caption: CKLF4 peptide block). For chromogenic parathyroid IHC, quench endogenous peroxidase and inspect the no-primary slide for residual background (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the A14124 paraffin-section caption does not state a fixative; fixation cannot be inferred (A14124 tissue-IHC caption). Antigen retrieval dependency is unreported, so retrieval needs empirical optimization; the supplied evidence does not establish that frozen sections or IF are easier (A14124 tissue-IHC caption; HPA: ICC-IF images available). No parathyroid-specific artefact is reported in the supplied evidence; check background on the positive section during scoring (HPA: parathyroid glandular cells High; standard chromogenic IHC practice). The selected A14124 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A14124).

HPA tissue IHC evidence for CMTM4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Parathyroid gland Glandular cells High Protein (IHC) HPA →
Thyroid gland Glandular cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Skin Fibroblasts Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CMTM4 IHC Tips

Troubleshoot CMTM4 staining in paraffin sections by checking retrieval, compartment, cell type and controls before scoring chromogenic signal.

What retrieval should I use when CMTM4 staining is weak in paraffin sections?
Use citrate buffer at pH 6.0 for heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval setting). Allow sections to cool in buffer, then compare a retrieved section with an otherwise matched section to assess whether signal improves (standard IHC practice). CMTM4 has 4 transmembrane segments within its MARVEL domain, so access to a particular epitope may vary with retrieval (UniProt Q8IZR5 topology and domain). If staining remains weak, test an alternative buffer or pH on matched sections as a fallback, while watching for tissue damage and increased background (standard IHC practice).
How should I troubleshoot variable CMTM4 staining between differently fixed specimens?
Record fixative, fixation duration and processing history for each specimen before comparing staining (standard IHC practice). Target-specific fixation sensitivity for CMTM4 is unknown from the supplied evidence; the selected A14124 paraffin-section caption does not state a fixative (A14124 tissue-IHC caption). Process a reference section alongside each run and compare intact areas under the same citrate pH 6.0, 95–98 °C, 20 min retrieval conditions (page retrieval setting; standard IHC practice). If staining differs, assess morphology and other assay controls before attributing the difference to CMTM4 abundance (standard IHC practice).
Which staining compartments should count as plausible CMTM4 signal?
Assess membrane-associated and cytoplasmic staining in tissue sections; these patterns are reported for CMTM4 tissue IHC (HPA tissue IHC profile). Plasma membrane, Golgi apparatus and vesicles are supported subcellular locations, so punctate intracellular signal can be plausible when cellular morphology is preserved (HPA subcellular). CMTM4 contains 4 transmembrane segments, consistent with examining membrane-associated signal carefully (UniProt Q8IZR5 topology). Compare the same cell compartment across specimens, and avoid counting diffuse extracellular deposit or isolated nuclear color as convincing CMTM4 without additional validation (HPA subcellular; standard IHC interpretation). Record membranous and cytoplasmic patterns separately when they differ (standard IHC scoring practice).
Could isoforms or epitope position explain inconsistent CMTM4 staining?
CMTM4 has 3 annotated isoforms, but the supplied evidence does not map the catalog antibody’s epitope to any isoform (UniProt Q8IZR5 isoforms; supplied antibody evidence). Check the antibody’s epitope information before interpreting a negative section as absence of all CMTM4 forms (standard antibody validation practice). The MARVEL domain spans residues 49–176 and includes 4 transmembrane segments, so epitope accessibility may depend on its location and tissue processing (UniProt Q8IZR5 domain and topology; standard IHC practice). Phosphoserine at residue 194 is annotated, but no supplied evidence establishes a staining effect for this antibody (UniProt Q8IZR5 modified residues; supplied antibody evidence).
How can IF help check an ambiguous chromogenic CMTM4 pattern?
Use IF as a separate validation experiment, since the supplied A14124 tissue image documents paraffin-section IHC rather than IF conditions (A14124 tissue-IHC caption). Multiplex CMTM4 with a marker identifying the cell type under study, and inspect whether signal occupies the same cells and plausible membrane or intracellular compartments (HPA subcellular; standard IF practice). Choose fluorophores after measuring tissue autofluorescence, favoring channels with clear separation from that background (standard IF practice). Adjust permeabilisation according to whether the antibody epitope faces the cytoplasm or an extracellular or luminal space; its position is not specified here (UniProt Q8IZR5 topology; supplied antibody evidence; standard IF practice).
What controls distinguish CMTM4 staining from chromogenic background?
Run a no-primary control to reveal secondary-detection background, and check the peroxidase block when using an HRP and DAB workflow (standard chromogenic IHC practice). Inspect tissue edges, folds and damaged areas separately because concentrated chromogen there can mislead scoring (standard IHC practice). The selected A14124 paraffin-section image includes peptide blocking in its caption, which provides a reagent-specific comparison for that image (A14124 tissue-IHC caption). HPA reports presumed off-target binding that was disregarded, so interpret isolated staining patterns cautiously (HPA tissue IHC reliability description). Compare suspicious deposits with expected membrane and cytoplasmic patterns in intact cells (HPA tissue IHC profile; standard IHC practice).
How should I quantify heterogeneous CMTM4 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring compartment before measuring signal, then apply the same criteria to every section (standard IHC scoring practice). For glandular cells, report the percentage positive and an H-score from intensity categories; specify whether membrane and cytoplasm were scored separately (HPA tissue IHC profile; standard IHC scoring practice). For dispersed positive cells, density per mm² of viable, evaluable tissue may be more useful than an area-wide intensity average (standard IHC quantification practice). Normalise counts to the relevant cell population or viable tissue area, and exclude necrosis, folds and edge staining from the denominator (standard IHC scoring practice).
When is a CMTM4-positive IHC result convincing rather than artefactual?
Look for reproducible membrane or cytoplasmic signal in intact cells, consistent with the reported tissue pattern and approved plasma membrane, Golgi and vesicle locations (HPA tissue IHC profile; HPA subcellular). Strong glandular-cell staining in parathyroid or thyroid tissue can provide context, while HPA reports no detection in adipocytes from adipose tissue (HPA tissue IHC positive and negative listings). Treat isolated nuclear staining, necrotic deposits and section-edge color as suspect until controls support them (HPA subcellular; standard IHC interpretation). Check no-primary and peroxidase controls before assigning weak DAB color to CMTM4, and record the stained cell type and compartment with each score (standard chromogenic IHC practice).
Boster reagents

Best CMTM4 / CKLF-like MARVEL transmembrane domain-containing protein 4 IHC Antibodies

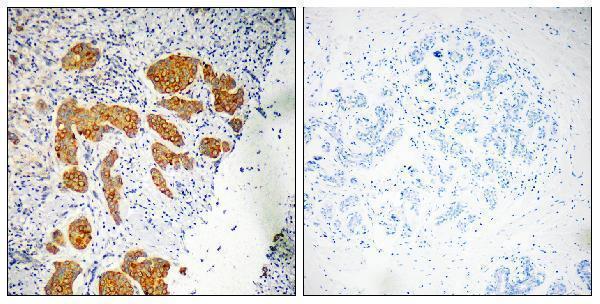
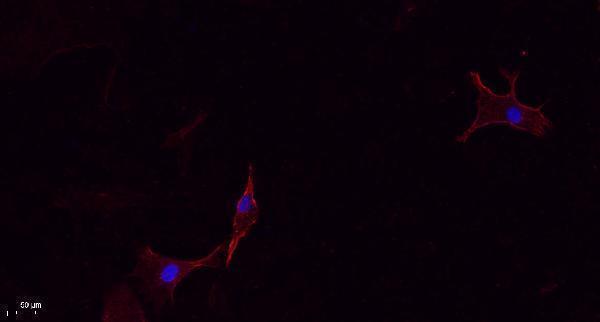
A14124 has human and mouse reactivity (catalog), with an IHC image from paraffin-embedded human breast carcinoma and an IF image from A549 cells (image captions).

Real IHC data Immunohistochemistryt analysis of paraffin-embedded human breast carcinoma, using CKLF4 Antibody. The lane on the right is blocked with the CKLF4 peptide.
Anti-CMTM4 Antibody
Cat # A14124

A14124 lists IHC and IF applications with human and mouse reactivity (catalog). Its images show IHC in paraffin-embedded human breast carcinoma and IF in A549 cells (image captions).

Which to pick: Choose A14124 for tissue IHC in paraffin sections; its IHC caption shows human breast carcinoma but does not report the fixative (IHC image caption). For IF, A14124 has an A549 image; ICC is not separately listed as an application (IF image caption; catalog applications). For work across species, A14124 is a rabbit polyclonal listed as reactive with human and mouse, although the supplied IHC image documents human tissue only (catalog; IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8IZR5 (CKLF4_HUMAN, CKLF-like MARVEL transmembrane domain-containing protein 4).
  2. Human Protein Atlas. CMTM4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CMTM4 subcellular location (ICC-IF): Localized to the plasma membrane, the Golgi apparatus and vesicles..
  4. Human Protein Atlas. CMTM4 antibody validation summary (2 antibodies).
  5. Prognostic significance of RKIP, TGM2, and CMTM4 expression in oral squamous cell carcinoma. Medicine 2024 — PMC10869054.
  6. CMTM4 inhibits gastric tumorigenesis and metastasis. Journal of gastrointestinal oncology 2024 — PMC11399846.
  7. CMTM4 is frequently downregulated and functions as a tumour suppressor in clear cell renal cell carcinoma. Journal of experimental & clinical cancer research : CR 2015 — PMC4609138.
  8. Expression Analysis of Canine CMTM6 and CMTM4 as Potential Regulators of the PD-L1 Protein in Canine Cancers. Frontiers in veterinary science 2020 — PMC7300202.
  9. PubMed PMID:12782130 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:21269460 — UniProt-cited evidence.