CNOT4 / CCR4-NOT transcription complex subunit 4 · IHC design guide

Design Immunohistochemistry for CNOT4

Plan CNOT4 paraffin IHC around widespread cytoplasmic staining, with high staining in selected glandular and neural cells as positive-control options (HPA tissue IHC). Start the catalog antibody at 1:100–1:300 (datasheet), and compare staining across consistently fixed sections.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CNOT4 (IHC for CNOT4): expected localisation Cytoplasmic staining observed in tissue; nucleus annotated (HPA tissue IHC; UniProt), antibody A08405, validated IHC image, and IHC protocol steps
Printable CNOT4 IHC protocol sheet — expected localisation Cytoplasmic staining observed in tissue; nucleus annotated (HPA tissue IHC; UniProt), antibody A08405, controls and protocol steps. Open the full CNOT4 IHC guide →

CNOT4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining observed in tissue; nucleus annotated (HPA tissue IHC; UniProt)
Staining pattern Widespread cytoplasmic staining across tissue cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat RNA predicts staining imperfectly: medium consistency (HPA tissue IHC)
Regulation No expression-inducing condition annotated (UniProt)
Isoform / epitope 10 isoforms; epitope coverage unspecified (UniProt; datasheet)
Section 1

Recommended CNOT4 IHC & IF Protocols

The catalog antibody’s IHC-P protocol and one published CNOT4 IHC method (PMC7714061) provide starting conditions for paraffin sections with chromogenic detection.

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human testis tissue; fixative not specified (datasheet A08405)
FixationImage fixative and duration unreported (datasheet A08405); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CNOT4, 1:100 - 1:300 (datasheet A08405)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCNOT4-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min for nuclear CNOT4 (UniProt: nucleus); compare the published retrieval (PMC7714061).
Section 2

What Is the Expected CNOT4 Staining Pattern?

CNOT4 is annotated in the cytoplasm and nucleus and has no transmembrane segment (UniProt O95628). In paraffin-section IHC, expect predominantly cytoplasmic staining across many cell types: HPA describes ubiquitous cytoplasmic expression and high staining in several glandular, epithelial, neural, and glial populations (HPA tissue IHC). The tissue profile is Approved, with medium consistency between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic chromogen in colon or appendix glandular cells, or bronchial respiratory epithelial cells.This matches the high staining reported for these cells and HPA’s ubiquitous cytoplasmic profile (HPA tissue IHC). Compare cells within the section as well as the overall field; HPA levels describe observed staining, not a required intensity in every specimen (HPA tissue IHC; general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal, or staining confined to lumens or cell borders.Nuclear localisation is possible (UniProt O95628), but a predominantly nuclear result differs from the reported tissue IHC pattern (HPA tissue IHC). Luminal or border-only signal also needs scrutiny because CNOT4 has no transmembrane segment or signal peptide (UniProt O95628). Check morphology and controls before assigning either pattern to CNOT4 (general IHC practice).
Strong adipocyte staining while expected glandular or epithelial cells are weak.HPA reports low staining in adipocytes and high staining in the listed glandular and respiratory epithelial cells (HPA tissue IHC). That reversal raises concern for cross-reactivity or detection-system background; it does not alone prove either cause (general IHC practice).
Diffuse colour across cells, stroma, or empty areas, obscuring cell boundaries.An indiscriminate deposit cannot establish the reported cytoplasmic pattern (HPA tissue IHC). Examine a section processed without primary antibody for detection background and review blocking, washes, and development time (general IHC practice).
No signal in a section containing colon glandular or bronchial respiratory epithelial cells.Both populations have high reported staining (HPA tissue IHC), so a blank run warrants a technical check before concluding CNOT4 is absent. Confirm tissue preservation and detection controls, then review antibody dilution and antigen-retrieval conditions using the assay’s validated instructions (general IHC practice).
💡Expected CNOT4 appearanceCall a positive result when cell-associated cytoplasmic staining is clear in HPA high populations such as colon glandular cells or bronchial respiratory epithelial cells (HPA tissue IHC); strong adipocyte, luminal, or uniform background staining is discordant with that pattern (HPA tissue IHC; UniProt O95628; general IHC practice).
How each factor affects the staining
Tissue and cell choiceHPA reports high staining in adrenal, appendix, cervix, and colon glandular cells; bronchial respiratory epithelial cells; caudate neurons; cerebellar molecular-layer cells; and cerebral-cortex glia (HPA tissue IHC). Adipocytes are reported low, so they are a useful within-run contrast where present (HPA tissue IHC).
Compartment interpretationUniProt lists both cytoplasm and nucleus (UniProt O95628), while HPA summarises tissue IHC as ubiquitously cytoplasmic (HPA tissue IHC). Record nuclear staining if seen, but assess it separately from the expected cytoplasmic result; neither source supplies a required nuclear-to-cytoplasmic ratio.
Antibody evidenceThe listed rabbit polyclonal antibody HPA005737 is Approved for IHC, while the overall tissue profile has medium staining–RNA consistency (HPA antibodies; HPA tissue IHC). These classifications support using the reported pattern as a reference, with morphology and run controls still needed for a new specimen (general IHC practice).
Protein formsUniProt lists ten isoforms, no signal peptide or propeptide, and a chain spanning residues 1–575 (UniProt O95628). The supplied record gives no antibody epitope, so it cannot establish which isoforms the IHC antibody detects or predict a form-specific staining pattern.
Retrieval and detectionTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-background chromogen masks cytoplasm.Nonspecific detection, incomplete blocking or washing, or excessive development can obscure localisation (general IHC practice).Compare the no-primary control, inspect blank tissue areas, and adjust the detection workflow before scoring CNOT4 (general IHC practice).
Chromogen appears in the no-primary control.The signal can arise from endogenous detection activity or detection reagents without primary antibody (general IHC practice).Address endogenous activity appropriate to the detection system and repeat its control; do not interpret that deposit as CNOT4 (general IHC practice).
Strong signal is limited to adipocytes.This conflicts with their low reported staining and may reflect cross-reactivity or background (HPA tissue IHC; general IHC practice).Compare HPA high cell populations on the same run, inspect morphology, and review the no-primary control before accepting a positive call (HPA tissue IHC; general IHC practice).
Expected high-staining cells remain blank.A technical failure is possible when colon glandular or bronchial respiratory epithelial cells lack signal (HPA tissue IHC; general IHC practice).Verify tissue and detection controls, then review dilution and retrieval against the antibody’s validated IHC instructions; the payload gives no CNOT4-specific retrieval setting (general IHC practice).
Only nuclear or luminal staining is visible.Nuclear CNOT4 is annotated, but HPA tissue IHC reports a cytoplasmic profile; luminal restriction lacks support from the supplied localisation and topology (UniProt O95628; HPA tissue IHC).Document the compartment, check cellular boundaries and controls, and avoid calling the result a match to the expected tissue pattern without cytoplasmic staining (general IHC practice).
Q: Can the tissue IHC pattern be used as an IF/ICC localisation call?HPA provides no main ICC-IF location or cell lines with ICC-IF images, and the listed antibody has no ICC validation entry (HPA subcellular; HPA antibodies).A: Treat UniProt’s cytoplasm-and-nucleus annotation as context only; establish IF/ICC localisation with its own controls and validation (UniProt O95628; general IF practice).

Sample controls for CNOT4 IHC & IF

🧪Start with adrenal gland: glandular cells should stain because HPA scores them High (HPA: adrenal gland, glandular cells, High). HPA detects CNOT4 in all 45 scored tissues, so there is no HPA-supported negative tissue; use no-primary and isotype controls, and treat other cells on the positive slide as unvalidated negatives rather than assuming they should be unstained (HPA: no negative rows; detected in all 45 scored tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: CNOT4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CNOT4; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Run a secondary-only slide and an antibody-class-matched isotype control from the same host species; where applicable, match monoclonal clonality (standard IHC practice). Use a CNOT4 knockout specimen or peptide competition as a biological specificity check—the selected catalog caption describes peptide blocking in human testis—and quench endogenous peroxidase when using chromogenic detection (selected-SKU IHC caption: peptide block; standard IHC practice).
⚠️Feasibility: No supplied target or application evidence reports a CNOT4-specific fixation window, fixation effect, or retrieval dependency; optimize retrieval empirically (supplied target/application evidence; standard IHC practice). The selected A08405 paraffin-section caption does not state a fixative, so it does not establish fixation or tissue processing (selected-SKU IHC caption: fixative unreported). The evidence does not establish that frozen sections or IF are easier, and it identifies no adrenal-specific artefact; assess nonspecific chromogenic background with the controls above (supplied target/application evidence; standard IHC practice). The selected A08405 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A08405).

HPA tissue IHC evidence for CNOT4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CNOT4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CNOT4 IHC Tips

Use compartment-aware controls to troubleshoot CNOT4 staining in paraffin sections (UniProt O95628: cytoplasm and nucleus; HPA: ubiquitous cytoplasmic expression).

How should I retrieve CNOT4 antigen when staining is weak in paraffin sections?
Use Tris-EDTA pH 9.0 heat-induced epitope retrieval at 95–98 °C for 20 min (page protocol). Allow sections to cool in retrieval buffer before washing, and keep heating and cooling consistent across the run (standard IHC practice). If staining remains weak, compare a shorter retrieval time on serial sections while holding antibody and detection conditions constant; excessive heating can damage tissue morphology (standard IHC practice). Assess both cytoplasmic and nuclear staining, since CNOT4 is reported in both compartments (UniProt O95628: cytoplasm and nucleus). The paraffin-section image for A08405 does not report fixation, so it cannot establish an optimal retrieval condition for every specimen (A08405 caption).
Could fixation explain weak or uneven CNOT4 staining?
Target-specific sensitivity of CNOT4 staining to fixative choice or fixation duration is unknown from the supplied evidence (A08405 caption: fixative unreported). Record the fixative, time to fixation, and fixation duration for each specimen, then compare sections processed together (standard IHC practice). If staining varies, evaluate matched sections with the same retrieval, antibody incubation, and detection settings before attributing the difference to fixation (standard IHC practice). Inspect morphology and staining at cut surfaces and deeper tissue separately, because uneven tissue processing can complicate interpretation (standard IHC practice). Neither the HPA staining profile nor CNOT4 topology or modifications establish a fixation-specific effect (HPA tissue IHC; UniProt O95628).
Should CNOT4 staining appear in nuclei, cytoplasm, or both?
Score nuclear and cytoplasmic staining separately because CNOT4 is reported in both locations (UniProt O95628: cytoplasm and nucleus). Ubiquitous cytoplasmic expression is the reported tissue-IHC pattern, so diffuse cytoplasmic signal can be plausible across several cell types (HPA tissue IHC: ubiquitous cytoplasmic expression). Use a nuclear counterstain and inspect high-power fields to distinguish nuclear chromogen from pigment or signal overlying nuclei (standard IHC practice). Treat a nuclear-only result as a finding to verify with controls, rather than assuming it is the expected tissue pattern (HPA tissue IHC; UniProt O95628). Compare adjacent sections processed identically when assessing a compartment shift (standard IHC practice).
How can isoforms or epitope accessibility affect the CNOT4 IHC pattern?
CNOT4 has 10 annotated isoforms, but the supplied A08405 caption does not map its antibody epitope (UniProt O95628: isoforms 1–10; A08405 caption). Therefore, staining alone cannot establish which isoform is present or whether all isoforms are detected (UniProt O95628: alternative splicing; A08405 caption). Use the peptide-blocked testis image as evidence that its pictured signal is peptide-competitive under those conditions, not as proof of isoform specificity (A08405 caption). If an unexpected compartment or cell pattern persists, compare an independently validated antibody with a documented, nonoverlapping epitope on serial sections (standard IHC practice). Keep retrieval and detection settings matched for that comparison (standard IHC practice).
How should I adapt the CNOT4 localisation check to multiplex IF?
Treat multiplex IF as a separate optimisation: the supplied HPA subcellular record lists no ICC/IF image examples for CNOT4 (HPA subcellular). Pair CNOT4 with a marker for the cell population being evaluated, and include a nuclear stain to assign cytoplasmic versus nuclear signal (standard IF practice; UniProt O95628: cytoplasm and nucleus). Choose fluorophores after checking unstained tissue autofluorescence, favouring a channel with clear separation from that background (standard IF practice). Because CNOT4 has no transmembrane segment and is reported intracellularly, permeabilise to reach cytoplasmic and nuclear epitopes; test a mild condition such as 0.1% Triton X-100 for 5 min (UniProt O95628: topology and localisation; standard IF practice).
What should I check when CNOT4 chromogen covers most of the section?
First compare no-primary and antibody-stained sections to separate detection-system background from antibody-dependent signal (standard IHC practice). Include an endogenous peroxidase block, such as 3% hydrogen peroxide for 10 min, when using peroxidase and DAB detection (standard IHC practice). Titrate the antibody and shorten chromogen development on adjacent sections if signal obscures cell boundaries; no working dilution is supplied here for A08405 (standard IHC practice; A08405 caption). Broad cytoplasmic staining alone is not evidence of background, because HPA reports ubiquitous cytoplasmic CNOT4 expression (HPA tissue IHC). Check whether signal follows tissue edges, folds, or damaged areas before scoring (standard IHC practice).
How should I quantify CNOT4 staining across different tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then report nuclear and cytoplasmic results separately (standard IHC practice; UniProt O95628: cytoplasm and nucleus). For cytoplasmic staining, record the percentage of positive cells and intensity by category, or calculate an H-score from 0–300 using intensity-weighted cell percentages (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or normalise spatial counts to analysed viable area in mm² (standard IHC practice). Exclude necrosis, folds, and section edges by a predefined rule, and keep staining and image thresholds consistent across specimens (standard IHC practice). Report cell type because HPA staining levels vary by cell population (HPA tissue IHC).
How can I distinguish true CNOT4 signal from staining artefacts?
A plausible result includes cytoplasmic staining, with possible nuclear staining, because CNOT4 is reported in both compartments and HPA describes ubiquitous cytoplasmic tissue expression (UniProt O95628; HPA tissue IHC). Check cell identity before calling a region anomalous: HPA reports high staining in several glandular, respiratory epithelial, neuronal, and glial populations, and low staining in adipocytes (HPA tissue IHC). Distrust signal confined to cut edges, necrotic areas, or tissue folds, and compare it with a no-primary control for endogenous enzyme or detection background (standard IHC practice). The peptide-blocked A08405 testis image supports peptide competition in that image, but does not independently establish specificity in every tissue or processing condition (A08405 caption).
Boster reagents

Best CNOT4 / CCR4-NOT transcription complex subunit 4 IHC Antibodies

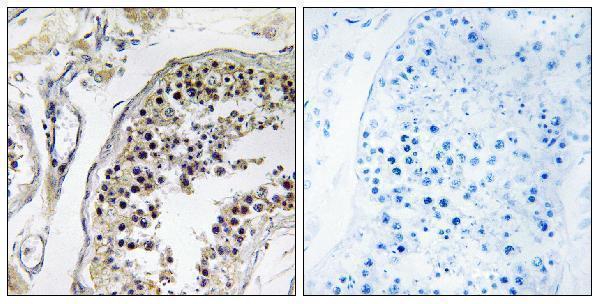
A08405 has real IHC data from paraffin-embedded human testis (IHC image caption); IF/ICC applications and human, mouse, and rat reactivity are listed in the catalog (catalog: applications and reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human testis tissue, using CNOT4 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-CNOT4 Antibody
Cat # A08405

A08405 will render with an IHC image of paraffin-embedded human testis and a peptide-blocked comparison (IHC image caption). Its catalog lists IHC, IF, and ICC applications and human, mouse, and rat reactivity; no IF image is supplied (catalog: applications, reactivity, and image alts).

Which to pick: Choose A08405 for tissue IHC because its own image shows paraffin-embedded human testis staining with a peptide-blocked comparison; the fixative is unreported (IHC image caption). For IF/ICC, A08405 is a listed rabbit polyclonal option, although the payload supplies no IF image (catalog: host, clonality, applications, and image alts). For human, mouse, or rat work, A08405 lists reactivity with all three species; the supplied IHC image documents human tissue only (catalog: reactivity; IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95628 (CNOT4_HUMAN, CCR4-NOT transcription complex subunit 4).
  2. Human Protein Atlas. CNOT4 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CNOT4 subcellular location (ICC-IF): Highest expression in PODO/TERT256: 22.1 nTPM.
  4. Human Protein Atlas. CNOT4 antibody validation summary (1 antibodies).
  5. Aberrant expression of MYD88 via RNA-controlling CNOT4 and EXOSC3 in colonic mucosa impacts generation of colonic cancer. Cancer science 2021 — PMC8645755.
  6. CNOT4 enhances the efficacy of anti-PD-1 immunotherapy in a model of non-small cell lung cancer. FEBS open bio 2020 — PMC7714061.
  7. PubMed PMID:10637334 — UniProt-cited evidence.
  8. PubMed PMID:14702039 — UniProt-cited evidence.
  9. PubMed PMID:12853948 — UniProt-cited evidence.