COL12A1 / Collagen alpha-1(XII) chain · IHC design guide

Design Immunohistochemistry for COL12A1

Plan COL12A1 staining in paraffin sections with the IHC-validated antibody at 1:100–1:300 (datasheet). Assess the extracellular matrix expected for a secreted protein (UniProt) alongside the low cytoplasmic staining and plasma positivity reported in tissues (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for COL12A1 (IHC for COL12A1): expected localisation Extracellular matrix expected (UniProt); cytoplasmic staining observed (HPA tissue IHC), antibody A05008, validated IHC image, and IHC protocol steps
Printable COL12A1 IHC protocol sheet — expected localisation Extracellular matrix expected (UniProt); cytoplasmic staining observed (HPA tissue IHC), antibody A05008, controls and protocol steps. Open the full COL12A1 IHC guide →

COL12A1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Extracellular matrix expected (UniProt); cytoplasmic staining observed (HPA tissue IHC)
Staining pattern Low cytoplasmic staining in several tissues; plasma positive (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Lung+4 more · see all
Negative control ⓘ Bone marrow+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A05008)
Caveat Secreted variants may uncouple tissue RNA and staining (HPA tissue IHC)
Regulation Ovary-enhanced RNA; IHC link uncertain (HPA tissue RNA)
Isoform / epitope 3 isoforms; validate the epitope against the mature chain (UniProt)
Section 1

Recommended COL12A1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by a published corneal tissue microarray protocol (PMC10466210).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human skeletal muscle tissue; fixative not specified (datasheet A05008)
FixationImage fixative and duration unreported (datasheet A05008); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-COL12A1, 1:100-1:300 (datasheet A05008)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCOL12A1-positive staining in macrophages of lung (HPA tissue IHC: High). HPA tissue profile: Low cytoplasmic expression in several tissues, including plasma positivity. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen-retrieval setting). The corneal study does not report retrieval (PMC10466210).
Section 2

What Is the Expected COL12A1 Staining Pattern?

COL12A1 is a secreted collagen associated with the extracellular matrix and has no transmembrane segment (UniProt Q99715). On paraffin sections, assess matrix-associated staining alongside reported cellular staining: lung macrophages are high, while several other listed cell types are medium (HPA: tissue IHC). HPA calls its tissue pattern uncertain because secretion and transcript discrepancies complicate interpretation (HPA: reliability Uncertain).

What am I looking at on my slide?
Matrix-associated staining near collagen-rich structures, with cellular signal in a supported tissue.An extracellular pattern fits COL12A1 association with type I collagen fibrils (UniProt Q99715). Judge the cellular component against the selected tissue and cell type (HPA: tissue IHC); HPA does not establish that every extracellular deposit will stain.
Strong, sharply nuclear staining dominates the section.A dominant nuclear pattern conflicts with the secreted extracellular assignment (UniProt Q99715) and HPA's reported cytoplasmic tissue profile (HPA: tissue IHC). Treat it as possible nonspecific staining and review controls before interpreting it as COL12A1.
Prominent signal appears in a cell population listed as not detected.For example, HPA reports no detection in bone marrow hematopoietic cells (HPA: bone marrow tissue IHC). Check antibody cross-reactivity and endogenous chromogen-generating activity using appropriate controls (general IHC practice); an HPA-negative population is not proof of absence.
Diffuse color covers cells, matrix, and empty-looking areas without a defined distribution.This is difficult to reconcile with a scored cell-type pattern (HPA: tissue IHC). Excess background can arise from detection or blocking conditions (general IHC practice); compare a no-primary control before assigning weak color to COL12A1.
No signal appears in a selected HPA-positive tissue.A negative result in lung macrophages, reported high by HPA, warrants an assay check (HPA: High in lung macrophages). Because HPA rates tissue reliability uncertain, first verify morphology, controls, and the antibody's IHC validation before concluding the target is absent.
💡Expected COL12A1 appearanceCall a section positive when staining has a coherent matrix-associated distribution consistent with secreted COL12A1 (UniProt Q99715), with cell-type signal matching the tissue selected—potentially high in lung macrophages (HPA: tissue IHC); isolated dominant nuclear color or diffuse control-matched color is suspect (general IHC practice).
How each factor affects the staining
Biological compartment (UniProt Q99715)COL12A1 is secreted and associated with collagen I-containing fibrils (UniProt Q99715). Interpret deposited extracellular signal in its tissue context; the HPA cellular profile alone cannot define all matrix deposits (HPA: tissue IHC, reliability Uncertain).
Cellular staining and source reliability (HPA: tissue IHC)HPA describes low cytoplasmic staining across several tissues, including plasma positivity, yet scores lung macrophages high (HPA: tissue IHC). Its reliability is Uncertain because secreted variants and splice or transcript discrepancies can separate RNA location from protein staining.
Isoforms and tissue distribution (UniProt Q99715)UniProt lists three isoforms and reports isoform-specific tissue distribution, including isoform 2 in lung, placenta, and kidney (UniProt Q99715). Without a supplied epitope map, a negative stain cannot identify which isoform is absent or whether the antibody detects each isoform.
IHC antibody evidence (HPA: antibody validation)HPA009143 has an Uncertain IHC assessment; HPA010021 has no supplied IHC status (HPA: antibodies). The latter's Approved ICC status is evidence for a different application (HPA: antibodies), so compare IHC results with tissue and assay controls.
Q: What should IF/ICC show? (HPA: subcellular ICC-IF)A: HPA reports mainly vesicles and additional cytosol in ICC-IF, with both locations Approved (HPA: subcellular ICC-IF). This cellular observation does not replace the extracellular assignment (UniProt Q99715) or validate an IHC-P pattern.
Epitope and retrieval limits (UniProt Q99715)The supplied record lists a signal peptide, glycosylation sites, and collagen-like regions (UniProt Q99715), but gives no antibody epitope or target-specific retrieval response. Select retrieval conditions from an IHC-validated antibody's documented method (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Lung macrophages are unstained despite acceptable tissue morphology (HPA: High in macrophages).A failed detection step or unsuitable antibody conditions are possible (general IHC practice); absence of COL12A1 is not established by this slide.Check the detection control, antibody IHC validation, and documented dilution and retrieval conditions; then repeat alongside a positive tissue control (general IHC practice).
Strong nuclear color appears across unrelated cell types.The distribution conflicts with secreted extracellular COL12A1 (UniProt Q99715) and HPA's cytoplasmic tissue description (HPA: tissue IHC).Review a no-primary control and detection background, then score only reproducible compartment and cell-type patterns (general IHC practice).
A tissue reported as not detected shows broad cellular color.Cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA's negative calls carry Uncertain tissue reliability (HPA: tissue IHC).Compare cell types within the section and run no-primary and detection controls before calling the staining COL12A1 (general IHC practice).
Weak, diffuse color obscures the tissue distribution.Background from antibody or detection conditions can hide a localized pattern (general IHC practice).Compare a no-primary control; review blocking, primary antibody dilution, wash steps, and chromogen development against the documented IHC method (general IHC practice).
Cellular staining is present but extracellular matrix looks negative.HPA reports cellular staining, while UniProt places COL12A1 in the extracellular matrix (HPA: tissue IHC; UniProt Q99715); these records do not explain this specific discrepancy.Record cellular and matrix scores separately, check the antibody's IHC evidence, and avoid inferring target absence from the matrix compartment alone (general IHC practice).
Results differ between tissues with reported isoform differences.UniProt reports tissue-specific isoform distribution (UniProt Q99715); the supplied evidence does not map the antibody epitope to those isoforms.Document the tissue and cell type for each slide, compare with its HPA IHC call, and avoid assigning an isoform from staining intensity alone (HPA: tissue IHC; UniProt Q99715).

Sample controls for COL12A1 IHC & IF

🧪Run lung first and assess staining in macrophages (High; HPA: lung macrophages). Use bone marrow hematopoietic cells as the negative comparison (Not detected; HPA: bone marrow hematopoietic cells). On the lung slide, cells without specific signal serve as internal negatives, while extracellular matrix staining should be assessed separately (UniProt Q99715: extracellular matrix localization).
Positive control tissue: Lung (Macrophages, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show COL12A1 in BJ [Human fibroblast], SiHa, U2OS, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a host-matched isotype control appropriate to the antibody's clonality, and a biological specificity control using knockout material or cognate-peptide blocking; peptide blocking is shown for catalog antibody A05008 in skeletal muscle (selected tissue-IHC caption; standard IHC practice). Check lung macrophages for endogenous peroxidase signal in chromogenic IHC and autofluorescence if assessing IF (HPA: lung macrophages; standard IHC/IF practice).
⚠️Feasibility: A target-specific fixation window and retrieval dependency are unreported in the supplied evidence; the paraffin-section caption for A05008 also leaves the fixative unreported (selected tissue-IHC caption). The evidence does not establish whether frozen sections or IF are easier for COL12A1 (selected tissue-IHC caption; HPA subcellular ICC-IF record). In lung, macrophage pigment and autofluorescence can complicate interpretation, so compare staining with the control slide (HPA: lung macrophages; standard IHC/IF practice).

HPA tissue IHC evidence for COL12A1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex. Caution, Splice and/or transcript discrepancy exists.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Macrophages High Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Colon Glandular cells Medium Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells Medium Protein (IHC) HPA →
Placenta Trophoblastic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Section 3

Advanced COL12A1 IHC Tips

Troubleshoot COL12A1 staining in paraffin sections by checking retrieval, extracellular localisation, antibody specificity and scoring before interpreting chromogenic signal.

How should I retrieve COL12A1 in paraffin sections when staining is weak?
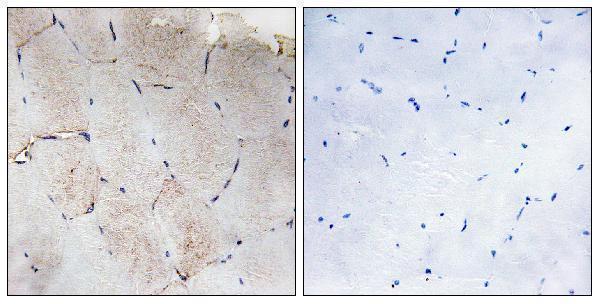
Use citrate buffer at pH 6.0 for heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval setting). If staining remains weak, compare a shorter and longer heating interval on adjacent sections while keeping the antibody and detection conditions constant (standard IHC optimisation practice). Assess whether signal appears along extracellular fibrillar structures, since COL12A1 is secreted into the extracellular matrix and interacts with type I collagen-containing fibrils (UniProt Q99715 localisation and function). Include the catalog antibody’s peptide-blocked comparison when available, because its paraffin-section image shows peptide blocking in human skeletal muscle (A05008 tissue-IHC caption).
Can I infer an optimal fixative for COL12A1 from the available tissue image?
No target-specific fixation condition or sensitivity is reported for the catalog antibody’s paraffin-embedded skeletal muscle image; the caption does not state a fixative (A05008 tissue-IHC caption). Record the actual fixative and fixation duration for each specimen, then compare sections processed under those conditions before changing retrieval or antibody incubation (standard IHC practice). Keep processing consistent across cases intended for comparison, because differences in preservation and epitope access can change chromogenic staining (standard IHC practice). Treat any observed fixation effect as an experimental result for that preparation, rather than inferring one from COL12A1 glycosylation or extracellular localisation (UniProt Q99715; A05008 tissue-IHC caption).
Where should convincing COL12A1 staining appear in a tissue section?
Prioritise extracellular and fibril-associated signal when judging tissue staining: COL12A1 is secreted into the extracellular matrix and interacts with type I collagen-containing fibrils (UniProt Q99715 localisation and function). It has no transmembrane segment, so a crisp membrane outline alone is insufficient evidence for the expected protein distribution (UniProt Q99715 topology). Compare stained structures with tissue morphology and a matched negative control, checking whether colour follows intact matrix rather than section folds or damaged edges (standard IHC practice). HPA also reports cellular cytoplasmic staining, but flags its tissue-IHC reliability as uncertain, so document cellular and extracellular patterns separately (HPA tissue IHC).
Could isoform choice or epitope masking explain different COL12A1 staining patterns?
Map the antibody’s stated immunogen to the COL12A1 sequence before comparing staining across specimens; the provided caption does not identify that epitope (A05008 tissue-IHC caption). COL12A1 has 3 listed isoforms, and isoforms 1 and 2 have different reported tissue distributions, so an epitope absent from one isoform could change what the antibody detects (UniProt Q99715 isoforms and tissue specificity). Its annotated glycosylation and hydroxyproline sites provide sequence context for epitope review, but do not establish masking in fixed sections (UniProt Q99715 modifications). Compare the mapped epitope, peptide-block result and staining morphology before attributing a difference to isoform expression (A05008 tissue-IHC caption; standard IHC practice).
How can I check a COL12A1 immunofluorescence pattern alongside chromogenic IHC?
Use a separate IF/ICC optimisation series and multiplex COL12A1 with a marker for the cell type being examined, while evaluating extracellular signal against the surrounding tissue structure (UniProt Q99715 localisation; standard IF practice). Choose spectrally separated fluorophores and inspect unstained tissue in each channel to identify autofluorescence before assigning a COL12A1 signal (standard IF practice). Because COL12A1 is secreted and has no transmembrane segment, begin with access to extracellular antigen; test permeabilisation separately if the antibody’s mapped epitope or a proposed intracellular pool requires it (UniProt Q99715 topology; standard IF practice). HPA reports vesicular and cytosolic IF localisation, which warrants comparison with its uncertain tissue-IHC profile rather than automatic transfer to paraffin-section scoring (HPA subcellular; HPA tissue IHC).
How do I distinguish matrix staining from chromogenic background?
Examine a no-primary control and the catalog antibody’s peptide-blocked comparison before accepting diffuse brown staining as COL12A1 (standard IHC practice; A05008 tissue-IHC caption). In a peroxidase-based workflow, include a peroxidase block before DAB development and check whether residual colour persists in the no-primary section (standard chromogenic IHC practice). Reduce nonspecific binding with an appropriate protein block and titrate the primary antibody and detection time against matched sections, recording each change (standard IHC practice). Genuine signal should be assessed against COL12A1’s extracellular, type I collagen-associated distribution; staining concentrated at folds, cut edges or damaged areas needs separate scrutiny (UniProt Q99715 localisation and function; standard IHC practice).
What should I measure when comparing COL12A1 IHC across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored compartment before measuring signal: matrix-associated staining is biologically relevant for secreted COL12A1, while HPA’s cellular staining carries an uncertain tissue-IHC reliability rating (UniProt Q99715 localisation; HPA tissue IHC). For matrix signal, measure DAB-positive area or optical density per mm² of annotated viable tissue, applying the same threshold and colour separation settings across slides (standard image-analysis practice). If a cellular question is specified, report percentage-positive cells or an H-score for the named cell population separately from matrix density (standard IHC scoring practice). Normalise to viable tissue area or the relevant cell count, and exclude folds, necrosis and edge artefacts using predefined rules (standard IHC quantification practice).
When is an apparent COL12A1-positive structure likely to be an artefact?
A reproducible extracellular pattern near collagen-containing fibrils fits COL12A1’s reported location and interaction better than isolated colour at a cut edge (UniProt Q99715 localisation and function; standard IHC interpretation practice). Check suspicious cellular staining against morphology and controls: HPA reports high staining in lung macrophages and medium staining in skeletal muscle myocytes, yet rates its tissue-IHC profile uncertain (HPA tissue IHC). Colour confined to necrotic regions, folds or section edges, or persisting after primary antibody omission, supports an artefact assessment (standard IHC practice). Residual endogenous peroxidase can also produce misleading DAB colour, so review the peroxidase block and no-primary control before calling a result positive (standard chromogenic IHC practice).
Boster reagents

Best COL12A1 / Collagen alpha-1(XII) chain IHC Antibodies

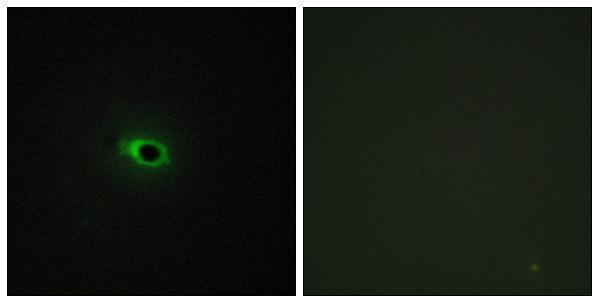
A05008 has IHC data from paraffin-embedded human skeletal muscle and IF data from COS7 cells (catalog image captions); listed reactivity covers human, mouse, and rat (catalog reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human skeletal muscle tissue, using Collagen XII alpha1 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-Collagen alpha-1(XII) chain COL12A1 Antibody
Cat # A05008

A05008 will render with an IHC figure from paraffin-embedded human skeletal muscle; its caption also describes peptide blocking (A05008 IHC image caption). The catalog lists IF and an IF image from COS7 cells, alongside human, mouse, and rat reactivity (A05008 applications, IF image caption, and reactivity).

Which to pick: Choose A05008 for tissue IHC because its own figure shows paraffin-embedded human skeletal muscle (A05008 IHC image caption); the fixative is unreported (A05008 IHC image caption). A05008 is also the listed IF option, with a COS7-cell image, while ICC validation is unreported (A05008 applications and IF image caption). For mouse or rat samples, A05008 lists reactivity with both species, although its IHC figure uses human tissue (A05008 reactivity and IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q99715 (COCA1_HUMAN, Collagen alpha-1(XII) chain).
  2. Human Protein Atlas. COL12A1 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. COL12A1 subcellular location (ICC-IF): Mainly localized to vesicles. In addition localized to the cytosol..
  4. Human Protein Atlas. COL12A1 antibody validation summary (2 antibodies).
  5. Collagen type XII is undetectable in keratoconus Bowman's layer. The British journal of ophthalmology 2024 — PMC10466210.
  6. Proteomic analysis of papillary thyroid carcinoma in the context of Hashimoto's thyroiditis. Scientific reports 2026 — PMC13039902.
  7. COL12A1 Acts as a Novel Prognosis Biomarker and Activates Cancer-Associated Fibroblasts in Pancreatic Cancer through Bioinformatics and Experimental Validation. Cancers 2023 — PMC10000532.
  8. Caffeine enhances antitumor T-cell activity by suppressing kynurenine pathway in colorectal cancer. Nature communications 2025 — PMC12216989.
  9. PubMed PMID:9143499 — UniProt-cited evidence.
  10. PubMed PMID:14574404 — UniProt-cited evidence.
  11. PubMed PMID:9826181 — UniProt-cited evidence.