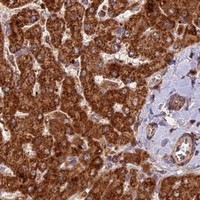
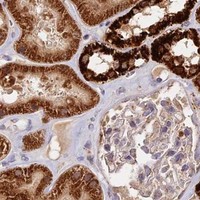
COX17 / Cytochrome c oxidase copper chaperone · IHC design guide

Design Immunohistochemistry for COX17

Plan COX17 staining in paraffin sections using the cytoplasmic tissue pattern (HPA tissue IHC) and its mitochondrial intermembrane space location (UniProt). This guide covers fixation, controls and chromogenic scoring, with high cardiomyocyte staining and undetected adipocytes as tissue references (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for COX17 (IHC for COX17): expected localisation Cytoplasmic tissue stain (HPA tissue IHC); intermembrane space location (UniProt), antibody A04584-1, validated IHC image, and IHC protocol steps
Printable COX17 IHC protocol sheet — expected localisation Cytoplasmic tissue stain (HPA tissue IHC); intermembrane space location (UniProt), antibody A04584-1, controls and protocol steps. Open the full COX17 IHC guide →

COX17 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue stain (HPA tissue IHC); intermembrane space location (UniProt)
Staining pattern Cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04584-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Ubiquitous expression (UniProt)
Isoform / epitope No listed isoforms; chain spans residues 2–63 (UniProt)
Section 1

Recommended COX17 IHC & IF Protocols

Compare the catalog antibody’s EDTA pH 8.0 IHC-P protocol (datasheet A04584-1) with the published mouse xenograft IHC protocol (PMC11340132).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A04584-1)
FixationImage fixative and duration unreported (datasheet A04584-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04584-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04584-1)
Primary antibodyRabbit anti-COX17, 1:50 recommended; image 1:100 (datasheet A04584-1)
Primary incubationOvernight at 4 °C (datasheet A04584-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04584-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCOX17-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A04584-1). Use sodium citrate retrieval when reproducing the published protocol (PMC11340132).
Section 2

What Is the Expected COX17 Staining Pattern?

COX17 localizes to the mitochondrial intermembrane space and cytoplasm and has no transmembrane segment (UniProt Q14061). In paraffin-section IHC, expect predominantly cytoplasmic staining in many tissues, including strong staining in selected glandular cells, bronchial basal cells, and cardiomyocytes (HPA tissue IHC). HPA rates the tissue pattern Supported but reports low consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in glandular cells of colon or duodenum, with little nuclear signal.This fits the reported High staining in those cells (HPA tissue IHC). Assess intensity in the named cells, rather than assigning one score to the entire section. A fine granular appearance can be consistent with mitochondrial COX17, but IHC alone does not confirm organelle identity (UniProt Q14061; HPA subcellular ICC-IF).
Predominantly nuclear staining, or a pattern confined to cell borders or extracellular material.These compartments do not match the reported cytoplasmic tissue pattern or mitochondrial intermembrane-space localization (HPA tissue IHC; UniProt Q14061). Treat the pattern as suspect and check morphology, primary-antibody omission, and detection controls before interpreting it as COX17.
Strong signal in adipocytes, ovarian stroma cells, or chondrocytes.HPA lists these specific cell populations as Not detected (HPA tissue IHC). Review cell identification and compare controls; cross-reactivity or endogenous detection activity are possible explanations. These entries describe cells, not a guarantee that every structure in adipose tissue, ovary, or soft tissue is negative.
Diffuse color across cells, stroma, and empty areas, with weak distinction between compartments.This does not resemble HPA's predominantly cytoplasmic pattern (HPA tissue IHC). Uneven reagent exposure, nonspecific binding, or detection background may obscure a genuine signal (general IHC practice). Judge staining against a no-primary control and the tissue morphology before scoring intensity.
No signal in glandular cells of a colon or duodenum section used as a positive control.Those cells are reported High by HPA, so a blank result warrants a technical check (HPA tissue IHC). Confirm that the expected cells are present, then review antibody concentration, retrieval and detection as general IHC workflow variables; the payload supplies no COX17-specific retrieval condition.
💡Expected COX17 appearanceCall a result consistent with COX17 when named High cell populations show clear, predominantly cytoplasmic staining above local background; isolated nuclear, extracellular, or uniformly diffuse color is suspect (HPA tissue IHC; UniProt Q14061).
How each factor affects the staining
Subcellular location and topologyCOX17 occupies the mitochondrial intermembrane space and cytoplasm and lacks a transmembrane segment (UniProt Q14061). Interpret chromogenic cytoplasmic color alongside cell morphology; its precise mitochondrial location cannot be established from a diffuse IHC signal alone.
Cell-specific comparison tissuesHPA reports High staining in heart cardiomyocytes and fallopian-tube ciliated cell bodies, but Not detected in adipocytes, ovarian stroma cells, and chondrocytes (HPA tissue IHC). Compare the identified cell types, since a mixed tissue can contain populations with different staining.
Confidence in tissue patternHPA labels its tissue IHC reliability Supported while noting low consistency between antibody staining and RNA expression (HPA tissue IHC). Use the reported pattern as a comparison, and avoid treating one unexpected intensity as definitive evidence of COX17 abundance.
IF/ICC: what localization should be expected?HPA reports a supported mitochondrial main location in ICC-IF images from A-431, U-251MG, and U2OS cells (HPA subcellular ICC-IF). This supports a mitochondrial interpretation in IF/ICC; it does not supply an IF protocol or prove that paraffin-section chromogenic staining will resolve individual mitochondria.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive glandular cells are blank.The staining run may have inadequate antibody signal or detection, or the expected cells may be absent from the section (general IHC practice; HPA tissue IHC: High in colon and duodenum glandular cells).Verify the cell population and run controls, then review catalog-antibody dilution, retrieval and detection settings (general IHC practice). No COX17-specific dilution or retrieval setting is supplied here.
Nuclei dominate the staining.The pattern conflicts with cytoplasmic tissue staining and the reported mitochondrial/cytoplasmic location (HPA tissue IHC; UniProt Q14061). Background or antibody binding outside the expected compartment is possible (general IHC practice).Inspect a no-primary control, check counterstain interpretation, and repeat with the IHC-validated antibody if needed (general IHC practice). Do not score nuclear color as a confirmed COX17-positive pattern.
Adipocytes or ovarian stroma cells appear strongly positive.Those cell types are listed as Not detected (HPA tissue IHC). Misidentified cells, nonspecific antibody binding, or endogenous detection activity could account for the discrepancy (general IHC practice).Recheck morphology and compare primary-omission and detection controls; investigate the specific stained cell population before assigning a tissue-wide positive result (general IHC practice).
Brown color covers the section with little cell-level contrast.A broadly diffuse deposit can mask the reported cytoplasmic pattern (HPA tissue IHC). Excess detection signal, nonspecific binding, or endogenous peroxidase activity are possible with peroxidase-based chromogenic IHC (general IHC practice).Compare a no-primary control; review blocking, washes, antibody concentration, and peroxidase control where applicable (general IHC practice). Reassess only after individual cells can be distinguished.
A positive area is much weaker than another reported High tissue.HPA's High categories describe named cells, and its tissue IHC has low consistency with RNA expression (HPA tissue IHC). Section composition and staining-run variation can also affect visual comparison (general IHC practice).Score the same identified cell type against local background and a control stained in the same run (general IHC practice). Avoid inferring a COX17 expression change from intensity alone.
IF/ICC shows diffuse fluorescence without a mitochondrial pattern.HPA's supported ICC-IF main location is mitochondrial (HPA subcellular ICC-IF). Diffuse fluorescence may reflect background or inadequate localization resolution (general IF practice).Compare appropriate IF controls and, if needed, a mitochondrial reference signal before assigning COX17 localization (general IF practice). Use the dedicated IF/ICC guide for its procedure.

Sample controls for COX17 IHC & IF

🧪Run colon first; glandular cells should stain (HPA: High in colon glandular cells). Run adipose tissue as a negative tissue control (HPA: Not detected in adipocytes); on the colon slide, assess non-glandular cells for background-only DAB, while recognizing that the supplied HPA row does not establish a specific internal negative cell type.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show COX17 in A-431, U-251MG, U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched rabbit IgG isotype control, and COX17-knockout tissue or cells as a biological negative (caption: rabbit primary antibody; standard IHC practice). Block endogenous peroxidase and check for residual DAB background in colon sections (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04584-1 tissue-IHC caption does not state the fixative. The reported paraffin-section procedure uses heat retrieval in EDTA at pH 8.0, followed by primary antibody at 1:100 overnight at 4°C (selected-SKU tissue-IHC caption). Frozen-section performance and whether IF is easier are unreported; mitochondrial ICC-IF localization is supported in A-431, U-251MG, and U2OS (HPA subcellular).

HPA tissue IHC evidence for COX17

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Basal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Soft tissue Chondrocytes Not detected Protein (IHC) HPA →
Section 3

Advanced COX17 IHC Tips

Troubleshoot COX17 staining in paraffin sections by checking retrieval, controls, compartment pattern and cell-specific scoring before interpreting chromogenic signal.

What retrieval should I start with for weak COX17 staining in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A04584-1). The selected COX17 image used that retrieval, followed by 10% goat serum blocking and a 1:100 primary dilution overnight at 4°C (datasheet A04584-1). If staining remains weak, compare carefully controlled changes in heating time while keeping section thickness, antibody dilution and detection constant; excessive heating can damage tissue morphology (standard IHC practice). Use a known positive tissue section alongside the test section, and judge improvement by stronger cell-associated signal without increased diffuse background (HPA: high in colon glandular cells; standard IHC practice).
Could fixation explain weak or uneven COX17 IHC signal?
The selected image documents a paraffin-embedded human colon cancer section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A04584-1). Record the actual fixative and fixation duration for each specimen before comparing staining across batches (standard IHC practice). Compare sections processed together using the same EDTA pH 8.0 retrieval, 1:100 primary dilution and overnight 4°C incubation reported for the selected image (datasheet A04584-1). If signal varies, inspect morphology and staining in internal positive cells before attributing the difference to fixation; neither tissue expression patterns nor protein features establish a COX17-specific fixation effect (HPA: cytoplasmic expression in most tissues; UniProt Q14061; standard IHC practice).
What staining pattern fits COX17, and when is a compartment mismatch suspicious?
COX17 is reported in the mitochondrial intermembrane space and cytoplasm, with no transmembrane segment (UniProt Q14061 topology and subcellular location). In chromogenic IHC, assess signal within the cell body and compare its distribution with cell morphology; a light-microscopy DAB pattern alone cannot prove intermembrane-space localisation (standard IHC practice). Mitochondrial localisation has independent ICC/IF support, while tissue IHC describes cytoplasmic expression in most tissues (HPA subcellular: mitochondria supported; HPA tissue: cytoplasmic expression). Predominantly nuclear or extracellular staining should trigger review of background, counterstain and section integrity before being scored as COX17 (UniProt Q14061 subcellular location; standard IHC practice).
How should I assess an unexpected COX17 staining pattern when the antibody epitope is unclear?
The supplied record lists 0 isoforms and a 63-amino-acid precursor, so an isoform explanation is unsupported here (UniProt Q14061). Its annotated chain spans residues 2–63, and its CHCH domain spans 23–63; these locations do not identify the catalog antibody’s epitope (UniProt Q14061). Phosphoserine 14 and acetyllysines 18 and 30 are annotated, but their effects on this antibody’s IHC staining are unknown (UniProt Q14061). Check the antibody’s documented immunogen or epitope, then compare retrieval and staining controls before attributing an unexpected pattern to processing or modification (standard IHC practice).
How can IF help investigate an ambiguous COX17 IHC pattern?
Use IF as a complementary localisation check when chromogenic IHC cannot resolve intracellular distribution (standard microscopy practice). Multiplex COX17 with a marker identifying the expected cell type in the sampled tissue, and consider a mitochondrial marker when testing compartment agreement (HPA tissue: cell-specific expression; HPA subcellular: mitochondria supported). Choose spectrally separated fluorophores and inspect unstained tissue to select channels with less autofluorescence (standard IF practice). For an intermembrane-space epitope, optimise permeabilisation for access across mitochondrial membranes, but first confirm the antibody’s epitope because its position is not supplied (UniProt Q14061 subcellular location; standard IF practice). Interpret IF alongside the IHC section’s cell pattern and controls rather than treating agreement alone as antibody specificity (standard IHC/IF practice).
How do I reduce diffuse brown staining without losing plausible COX17 signal?
Run a no-primary control to reveal detection-related background, and include a peroxidase block before HRP/DAB development (standard chromogenic IHC practice). The selected section used 10% goat serum blocking, 1:100 rabbit primary overnight at 4°C, and a peroxidase-conjugated secondary for 30 minutes at 37°C (datasheet A04584-1). If background persists, titrate primary antibody and DAB development while keeping retrieval at EDTA pH 8.0 for the comparison (datasheet A04584-1; standard IHC practice). Judge whether changes preserve cell-associated cytoplasmic signal in expected positive areas while reducing staining in the no-primary control (HPA tissue: cytoplasmic expression; standard IHC practice).
What should I score when comparing COX17 IHC across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and cell type before scoring, since COX17 tissue staining is described as cytoplasmic and varies by cell population (HPA tissue IHC). Report the percentage of positive eligible cells and staining intensity, or calculate an H-score from intensity categories 0–3 with a possible range of 0–300 (standard IHC scoring practice). Normalise counts to the number of eligible cells, or positive-cell density to analysed tissue area in mm², and apply one threshold across the comparison (standard image analysis practice). Keep acquisition, counterstain assessment and exclusion rules for damaged or necrotic areas consistent; report the scored compartment and replicate sections (standard IHC practice).
When should I doubt an apparent COX17-positive result?
A credible result should show cell-associated staining in a plausible cytoplasmic distribution, interpreted against the sampled cell type and control sections (HPA tissue: cytoplasmic expression; standard IHC practice). Colon glandular cells are reported as high, whereas adipocytes are reported as not detected; these patterns offer comparison points rather than absolute specificity tests (HPA tissue IHC). Question predominantly nuclear, extracellular, section-edge or necrotic staining, especially if similar brown signal appears in the no-primary control (UniProt Q14061 subcellular location; standard IHC practice). Review peroxidase blocking and DAB development because endogenous enzyme activity can mimic chromogenic signal; HPA rates tissue staining as supported but reports low agreement with RNA expression (standard IHC practice; HPA tissue IHC reliability).
Boster reagents

Best COX17 / Cytochrome c oxidase copper chaperone IHC Antibodies

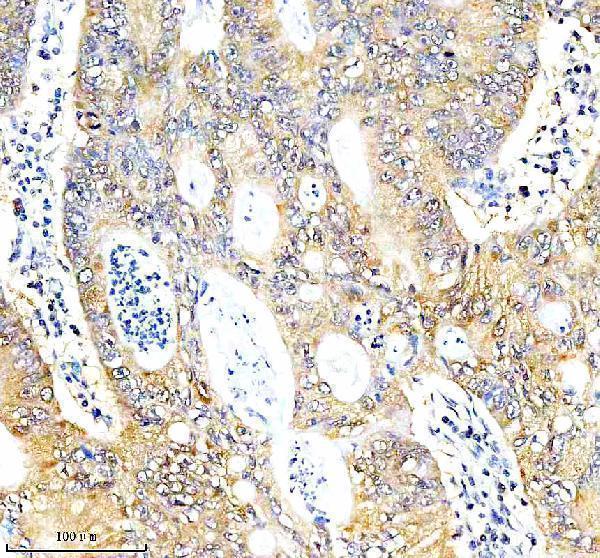
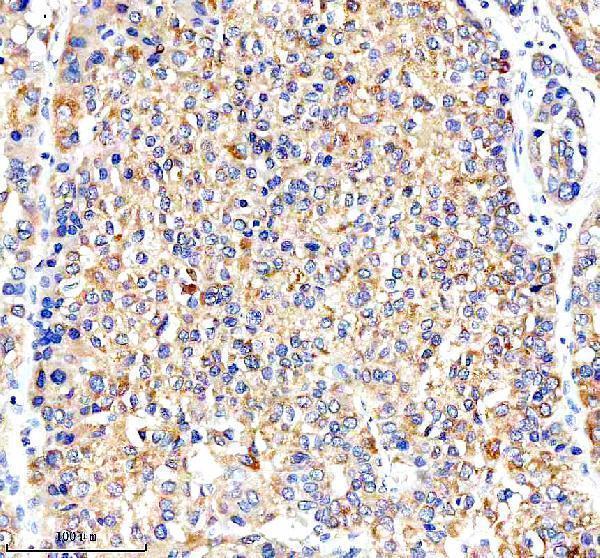
A04584-1 has IHC images from paraffin-embedded human colon and liver cancer and mouse and rat heart (catalog IHC captions). IF/ICC is listed for human, mouse, and rat (catalog applications/reactivity).

Real IHC data IHC analysis of COX17 using anti-COX17 antibody (A04584-1). COX17 was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:100 rabbit anti-COX17 Antibody (A04584-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-COX17 Antibody ®
Cat # A04584-1

A04584-1 will render with an IHC figure from a paraffin-embedded human colon cancer section (catalog IHC caption). Its other IHC captions document human liver cancer and mouse and rat heart; IF/ICC is listed, with no IF image supplied (catalog IHC captions; applications; if_image_alts).

Which to pick: Choose A04584-1 for paraffin-section IHC: its captions document EDTA retrieval at pH 8.0 and primary antibody at 1:100 overnight (catalog IHC captions). Choose the same rabbit polyclonal antibody for IF/ICC or cross-species work because those applications and human, mouse, and rat reactivity are listed (catalog host; dilution_raw; applications; reactivity). The IHC captions report paraffin embedding but do not report the fixative (catalog IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14061 (COX17_HUMAN, Cytochrome c oxidase copper chaperone).
  2. Human Protein Atlas. COX17 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. COX17 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. COX17 antibody validation summary (2 antibodies).
  5. Curcumin suppresses copper accumulation in non-small cell lung cancer by binding ATOX1. BMC pharmacology & toxicology 2024 — PMC11340132.
  6. Integrative analysis of single-cell and bulk RNA seq to reveal the prognostic model and tumor microenvironment remodeling mechanisms of cuproptosis-related genes in colorectal cancer. Aging 2023 — PMC10756095.
  7. Copper and cuproptosis-related genes in hepatocellular carcinoma: therapeutic biomarkers targeting tumor immune microenvironment and immune checkpoints. Frontiers in immunology 2023 — PMC10157396.
  8. PubMed PMID:9050918 — UniProt-cited evidence.
  9. PubMed PMID:10982038 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.