COX6B1 / Cytochrome c oxidase subunit 6B1 · IHC design guide

Design Immunohistochemistry for COX6B1

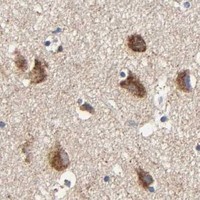
Plan chromogenic COX6B1 IHC around the granular cytoplasmic pattern seen in tissue (HPA tissue IHC) and its inner mitochondrial membrane location (UniProt). Colon glandular cells stain strongly, while bone marrow hematopoietic cells have no detected staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for COX6B1 (IHC for COX6B1): expected localisation Granular cytoplasm in tissue (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A10285-2, validated IHC image, and IHC protocol steps
Printable COX6B1 IHC protocol sheet — expected localisation Granular cytoplasm in tissue (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A10285-2, controls and protocol steps. Open the full COX6B1 IHC guide →

COX6B1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm in tissue (HPA tissue IHC); inner mitochondrial membrane (UniProt)
Staining pattern Widespread granular cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A10285-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Bone marrow+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A10285-2); verify before use.
Caveat Bone marrow hematopoietic cells: not detected (HPA tissue IHC)
Regulation Regulation not annotated (UniProt)
Isoform / epitope No annotated isoforms; chain 2–86; no transmembrane segment (UniProt)
Section 1

Recommended COX6B1 IHC & IF Protocols

The catalog antibody protocol uses EDTA retrieval (datasheet: A10285-2). These published tissue section protocols provide COX6B1 staining conditions for comparison (PMC12800125; PMC7646598; PMC10965397).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human placenta tissue; fixative not specified (datasheet A10285-2)
FixationImage fixative and duration unreported (datasheet A10285-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A10285-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A10285-2)
Primary antibodyRabbit anti-COX6B1, 2 μg/ml (datasheet A10285-2)
Primary incubationOvernight at 4 °C (datasheet A10285-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A10285-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCOX6B1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 retrieval (datasheet: A10285-2); citrate retrieval is documented in two published protocols (PMC7646598; PMC10965397).
Section 2

What Is the Expected COX6B1 Staining Pattern?

COX6B1 is a mitochondrial inner-membrane protein with no transmembrane segment (UniProt P14854: location and topology). In paraffin-section IHC, expect granular cytoplasmic staining across many tissues, including glandular, respiratory epithelial and neuronal cells (HPA: ubiquitous granular cytoplasmic profile; High in the listed cells). HPA rates the tissue staining Supported, with medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Granular cytoplasmic signal in adrenal or colonic glandular cells, bronchial respiratory epithelial cells, or cortical neurons.This fits the reported tissue pattern and High staining in those cell populations (HPA: tissue IHC). The granules are consistent with mitochondrial localization (UniProt P14854: inner membrane); chromogenic IHC alone does not resolve the inner membrane.
Predominantly nuclear, membrane-outline, or extracellular staining instead of cytoplasmic granules.Those compartments conflict with the reported granular cytoplasmic pattern (HPA: tissue IHC) and mitochondrial location (UniProt P14854: location). Treat the signal as suspect; review controls and detection conditions before assigning it to COX6B1.
Strong staining in bone-marrow hematopoietic cells or ovarian stromal cells while expected positive cells stain appropriately.These populations were Not detected in the HPA IHC observations (HPA: bone marrow; ovarian stroma). Cross-reactivity or endogenous chromogen-generating activity is possible; the discrepancy alone does not establish its cause.
Diffuse color across tissue, including spaces between cells, obscures any granular cytoplasmic pattern.That appearance cannot be scored reliably against the HPA profile (HPA: granular cytoplasmic staining). In chromogenic IHC, nonspecific binding, incomplete washing, or detection background can produce diffuse signal (general IHC practice).
No convincing signal in a well-preserved section containing adrenal glandular cells or cerebellar Purkinje cells.Both cell populations have High staining in the HPA observations (HPA: adrenal gland; cerebellum). Check the run before interpreting absence as biology: a failed primary or detection step, or unsuitable assay conditions, can remove signal (general IHC practice).
💡Expected COX6B1 appearanceCall positive a discernible granular cytoplasmic signal in HPA High cell populations, such as glandular or neuronal cells; uniform nuclear, extracellular, or diffuse tissue-wide color is suspect (HPA: tissue IHC profile and levels; UniProt P14854: mitochondrial location).
How each factor affects the staining
Compartment and optical resolutionUniProt places COX6B1 at the mitochondrial inner membrane and reports no transmembrane segment (UniProt P14854: location and topology). Score the visible cytoplasmic granules in IHC; do not claim that chromogenic granules identify a membrane leaflet (general IHC practice).
Cell population selected for comparisonHPA reports High staining in several glandular, respiratory epithelial and neuronal populations, Low staining in smooth muscle cells, fibroblasts and adipocytes, and Not detected in specified hematopoietic and ovarian stromal cells (HPA: tissue IHC). Compare like cell types when judging intensity.
Evidence strengthThe tissue profile is Supported, with medium staining-to-RNA consistency; HPA004192 is listed as Supported for IHC (HPA: reliability; antibody validation). These ratings support pattern checking but do not make every discrepant cell an assay failure.
Processing and isoform annotationUniProt lists a chain spanning residues 2–86, no signal peptide or propeptide, and 0 annotated isoforms (UniProt P14854: processing and isoforms). This record supplies no basis for a shedding pattern or isoform-specific IHC interpretation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known High cells show no staining.The result conflicts with the HPA observations, but does not identify a COX6B1-specific failure mode (HPA: High in adrenal glandular cells and Purkinje cells).Verify the section contains the expected cells, then check the primary-antibody, detection and chromogen steps with run controls (general IHC practice). Interpret a negative result only after the controls perform as expected.
Signal is weak and lacks distinct cytoplasmic granules.The readout is below the pattern needed to assess the HPA profile (HPA: granular cytoplasmic staining); the supplied sources do not establish target-specific retrieval or fixation sensitivity.Review general IHC variables such as retrieval conditions, primary concentration and detection development against the assay's controls (general IHC practice). Do not infer a COX6B1 fixation effect from the tissue profile.
Diffuse tissue-wide color masks cell boundaries.Background from nonspecific binding or the chromogenic detection system is possible (general IHC practice); it does not match the HPA granular cytoplasmic profile (HPA: tissue IHC).Inspect a no-primary control, wash and blocking steps, and detection timing (general IHC practice). Reassess cell-specific granules only after background is reduced.
Nuclei dominate the stain.Nuclear predominance conflicts with mitochondrial localization (UniProt P14854: location) and the observed cytoplasmic profile (HPA: tissue IHC).Check the counterstain and no-primary control, then review primary and detection conditions (general IHC practice). Do not score nuclear color as COX6B1 without independent validation.
Cells reported as Not detected stain strongly.Strong color in bone-marrow hematopoietic or ovarian stromal cells differs from the HPA observations (HPA: tissue IHC). Cross-reactivity or endogenous detection activity may contribute (general IHC practice).Compare with a High-staining cell population and a no-primary control; assess endogenous detection activity for the chromogen system used (general IHC practice). Keep the discrepancy explicit in scoring.
Q: What should an IF/ICC image show?HPA reports mitochondria as the supported main location and the sperm principal piece as an additional approved location (HPA: subcellular ICC-IF).A: Look for a mitochondrial distribution, using an appropriate mitochondrial reference when checking colocalization (HPA: subcellular ICC-IF; general IF practice). The sperm principal-piece observation is an additional context, not an IHC tissue-scoring rule.

Sample controls for COX6B1 IHC & IF

🧪Run bronchus first and look for staining in respiratory epithelial cells (HPA: High in bronchus respiratory epithelial cells); use bone marrow hematopoietic cells as the negative tissue comparator (HPA: Not detected in bone marrow hematopoietic cells). On the bronchus slide, cells that lack specific staining should show counterstain without a distinct cytoplasmic reaction, but adjacent cell types are not validated as COX6B1-negative by the supplied HPA row (HPA: bronchus respiratory epithelial cells High).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show COX6B1 in A-431, U-251MG, U2OS, Sperm, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a concentration-matched nonimmune rabbit IgG isotype control, and COX6B1 knockout material where available (caption: rabbit anti-COX6B1 antibody; standard IHC practice). Quench endogenous peroxidase and check for endogenous biotin background if using the caption’s biotin-based DAB detection on bronchus (caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected SKU’s paraffin-section caption does not state the fixative (caption: A10285-2, fixative not stated). Heat retrieval in EDTA at pH 8.0 is a documented IHC starting point, but retrieval dependence has not been established (caption: placenta IHC, EDTA pH 8.0). The supplied evidence does not establish whether frozen sections or IF are easier; for bronchus, assess airway mucus and inflammatory-cell peroxidase as possible staining background (HPA: bronchus respiratory epithelial cells High; standard IHC practice).

HPA tissue IHC evidence for COX6B1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Section 3

Advanced COX6B1 IHC Tips

Troubleshoot COX6B1 staining in paraffin sections by checking retrieval, compartment, controls and scoring before interpreting signal intensity.

Which retrieval condition should I try first for weak COX6B1 staining?
Start with heat-mediated EDTA pH 8.0 antigen retrieval for paraffin sections (datasheet A10285-2). The selected image used this condition before 10% goat serum blocking and 2 µg/mL primary antibody overnight at 4°C (datasheet A10285-2). If staining is weak, compare retrieval duration on serial sections while holding antibody concentration and detection constant (standard IHC practice). Include a known positive section, such as the documented human placenta section, in each comparison (datasheet A10285-2). Judge improvement by a granular cytoplasmic pattern with preserved morphology, rather than by stronger diffuse color alone (HPA: ubiquitous granular cytoplasmic expression; standard IHC practice).
Could fixation explain variable COX6B1 staining between paraffin blocks?
Target-specific fixation sensitivity is unknown because the selected tissue image identifies a paraffin-embedded section but does not state its fixative (datasheet A10285-2). Record each block’s fixative and fixation duration, then compare sections processed with the same EDTA pH 8.0 retrieval and detection conditions (datasheet A10285-2; standard IHC practice). Excessive or inconsistent fixation can change antigen accessibility in IHC generally, so assess morphology and staining together (standard IHC practice). Use a documented positive section in the same run to distinguish a block-dependent problem from a staining-run problem (datasheet A10285-2; standard IHC practice). Neither mitochondrial topology nor tissue-expression patterns establish a COX6B1-specific fixation effect (UniProt P14854 topology; HPA tissue IHC).
Where should convincing COX6B1 chromogenic signal appear?
Expect a granular cytoplasmic pattern in tissue sections, consistent with the reported ubiquitous IHC profile (HPA tissue IHC). COX6B1 is assigned to the mitochondrial inner membrane, and its main subcellular location is supported as mitochondrial (UniProt P14854 localisation; HPA subcellular). In chromogenic IHC, evaluate granules within intact cells against adjacent negative space and the nuclear counterstain; routine light microscopy does not resolve the inner membrane itself (standard IHC practice). High staining has been reported in adrenal glandular and cerebellar Purkinje cells, while ovarian stromal cells were not detected in the cited survey (HPA tissue IHC). Predominantly nuclear or extracellular color warrants investigation before assignment to COX6B1 (UniProt P14854 localisation; standard IHC practice).
How should epitope uncertainty affect antibody selection and retrieval?
COX6B1 has no annotated isoforms in the supplied record, but its epitope is not specified here (UniProt P14854 record; datasheet A10285-2). The mature chain spans residues 2–86, includes a CHCH domain at 27–73, and has N-acetylalanine at residue 2 (UniProt P14854 processing and modifications). None of those annotations identifies where this antibody binds or establishes its accessibility after processing (UniProt P14854 record; standard IHC practice). Check documented epitope and specificity information before interpreting a changed retrieval response or possible recognition of the related COX6B2 subunit (UniProt P14854 complex-IV composition; standard IHC practice). Compare staining with an independent, validated antibody where available and retain compartment and negative controls (standard IHC practice).
How can I check the same localisation by multiplex IF?
For a separate IF experiment, pair COX6B1 with a validated marker of the expected cell type, such as a glandular-cell marker when examining colon, and a mitochondrial reference marker (HPA: high in colon glandular cells; standard IF practice). Choose spectrally separated fluorophores and assess an unstained section for tissue autofluorescence before assigning a weak mitochondrial signal (standard IF practice). Because the supplied topology gives no transmembrane segment but does not specify the antibody epitope’s membrane-facing side, test permeabilisation for epitope access rather than assuming a side (UniProt P14854 topology; standard IF practice). Compare single-stain controls with the multiplex image to detect channel bleed-through (standard IF practice). HPA reports mainly mitochondrial IF localisation (HPA subcellular).
What should I check when DAB obscures granular COX6B1 staining?
Compare the stained section with a no-primary control to assess detection-system color that does not require the COX6B1 antibody (standard IHC practice). Apply an endogenous peroxidase block before peroxidase-based DAB detection and check whether background remains after blocking (standard IHC practice). The selected protocol used 10% goat serum, a biotinylated secondary antibody, a streptavidin–biotin complex and DAB (datasheet A10285-2). With that detection scheme, assess endogenous biotin or nonspecific secondary binding if color persists in controls (datasheet A10285-2; standard IHC practice). Shorten DAB development or adjust antibody concentration only while retaining a positive control and the expected granular cytoplasmic pattern (HPA tissue IHC; standard IHC practice).
How should I score COX6B1 across specimens with different cellularity? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue area before scoring, then apply the same segmentation and color threshold to every section (standard IHC practice). Report an H-score or the percentage of positive cells with intensity categories, using only eligible intact cells in the denominator (standard IHC practice). For spatial comparisons, report positive-cell density per mm² of viable tissue and record the number of eligible cells or area assessed (standard IHC practice). Keep retrieval, counterstain, DAB development and imaging settings consistent across the comparison (standard IHC practice). Interpret intensity alongside cell composition because HPA reports high signal in some glandular and neuronal populations but no detected signal in ovarian stromal cells (HPA tissue IHC).
How do I distinguish genuine COX6B1 staining from artefact?
A credible positive is granular cytoplasmic staining in intact cells, consistent with mitochondrial localisation, rather than isolated nuclear or extracellular deposits (HPA tissue IHC; UniProt P14854 localisation). Check whether the stained cell population fits the specimen: HPA reports high signal in bronchial respiratory epithelial cells and no detected signal in bone-marrow hematopoietic cells (HPA tissue IHC). Discount color confined to cut edges, folds or necrotic areas when comparable intact tissue lacks that pattern (standard IHC practice). Use no-primary and peroxidase-block controls to investigate endogenous enzyme activity or detection background, especially with DAB (standard IHC practice). HPA labels tissue staining supported with medium RNA–protein consistency, so interpret an unexpected pattern with independent controls (HPA tissue IHC; standard IHC practice).
Boster reagents

Best COX6B1 / Cytochrome c oxidase subunit 6B1 IHC Antibodies

Anti-COX6B1 antibodies have IHC images from human paraffin sections and IF images from A549 cells (catalog image captions); listed reactivity spans human, mouse, and rat (catalog reactivity).

Real IHC data IHC analysis of COX6B1 using anti-COX6B1 antibody (A10285-2). COX6B1 was detected in a paraffin-embedded section of human placenta tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-COX6B1 Antibody (A10285-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-COX6B1 Antibody ®
Cat # A10285-2
Real IF data Fluorescent image of A549 cells stained with COX6B1 Antibody (N-term). A10285-1 was diluted at 1:25 dilution. An Alexa Fluor 488-conjugated goat anti-rabbit lgG at 1:400 dilution was used as the secondary antibody (green). DAPI was used to stain the cell nuclear (blue). Cytoplasmic actin was counterstained with Alexa Fluor® 555 conjugated with Phalloidin (red).
Anti-COX6B1 Antibody (N-term)
Cat # A10285-1

A10285-2 has IHC images from human paraffin sections of placenta, colorectal cancer, liver cancer, and gallbladder adenocarcinoma, plus an IF image from A549 cells (A10285-2 image captions). A10285-1 has an IF image from A549 cells and is listed for human IF (A10285-1 image caption; catalog applications and reactivity).

Which to pick: Choose A10285-2 for tissue IHC: its images document paraffin sections with EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A10285-2 IHC captions). For IF/ICC, A10285-2 lists both applications and has an A549 IF image, while polyclonal A10285-1 has an A549 IF image at 1:25 and lists IF but not ICC (catalog applications; A10285-2 IF caption; A10285-1 dilution field and IF caption). For mouse or rat samples, A10285-2 is the listed option, though its supplied IHC and IF images use human samples (catalog reactivity; A10285-2 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P14854 (CX6B1_HUMAN, Cytochrome c oxidase subunit 6B1).
  2. Human Protein Atlas. COX6B1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. COX6B1 subcellular location (ICC-IF): Mainly localized to the mitochondria. In addition localized to the principal piece..
  4. Human Protein Atlas. COX6B1 antibody validation summary (1 antibodies).
  5. Identification of potential biomarkers associated with mitochondrial oxidative stress in idiopathic pulmonary arterial hypertension via bioinformatic and experimental analysis. Scientific reports 2025 — PMC12800125.
  6. Glioma cells are resistant to inflammation‑induced alterations of mitochondrial dynamics. International journal of oncology 2020 — PMC7646598.
  7. Integrative analysis of metabolism subtypes and identification of prognostic metabolism-related genes for glioblastoma. Bioscience reports 2024 — PMC10965397.
  8. PubMed PMID:2537962 — UniProt-cited evidence.
  9. PubMed PMID:2172092 — UniProt-cited evidence.
  10. PubMed PMID:1651883 — UniProt-cited evidence.