This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic COX6C IHC in paraffin sections using granular cytoplasmic staining as the tissue reference (HPA tissue IHC). Compare high staining in glandular cells with low staining in adipocytes and chondrocytes (HPA tissue IHC), and titrate the catalog antibody within 1:50–1:200 (datasheet: IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt) | |
| Staining pattern | Granular cytoplasm in glandular cells and neurons (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Adipocytes and chondrocytes may stain weakly (HPA tissue IHC) | |
| Regulation | Regulation unreported (UniProt) | |
| Isoform / epitope | No isoforms or processing annotated; one 75-aa chain (UniProt) |
The catalog antibody’s IHC-P protocol and one published COX6C tissue microarray staining workflow (PMC10799076) provide starting conditions for paraffin sections.
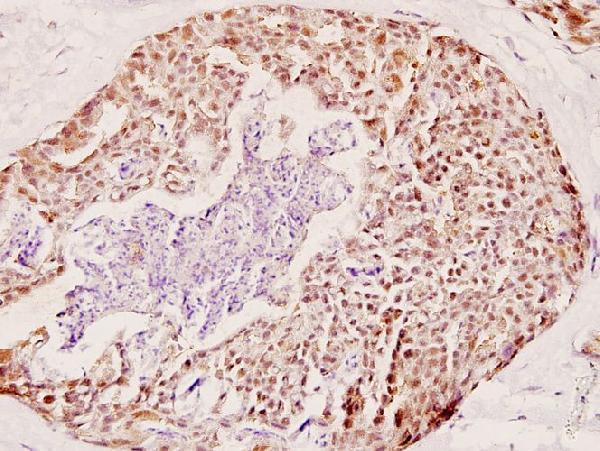
| Sample | Paraffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A11443-1) |
| Fixation | Image fixative and duration unreported (datasheet A11443-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-COX6C, 1:50-1:200 (datasheet A11443-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | COX6C-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a granular pattern. No signal in the no-primary control. |
COX6C is an inner mitochondrial membrane component with a transmembrane segment spanning residues 14–54 (UniProt P09669 topology). On IHC sections, expect granular cytoplasmic staining, especially in the glandular, respiratory epithelial, and neuronal populations reported as High by HPA (HPA tissue IHC). HPA rates the tissue staining evidence Enhanced, reflecting high consistency between antibody staining and RNA expression data (HPA tissue IHC).
| Granular cytoplasmic staining in adrenal or colon glandular cells. | This matches HPA’s reported pattern and High staining in those cells (HPA tissue IHC). The appearance is consistent with mitochondrial localisation (UniProt P09669; HPA subcellular), though chromogenic granules alone do not prove organelle identity (standard IHC interpretation). Assess staining within the named cell population rather than assigning one score to the entire tissue (standard IHC practice). |
| Predominantly nuclear or sharply outlined plasma membrane staining. | That compartment conflicts with the inner mitochondrial membrane annotation and reported granular cytoplasmic IHC pattern (UniProt P09669 topology; HPA tissue IHC). Treat it as a possible nonspecific result, and compare the same tissue with appropriate staining controls before interpreting it as COX6C (standard IHC practice). |
| Strong staining in an unexpected cell population, especially where the reference pattern is Low. | HPA reports Low staining in adipocytes and chondrocytes, but does not designate them negative (HPA tissue IHC). A strong result there warrants checks for cross-reactivity or endogenous detection activity (standard IHC practice). Tissue-wide expression is plausible because HPA reports low RNA tissue specificity, so cell identity and staining pattern matter (HPA tissue IHC). |
| Uniform haze or widespread chromogen that obscures cell boundaries. | This does not resemble the reported granular cytoplasmic pattern (HPA tissue IHC). Background may arise from nonspecific reagent binding, endogenous detection activity, or excessive chromogen development (standard IHC practice). A background pattern alone cannot establish whether COX6C is present or absent in the affected cells (standard IHC interpretation). |
| No visible signal in a well-preserved adrenal gland or colon glandular compartment. | HPA reports High staining in these glandular cells, so an entirely blank expected-positive compartment calls for a run check (HPA tissue IHC). Review slide integrity, retrieval, antibody application, and detection controls (standard IHC practice). One negative run does not establish biological absence or a COX6C-specific fixation effect. |
| Cell and tissue context | HPA reports High staining in adrenal, appendix, breast, cervix, and colon glandular cells; bronchial respiratory epithelial cells; and selected cerebellar and cortical cells (HPA tissue IHC). It reports Low staining in adipocytes and chondrocytes, with no negative population listed (HPA tissue IHC). Choose comparison fields by named cell population. |
| Topology and epitope information | COX6C spans the inner mitochondrial membrane at residues 14–54, with residues 1–13 on the matrix side and 55–75 on the intermembrane side (UniProt P09669 topology). The supplied record does not locate either antibody’s epitope; topology therefore cannot predict an antibody-specific retrieval requirement or fixation sensitivity. |
| Validation and molecular annotations | HPA assigns Enhanced reliability to tissue IHC and Enhanced IHC validation to HPA014295 and CAB016244 (HPA tissue IHC; HPA antibodies). UniProt lists no annotated isoforms, glycosylation sites, modified residues, signal sequence, or propeptide (UniProt P09669). These annotations do not establish why an individual slide stains weakly or strongly. |
| IF/ICC Q: What localisation should be expected? | A: HPA reports mitochondrial localisation, rated enhanced, with ICC-IF images in A-431, U-251MG, and U2OS cells (HPA subcellular). This supports a mitochondrial localisation check for IF/ICC; it does not supply an IF/ICC protocol or change the IHC slide criteria. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected-positive glandular cells have no stain. | The run may have failed; HPA reports High staining in adrenal and colon glandular cells (HPA tissue IHC). | Confirm tissue identity and examine retrieval, primary-antibody, and detection controls using the IHC workflow (standard IHC practice). Do not infer target-specific fixation sensitivity from this result. |
| Signal is mainly nuclear or at the cell surface. | The location disagrees with mitochondrial COX6C and HPA’s granular cytoplasmic pattern (UniProt P09669; HPA tissue IHC). | Check a reported High cell population and review a primary-omission control for nonspecific detection (HPA tissue IHC; standard IHC practice). |
| Diffuse brown background obscures granules. | Nonspecific binding, endogenous detection activity, or overdevelopment are possible (standard IHC practice). | Inspect a primary-omission control; review blocking, washing, and chromogen development within the IHC workflow (standard IHC practice). |
| Adipocytes or chondrocytes stain strongly. | HPA reports Low staining in these cells, so the result merits scrutiny; Low is not an absence claim (HPA tissue IHC). | Confirm cell identity, compare a reported High population, and inspect controls for cross-reactivity or endogenous activity (HPA tissue IHC; standard IHC practice). |
| Staining appears widespread but varies between cell populations. | COX6C has low RNA tissue specificity, while HPA’s protein staining levels vary by named cell type (HPA tissue IHC). | Score identifiable cells separately and compare each with HPA’s cell-specific pattern; retain granular cytoplasmic localisation as a check (HPA tissue IHC; standard IHC interpretation). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: COX6C is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot COX6C staining in chromogenic paraffin section IHC using its mitochondrial location, tissue staining profile, and the available antibody evidence.
The catalog provides one COX6C antibody with IHC data from a paraffin-embedded human breast carcinoma section (catalog image caption); its listed reactivity includes human, mouse and rat (catalog reactivity).
A11443-1 has an IHC image from paraffin-embedded human breast carcinoma tissue at 1:100 (catalog image caption). Its listed application is IHC, and its listed reactivity is human, mouse and rat (catalog applications and reactivity).
Which to pick: Choose A11443-1 for paraffin-section IHC: its own image shows staining in paraffin-embedded human breast carcinoma tissue at 1:100 (catalog image caption), and it is a rabbit polyclonal antibody (catalog host and dilution record). There is no IF/ICC option in this catalog: A11443-1 lists IHC only (catalog applications). For mouse or rat tissue, A11443-1 lists reactivity with both species, although its supplied IHC image is from human tissue (catalog reactivity; catalog image caption); the fixative is unreported (catalog image caption).