This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section IHC for CSGALNACT2 using granular cytoplasmic tissue staining as the observed pattern and Golgi localization as molecular context (HPA tissue IHC; UniProt). Use adrenal gland glandular cells as a high-staining control (HPA tissue IHC), and optimize the catalog antibody within 1:100–1:300 (datasheet).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm observed; Golgi membrane expected (HPA tissue IHC; UniProt) | |
| Staining pattern | Granular cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A10939) | |
| Caveat | Staining shows low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Specific expression regulation is unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope map unknown; cytosolic versus lumenal side matters (UniProt) |
Use the catalog antibody’s IHC-P protocol (datasheet) alongside the published ovarian cancer tissue protocol (PMC11219422).
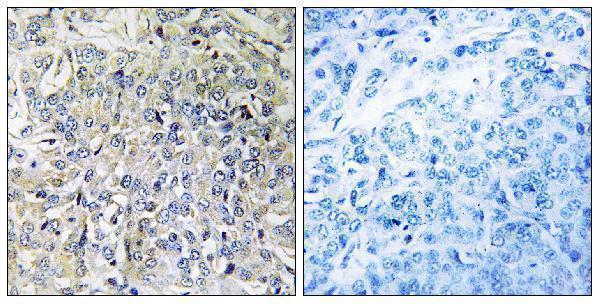
| Sample | Paraffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A10939) |
| Fixation | Image fixative and duration unreported (datasheet A10939); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CSGALNACT2, 1:100-1:300 (datasheet A10939) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CSGALNACT2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression in most tissues. No signal in the no-primary control. |
CSGALNACT2 is a Golgi stack membrane protein with a short cytoplasmic segment and a large lumenal region (UniProt Q8N6G5 topology). In paraffin sections, expect granular cytoplasmic staining in tissue cells, including strong staining in several epithelial, glandular, glial, and endothelial populations (HPA tissue IHC). Interpret intensity cautiously: HPA rates the tissue staining Approved but reports low consistency with RNA expression (HPA tissue IHC).
| Granular cytoplasmic staining in the relevant cells, with little nuclear or diffuse background. | This matches the broad tissue pattern reported by HPA (HPA tissue IHC). A Golgi-associated pattern is biologically plausible for this membrane enzyme (UniProt Q8N6G5 localisation and topology). In a paraffin section, granules may not resolve into a distinct Golgi stack (general IHC practice). |
| Predominantly nuclear staining, or a crisp cell-surface outline without convincing cytoplasmic granules. | Neither pattern fits the reported Golgi membrane localisation or granular tissue staining (UniProt Q8N6G5 localisation; HPA tissue IHC). Treat it as suspect and assess controls before assigning it to CSGALNACT2; appearance alone cannot identify the source of an artefact (general IHC practice). |
| Strong staining appears chiefly in an unexpected cell population while the expected population is weak. | Consider cross-reactivity or endogenous chromogenic activity, depending on the detection system (general IHC practice). HPA documents high staining in selected cell types, but its list is not an exhaustive map: UniProt describes tissue expression as ubiquitous (HPA tissue IHC; UniProt Q8N6G5 tissue specificity). |
| Broad, featureless colour covers cells and surrounding tissue. | Diffuse background makes the granular cytoplasmic pattern difficult to judge (HPA tissue IHC). Non-specific antibody binding, inadequate washing, or endogenous detection activity are possible workflow causes; their presence must be checked with appropriate controls (general IHC practice). |
| No convincing stain appears in a section containing a cell population reported as strongly positive. | A failed stain is possible, but the HPA level is an observation, not a guarantee for every specimen (HPA tissue IHC). Check the run and tissue integrity first; HPA's reported low staining–RNA consistency limits conclusions drawn from one negative section (HPA tissue IHC; general IHC practice). |
| Compartment and epitope access | The protein has one membrane span at residues 12–32; residues 33–542 are lumenal (UniProt Q8N6G5 topology). The antibody epitope is unspecified here, so topology alone cannot determine an antigen retrieval condition or explain a failed paraffin stain. |
| Tissue choice | HPA reports high staining in bronchial respiratory epithelium and glandular cells in adrenal gland, appendix, and endometrium; it also reports high staining in selected glial and endothelial populations (HPA tissue IHC). Use the stated cell population, not the tissue name alone, when reading a section. |
| Evidence strength | HPA rates the listed antibody's IHC staining Approved and reports low consistency between staining and RNA expression (HPA antibody validation; HPA tissue IHC). A matching pattern supports interpretation but does not establish specificity in an individual run. |
| IF/ICC Q: Should the same compartment be expected? | HPA's approved ICC-IF location is endoplasmic reticulum, whereas UniProt assigns CSGALNACT2 to the Golgi stack membrane (HPA subcellular; UniProt Q8N6G5 localisation). Record the discrepancy when comparing images; the supplied evidence does not resolve it or justify an IF protocol here. |
| Situation | Likely cause | Next action |
|---|---|---|
| The expected granular cytoplasmic signal is absent throughout the run. | A run-level staining or detection failure is possible (general IHC practice). | Review the run control, reagent sequence, antigen retrieval record, and chromogen development before interpreting tissue as negative (general IHC practice). No target-specific fixation sensitivity is reported in the supplied UniProt or HPA evidence. |
| An HPA-listed high cell population is weak in one section. | The reported intensity may vary between specimens, or section quality may limit interpretation (HPA tissue IHC; general IHC practice). | Confirm that the named cell population is present and preserved; compare an independently stained section and run control (general IHC practice). Avoid treating HPA's high label as a required intensity for every specimen (HPA tissue IHC). |
| Nuclei dominate the staining. | This conflicts with Golgi membrane localisation and HPA's granular cytoplasmic tissue profile (UniProt Q8N6G5 localisation; HPA tissue IHC). | Inspect a negative reagent control and repeat the stain if needed; score nuclear-only colour as unconfirmed CSGALNACT2 (general IHC practice). |
| Unexpected cells stain strongly in a chromogenic section. | Cross-reactivity or endogenous activity in the chosen detection system is possible (general IHC practice). | Compare reagent controls and the distribution of cytoplasmic granules; check an HPA-described population in the same or a companion section (HPA tissue IHC; general IHC practice). Do not exclude a cell solely because HPA did not list it (UniProt Q8N6G5 tissue specificity). |
| Diffuse colour obscures cell boundaries. | Non-specific binding, residual detection reagents, or endogenous chromogenic activity may contribute (general IHC practice). | Check negative controls and washing and blocking steps; assess whether discrete cytoplasmic granules remain visible before scoring (general IHC practice; HPA tissue IHC). |
| An IF image suggests ER while the IHC section appears Golgi-associated. | The supplied location annotations differ by source and application (HPA subcellular; UniProt Q8N6G5 localisation). | Report the observed compartment and method separately. Do not use the IF annotation alone to relabel a granular paraffin-section result or to establish antibody specificity (HPA subcellular; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in molecular layer | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: CSGALNACT2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot CSGALNACT2 staining by checking retrieval, compartment, cell identity and controls before comparing IHC scores across sections.
A10939 has a human breast carcinoma paraffin-section IHC image with peptide blocking (catalog image caption). IF and Human/Mouse reactivity are listed, but no IF image is supplied (catalog applications/reactivity/IF image alts).
A10939 is the only rendering SKU; its IHC figure shows paraffin-embedded human breast carcinoma tissue alongside a peptide-blocked image (catalog image caption). A10939 lists IHC and IF applications and Human/Mouse reactivity (catalog applications/reactivity), with no IF image supplied (catalog IF image alts).
Which to pick: Choose A10939 for paraffin-section tissue IHC based on its human breast carcinoma figure (catalog image caption); the fixative is unreported (catalog image caption). For IF/ICC, A10939 lists IF but has no IF image or ICC application listed, so validate it for the intended preparation (catalog applications/IF image alts). For Human/Mouse work, A10939 is a rabbit antibody listing both species (catalog host/reactivity), though its IHC figure shows human tissue only (catalog image caption).