CSRP1 / Cysteine and glycine-rich protein 1 · IHC design guide

Design Immunohistochemistry for CSRP1

Plan chromogenic CSRP1 IHC in paraffin sections using the observed cytoplasmic and membranous tissue pattern; UniProt also annotates a nuclear location (HPA tissue IHC; UniProt). Colon glandular cells are a candidate positive control, but interpret staining cautiously because HPA flags possible recognition of proteins from more than one gene (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CSRP1 (IHC for CSRP1): expected localisation Cytoplasmic and membranous in most tissues (HPA tissue IHC), antibody A06894-1, validated IHC image, and IHC protocol steps
Printable CSRP1 IHC protocol sheet — expected localisation Cytoplasmic and membranous in most tissues (HPA tissue IHC), antibody A06894-1, controls and protocol steps. Open the full CSRP1 IHC guide →

CSRP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous in most tissues (HPA tissue IHC)
Staining pattern Glandular cells stain strongly; tissue staining is cytoplasmic and membranous (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06894-1)
Caveat Antibody may recognize proteins from more than one gene (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No annotated isoforms; one 1–193 chain, with no signal peptide (UniProt)
Section 1

Recommended CSRP1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by three published CSRP1 IHC protocols for prostate, cholangiocarcinoma and liver specimens (PMC11849366; PMC9932535; PMC2847390).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human esophageal carcinoma tissue; fixative not specified (datasheet A06894-1)
FixationImage fixative and duration unreported (datasheet A06894-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CSRP1, 1:50-1:200 (datasheet A06894-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCSRP1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 retrieval for the catalog antibody (page protocol); citrate pH 6.0 is a published alternative for prostate biopsies (PMC11849366).
Section 2

What Is the Expected CSRP1 Staining Pattern?

CSRP1 is annotated in the nucleus (UniProt P21291), while HPA tissue IHC reports mainly cytoplasmic and membranous staining across most tissues, including high staining in colon glandular cells and kidney tubular cells (HPA tissue IHC). CSRP1 has no transmembrane segment (UniProt P21291 topology); membranous staining does not establish membrane insertion. Interpret the tissue pattern cautiously: HPA rates its IHC reliability Uncertain because the antibody may detect proteins from more than one gene (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic or membranous staining in colon glandular cells or kidney tubular cells.This matches reported high staining in those cell populations (HPA tissue IHC). Record the stained cells and compartment separately; the matching pattern alone does not resolve HPA's antibody-specificity concern (HPA tissue IHC).
Predominantly nuclear staining, or staining confined to extracellular material, replaces the reported tissue pattern.Nuclear localisation is annotated (UniProt P21291), so nuclear signal alone cannot be dismissed. Extracellular-only signal is outside the reported cytoplasmic and membranous pattern (HPA tissue IHC); check morphology and controls before interpreting it as CSRP1.
Strong signal appears in adipocytes or cardiomyocytes, or in a different cell population than the expected positive cells.HPA reports CSRP1 as not detected in adipocytes and cardiomyocytes (HPA tissue IHC). Such staining warrants checks for cross-reactivity or endogenous chromogenic activity (general IHC practice), especially given the antibody warning (HPA tissue IHC).
Color covers the section diffusely, with little separation between cells and surrounding tissue.The distribution cannot be scored reliably against HPA's cell-specific observations (HPA tissue IHC). Check the no-primary control and detection background, then reassess whether any signal follows recognizable cell boundaries (general IHC practice).
Colon glandular cells or kidney tubular cells show no detectable staining.Both are reported high by HPA tissue IHC. First check section integrity, detection controls, and the antibody's IHC-P conditions (general IHC practice); a single blank slide cannot establish that CSRP1 is absent.
💡Expected CSRP1 appearanceA convincing positive shows high cytoplasmic or membranous staining in colon glandular cells or kidney tubular cells (HPA tissue IHC), while strong staining of adipocytes or cardiomyocytes conflicts with HPA's not detected calls (HPA tissue IHC).
How each factor affects the staining
Tissue and cell selectionUse a reported high population, such as colon glandular cells, alongside a reported not detected population, such as adipocytes (HPA tissue IHC). Score the named cells, since a tissue label alone does not describe every cell in the section.
Compartment evidenceHPA reports cytoplasmic and membranous tissue staining (HPA tissue IHC), whereas UniProt annotates the nucleus (UniProt P21291). Record each compartment observed rather than treating either source as proof that the other pattern is artifactual.
Antibody specificityHPA calls tissue IHC reliability Uncertain and warns that the antibody targets protein from more than one gene (HPA tissue IHC). Agreement with a reference image supports pattern matching, but does not establish CSRP1-specific detection.
Protein topologyCSRP1 has no transmembrane segment and no signal peptide (UniProt P21291 topology and processing). Membranous chromogen should therefore be described as a staining pattern, without inferring a membrane-spanning or secreted CSRP1 form.
IF comparisonHPA provides no main ICC-IF location or ICC-IF image-bearing cell line in this payload (HPA subcellular). The IHC compartment pattern should not be presented as an independently confirmed IF pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in the selected positive tissueA blank result conflicts with the high call for colon glandular cells or kidney tubular cells (HPA tissue IHC); the failed step is undetermined.Check the assay's detection control and section quality; review the catalog antibody's IHC-P conditions and repeat with a reported positive cell population (general IHC practice; HPA tissue IHC).
Only nuclear signal is visibleNuclear localisation is annotated (UniProt P21291), but nuclear-only staining differs from HPA's reported tissue pattern (HPA tissue IHC).Document the compartment and compare a reported positive tissue with appropriate controls before assigning specificity (HPA tissue IHC; general IHC practice).
Strong color in a reported negative cell populationAdipocytes and cardiomyocytes are not detected in HPA tissue IHC; cross-reactivity or endogenous detection activity is possible (general IHC practice).Inspect a no-primary control and, for peroxidase detection, assess endogenous peroxidase blocking; interpret persistent antibody-dependent signal cautiously (general IHC practice).
Diffuse chromogen obscures cell boundariesBackground can prevent comparison with HPA's cell-specific pattern (HPA tissue IHC; general IHC practice).Compare with the no-primary control and review blocking, antibody concentration, and wash conditions using the assay's validated IHC-P instructions (general IHC practice).
Membranous signal is scored as membrane-spanning CSRP1HPA describes membranous staining (HPA tissue IHC), but CSRP1 has no transmembrane segment (UniProt P21291 topology).Report the observed compartment as membranous staining; avoid assigning membrane insertion from chromogenic appearance alone (HPA tissue IHC; UniProt P21291 topology).
IHC and IF results appear to disagreeThe supplied HPA ICC-IF record has no main location or image-bearing cell line for comparison (HPA subcellular).Keep the IHC interpretation tied to tissue IHC evidence, and evaluate IF with its own controls and guide (HPA tissue IHC; HPA subcellular; general IF practice).

Sample controls for CSRP1 IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use heart muscle as a negative tissue, where cardiomyocytes are reported as not detected (HPA: Not detected in heart muscle cardiomyocytes); on the colon slide, cells without specific staining should show counterstain alone, but their CSRP1 status should not be assumed from the glandular-cell result.
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CSRP1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit polyclonal isotype control (selected IHC caption: CSRP1 pAb with goat anti-rabbit secondary); use a matched CSRP1 knockout sample, if available, as a biological negative. Block endogenous peroxidase and check for endogenous biotin background in colon when using the caption’s avidin-peroxidase detection (selected IHC caption: avidin-peroxidase).
⚠️Feasibility: Paraffin-section IHC staining is shown at 1:50 with nuclear staining (selected IHC caption), but the exact caption does not report a fixative. A target-specific fixation window, fixation effect and antigen-retrieval dependency are unreported in the supplied evidence; the paraffin caption alone does not establish fixation. There is no supplied frozen-section comparison or HPA ICC-IF image from which to judge whether frozen sections or IF are easier (HPA subcellular: no ICC-IF image cell lines); assess glandular background in colon during assay setup (HPA: High in colon glandular cells). The selected A06894-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A06894-1).

HPA tissue IHC evidence for CSRP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Caution, targets protein from more than one gene. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CSRP1 IHC Tips

Troubleshoot CSRP1 staining in paraffin sections by checking retrieval, controls, compartment, and cell type before comparing chromogenic signals (standard IHC practice).

How should I retrieve CSRP1 antigen when nuclear staining is weak?
Start with Tris-EDTA pH 9.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval rule: nuclear antigen). Allow sections to cool in retrieval buffer, then compare a short primary-antibody dilution series on adjacent sections while holding detection conditions constant (standard IHC practice). The selected A06894-1 image shows nuclear staining in paraffin-embedded human esophageal carcinoma at 1:50, but does not report its retrieval method (A06894-1 caption). If staining remains weak, test citrate pH 6.0 on a matched section as a fallback and record which condition preserves morphology and gives the best specific contrast (standard IHC practice).
Could fixation explain weak or uneven CSRP1 staining?
Target-specific sensitivity of CSRP1 to fixation is unknown from the supplied evidence; the A06894-1 paraffin-section caption does not state a fixative (A06894-1 caption). For a new specimen, record fixation time and processing history, and compare sections processed together before changing antibody concentration (standard IHC practice). Inspect poorly preserved areas separately from intact tissue, because loss of morphology makes cellular staining difficult to interpret (standard IHC practice). Keep the page retrieval condition at Tris-EDTA pH 9.0, 95–98 °C for 20 min during the first comparison, so a retrieval change does not confound the fixation assessment (page retrieval rule: nuclear antigen).
How should I assess nuclear staining when tissue staining also appears cytoplasmic?
Score nuclear and cytoplasmic staining separately: UniProt annotates CSRP1 in the nucleus, whereas HPA describes cytoplasmic and membranous tissue expression (UniProt P21291 subcellular; HPA tissue IHC profile). The selected A06894-1 paraffin-section image reports nuclear staining in human esophageal carcinoma at 1:50 (A06894-1 caption). Examine cell boundaries and nuclei at higher magnification, using the counterstain to distinguish diffuse cytoplasmic signal from overlapping cells (standard IHC practice). Treat compartment differences as a reason to validate specificity with a second antibody or orthogonal assay, especially because HPA rates its tissue staining uncertain (HPA tissue IHC reliability).
Could epitope location or modification change the CSRP1 staining pattern?
The supplied UniProt record lists one 193-aa chain and 0 isoforms, so the record does not support an isoform-based explanation for discordant staining (UniProt P21291 processing and isoforms). CSRP1 contains LIM zinc-binding regions at residues 10–61 and 119–170, with reported phosphorylation at 81 and acetylation at 84, 112, 131, and 137 (UniProt P21291 domains and modified residues). Without the antibody’s epitope sequence, modification-dependent recognition remains a hypothesis rather than an established effect (supplied antibody evidence). Compare staining from an independently validated epitope and the same retrieval condition on adjacent sections before assigning biological meaning to a discrepant compartment (standard IHC practice).
How can I use IF to investigate a disputed IHC localisation?
Use IF as a separate validation experiment and multiplex CSRP1 with a marker identifying the cell population being scored, plus a nuclear counterstain (standard IF practice). Select fluorophores after checking the tissue’s autofluorescence in unstained controls; choose channels with clear spectral separation and verify each channel with single-stain controls (standard IF practice). CSRP1 has no transmembrane segment and is annotated in the nucleus, so use a nuclear-compatible permeabilisation step when testing intracellular access, then check that cell morphology remains intact (UniProt P21291 topology and subcellular; standard IF practice). HPA supplies no CSRP1 ICC/IF images here, so do not treat its tissue IHC profile as IF validation (HPA subcellular record; HPA tissue IHC profile).
What controls distinguish CSRP1 signal from chromogenic background?
Run a no-primary control beside each staining batch; the A06894-1 image used PBS in place of primary antibody and a biotin-secondary, avidin-peroxidase detection sequence (A06894-1 caption). Block endogenous peroxidase before chromogen development and assess endogenous biotin if using that detection chemistry (standard chromogenic IHC practice). Titrate the primary around the caption’s 1:50 condition on matched sections, judging specific cellular contrast against the no-primary slide rather than total color intensity (A06894-1 caption; standard IHC practice). If edges or damaged regions stain disproportionately, inspect section adhesion, washing, and reagent coverage before changing the interpretation of CSRP1 distribution (standard IHC practice).
How should I quantify CSRP1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored compartment and cell population before analysis, because UniProt annotates nuclear CSRP1 while HPA reports cytoplasmic and membranous tissue expression (UniProt P21291 subcellular; HPA tissue IHC profile). For each compartment, record the percentage of positive cells and an intensity-based H-score from 0–300, using consistent intensity thresholds across batches (standard IHC scoring practice). Normalize positive-cell counts to all evaluable cells of the same type, or report positive-cell density per mm² of viable tissue when cellular composition differs (standard quantitative IHC practice). Exclude folds and necrotic areas by a prespecified rule, and report biological replicates separately from fields sampled within each specimen (standard quantitative IHC practice).
When is an apparent CSRP1-positive region likely to be artefactual?
First confirm that color sits within intact cells of the population being evaluated and has a reproducible compartment pattern across sections (standard IHC practice). Nuclear signal is consistent with UniProt and the selected A06894-1 carcinoma image, while HPA reports cytoplasmic and membranous tissue staining with uncertain reliability (UniProt P21291 subcellular; A06894-1 caption; HPA tissue IHC profile and reliability). Check whether apparent positives cluster at section edges or necrotic areas, or persist on the no-primary control; these patterns warrant investigation of handling or endogenous detection signal (standard IHC practice). Use an independent specificity control before calling an unexpected cell type or compartment positive, particularly when comparing with HPA’s uncertain tissue profile (HPA tissue IHC reliability; standard IHC practice).
Boster reagents

Best CSRP1 / Cysteine and glycine-rich protein 1 IHC Antibodies

The IHC-validated anti-CSRP1 antibody has a paraffin-section image from human esophageal carcinoma (catalog IHC caption). Human, mouse and rat are listed as reactive species (catalog: reactivity).

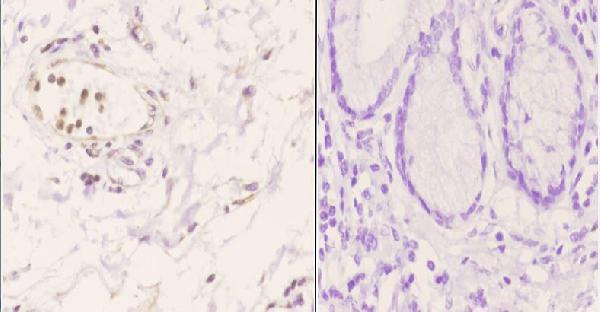
Real IHC data Immunohistochemistry (IHC) analyzes of CSRP1 pAb in paraffin-embedded human esophageal carcinoma tissue at 1:50.showing nucleus staining. Negative control (the right)Using PBS instead of primary antibody, secondary antibody is Goat Anti-Rabbit IgG-biotin followed by avidin-peroxidase.
Anti-CSRP1 Antibody
Cat # A06894-1

A06894-1 is the only card; its IHC image shows nuclear staining in paraffin-embedded human esophageal carcinoma at 1:50, with a PBS primary-omission control (catalog IHC caption). IHC and ICC are listed applications, and human, mouse and rat are listed as reactive species (catalog: applications and reactivity); no IF image is supplied (catalog: IF images).

Which to pick: Choose A06894-1 for paraffin-section tissue IHC because its own image documents that preparation; the fixative is unreported (catalog IHC caption). For IF/ICC, A06894-1 lists ICC and a 1:50–1:200 dilution range, but has no IF image in this payload (catalog: applications, IF dilution and IF images). It is a rabbit polyclonal with listed human, mouse and rat reactivity; the supplied tissue image documents human tissue only (catalog: host, clonality and reactivity; catalog IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P21291 (CSRP1_HUMAN, Cysteine and glycine-rich protein 1).
  2. Human Protein Atlas. CSRP1 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. CSRP1 subcellular location (ICC-IF): Highest expression in HeLa: 609.2 nTPM.
  4. Human Protein Atlas. CSRP1 antibody validation summary (1 antibodies).
  5. Identification of CSRP1 as novel biomarker for hormone-sensitive prostate cancer by the combination of clinical and functional research. Cancer cell international 2025 — PMC11849366.
  6. Identification of immune related gene signature for predicting prognosis of cholangiocarcinoma patients. Frontiers in immunology 2023 — PMC9932535.
  7. CSRP1 expression is associated with a mesenchymal, stroma-rich tumor profile and poor prognosis in colon cancer. Turkish journal of medical sciences 2023 — PMC10760585.
  8. O Labeling for a Quantitative Proteomic Analysis of Glycoproteins in Hepatocellular Carcinoma. Clinical proteomics 2008 — PMC2847390.
  9. PubMed PMID:2115670 — UniProt-cited evidence.
  10. PubMed PMID:1374386 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.