CSTB / Cystatin-B · IHC design guide

Design Immunohistochemistry for CSTB

Plan CSTB chromogenic IHC around cytoplasmic and nuclear staining in squamous epithelia and urothelium (HPA tissue IHC). Use esophageal squamous epithelium as a high-staining reference while accounting for the reported medium consistency between staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
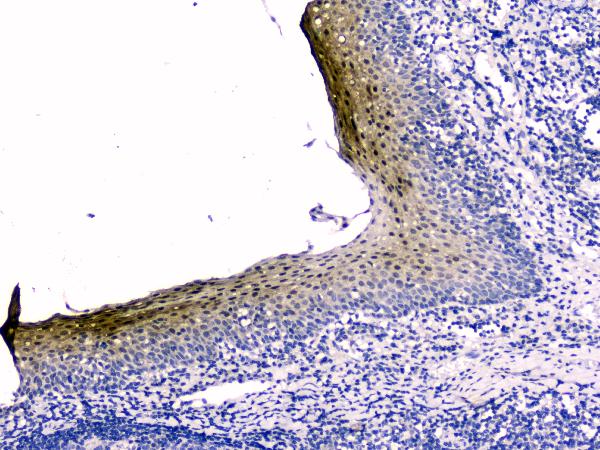
Immunohistochemistry protocol sheet for CSTB (IHC for CSTB): expected localisation Cytoplasmic and nuclear staining in squamous epithelia (HPA tissue IHC), antibody M02794, validated IHC image, and IHC protocol steps
Printable CSTB IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining in squamous epithelia (HPA tissue IHC), antibody M02794, controls and protocol steps. Open the full CSTB IHC guide →

CSTB Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining in squamous epithelia (HPA tissue IHC)
Staining pattern Squamous epithelia and urothelium: cytoplasmic and nuclear (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet M02794)
Positive control ⓘ Esophagus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Esophagus-enriched RNA expression (HPA tissue RNA)
Isoform / epitope No isoforms; the chain spans residues 1–98 (UniProt)
Section 1

Recommended CSTB IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M02794) with three published CSTB IHC protocols (PMC3977810; PMC11854580; PMC10913530).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet M02794)
FixationImage fixative and duration unreported (datasheet M02794); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet M02794)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02794)
Primary antibodyMouse monoclonal (clone 2B6) anti-CSTB, 0.5-1μg/ml recommended; image 2μg/ml (datasheet M02794)
Primary incubationOvernight at 4 °C (datasheet M02794)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet M02794)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCSTB-positive staining in squamous epithelial cells of esophagus (HPA tissue IHC: High). HPA tissue profile: Selective cytoplasmic and nuclear expression in squamous epithelia and urothelium. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval (datasheet M02794); one published protocol also specifies citrate pH 6 (PMC3977810).
Section 2

What Is the Expected CSTB Staining Pattern?

CSTB is intracellular, with cytoplasmic and nuclear localization and no transmembrane segment (UniProt P04080). In paraffin-section IHC, expect selective staining of squamous epithelium and urothelium, strongest in esophageal squamous epithelial cells (HPA: High in esophagus; Medium in oral mucosa, tonsil, vagina, and urinary bladder). HPA rates the tissue pattern Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA: tissue IHC).

What am I looking at on my slide?
Esophageal squamous epithelial cells show strong cytoplasmic and nuclear staining.This matches the highest reported tissue IHC signal and the expected compartments (HPA: High in esophageal squamous epithelial cells; UniProt P04080: cytoplasm and nucleus). Compare cells within the same section before assigning a score.
Signal is confined to cell borders or extracellular material, with little intracellular staining.Treat a predominantly membrane or extracellular pattern as suspect: CSTB has no transmembrane segment and is annotated in the cytoplasm and nucleus (UniProt P04080). Recheck morphology and control sections before interpreting it as CSTB.
Strong staining appears in a cell population reported as undetected.For example, adipocytes in adipose tissue are reported Not detected (HPA: adipose tissue). Consider antibody cross-reactivity or endogenous chromogen-generating activity; those are possible explanations, not diagnoses from staining alone (general IHC practice).
Color spreads across stroma, empty spaces, and unrelated cells.Diffuse background obscures the selective epithelial pattern reported by HPA (HPA: tissue IHC). Inspect a no-primary control and review blocking, antibody concentration, washing, and detection chemistry to locate the nonspecific component (general IHC practice).
Esophageal squamous epithelium has no convincing signal.A known high-expression reference has failed to stain as expected (HPA: High in esophageal squamous epithelial cells). First check tissue integrity and the staining run with a positive control; absence here cannot by itself establish a CSTB-negative sample (general IHC practice).
💡Expected CSTB appearanceCall a section positive when esophageal squamous epithelial cells show strong intracellular cytoplasmic and nuclear signal; isolated membrane staining or widespread stromal color is suspect (HPA: High in esophagus; UniProt P04080: cytoplasm and nucleus; general IHC practice).
How each factor affects the staining
Tissue and cell selection (HPA: tissue IHC)Esophagus provides a High squamous epithelial reference; oral mucosa, tonsil, vagina, and bladder have Medium signal in the specified epithelial cells (HPA: tissue IHC). Score the identified cell population, not the whole section.
Compartment and molecular form (UniProt P04080)CSTB is a 98-residue intracellular protein with cytoplasmic and nuclear annotation, no transmembrane segment, and no annotated signal peptide or propeptide (UniProt P04080). These features support an intracellular interpretation.
Strength of tissue evidence (HPA: tissue IHC)The tissue profile is rated Enhanced, but antibody staining and RNA expression have only medium consistency (HPA: reliability description). Use observed cell-level staining and controls when interpreting a discordant specimen.
Antibody validation (HPA: antibody records)HPA017380, HPA058557, and CAB047320 each have Enhanced IHC status (HPA: antibody records). That supports the reported tissue pattern; it does not prove every signal from a different catalog antibody is specific.
IF/ICC Q: What localization should be expected? (HPA: subcellular ICC-IF)A: HPA reports supported nucleolar and cytosolic localization in ICC-IF, including images from A-431, U-251MG, and KOLF2.1J (HPA: subcellular ICC-IF). This is context for the separate IF/ICC guide, not an IHC retrieval or staining condition.
Chromogenic detection (general IHC practice)Endogenous enzyme activity or nonspecific reagent binding can produce color independent of primary-antibody binding (general IHC practice). Interpret unexpected staining against a no-primary control and the HPA cell-type pattern (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in esophageal squamous epithelium (HPA: High in esophagus)The section or staining run may have failed; the cause is unresolved from this image alone (general IHC practice).Check a known-positive section, tissue preservation, and staining reagents; then review the antibody's documented IHC-P conditions (general IHC practice).
Only membrane-edge staining is visible (UniProt P04080: intracellular localization)This distribution conflicts with cytoplasmic and nuclear annotation and the absence of a transmembrane segment (UniProt P04080).Inspect the cell boundaries and a no-primary control; reassess whether the color is specific intracellular signal (general IHC practice).
Adipocytes stain strongly (HPA: Not detected in adipose adipocytes)Cross-reactivity or endogenous detection activity is possible, but staining alone cannot distinguish them (general IHC practice).Compare a no-primary control and an esophageal positive control; investigate antibody specificity if the unexpected signal persists (general IHC practice).
Background covers stroma and empty spaces (general IHC practice)Nonspecific reagent binding, inadequate washing, or chromogenic detection background may obscure cellular staining (general IHC practice).Review the no-primary control, blocking, washing, detection reagents, and antibody concentration before scoring (general IHC practice).
Bladder or oral mucosa looks weaker than esophagus (HPA: tissue IHC)HPA reports Medium urothelial or oral squamous signal versus High esophageal squamous signal (HPA: tissue IHC).Score the appropriate epithelial cells and compare matched controls; do not call a weaker tissue negative solely by comparison with esophagus (HPA: tissue IHC; general IHC practice).
Nuclear color appears without a clear cytoplasmic component (UniProt P04080: both compartments)CSTB can localize to the nucleus, but a single-compartment image does not establish why cytoplasmic signal is absent (UniProt P04080).Confirm the stained cells and morphology, compare the positive control, and exclude nuclear counterstain or detection artifact (general IHC practice).

Sample controls for CSTB IHC & IF

🧪Run esophagus first and confirm staining in its squamous epithelial cells (HPA: High); use adipose tissue as the negative comparator, scoring its adipocytes (HPA: Not detected). On the esophagus slide, use adjacent stromal cells as internal background comparators only if they show no signal above the no-primary control; HPA assigns a level only to squamous epithelial cells in that row (HPA: esophagus row).
Positive control tissue: Esophagus (Squamous epithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CSTB in A-431, U-251MG, KOLF2.1J, with annotated localisation: Nucleoli (supported), Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration- and subclass-matched mouse IgG isotype controls (selected IHC caption: mouse primary antibody), plus independently validated CSTB knockout material or peptide competition if the immunizing peptide is available. Block endogenous peroxidase and check for endogenous biotin because the selected IHC detection uses a streptavidin–biotin complex and DAB (selected IHC caption: SABC/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected IHC caption: fixative not stated). The reported tonsil IHC result used heat-mediated citrate retrieval at pH 6 for 20 minutes, but retrieval dependence across tissues has not been established (selected IHC caption: tonsil retrieval conditions). Frozen sections cannot be judged easier from these data; HPA ICC-IF images support examining cytosol and nucleoli in cultured cells, while tissue IF feasibility and esophagus-specific artefacts remain unreported (HPA subcellular: supported cytosol and nucleoli; HPA: ICC-IF image cell lines).

HPA tissue IHC evidence for CSTB

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Medium Protein (IHC) HPA →
Tonsil Squamous epithelial cells Medium Protein (IHC) HPA →
Urinary bladder Urothelial cells Medium Protein (IHC) HPA →
Vagina Squamous epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CSTB IHC Tips

Troubleshoot CSTB staining in paraffin sections by checking retrieval, controls, cellular compartment and cell type before comparing staining intensity.

Which retrieval condition should I try first for weak CSTB staining in paraffin sections?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes (datasheet M02794). The tonsil example used this condition before 10% goat-serum blocking and 2 μg/mL primary antibody overnight at 4°C (datasheet M02794). If staining remains weak, compare matched sections using modest changes in heating time while keeping antibody incubation and DAB development constant (standard IHC practice). Check whether stronger staining retains cellular detail, because diffuse brown precipitate or damaged morphology does not establish improved CSTB detection (standard IHC practice). Evaluate both cytoplasmic and nuclear staining in squamous epithelium when judging the result (HPA tissue IHC; UniProt P04080 localisation).
Could fixation explain weak or uneven CSTB staining?
The selected paraffin-section caption does not state a fixative, so target-specific CSTB fixation sensitivity is unknown (datasheet M02794). Record the fixative, time to fixation, fixation duration, processing schedule and section age for each specimen before comparing staining intensity (standard IHC practice). Compare sections processed together and stain a documented positive control in the same run to distinguish specimen handling from a run-wide failure (HPA tissue IHC; standard IHC practice). If signal varies across a section, inspect tissue preservation and edges before changing antibody concentration or retrieval (standard IHC practice). Do not assign a CSTB-specific fixation mechanism without direct fixation evidence (datasheet M02794).
What cellular pattern should I expect for CSTB in tissue IHC?
Expect cytoplasmic and nuclear staining in appropriate cells, since CSTB is annotated in both compartments and tissue IHC shows selective expression in squamous epithelia and urothelium (UniProt P04080 localisation; HPA tissue IHC). In esophagus, squamous epithelial cells are reported as high; tonsil squamous epithelial cells and bladder urothelial cells are reported as medium (HPA tissue IHC). Compare those cell types with adjacent tissue and a no-primary control under the same DAB exposure (standard IHC practice). The protein has no transmembrane segment or signal peptide, so an isolated sharp membrane rim needs scrutiny (UniProt P04080 topology and processing). Record nuclear and cytoplasmic staining separately when their balance changes (standard IHC practice).
How should I troubleshoot a CSTB pattern that changes with retrieval?
CSTB has no annotated isoforms or domains, and its annotated chain spans residues 1–98 (UniProt P04080 isoforms, domains and processing). The record lists N-terminal acetylmethionine but provides no epitope map for the catalog antibody, so a retrieval-dependent pattern cannot be assigned to that modification (UniProt P04080 modified residues; datasheet M02794). Compare adjacent sections with the same antibody lot, dilution, incubation and DAB development while changing only the retrieval condition (standard IHC practice). Check whether the resulting signal stays within expected cytoplasmic or nuclear compartments and appropriate epithelial cells (UniProt P04080 localisation; HPA tissue IHC). Document the condition that preserves morphology and reproducible cellular contrast (standard IHC practice).
How can I assess a CSTB IF result alongside paraffin-section IHC?
Treat IF as a separate assay: the selected caption documents paraffin-section chromogenic IHC, while HPA reports supported cytosolic and nucleolar ICC/IF localisation (datasheet M02794; HPA subcellular). Multiplex CSTB with a marker identifying the expected squamous epithelial or urothelial cells, and include single-color controls to check channel bleed-through (HPA tissue IHC; standard IF practice). Choose fluorophores and imaging channels after measuring tissue autofluorescence, especially if a weak signal overlaps the autofluorescence spectrum (standard IF practice). Because CSTB is intracellular and has no transmembrane segment, permeabilisation must permit access to cytosolic and nuclear epitopes (UniProt P04080 topology and localisation; standard IF practice). Compare compartment patterns without transferring the IHC antibody concentration to IF (standard IF practice).
What should I check when DAB background obscures CSTB staining?
First compare the stained section with a no-primary control and inspect whether color follows tissue edges, folds or damaged areas (standard IHC practice). The selected tonsil example used 10% goat-serum blocking, a biotinylated secondary, a streptavidin-biotin detection complex and DAB (datasheet M02794). For that detection format, assess endogenous peroxidase and biotin-related background with appropriate controls, then adjust blocking or detection steps as indicated (standard IHC practice). Keep primary incubation and DAB development consistent while troubleshooting so reduced background can be distinguished from lost signal (standard IHC practice). Require cellular cytoplasmic or nuclear contrast in expected epithelium before scoring brown staining as CSTB (UniProt P04080 localisation; HPA tissue IHC).
How should I quantify CSTB staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define epithelial regions before scoring and report the percentage of positive cells plus a compartment-specific H-score if intensity matters (HPA tissue IHC; standard IHC practice). Score cytoplasmic and nuclear staining separately, using the same positivity threshold, illumination and DAB development for every compared section (UniProt P04080 localisation; standard IHC practice). Normalise positive counts to the number of evaluable cells in the same cell population, or report positive-cell density per mm² of annotated tissue area (standard IHC practice). Exclude folds, tissue loss and necrotic regions using prespecified criteria, and retain a positive control in each staining run (standard IHC practice). Report cell type and compartment with the score because tissue expression is selective (HPA tissue IHC).
How can I distinguish genuine CSTB staining from artefact?
A credible result shows cellular cytoplasmic or nuclear staining in the relevant epithelial population, consistent with CSTB localisation and the reported tissue IHC profile (UniProt P04080 localisation; HPA tissue IHC). Esophageal squamous epithelial cells are reported as high, whereas adipocytes in adipose tissue are reported as not detected; use such contrasts cautiously because the HPA reliability description notes medium staining–RNA consistency (HPA tissue IHC). Scrutinise isolated membrane rims, diffuse edge staining, necrotic deposits and color in a no-primary control before calling a positive result (UniProt P04080 topology; standard IHC practice). Endogenous enzyme activity can produce DAB signal, so check the relevant detection controls when staining lacks cellular structure (standard IHC practice). Reproduce the pattern in separately processed sections before interpreting a biological difference (standard IHC practice).
Boster reagents

Best CSTB / Cystatin-B IHC Antibodies

The catalog shows anti-CSTB IHC images from human paraffin sections and an IF image from A431 cells (catalog image captions: M02794, PB9565).

Real IHC data IHC analysis of Stefin B using anti-Stefin B antibody (M02794). Stefin B was detected in paraffin-embedded section of human tonsil tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml mouse anti-Stefin B Antibody (M02794) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1021) with DAB as the chromogen.
Anti-Stefin B CSTB Antibody ® (monoclonal, 2B6)
Cat # M02794
Real IHC data IHC analysis of Stefin B using anti-Stefin B antibody (PB9565). Stefin B was detected in a paraffin-embedded section of human prostatic cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-Stefin B Antibody (PB9565) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-Stefin B/CSTB Antibody ®
Cat # PB9565

M02794 will render with an IHC image from human tonsil paraffin sections; it lists human reactivity and IHC and ICC applications (catalog image caption; catalog applications and reactivity). PB9565 will render with an IHC image from human prostatic cancer paraffin sections; it also lists IF and ICC and has an IF image from A431 cells (catalog image captions; catalog applications).

Which to pick: For tissue IHC, choose mouse monoclonal M02794 for the illustrated human tonsil workflow with citrate pH 6 retrieval, or rabbit PB9565 for the illustrated human prostatic cancer workflow with EDTA pH 8 retrieval; neither IHC caption reports a fixative (catalog hosts; catalog IHC captions). For IF/ICC, PB9565 lists both applications and has an A431 IF image, while M02794 lists ICC without an IF image (catalog applications; catalog image captions). For human and rat IHC, M02794-1 lists both species and is a rabbit monoclonal, but has no IHC image in the payload (catalog reactivity, host, clone and image list).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P04080 (CYTB_HUMAN, Cystatin-B).
  2. Human Protein Atlas. CSTB tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CSTB subcellular location (ICC-IF): Localized to the nucleoli and cytosol..
  4. Human Protein Atlas. CSTB antibody validation summary (3 antibodies).
  5. Cystatin B is a progression marker of human epithelial ovarian tumors mediated by the TGF-β signaling pathway. International journal of oncology 2014 — PMC3977810.
  6. Cystatin B Promotes the Proliferation, Migration, and Invasion of Intrahepatic Cholangiocarcinoma. Current oncology (Toronto, Ont.) 2025 — PMC11854580.
  7. Brain inflammation is accompanied by peripheral inflammation in Cstb (-/-) mice, a model for progressive myoclonus epilepsy. Journal of neuroinflammation 2016 — PMC5127053.
  8. Biomarker cystatin B expression correlates with pathogenesis in cervical cancer. The Journal of international medical research 2024 — PMC10913530.
  9. PubMed PMID:3902020 — UniProt-cited evidence.
  10. PubMed PMID:8596935 — UniProt-cited evidence.
  11. PubMed PMID:10830953 — UniProt-cited evidence.