CYP17A1 / Steroid 17-alpha-hydroxylase/17,20 lyase · IHC design guide

Design Immunohistochemistry for CYP17A1

Plan CYP17A1 paraffin-section IHC using adrenal zona fasciculata and testis Leydig cells as expected positive cell populations (HPA tissue IHC). The catalog antibody A00615-1 has an IHC dilution of 0.5–1 μg/mL (datasheet); assess staining at the cell level against appropriate negative controls.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CYP17A1 (IHC for CYP17A1): expected localisation ER/microsomal membrane is the molecular location; tissue-IHC compartment unverified (UniProt), antibody A00615-1, validated IHC image, and IHC protocol steps
Printable CYP17A1 IHC protocol sheet — expected localisation ER/microsomal membrane is the molecular location; tissue-IHC compartment unverified (UniProt), antibody A00615-1, controls and protocol steps. Open the full CYP17A1 IHC guide →

CYP17A1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation ER/microsomal membrane is the molecular location; tissue-IHC compartment unverified (UniProt)
Staining pattern High staining in adrenal zona fasciculata and testis Leydig cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A00615-1)
Positive control ⓘ Adrenal gland+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show medium consistency (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No isoforms or processing annotated; epitope effects unknown (UniProt)
Section 1

Recommended CYP17A1 IHC & IF Protocols

The catalog antibody uses citrate pH 6 retrieval (datasheet A00615-1). These four published protocols describe CYP17A1 IHC in adrenal tissue (PMC10512174; PMC12185499; PMC5638684; PMC7460193).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human testis tissues; fixative not specified (datasheet A00615-1)
FixationImage fixative and duration unreported (datasheet A00615-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A00615-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00615-1)
Primary antibodyRabbit anti-CYP17A1, 0.5-1μg/ml (datasheet A00615-1)
Primary incubationOvernight at 4 °C (datasheet A00615-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00615-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCYP17A1-positive staining in cells in zona fasciculata of adrenal gland (HPA tissue IHC: High). HPA tissue profile: High expression in Leydig cells and adrenal cotical cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval (datasheet A00615-1); consider the published EDTA pH 9 condition during FFPE optimization (PMC7460193).
Section 2

What Is the Expected CYP17A1 Staining Pattern?

CYP17A1 is associated with the endoplasmic reticulum and microsome membranes, with no annotated transmembrane segment (UniProt P05093 topology). In paraffin-section IHC, expect staining in adrenal zona fasciculata cells and testicular Leydig cells, both reported as high by HPA (HPA: tissue IHC). HPA rates the tissue profile Enhanced, while describing medium consistency between antibody staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Strong cytoplasmic staining in adrenal zona fasciculata cells or testicular Leydig cells (HPA: High in both).This matches the reported positive cell types (HPA: tissue IHC). A cytoplasmic, membrane-associated appearance is consistent with CYP17A1's endoplasmic reticulum and microsome location; the supplied IHC record does not define a finer staining texture (UniProt P05093 subcellular location; HPA: tissue IHC).
Predominantly nuclear staining in otherwise positive cells.An exclusively nuclear pattern conflicts with the annotated endoplasmic reticulum and microsome location (UniProt P05093 subcellular location). Check counterstain separation and detection controls before interpreting it as CYP17A1; nuclear staining alone does not establish target expression (standard IHC practice).
Prominent staining in an HPA-listed negative cell type, such as adipocytes in adipose tissue (HPA: Not detected).This does not match the supplied tissue profile (HPA: tissue IHC). Consider nonspecific antibody binding or endogenous detection activity; compare a no-primary control and the positive tissue on the same staining run (standard IHC practice).
Diffuse chromogen across cells and surrounding tissue, with no clear cellular pattern.That appearance does not resolve the HPA-reported positive cells (HPA: High in zona fasciculata and Leydig cells). Assess background with a no-primary control, then review blocking, washes and detection conditions (standard IHC practice).
No staining in adrenal zona fasciculata cells or testicular Leydig cells (HPA: High in both).The expected positive control has failed for this run; absence of signal cannot establish absence of CYP17A1 in the test sample. Check tissue identity, antibody performance and the IHC detection steps (HPA: tissue IHC; standard IHC practice).
💡Expected CYP17A1 appearanceA convincing positive is high staining in adrenal zona fasciculata cells or testicular Leydig cells, in a cytoplasmic pattern consistent with endoplasmic reticulum or microsome association; isolated nuclear staining or widespread signal in HPA-negative cells warrants investigation (HPA: tissue IHC; UniProt P05093 subcellular location).
How each factor affects the staining
Subcellular locationUniProt assigns CYP17A1 to endoplasmic reticulum and microsome membranes but annotates no transmembrane segment; assess the cellular distribution without requiring a cell-surface rim (UniProt P05093 topology and subcellular location).
Positive-control tissueAdrenal zona fasciculata cells and testicular Leydig cells are reported as High, giving two supported cell-level references for a successful IHC run (HPA: tissue IHC).
Negative-reference cell typesHPA reports adipocytes in adipose tissue and glandular cells in appendix as Not detected; these can help assess whether a run produces unexpected widespread staining (HPA: tissue IHC).
Strength of IHC evidenceThe tissue profile is Enhanced with medium staining–RNA consistency, and antibody HPA048533 has Enhanced IHC validation. Treat the pattern as a reference, while checking control performance in each run (HPA: tissue IHC reliability; HPA: HPA048533 IHC).
IF/ICC interpretationQ: What if IF/ICC shows vesicles? A: HPA lists vesicles as its approved ICC-IF location, while UniProt lists endoplasmic reticulum and microsome membranes. Record the assay and compartment before comparing results; the ICC-IF annotation does not redefine the paraffin IHC pattern (HPA: subcellular ICC-IF; UniProt P05093 subcellular location).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Adrenal zona fasciculata or testicular Leydig cells are blank (HPA: High in both).The staining run may lack sensitivity; the supplied sources do not establish a CYP17A1-specific fixation effect (HPA: tissue IHC).Confirm tissue identity and that the antibody is IHC-validated; review retrieval, antibody concentration and detection with a known-positive section (standard IHC practice).
Only nuclei stain in an otherwise expected positive tissue.The dominant signal does not match the annotated endoplasmic reticulum or microsome location (UniProt P05093 subcellular location).Check a no-primary control, inspect the counterstain separately and reassess antibody concentration and detection background (standard IHC practice).
HPA-listed negative cells stain strongly, such as adipose-tissue adipocytes (HPA: Not detected).Nonspecific binding or endogenous detection activity may explain signal outside the reported cell pattern (standard IHC practice; HPA: tissue IHC).Compare a no-primary control; review blocking, detection chemistry and antibody concentration alongside the positive control (standard IHC practice).
Diffuse staining obscures cell boundaries throughout the section.Background may reflect inadequate blocking, excess reagent or insufficient washing (standard IHC practice).Check the no-primary control, strengthen appropriate blocking or washes, and adjust antibody concentration while preserving the positive-control signal (standard IHC practice).
Adrenal and testis sections show different apparent staining strength.HPA reports High staining in the specified cells of both tissues, but this does not establish equal intensity across separate preparations (HPA: tissue IHC).Score the specified cell populations and compare sections stained in the same run with the same detection and exposure conditions (standard IHC practice).
IF/ICC vesicle staining seems inconsistent with the paraffin IHC result (HPA: Vesicles approved).The supplied annotations describe different assays: vesicles in HPA ICC-IF and endoplasmic reticulum or microsome membranes in UniProt (HPA: subcellular ICC-IF; UniProt P05093).Keep the assay labels distinct and judge paraffin IHC against its tissue controls and cell-level pattern; report the IF/ICC observation separately (HPA: tissue IHC; standard IHC practice).

Sample controls for CYP17A1 IHC & IF

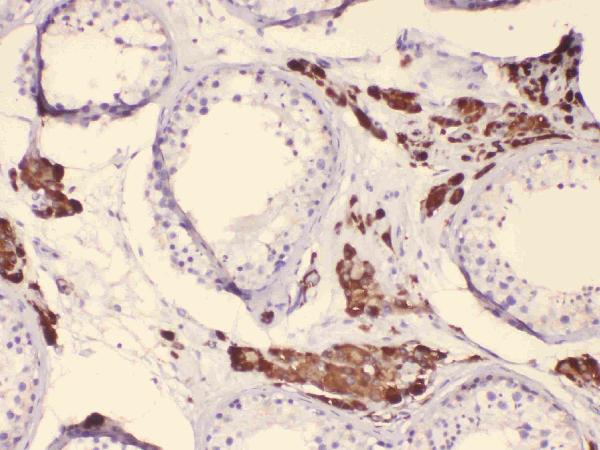
🧪Run testis first: Leydig cells should stain strongly (HPA: High in testis Leydig cells; selected-SKU caption: paraffin-section testis staining). Use adipose tissue as the negative tissue (HPA: Not detected in adipocytes), and compare Leydig cells with adjacent non-Leydig cells on the positive slide as an internal background reference (HPA: High in Leydig cells).
Positive control tissue: Adrenal gland (Cells in zona fasciculata, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CYP17A1 in OE19, SH-SY5Y, U2OS, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a host-matched rabbit IgG isotype control, and a CYP17A1 knockout sample where available as a biological negative (selected-SKU caption: rabbit primary antibody). For chromogenic detection in testis, check endogenous peroxidase and biotin background (selected-SKU caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). The demonstrated testis staining used citrate retrieval at pH 6 for 20 minutes; this supports that starting condition but does not establish retrieval as mandatory (selected-SKU caption: citrate retrieval). No matched frozen-section or IF protocol is supplied, so their relative ease is unknown; biotin-based detection in testis also calls for a background check (selected-SKU caption: SABC detection).

HPA tissue IHC evidence for CYP17A1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Cells in zona fasciculata High Protein (IHC) HPA →
Testis Leydig cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CYP17A1 IHC Tips

Use the documented paraffin section workflow as the IHC starting point, then judge staining against expected cell types and subcellular patterns (datasheet A00615-1; HPA; UniProt P05093).

What retrieval conditions should I try first for CYP17A1 in paraffin sections?
Start with heat mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A00615-1). The documented paraffin section example then uses 10% goat serum and 1 μg/ml primary antibody overnight at 4°C (datasheet A00615-1). Include testis with Leydig cells or adrenal gland with zona fasciculata cells as a positive control when available (HPA: High in these cells). Compare retrieved and unretrieved sections while holding antibody concentration and detection constant to assess whether retrieval improves cell specific signal (standard IHC practice). If staining remains weak, optimize heating duration on matched sections before changing the documented citrate conditions (standard IHC practice).
How should I troubleshoot weak staining when the fixation history is uncertain?
Target specific fixation sensitivity is unknown: the paraffin section caption does not state a fixative (datasheet A00615-1). Record the fixative, fixation duration, tissue thickness, and processing history for each specimen before comparing staining intensity (standard IHC practice). Start with citrate at pH 6 for 20 minutes and 1 μg/ml primary antibody, matching the documented conditions where practical (datasheet A00615-1). Compare specimens with similar processing and include a concurrently stained positive control, since processing differences can alter antigen accessibility in IHC (standard IHC practice). Do not attribute a weak result to CYP17A1 specific fixation damage without a direct comparison using controlled fixation conditions (standard IHC practice).
Which staining pattern fits CYP17A1, and how should I handle punctate signal?
Expect predominantly cytoplasmic staining associated with the endoplasmic reticulum and microsomal membranes, rather than a nuclear pattern (UniProt P05093: subcellular location). Prioritize Leydig cells in testis and zona fasciculata cells in adrenal gland when assessing whether the pattern is biologically plausible (HPA: High expression). HPA also reports vesicular localization in its subcellular imaging data, so puncta alone do not establish an IHC artefact (HPA: Vesicles, approved). Check whether puncta occur in the expected cells and persist across comparable sections and controls (standard IHC practice). Treat isolated nuclear or extracellular deposits with caution until detection controls exclude nonspecific signal (UniProt P05093 localization; standard IHC practice).
How can epitope placement affect interpretation of CYP17A1 staining?
The supplied record describes one 1–508 chain and lists no annotated isoforms, glycosylation sites, or modified residues (UniProt P05093 record). It also lists no transmembrane segment while placing CYP17A1 at endoplasmic reticulum and microsomal membranes (UniProt P05093 topology and location). If an antibody epitope is disclosed, map it against the full sequence before interpreting a negative stain in altered specimens (standard IHC practice). The supplied product caption does not identify its epitope, so antigen accessibility cannot be assigned to a particular sequence region (datasheet A00615-1). Compare staining with an independently validated antibody recognizing a different disclosed epitope when resolving a consequential discrepancy (standard IHC practice).
How should I relate multiplex IF findings to this chromogenic IHC result?
Use chromogenic IHC as the comparison: the documented antibody example detects CYP17A1 in paraffin sectioned human testis with citrate retrieval at pH 6 (datasheet A00615-1). For separate multiplex IF, pair CYP17A1 with a validated marker identifying Leydig cells or adrenal cortical cells, and judge colocalization at the cell level (HPA: High expression in these cells; standard IF practice). Choose fluorophores and imaging channels after checking tissue autofluorescence with an unstained section (standard IF practice). Set permeabilisation according to the antibody epitope’s membrane facing side if known, because CYP17A1 associates with endoplasmic reticulum and microsomal membranes (UniProt P05093; standard IF practice). Keep IF fixation and permeabilisation conclusions separate from the paraffin IHC caption, which does not report a fixative (datasheet A00615-1).
What should I check if CYP17A1 DAB staining appears widespread?
First compare the signal with expected Leydig cell and adrenal zona fasciculata staining; widespread labeling in unrelated cell types needs scrutiny (HPA: High in those cells). Run a no primary control and inspect unstained tissue for pigment or deposits that could be mistaken for DAB (standard IHC practice). Block endogenous peroxidase before chromogen development and assess a detection only control if diffuse brown signal persists (standard chromogenic IHC practice). The documented method uses a biotinylated secondary, streptavidin biotin complex, and DAB, making detection system background a relevant control (datasheet A00615-1). Titrate primary antibody around the documented 1 μg/ml condition while keeping retrieval and exposure comparable (datasheet A00615-1; standard IHC practice).
How should I score CYP17A1 across testis or adrenal sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population before scoring: Leydig cells in testis or zona fasciculata cells in adrenal gland are supported positive populations (HPA: High expression). For chromogenic IHC, report the percentage of positive cells and an H-score calculated from the proportions at each intensity category (standard IHC practice). Normalize the positive count to all evaluable cells in the same defined compartment, and report sampled tissue area if using positive cell density per mm² (standard IHC practice). Apply one staining threshold and acquisition or review procedure across the comparison set (standard IHC practice). Exclude folds, tissue edges, necrotic areas, and poorly preserved regions from the scored denominator using predefined criteria (standard IHC practice).
When is a CYP17A1 positive IHC result convincing rather than artefactual?
A convincing result labels the expected steroidogenic cells, particularly testicular Leydig cells or adrenal zona fasciculata cells (HPA: High expression). Its cellular distribution should be compatible with endoplasmic reticulum or microsome associated protein, while HPA subcellular imaging also reports vesicles (UniProt P05093 localization; HPA: Vesicles). Question staining confined to nuclei, tissue edges, necrotic regions, or extracellular deposits, especially when expected cells remain unstained (UniProt P05093 localization; standard IHC practice). Check a no primary control and peroxidase blocked section to distinguish detection artefact from CYP17A1 labeling (standard chromogenic IHC practice). Interpret discordance cautiously because HPA rates tissue staining reliability as Enhanced but reports only medium consistency with RNA expression (HPA: reliability description).
Boster reagents

Best CYP17A1 / Steroid 17-alpha-hydroxylase/17,20 lyase IHC Antibodies

A00615-1 has an IHC image from paraffin-embedded human testis (image caption); M00615-1 lists IHC and IF/ICC applications but has no supplied figure (catalog).

Real IHC data IHC analysis of CYP17A1 using anti-CYP17A1 antibody (A00615-1). CYP17A1 was detected in paraffin-embedded section of human testis tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-CYP17A1 Antibody (A00615-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Cytochrome P450 17A1/CYP17A1 Antibody ®
Cat # A00615-1

A00615-1 shows IHC staining in a paraffin-embedded human testis section and lists human and rat reactivity (image caption; catalog). M00615-1 lists IHC and IF/ICC applications and human, mouse and rat reactivity; no IHC or IF image is supplied (catalog).

Which to pick: For tissue IHC with documented staining, choose A00615-1: its caption shows a paraffin-embedded human testis section with citrate retrieval at pH 6 for 20 minutes; the fixative is unreported (image caption). For IF/ICC, consider rabbit monoclonal M00615-1, clone 20C02, because those applications are listed, although no IF image is supplied (catalog). M00615-1 has the broader listed reactivity—human, mouse and rat versus human and rat for A00615-1—but the supplied tissue image documents only A00615-1 in human testis (catalog; image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P05093 (CP17A_HUMAN, Steroid 17-alpha-hydroxylase/17,20 lyase).
  2. Human Protein Atlas. CYP17A1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CYP17A1 subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. CYP17A1 antibody validation summary (1 antibodies).
  5. Accelerated telomere shortening in adrenal zona reticularis in patients with prolonged critical illness. Frontiers in endocrinology 2023 — PMC10512174.
  6. Histopathological spectrum of common aldosterone-driver gene mutations in aldosterone-producing adenomas. Frontiers in medicine 2025 — PMC12185499.
  7. Histopathological and genetic characterization of aldosterone-producing adenomas with concurrent subclinical cortisol hypersecretion: a case series. Endocrine 2017 — PMC5638684.
  8. Incomplete Pattern of Steroidogenic Protein Expression in Functioning Adrenocortical Carcinomas. Biomedicines 2020 — PMC7460193.
  9. PubMed PMID:3025870 — UniProt-cited evidence.
  10. PubMed PMID:3500022 — UniProt-cited evidence.
  11. PubMed PMID:3274893 — UniProt-cited evidence.