CYP2R1 / Vitamin D 25-hydroxylase · IHC design guide

Design Immunohistochemistry for CYP2R1

Plan CYP2R1 IHC around mainly cytoplasmic tissue staining (HPA tissue IHC) and its annotated ER and microsomal membrane location (UniProt). Adrenal glandular cells show high staining (HPA tissue IHC); the catalog antibody lists an IHC dilution of 1:100–1:300 (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
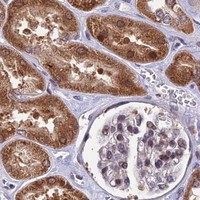
Immunohistochemistry protocol sheet for CYP2R1 (IHC for CYP2R1): expected localisation Mainly cytoplasmic in tissue (HPA tissue IHC), antibody A03557, validated IHC image, and IHC protocol steps
Printable CYP2R1 IHC protocol sheet — expected localisation Mainly cytoplasmic in tissue (HPA tissue IHC), antibody A03557, controls and protocol steps. Open the full CYP2R1 IHC guide →

CYP2R1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic in tissue (HPA tissue IHC)
Staining pattern Cytoplasmic staining in most tissues; high in glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Medium staining–RNA concordance; verification pending (HPA tissue IHC)
Regulation Expression regulation not established (UniProt)
Isoform / epitope No annotated isoforms; signal peptide 1–26, chain 27–501 (UniProt)
Section 1

Recommended CYP2R1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published CYP2R1 methods for liver sections (PMC8494743) and colorectal tumour sections (PMC5216813).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon carcinoma tissue; fixative not specified (datasheet A03557)
FixationImage fixative and duration unreported (datasheet A03557); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CYP2R1, 1:100-1:300 (datasheet A03557)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCYP2R1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen-retrieval setting). The published monoclonal method omitted retrieval (PMC5216813).
Section 2

What Is the Expected CYP2R1 Staining Pattern?

CYP2R1 is associated with the endoplasmic reticulum and microsome membranes, with no annotated transmembrane segment (UniProt Q6VVX0 topology). In paraffin section IHC, expect mainly cytoplasmic staining across many tissues, including strong staining in several glandular, respiratory epithelial and hematopoietic cell populations (HPA tissue IHC). HPA rates the tissue staining “Approved,” with medium agreement between staining and RNA data; external verification is pending (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in adrenal gland or appendix glandular cells, with clear tissue structure and limited background.This fits the reported high staining in those cells (HPA tissue IHC: High). The compartment also fits CYP2R1’s endoplasmic reticulum and microsome association (UniProt Q6VVX0). A matching pattern supports interpretation, but HPA’s Approved rating still carries a pending external verification caveat (HPA tissue IHC).
Strong, predominantly nuclear or extracellular signal, without a convincing cytoplasmic component.That compartment conflicts with the mainly cytoplasmic tissue profile (HPA tissue IHC) and the annotated membrane associated location (UniProt Q6VVX0). Treat it as a possible staining artefact; assess morphology and controls before scoring it as CYP2R1 (standard IHC practice).
Signal is concentrated in an unexpected cell population while the expected cells show little staining.Consider antibody cross-reactivity or endogenous detection activity (standard IHC practice). Compare cell identity with the tissue specific HPA observations before judging the pattern: HPA reports high staining in bronchial respiratory epithelial cells and bone marrow hematopoietic cells, among others (HPA tissue IHC).
Diffuse color covers cells and surrounding tissue, obscuring cytoplasmic boundaries.This is difficult to score as specific cytoplasmic staining. Background can arise from nonspecific binding, incomplete blocking or endogenous chromogenic detection activity (standard IHC practice). Assess a control lacking primary antibody and inspect whether color follows recognizable cells (standard IHC practice).
No detectable signal in a reference section expected to stain strongly.First confirm the reference cell population is present; HPA reports high staining in adrenal glandular cells and bronchial respiratory epithelial cells (HPA tissue IHC). A blank reference section calls the run into question, but HPA’s medium staining to RNA consistency means one result alone cannot settle target expression (HPA tissue IHC).
💡Expected CYP2R1 appearanceCall a result consistent with CYP2R1 when staining is predominantly cytoplasmic and strong in an HPA high cell population, such as adrenal glandular cells; dominant nuclear, extracellular or diffuse background color is suspect (HPA tissue IHC; UniProt Q6VVX0; standard IHC practice).
How each factor affects the staining
Reference cell populationHPA reports high staining in glandular cells of adrenal gland, appendix, breast, duodenum, epididymis and gallbladder; bronchial respiratory epithelial and bone marrow hematopoietic cells are also high (HPA tissue IHC). Choose a reference by cell type, not by the presence of tissue alone (standard IHC practice).
Strength of a low staining comparatorNon-germinal center cells in lymph node are listed as low, while no negative tissue is supplied (HPA tissue IHC). Low staining is a comparison point, not proof that a completely blank section is required or that every other lymph node cell is negative.
Location and processingUniProt places CYP2R1 at endoplasmic reticulum and microsome membranes, annotates a signal sequence at residues 1–26 and a chain at 27–501, and lists no transmembrane segment or isoforms (UniProt Q6VVX0). These annotations support compartment interpretation; they do not identify this antibody’s epitope or establish an antigen retrieval requirement.
Evidence strengthThe tissue IHC profile is Approved, described as having medium consistency with RNA expression and awaiting external verification; the listed HPA042949 IHC status is Approved (HPA tissue IHC; HPA antibodies). Interpret an unexpected pattern with controls and tissue morphology rather than treating the reference image as conclusive (standard IHC practice).
Chromogenic detectionEndogenous detection activity can create color independent of primary antibody binding (standard IHC practice). Its presence is assessed with detection appropriate controls; the supplied HPA and UniProt records do not establish a CYP2R1 specific source of endogenous activity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reference section expected to stain strongly is blank.The relevant cells may be absent, or the IHC run may have lost signal (standard IHC practice); HPA lists several high staining reference populations (HPA tissue IHC).Verify the expected cells on the section, then check the run controls and the catalog antibody’s IHC-P instructions for retrieval, dilution and detection settings (standard IHC practice). Do not infer a CYP2R1 specific fixation effect from this result.
Color is widespread outside recognizable cells.Nonspecific staining or endogenous chromogenic detection activity may obscure the mainly cytoplasmic pattern (standard IHC practice; HPA tissue IHC).Inspect a control lacking primary antibody, review blocking and detection controls, and score only signal that follows intact cell morphology (standard IHC practice).
Nuclei dominate the staining.A nuclear dominant pattern disagrees with HPA’s mainly cytoplasmic profile and UniProt’s endoplasmic reticulum and microsome location (HPA tissue IHC; UniProt Q6VVX0).Check the counterstain and detection controls, then reassess whether cytoplasmic signal is present in an HPA high reference cell population (standard IHC practice; HPA tissue IHC).
Unexpected cells stain more strongly than the HPA reference population.Cross-reactivity or endogenous detection activity is possible (standard IHC practice). HPA describes broad tissue expression, so unexpected staining alone does not establish either cause (HPA tissue IHC).Confirm cell identity and compare matched controls with the HPA cell specific observations; document the discrepancy rather than assigning CYP2R1 from color alone (standard IHC practice; HPA tissue IHC).
Lymph node non-germinal center cells show faint staining.Low staining in that population is reported by HPA (HPA tissue IHC).Compare its intensity and compartment with a high staining reference population in the same run; do not treat this HPA low population as a validated negative control (HPA tissue IHC; standard IHC practice).
IF/ICC question: should an IF image reproduce the IHC slide pattern?HPA supplies no main ICC-IF location or cell line ICC-IF images for CYP2R1 (HPA subcellular). The tissue staining observations come from IHC (HPA tissue IHC).Use the UniProt endoplasmic reticulum and microsome location as a compartment expectation, while evaluating IF/ICC controls and imaging independently (UniProt Q6VVX0; standard IF practice).

Sample controls for CYP2R1 IHC & IF

🧪Run adrenal gland first and score staining in its glandular cells (HPA: High in adrenal gland glandular cells). HPA detects CYP2R1 in all 45 scored tissues, so there is no validated negative tissue; use no-primary and isotype controls, and treat unstained cells within the positive section only as background comparators, not proven target-negative cells (HPA: no negative rows; detected in all 45 scored tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: CYP2R1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CYP2R1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and clonality; use knockout material if available or a peptide-blocked antibody aliquot as a biological specificity control (A03557 caption: peptide block). For chromogenic detection, check endogenous peroxidase background in the adrenal section and block endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A03557 paraffin-section caption does not state a fixative (A03557 caption: paraffin-embedded colon carcinoma; fixative unreported). Antigen retrieval dependence is also unreported; optimize retrieval empirically for paraffin-section IHC (standard IHC practice). There is no supplied basis to call frozen sections or IF/ICC easier, and adrenal chromogenic staining should be checked for endogenous peroxidase background (HPA: no ICC-IF image cell lines; standard IHC practice).

HPA tissue IHC evidence for CYP2R1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: CYP2R1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced CYP2R1 IHC Tips

Troubleshoot CYP2R1 staining in paraffin sections by checking retrieval, compartment, controls and scoring before interpreting chromogenic signal.

How should I retrieve CYP2R1 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes (page retrieval rule: cytoplasmic / membrane antigen). Let sections cool in the buffer, then compare a small retrieval time series using the same antibody concentration and detection conditions (standard IHC practice). CYP2R1 is associated with endoplasmic reticulum and microsome membranes, so judge retrieval by cytoplasmic staining in intact cells rather than by diffuse section colour (UniProt Q6VVX0 localisation; HPA: mainly cytoplasmic expression). If staining remains weak, compare a second retrieval condition as a fallback while retaining the citrate condition as the reference and monitoring tissue damage and background (standard IHC practice).
Could fixation explain weak or uneven CYP2R1 staining?
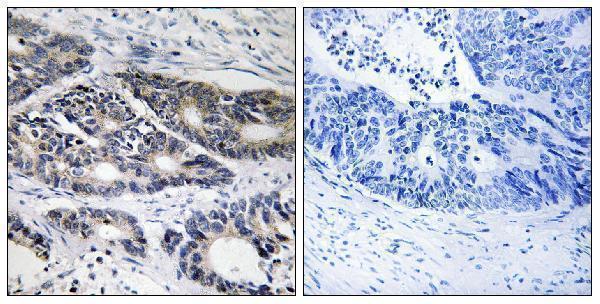
The selected CYP2R1 image shows paraffin-embedded human colon carcinoma, but its caption does not report the fixative (A03557 tissue-IHC caption). Target-specific sensitivity to fixation is therefore unknown; neither tissue staining patterns nor CYP2R1 topology establishes it (A03557 tissue-IHC caption; HPA tissue IHC; UniProt Q6VVX0 topology). Record the fixative, fixation duration and section age for each case, then compare similarly processed sections under the same pH 6.0, 20-minute retrieval condition (standard IHC practice; page retrieval rule). If staining varies across a section, inspect preservation and section adhesion before changing antibody concentration, and include a consistently processed control section in each run (standard IHC practice).
What CYP2R1 staining pattern should I accept as plausible?
Expect predominantly cytoplasmic chromogenic signal in intact cells, consistent with the tissue profile and CYP2R1 association with endoplasmic reticulum and microsome membranes (HPA: mainly cytoplasmic expression; UniProt Q6VVX0 localisation). The record annotates no transmembrane segment, so it does not justify calling a crisp cell-surface outline the expected pattern (UniProt Q6VVX0 topology). Compare glandular cells and nearby compartments within the same section; strong glandular-cell staining is reported in several tissues, while low staining is reported for lymph-node non-germinal-centre cells (HPA tissue IHC). Assess staining at the cellular level with morphology and counterstain visible, and investigate isolated nuclear or acellular signal before scoring it as CYP2R1 (standard IHC practice).
How can I assess whether the antibody recognises the relevant CYP2R1 epitope?
Check the antibody's disclosed immunogen against the mature CYP2R1 chain, residues 27–501; the record also annotates a signal sequence at 1–26 (UniProt Q6VVX0 processing). No isoforms, glycosylation sites or modified residues are annotated, so the record supplies no isoform-specific or modification-dependent explanation for a staining difference (UniProt Q6VVX0 annotations). The selected paraffin-section image includes a synthesized-peptide blocking comparison, which supports assessing that reagent's peptide-sensitive signal without establishing every tissue epitope or its membrane-facing side (A03557 tissue-IHC caption; UniProt Q6VVX0 topology). If epitope details are unavailable, use appropriate controls and compare cellular localisation before attributing a negative section to CYP2R1 absence (standard IHC practice).
How should I check a CYP2R1 IF result against the chromogenic IHC result?
Treat IF/ICC as a separate application: the supplied subcellular record lists no cell lines with ICC/IF images, while the selected product image documents paraffin-section IHC (HPA subcellular; A03557 tissue-IHC caption). For multiplex IF, pair CYP2R1 with a marker identifying the expected cell population, such as a glandular epithelial marker where glandular cells are being assessed (HPA tissue IHC; standard IF practice). Choose fluorophores after checking unstained tissue autofluorescence and include single-colour controls to distinguish overlap from bleed-through (standard IF practice). Because the record does not specify which side of the endoplasmic reticulum membrane contains the antibody epitope, optimise permeabilisation against the disclosed epitope and verify that cellular structure remains interpretable (UniProt Q6VVX0 localisation and topology; standard IF practice).
How do I distinguish CYP2R1 signal from chromogenic IHC background?
Run a no-primary control and inspect endogenous pigment, diffuse substrate deposition and staining at tissue edges before adjusting the CYP2R1 antibody (standard IHC practice). For peroxidase detection, apply an endogenous peroxidase block before the detection reagent and monitor DAB development consistently across sections; these are general workflow steps (standard IHC practice). Compare suspicious colour with the selected image's peptide-blocked condition where that exact antibody and blocking reagent are available (A03557 tissue-IHC caption). Preserve the pH 6.0, 20-minute retrieval reference while changing one background-control variable at a time, and accept signal only when cellular morphology and cytoplasmic localisation remain clear (page retrieval rule; HPA: mainly cytoplasmic expression; standard IHC practice).
What should I measure when comparing CYP2R1 staining between sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then record the percentage of positive intact cells and cytoplasmic intensity separately (standard IHC practice; HPA: mainly cytoplasmic expression). An H-score can combine intensity categories 0–3 with their percentages for a 0–300 range, while positive-cell density per mm² can suit mapped regions (standard IHC practice). Normalise cell counts to the eligible cell population, or density to analysed viable tissue area, and exclude folds, necrosis and missing tissue using the same rules for every section (standard IHC practice). Keep retrieval, chromogen development, imaging and scoring thresholds consistent, and report cell-type-specific results because the tissue profile varies by cell population (standard IHC practice; HPA tissue IHC).
When is a positive CYP2R1 IHC result biologically credible?
A credible result places signal in intact cell cytoplasm, consistent with the reported tissue pattern and CYP2R1 endoplasmic reticulum or microsome association (HPA: mainly cytoplasmic expression; UniProt Q6VVX0 localisation). Compare the stained cell type with morphology: glandular cells are reported high in several tissues, whereas lymph-node non-germinal-centre cells are reported low (HPA tissue IHC). Discount colour confined to cut edges, necrotic material or sites of endogenous enzyme activity when corresponding controls indicate artefact (standard IHC practice). Interpret peptide blocking for the selected antibody as evidence about peptide-sensitive staining, and retain uncertainty about broader tissue specificity because the HPA tissue profile has medium RNA–staining consistency and awaits external verification (A03557 tissue-IHC caption; HPA reliability).
Boster reagents

Best CYP2R1 / Vitamin D 25-hydroxylase IHC Antibodies

A03557 has real IHC data from paraffin-embedded human colon carcinoma (IHC image caption), catalog-listed IF use (catalog: applications), and listed human, monkey, and mouse reactivity (catalog: reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human colon carcinoma, using Cytochrome P450 2R1 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-Vitamin D 25-hydroxylase CYP2R1 Antibody
Cat # A03557

A03557 will render with its own IHC image from paraffin-embedded human colon carcinoma (IHC image caption). The catalog lists IHC and IF applications and human, monkey, and mouse reactivity (catalog: applications; reactivity); no IF image is supplied (catalog: IF image alts).

Which to pick: For tissue IHC, choose A03557 based on its paraffin-section image (IHC image caption); the fixative is unreported (IHC image caption). For IF/ICC planning, A03557 has listed IF use, but no IF image or ICC-specific validation is supplied (catalog: applications; IF image alts). For cross-species work, A03557 is rabbit polyclonal (catalog: host; dilution_raw) with listed human, monkey, and mouse reactivity (catalog: reactivity); its IHC image shows only a human sample (IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6VVX0 (CP2R1_HUMAN, Vitamin D 25-hydroxylase).
  2. Human Protein Atlas. CYP2R1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CYP2R1 subcellular location (ICC-IF): Highest expression in NB4: 12.0 nTPM.
  4. Human Protein Atlas. CYP2R1 antibody validation summary (1 antibodies).
  5. Phosphate, calcium, and vitamin D signaling, transport, and metabolism in the endometria of cyclic ewes. Journal of animal science and biotechnology 2023 — PMC9835233.
  6. Effect and mechanism of vitamin D activation disorder on liver fibrosis in biliary atresia. Scientific reports 2021 — PMC8494743.
  7. Characterisation of the oxysterol metabolising enzyme pathway in mismatch repair proficient and deficient colorectal cancer. Oncotarget 2016 — PMC5216813.
  8. Differential Expression of Prostaglandin I2 Synthase Associated with Arachidonic Acid Pathway in the Oral Squamous Cell Carcinoma. Journal of oncology 2018 — PMC6250001.
  9. PubMed PMID:12867411 — UniProt-cited evidence.
  10. PubMed PMID:15465040 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.