CYP51A1 / Lanosterol 14-alpha demethylase · IHC design guide

Design Immunohistochemistry for CYP51A1

Plan chromogenic CYP51A1 IHC in paraffin sections using Leydig-cell cytoplasmic staining as the tissue reference (HPA tissue IHC). The IHC-validated antibody has a listed dilution of 1:10–1:50 (datasheet: A04032-2); interpret staining with the reported antibody specificity caution (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
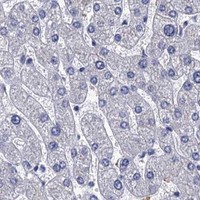
Immunohistochemistry protocol sheet for CYP51A1 (IHC for CYP51A1): expected localisation Leydig-cell cytoplasm (HPA tissue IHC); ER membrane expected (UniProt), antibody A04032-2, validated IHC image, and IHC protocol steps
Printable CYP51A1 IHC protocol sheet — expected localisation Leydig-cell cytoplasm (HPA tissue IHC); ER membrane expected (UniProt), antibody A04032-2, controls and protocol steps. Open the full CYP51A1 IHC guide →

CYP51A1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Leydig-cell cytoplasm (HPA tissue IHC); ER membrane expected (UniProt)
Staining pattern Cytoplasmic staining in Leydig cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Testis
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Possible staining of proteins from another gene (HPA tissue IHC)
Regulation Stimulus-dependent regulation not reported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended CYP51A1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published CYP51A1 chromogenic IHC protocol (PMC5216813).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleFFPE human prostate carcinoma tissue (datasheet A04032-2)
FixationImage formalin-fixed; duration unreported (datasheet A04032-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CYP51A1, 1:10-1:50 (datasheet A04032-2)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCYP51A1-positive staining in leydig cells of testis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in Leydig cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval); the published protocol also uses citrate pH 6 (PMC5216813).
Section 2

What Is the Expected CYP51A1 Staining Pattern?

CYP51A1 is an endoplasmic reticulum and microsomal membrane protein with one transmembrane segment at residues 30–50 (UniProt Q16850). In paraffin sections, expect cytoplasmic staining strongest in testicular Leydig cells (HPA tissue IHC: High in Leydig cells). HPA rates the tissue staining Approved, while reporting low agreement with RNA data, possible recognition of more than one gene, and a splice or transcript discrepancy (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic staining in testicular Leydig cells.This matches the reported high Leydig-cell signal (HPA tissue IHC: High) and the expected membrane-associated cytoplasmic location (UniProt Q16850 topology). Assess the cell identity and distribution together; intensity alone is less informative.
Predominantly nuclear staining, or a sharp cell-surface outline with little cytoplasmic signal.These compartments differ from the reported ER and microsomal membrane location (UniProt Q16850). Treat the pattern as suspect and compare it with a positive tissue and a no-primary control (standard IHC practice).
Strong staining in adipocytes or another cell population reported as negative.HPA reports adipocytes in adipose tissue and breast as Not detected (HPA tissue IHC). Possible explanations include antibody cross-reactivity or endogenous detection activity; the slide alone cannot distinguish them. Check the antibody and detection controls (standard IHC practice).
Diffuse color over cells and extracellular space, obscuring cell boundaries.A widespread haze cannot establish the Leydig-cell cytoplasmic pattern (HPA tissue IHC). Review the no-primary control, background blocking, washes, and chromogen development (standard IHC practice) before scoring specific staining.
No discernible signal in the testicular Leydig-cell positive control.Because HPA reports High staining in these cells, a blank control makes a negative study section hard to interpret (HPA tissue IHC). Confirm tissue identity, antibody suitability for IHC-P, retrieval, dilution, and detection with appropriate controls (standard IHC practice).
💡Expected CYP51A1 appearanceCall a result positive when testicular Leydig cells show strong cytoplasmic staining (HPA tissue IHC: High; UniProt Q16850: ER/microsomal membrane); nuclear-only or diffuse extracellular color is suspect (UniProt Q16850; standard IHC practice).
How each factor affects the staining
Membrane topologyCYP51A1 has one predicted transmembrane segment at residues 30–50 and is assigned to ER and microsomal membranes (UniProt Q16850). Interpret chromogenic signal as cytoplasmic at light-microscope resolution; the record does not define a required fine-grained IHC pattern.
Positive and lower-signal tissue contextHPA reports High staining in testicular Leydig cells and Low staining in adrenal glandular cells (HPA tissue IHC). The adrenal result may be harder to score; use the stronger documented positive pattern when judging whether the stain worked.
Antibody evidence and limitsTwo listed rabbit polyclonal antibodies, HPA041325 and HPA043508, are rated Approved for IHC (HPA antibodies). The tissue summary flags low RNA agreement, possible multi-gene recognition, and a splice or transcript discrepancy (HPA tissue IHC); Approved is not proof that every positive cell is specific.
Isoforms and epitope coverageUniProt lists two isoforms but supplies no epitope positions or isoform-specific staining pattern (UniProt Q16850). If an antibody gives an unexpected distribution, check its documented immunogen or epitope before attributing the difference to an isoform (standard IHC practice).
IF/ICC Q: What location should fluorescence show?A: HPA reports an approved ER location in ICC-IF, with a caution that the evidence uses antibodies targeting proteins from multiple genes (HPA subcellular ICC-IF). Use that location as supporting context for IHC interpretation, not as proof of IHC antibody specificity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Leydig cells are blank while the whole section is pale.The expected high positive signal is absent (HPA tissue IHC: High in Leydig cells); the failure point is not identifiable from this image alone.Check that the control contains Leydig cells, then review the IHC-P antibody instructions, retrieval, dilution, detection reagents, and chromogen development (standard IHC practice).
Leydig cells stain weakly, and adrenal glandular cells are also weak.Adrenal glandular cells have a reported Low level, so their faint staining alone is not evidence of assay failure (HPA tissue IHC).Judge the run against testicular Leydig cells, reported as High (HPA tissue IHC), and compare control sections processed in the same run (standard IHC practice).
Strong color appears in adipocytes despite little Leydig-cell staining.That distribution conflicts with HPA's High Leydig-cell and Not detected adipocyte observations (HPA tissue IHC); cross-reactivity or detection background are possibilities.Inspect no-primary and detection controls, confirm tissue identity, and reassess the antibody's IHC validation before assigning the color to CYP51A1 (standard IHC practice; HPA antibodies).
Nuclei dominate the stain.Nuclear predominance does not match the ER and microsomal membrane assignment (UniProt Q16850); morphology alone cannot establish the source of the color.Check counterstain and chromogen appearance, compare a no-primary control, and review the antibody's documented IHC pattern (standard IHC practice).
A diffuse brown haze obscures which cells stain.Unresolved background prevents assessment of the reported cytoplasmic Leydig-cell signal (HPA tissue IHC).Compare the no-primary control, then optimize blocking, washing, antibody dilution, and development time using the antibody's IHC instructions (standard IHC practice).
Two antibodies give different cell distributions.Both listed antibodies are IHC Approved, but HPA notes low RNA agreement, possible multi-gene targeting, and a splice or transcript discrepancy (HPA antibodies; HPA tissue IHC).Compare their documented targets and epitope information, then prioritize the pattern that agrees with the reported Leydig-cell staining and ER location (HPA tissue IHC; UniProt Q16850).

Sample controls for CYP51A1 IHC & IF

🧪Run testis first and score Leydig cells for strong staining (HPA: High in Leydig cells). Use adipose tissue adipocytes as a negative comparator (HPA: Not detected in adipocytes); on the testis slide, compare other cells with Leydig cells, but do not label them confirmed internal negatives because their staining levels are not supplied (HPA: Leydig-cell row only).
Positive control tissue: Testis (Leydig cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CYP51A1 in A-431, U-251MG, U2OS, MCF-7, with annotated localisation: Endoplasmic reticulum (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and primary-host- and isotype-matched controls, plus a CYP51A1 knockout sample or cognate-peptide block if available (standard IHC practice). For DAB staining in testis, quench endogenous peroxidase and check background in the no-primary section; assess endogenous biotin if using biotin-based detection (standard IHC practice).
⚠️Feasibility: The selected A04032-2 caption explicitly describes a formalin-fixed, paraffin-embedded prostate carcinoma section stained with DAB, but reports no CYP51A1-specific fixation window or fixation effect (selected-SKU tissue-IHC caption). Antigen-retrieval dependence is unreported in the supplied evidence, so optimize retrieval on the testis control (HPA: High in Leydig cells; standard IHC practice). The supplied evidence does not establish that frozen sections or IF are easier, and documents no testis-specific artefact; check peroxidase background when interpreting chromogenic staining (standard IHC practice).

HPA tissue IHC evidence for CYP51A1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene. Caution, Splice and/or transcript discrepancy exists.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Leydig cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CYP51A1 IHC Tips

Troubleshoot CYP51A1 staining in paraffin sections by checking retrieval, cytoplasmic localisation, controls and scoring before interpreting chromogenic signal.

How should I optimise retrieval when CYP51A1 staining is weak in paraffin sections?
Begin CYP51A1 paraffin IHC with citrate pH 6.0 heat retrieval at 95–98 °C for 20 min (page retrieval rule). Let sections cool in retrieval buffer, then compare the same staining run across a positive control and a matched section processed without primary antibody (standard IHC practice). If staining remains weak, test a longer citrate retrieval period first, watching for tissue damage or increased background (standard IHC practice). Only then consider an alternative buffer as a fallback, recording its pH and heating time alongside the citrate result (standard IHC practice). Judge improvement by clearer cytoplasmic staining in the expected cells, rather than darker staining across the whole section (HPA tissue IHC; standard IHC practice).
Could fixation explain weak CYP51A1 staining in my paraffin sections?
Target-specific fixation sensitivity is unknown because no comparison of fixatives or fixation times is supplied for CYP51A1 (supplied evidence). The selected A04032-2 image documents formalin-fixed, paraffin-embedded human prostate carcinoma stained by a peroxidase secondary antibody and DAB, but establishes only that this workflow produced an image (A04032-2 tissue-IHC caption). Record fixation duration, section thickness and processing history when comparing specimens, and stain matched controls together (standard IHC practice). If signal varies with processing, repeat the comparison using the same retrieval and detection conditions before assigning the difference to fixation (standard IHC practice). Do not infer fixation tolerance from CYP51A1 membrane topology or expression patterns (UniProt Q16850 topology; HPA tissue IHC).
What staining pattern should I expect, and when is localisation suspicious?
Expect predominantly cytoplasmic, potentially reticular staining because CYP51A1 resides in the endoplasmic reticulum and microsome membranes (UniProt Q16850 subcellular location). Its annotated transmembrane segment spans residues 30–50, supporting membrane association without defining the antibody epitope or its accessibility in fixed sections (UniProt Q16850 topology). HPA reports cytoplasmic expression in Leydig cells and an approved endoplasmic reticulum location, while cautioning that its antibodies may recognise proteins from multiple genes (HPA tissue IHC; HPA subcellular). Diffuse nuclear staining or staining confined to section edges warrants checking retrieval, background and antibody specificity (UniProt Q16850 subcellular location; standard IHC practice). Compare the pattern with a no-primary control before scoring cells (standard IHC practice).
How can epitope location and isoforms affect CYP51A1 IHC interpretation?
CYP51A1 has 2 annotated isoforms, but the supplied record does not identify the catalog antibody’s immunogen or establish which isoforms it detects (UniProt Q16850 isoforms; supplied evidence). The annotated protein chain spans residues 1–509, with one transmembrane segment at 30–50 and no annotated glycosylation sites (UniProt Q16850 processing, topology and glycosylation). Check the antibody’s documented epitope against isoform sequences before claiming isoform-specific staining (standard IHC practice). Optimise retrieval on matched sections if an epitope appears poorly accessible, while keeping detection conditions constant (standard IHC practice). A blocking peptide can support epitope binding, but cannot alone establish cellular specificity in tissue (standard IHC practice).
How should I adapt CYP51A1 localisation checks to multiplex IF?
Use IF as a localisation cross-check for chromogenic IHC, and multiplex CYP51A1 with an independently validated Leydig-cell marker when examining the HPA-positive testis compartment (HPA tissue IHC; standard IF practice). HPA reports endoplasmic reticulum localisation but cautions that its subcellular antibodies may target proteins from multiple genes, so confirm the IF reagent’s identity and specificity (HPA subcellular). Choose a spectrally separated, preferably far-red fluorophore after inspecting unstained tissue for autofluorescence (standard IF practice). Optimise permeabilisation for the antibody’s documented epitope side of the membrane; the 30–50 transmembrane annotation alone does not establish that side (UniProt Q16850 topology; standard IF practice). Include single-colour and no-primary controls to assess bleed-through and background (standard IF practice).
How do I reduce diffuse brown staining without losing CYP51A1 signal?
First compare stained sections with no-primary and secondary-only controls to separate antibody-dependent signal from detection background (standard IHC practice). The selected A04032-2 image used a peroxidase-conjugated secondary antibody followed by DAB in formalin-fixed, paraffin-embedded human prostate carcinoma (A04032-2 tissue-IHC caption). For a peroxidase workflow, block endogenous peroxidase, use an appropriate protein block, and titrate primary antibody and DAB development against the controls (standard IHC practice). Keep washes and counterstaining consistent across sections so changes in brown signal remain interpretable (standard IHC practice). Treat staining at section edges, folds or damaged areas as suspect until it persists in intact tissue with the expected cytoplasmic distribution (UniProt Q16850 subcellular location; standard IHC practice).
How should I score CYP51A1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: HPA reports high cytoplasmic staining in testis Leydig cells, while UniProt places CYP51A1 at endoplasmic reticulum membranes (HPA tissue IHC; UniProt Q16850 subcellular location). For intensity scoring, calculate an H-score from the percentages of viable cells at intensities 0–3, giving a possible range of 0–300 (standard IHC practice). Alternatively, report the percentage of positive viable cells or positive-cell density per mm², with the threshold fixed before comparison (standard IHC practice). Normalise to the same defined cell population or viable tissue area, and exclude necrosis, folds and edges (standard IHC practice). Record retrieval, imaging and scoring settings for each batch (standard IHC practice).
Which observations support a true CYP51A1 positive rather than artefact?
A credible positive is cytoplasmic in an expected cell population, consistent with CYP51A1 endoplasmic reticulum localisation and HPA’s high Leydig-cell staining in testis (UniProt Q16850 subcellular location; HPA tissue IHC). Check that this pattern is absent from no-primary and secondary-only controls, and that it persists in intact tissue away from edges and necrosis (standard IHC practice). Diffuse nuclear staining, brown deposits unrelated to cells, or signal removed by an endogenous peroxidase block should prompt investigation (UniProt Q16850 subcellular location; standard IHC practice). The A04032-2 prostate carcinoma image demonstrates an IHC workflow, but its caption does not establish clinical relevance (A04032-2 tissue-IHC caption). Interpret HPA patterns cautiously because its tissue-IHC record reports low staining-to-RNA consistency and possible multi-gene recognition (HPA tissue IHC).
Boster reagents

Best CYP51A1 / Lanosterol 14-alpha demethylase IHC Antibodies

Catalog antibodies have real CYP51A1 IHC data from human prostate carcinoma and IF data from CACO-2 cells; listed reactivity covers human, mouse, and monkey (catalog images and reactivity).

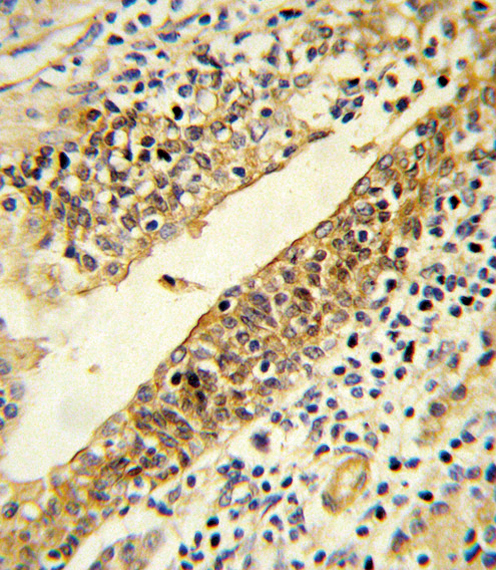
Real IHC data Formalin-fixed and paraffin-embedded human prostate carcinoma reacted with CYP51A1 Antibody (Center) , which was peroxidase-conjugated to the secondary antibody, followed by DAB staining. This data demonstrates the use of this antibody for immunohistochemistry; clinical relevance has not been evaluated.
Anti-CYP51A1 Antibody (Center)
Cat # A04032-2
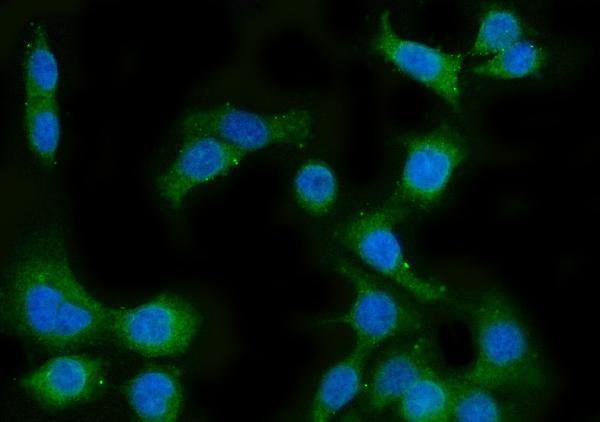
Real IF data IF analysis of CYP51A1/CYP51 using anti-CYP51A1/CYP51 antibody (A04032-1). CYP51A1/CYP51 was detected in immunocytochemical section of CACO-2 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5μg/mL rabbit anti-CYP51A1/CYP51 Antibody (A04032-1) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-CYP51A1/CYP51 Antibody ®
Cat # A04032-1

A04032-2 is listed for human IHC-P and has a DAB-stained image of formalin-fixed, paraffin-embedded human prostate carcinoma (catalog applications, reactivity, and IHC image). A04032-1 is listed for ICC/IF and has an IF image of CACO-2 cells (catalog applications and IF image).

Which to pick: Choose A04032-2 for human tissue IHC-P: it is polyclonal, with a listed dilution of 1:10–1:50 and an image from formalin-fixed, paraffin-embedded human prostate carcinoma (catalog dilution_raw, applications, and IHC image). Choose A04032-1 for IF/ICC at the listed 5 μg/mL; its image shows CACO-2 cells, and its listed reactivity includes human, mouse, and monkey (catalog IF image, dilution, and reactivity). Mouse and monkey IF examples are unreported in the supplied images (catalog IF image).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q16850 (CP51A_HUMAN, Lanosterol 14-alpha demethylase).
  2. Human Protein Atlas. CYP51A1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CYP51A1 subcellular location (ICC-IF): Localized to the endoplasmic reticulum. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. CYP51A1 antibody validation summary (2 antibodies).
  5. Machine Learning-based Framework Develops a Tumor Thrombus Coagulation Signature in Multicenter Cohorts for Renal Cancer. International journal of biological sciences 2024 — PMC11234220.
  6. Characterisation of the oxysterol metabolising enzyme pathway in mismatch repair proficient and deficient colorectal cancer. Oncotarget 2016 — PMC5216813.
  7. Atorvastatin inhibits pancreatic carcinogenesis and increases survival in LSL-KrasG12D-LSL-Trp53R172H-Pdx1-Cre mice. Molecular carcinogenesis 2013 — PMC3411900.
  8. PubMed PMID:8619637 — UniProt-cited evidence.
  9. PubMed PMID:8797093 — UniProt-cited evidence.
  10. PubMed PMID:8809088 — UniProt-cited evidence.