This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan DAB2 paraffin-section IHC around its reported cytoplasmic tissue staining (HPA tissue IHC). Use high-staining Hofbauer cells and lung macrophages to assess the expected pattern, and score mixed tissues by cell type (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic signal, mainly in placenta and peripheral leukocytes (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A01546-3) | |
| Positive control | Lung+4 more · see all | |
| Negative control | Appendix+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | High macrophage staining can complicate cell-level scoring (HPA tissue IHC) | |
| Regulation | Expression regulation is unreported (UniProt) | |
| Isoform / epitope | 3 isoforms; cytoplasmic protein with no transmembrane segment; epitope coverage unknown (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A01546-3) is accompanied by published DAB2 IHC methods for endometrial cancer (PMC5047385) and breast cancer (PMC3956763).
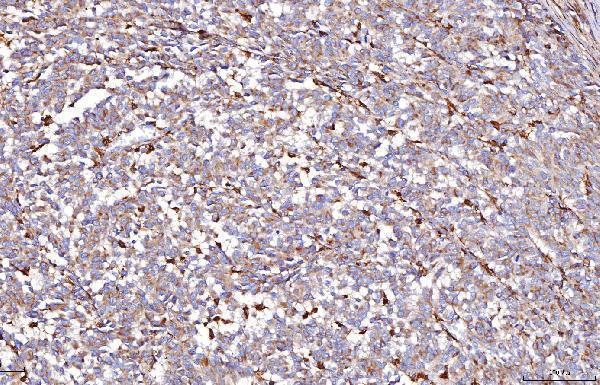
| Sample | Paraffin-embedded human melanoma tissue; fixative not specified (datasheet A01546-3) |
| Fixation | Image fixative and duration unreported (datasheet A01546-3); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A01546-3); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A01546-3) |
| Primary antibody | Rabbit anti-DAB2, 2-5 μg/ml (datasheet A01546-3) |
| Primary incubation | Overnight at 4 °C (datasheet A01546-3) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A01546-3) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | DAB2-positive staining in macrophages of lung (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in placenta and peripheral leukocytes. No signal in the no-primary control. |
DAB2 is cytoplasmic and associates with clathrin-coated pits and vesicles; it has no transmembrane segment (UniProt P98082: localization and topology). In tissue IHC, expect cytoplasmic staining, especially in lung macrophages and placental Hofbauer cells (HPA: High in both). HPA rates the tissue IHC profile Enhanced, with medium consistency between staining and RNA expression (HPA: tissue IHC reliability).
| Cytoplasmic staining in lung macrophages or placental Hofbauer cells, stronger than surrounding unstained cells (HPA: High in both cell types). | This matches the reported cell-specific IHC pattern (HPA: tissue IHC). Vesicle-associated or peripheral emphasis is plausible given DAB2's association with coated pits and vesicles, but chromogenic IHC may not resolve individual vesicles (UniProt P98082: localization; standard IHC resolution). |
| Predominantly nuclear staining in a putative positive cell, without a convincing cytoplasmic component. | Treat this as a localization mismatch requiring review, since the tissue IHC profile is cytoplasmic (HPA: tissue IHC). ICC-IF additionally reports a nucleolar fibrillar-center location; that observation alone does not establish a predominantly nuclear tissue IHC pattern (HPA: subcellular ICC-IF). |
| Strong signal in a cell type reported as undetected, such as bronchial basal cells or heart cardiomyocytes (HPA: Not detected in those cells). | Review cell identification and assay controls before calling it DAB2. Cross-reactivity or endogenous chromogenic activity are possible general IHC explanations; an HPA 'Not detected' entry is an observed pattern, not proof that every specimen must be negative (HPA: tissue IHC; standard IHC practice). |
| Uniform brown haze across cells, stroma, and empty regions, obscuring cell boundaries. | This does not support a cell-specific DAB2 call. Assess background from detection reagents, incomplete blocking, or excessive primary-antibody concentration using appropriate controls (standard IHC practice); HPA instead describes cytoplasmic expression mainly in placenta and peripheral leukocytes (HPA: tissue IHC profile). |
| No staining in lung macrophages or placental Hofbauer cells (HPA: High in both cell types). | An absent signal in an expected-positive cell warrants checking the assay and tissue identity before interpreting other sections as negative (standard IHC practice). The HPA profile has medium staining-to-RNA consistency, so its positive examples are useful benchmarks rather than guaranteed results in every specimen (HPA: tissue IHC reliability). |
| Cell-specific reference pattern | HPA reports High staining in lung macrophages and placental Hofbauer cells, Medium in several other listed cell types, and Not detected in selected cells (HPA: tissue IHC). Score the identified cell population within its tissue rather than assigning one intensity to an entire section (standard IHC practice). |
| Subcellular localization | DAB2 is cytoplasmic and associates with coated vesicles and pits; it has no transmembrane segment (UniProt P98082: localization and topology). A peripheral accent can fit that biology, but a crisp continuous surface outline is not required for a positive chromogenic section (standard IHC interpretation). |
| Antibody validation and isoforms | HPA lists HPA028888 as IHC Enhanced and CAB009314 as IHC Supported; these are antibody-specific validation ratings (HPA: antibodies). UniProt lists three isoforms, but the supplied record does not map either antibody's epitope to them, so isoform-specific staining cannot be inferred (UniProt P98082: isoforms). |
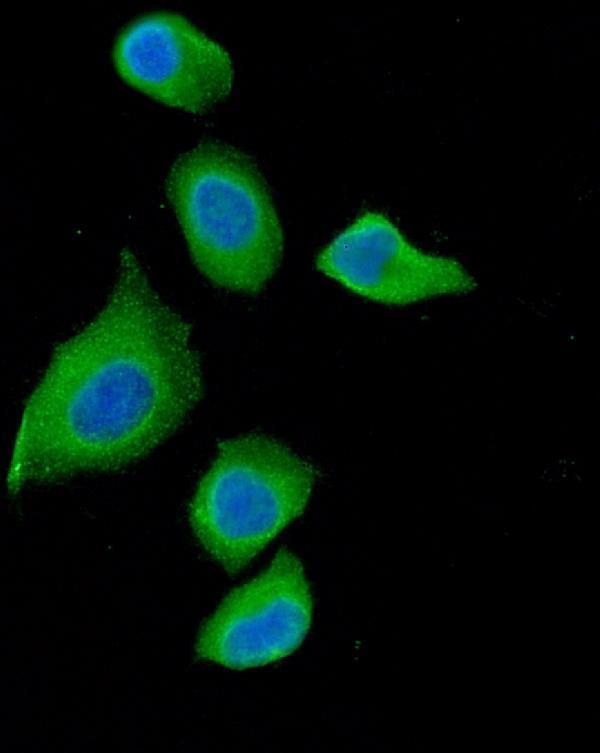
| IF/ICC Q&A: where should fluorescence localize? | Mainly to vesicles and plasma membrane, with an additional nucleolar fibrillar-center location (HPA: subcellular ICC-IF). That cell-imaging result helps assess localization; it does not replace the cytoplasmic tissue IHC reference pattern (HPA: tissue IHC and subcellular ICC-IF). |
| Retrieval and chromogenic detection | These are general IHC workflow variables that can alter visibility or background (standard IHC practice). The supplied sources give no DAB2-specific retrieval condition or fixation sensitivity; do not attribute an unexpected result to either mechanism without assay-specific evidence. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected-positive macrophages or Hofbauer cells are blank (HPA: High in those cells). | Possible tissue-identification or assay failure; the supplied sources do not identify a DAB2-specific failure mechanism. | Confirm the cell population and run an expected-positive section alongside a reagent control; review retrieval, antibody incubation, and detection steps as general IHC checks (standard IHC practice). |
| Signal appears mainly nuclear in tissue IHC. | The distribution conflicts with HPA's cytoplasmic tissue profile, although HPA notes an additional nucleolar location in ICC-IF (HPA: tissue IHC and subcellular ICC-IF). | Check morphology, counterstain, and control sections before scoring. Record a nuclear-only pattern as unresolved rather than equating it with the ICC-IF observation (standard IHC interpretation). |
| Broad brown staining appears in nominally negative cells or across the section. | Cross-reactivity, endogenous peroxidase activity, or reagent background are possible general chromogenic IHC causes (standard IHC practice). | Compare a no-primary control, check peroxidase blocking and washing, and reassess primary-antibody concentration; verify the scored cell type against HPA's cell-level tissue entries (standard IHC practice; HPA: tissue IHC). |
| A reported Not detected cell type shows a discrete positive signal (HPA: tissue IHC). | Cell misclassification or assay-specific signal is possible; an HPA absence call does not establish universal biological absence (HPA: tissue IHC; standard IHC interpretation). | Confirm histology and compare controls, then describe the result as differing from the HPA reference pattern if it persists (HPA: tissue IHC; standard IHC reporting). |
| Cell-specific staining is present but too faint to score confidently. | Staining intensity can vary with general IHC workflow conditions; HPA reports medium consistency between staining and RNA data (standard IHC practice; HPA: reliability). | Compare an expected-positive section processed in the same run, then review retrieval, incubation, detection, and counterstain without assuming a DAB2-specific fixation effect (standard IHC practice). |
| Two antibodies yield different compartments or cell populations. | Their HPA IHC validation ratings differ: HPA028888 is Enhanced and CAB009314 is Supported; the supplied evidence does not explain any particular discrepancy (HPA: antibodies). | Compare each result with the HPA cell-specific pattern and appropriate controls; report the antibody ID and unresolved difference instead of merging discordant signals into one DAB2 score (HPA: tissue IHC; standard IHC reporting). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Lung | Macrophages | High | Protein (IHC) | HPA → |
| Placenta | Hofbauer cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Endocrine cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Basal cells | Not detected | Protein (IHC) | HPA → |
| Duodenum | Endocrine cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Seminal vesicle | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot DAB2 staining in paraffin sections by checking retrieval, cell identity, subcellular pattern, and controls before comparing signal across samples.
The catalog antibody has IHC data from a human melanoma paraffin section and IF/ICC data from HeLa cells (catalog image captions); listed reactivity covers human, mouse, rat and monkey (catalog reactivity).
A01546-3 will render with its IHC figure from a human melanoma paraffin section (A01546-3 IHC image caption). The same SKU lists IF/ICC and has a separate HeLa cell IF image (A01546-3 applications; A01546-3 IF image caption).
Which to pick: Choose A01546-3 for paraffin-section IHC: its own caption shows heat retrieval in EDTA at pH 8.0 and staining at 2 μg/ml; the fixative is unreported (A01546-3 IHC image caption). For IF/ICC, the same SKU has a HeLa cell image, and its listed IF concentration is 5 μg/ml (A01546-3 IF image caption; catalog dilution). For cross-species work, A01546-3 lists human, mouse, rat and monkey reactivity, although its supplied IHC and IF images show human samples only; clonality is unreported (catalog reactivity; A01546-3 image captions; catalog clone field).