DDC / Aromatic-L-amino-acid decarboxylase · IHC design guide

Design Immunohistochemistry for DDC

Plan chromogenic IHC-P for DDC using renal proximal tubules as a positive control (HPA tissue IHC). Assess cytoplasmic staining while accounting for presumed off-target binding (HPA tissue IHC).

Evidence assembled Nov 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DDC (IHC for DDC): expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A01374-2, validated IHC image, and IHC protocol steps
Printable DDC IHC protocol sheet — expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A01374-2, controls and protocol steps. Open the full DDC IHC guide →

DDC Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC)
Staining pattern Strong cytoplasmic staining in renal proximal tubules (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01374-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Presumed off-target staining was observed (HPA tissue IHC)
Regulation High expression in kidney (UniProt)
Isoform / epitope 4 isoforms; check epitope coverage (UniProt)
Section 1

Recommended DDC IHC & IF Protocols

The catalog antibody’s IHC-P protocol and one published DDC IHC protocol are presented here (datasheet: IHC-P; PMC10593861: DDC IHC).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human kidney tissue; fixative not specified (datasheet A01374-2)
FixationImage fixative and duration unreported (datasheet A01374-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01374-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01374-2)
Primary antibodyRabbit anti-DDC, 2-5 μg/ml (datasheet A01374-2)
Primary incubationOvernight at 4 °C (datasheet A01374-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01374-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDDC-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, most abundant in renal tubules. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A01374-2). The published study does not specify retrieval (PMC10593861: methods).
Section 2

What Is the Expected DDC Staining Pattern?

DDC staining should be predominantly cytoplasmic, strongest in kidney proximal tubule cell bodies and visible in intestinal endocrine cells (HPA tissue IHC: high). HPA rates the tissue pattern Enhanced while noting presumed off-target binding, so assess both cell identity and compartment (HPA tissue IHC: Enhanced). UniProt lists no transmembrane segment and provides no subcellular annotation (UniProt P20711 topology and subcellular record).

What am I looking at on my slide?
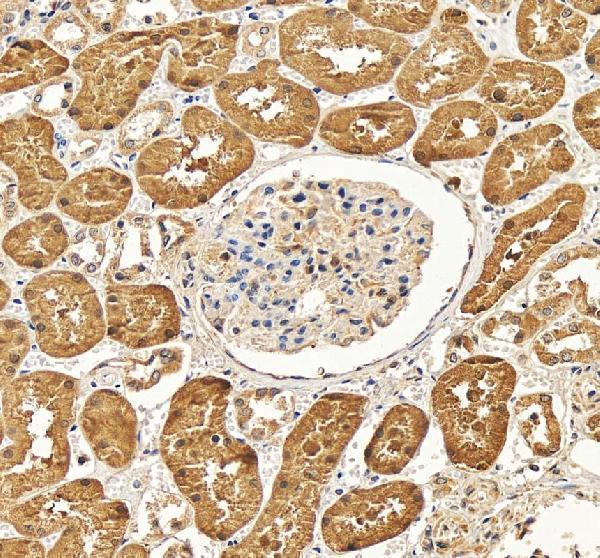
Strong cytoplasmic staining in kidney proximal tubule cell bodies.This is the clearest tissue benchmark: HPA reports high proximal tubule staining and describes renal tubules as the most abundant site (HPA tissue IHC). Score the tubule cells rather than assigning every stained structure in the section to DDC.
Cytoplasmic staining in scattered endocrine cells of appendix or intestinal mucosa.HPA reports high staining in endocrine cells of appendix, colon, duodenum, rectum and small intestine (HPA tissue IHC). A selective cell pattern is more consistent with that evidence than uniform staining of adjacent epithelium.
Predominantly nuclear, sharply membranous or extracellular signal in a kidney section.This differs from HPA's cytoplasmic renal pattern (HPA tissue IHC). UniProt reports no transmembrane segment or signal peptide (UniProt P20711 topology and processing). Check morphology and controls before interpreting it as DDC.
Broad staining of cell types reported as undetected, such as adipocytes or marrow hematopoietic cells.HPA reports DDC as not detected in those specified cells and notes presumed off-target binding in its tissue assessment (HPA tissue IHC). Treat broad staining there as a specificity concern; a single negative cell type cannot prove cross-reactivity.
Little or no staining in kidney proximal tubule cell bodies.This conflicts with HPA's high renal benchmark (HPA tissue IHC). First check that proximal tubules are present and identifiable, then review the antibody and IHC detection controls (general IHC practice).
💡Expected DDC appearanceCall a section positive when kidney proximal tubule cell bodies show strong cytoplasmic staining, with selective intestinal endocrine-cell staining also consistent; widespread nuclear, membrane or unrelated-cell staining warrants review (HPA tissue IHC; UniProt P20711 topology).
How each factor affects the staining
Choice of tissue and cell typeKidney proximal tubules offer a high-signal reference; intestinal endocrine cells are another high-staining population, while adipocytes and marrow hematopoietic cells are reported undetected (HPA tissue IHC). Compare the named cells, not whole-section colour.
Antibody validation and interpretationHPA lists HPA017742 as IHC Enhanced and describes the tissue profile as Enhanced, with medium agreement between staining and RNA and presumed off-target binding disregarded (HPA antibodies; HPA tissue IHC). Validation supports use of the pattern but does not identify every stained cell.
Topology and processingUniProt lists one 1–480 chain, no signal peptide, no propeptide and no transmembrane segment (UniProt P20711 topology and processing). These features give no basis to expect a membrane-rim or secreted-protein pattern; HPA tissue IHC supplies the observed cytoplasmic benchmark.
Isoforms and antibody epitopeUniProt lists four DDC isoforms, but the supplied records do not map the antibody epitope or establish isoform-specific staining (UniProt P20711 isoforms; HPA antibodies). Do not infer which isoform accounts for a stronger or weaker cell signal.
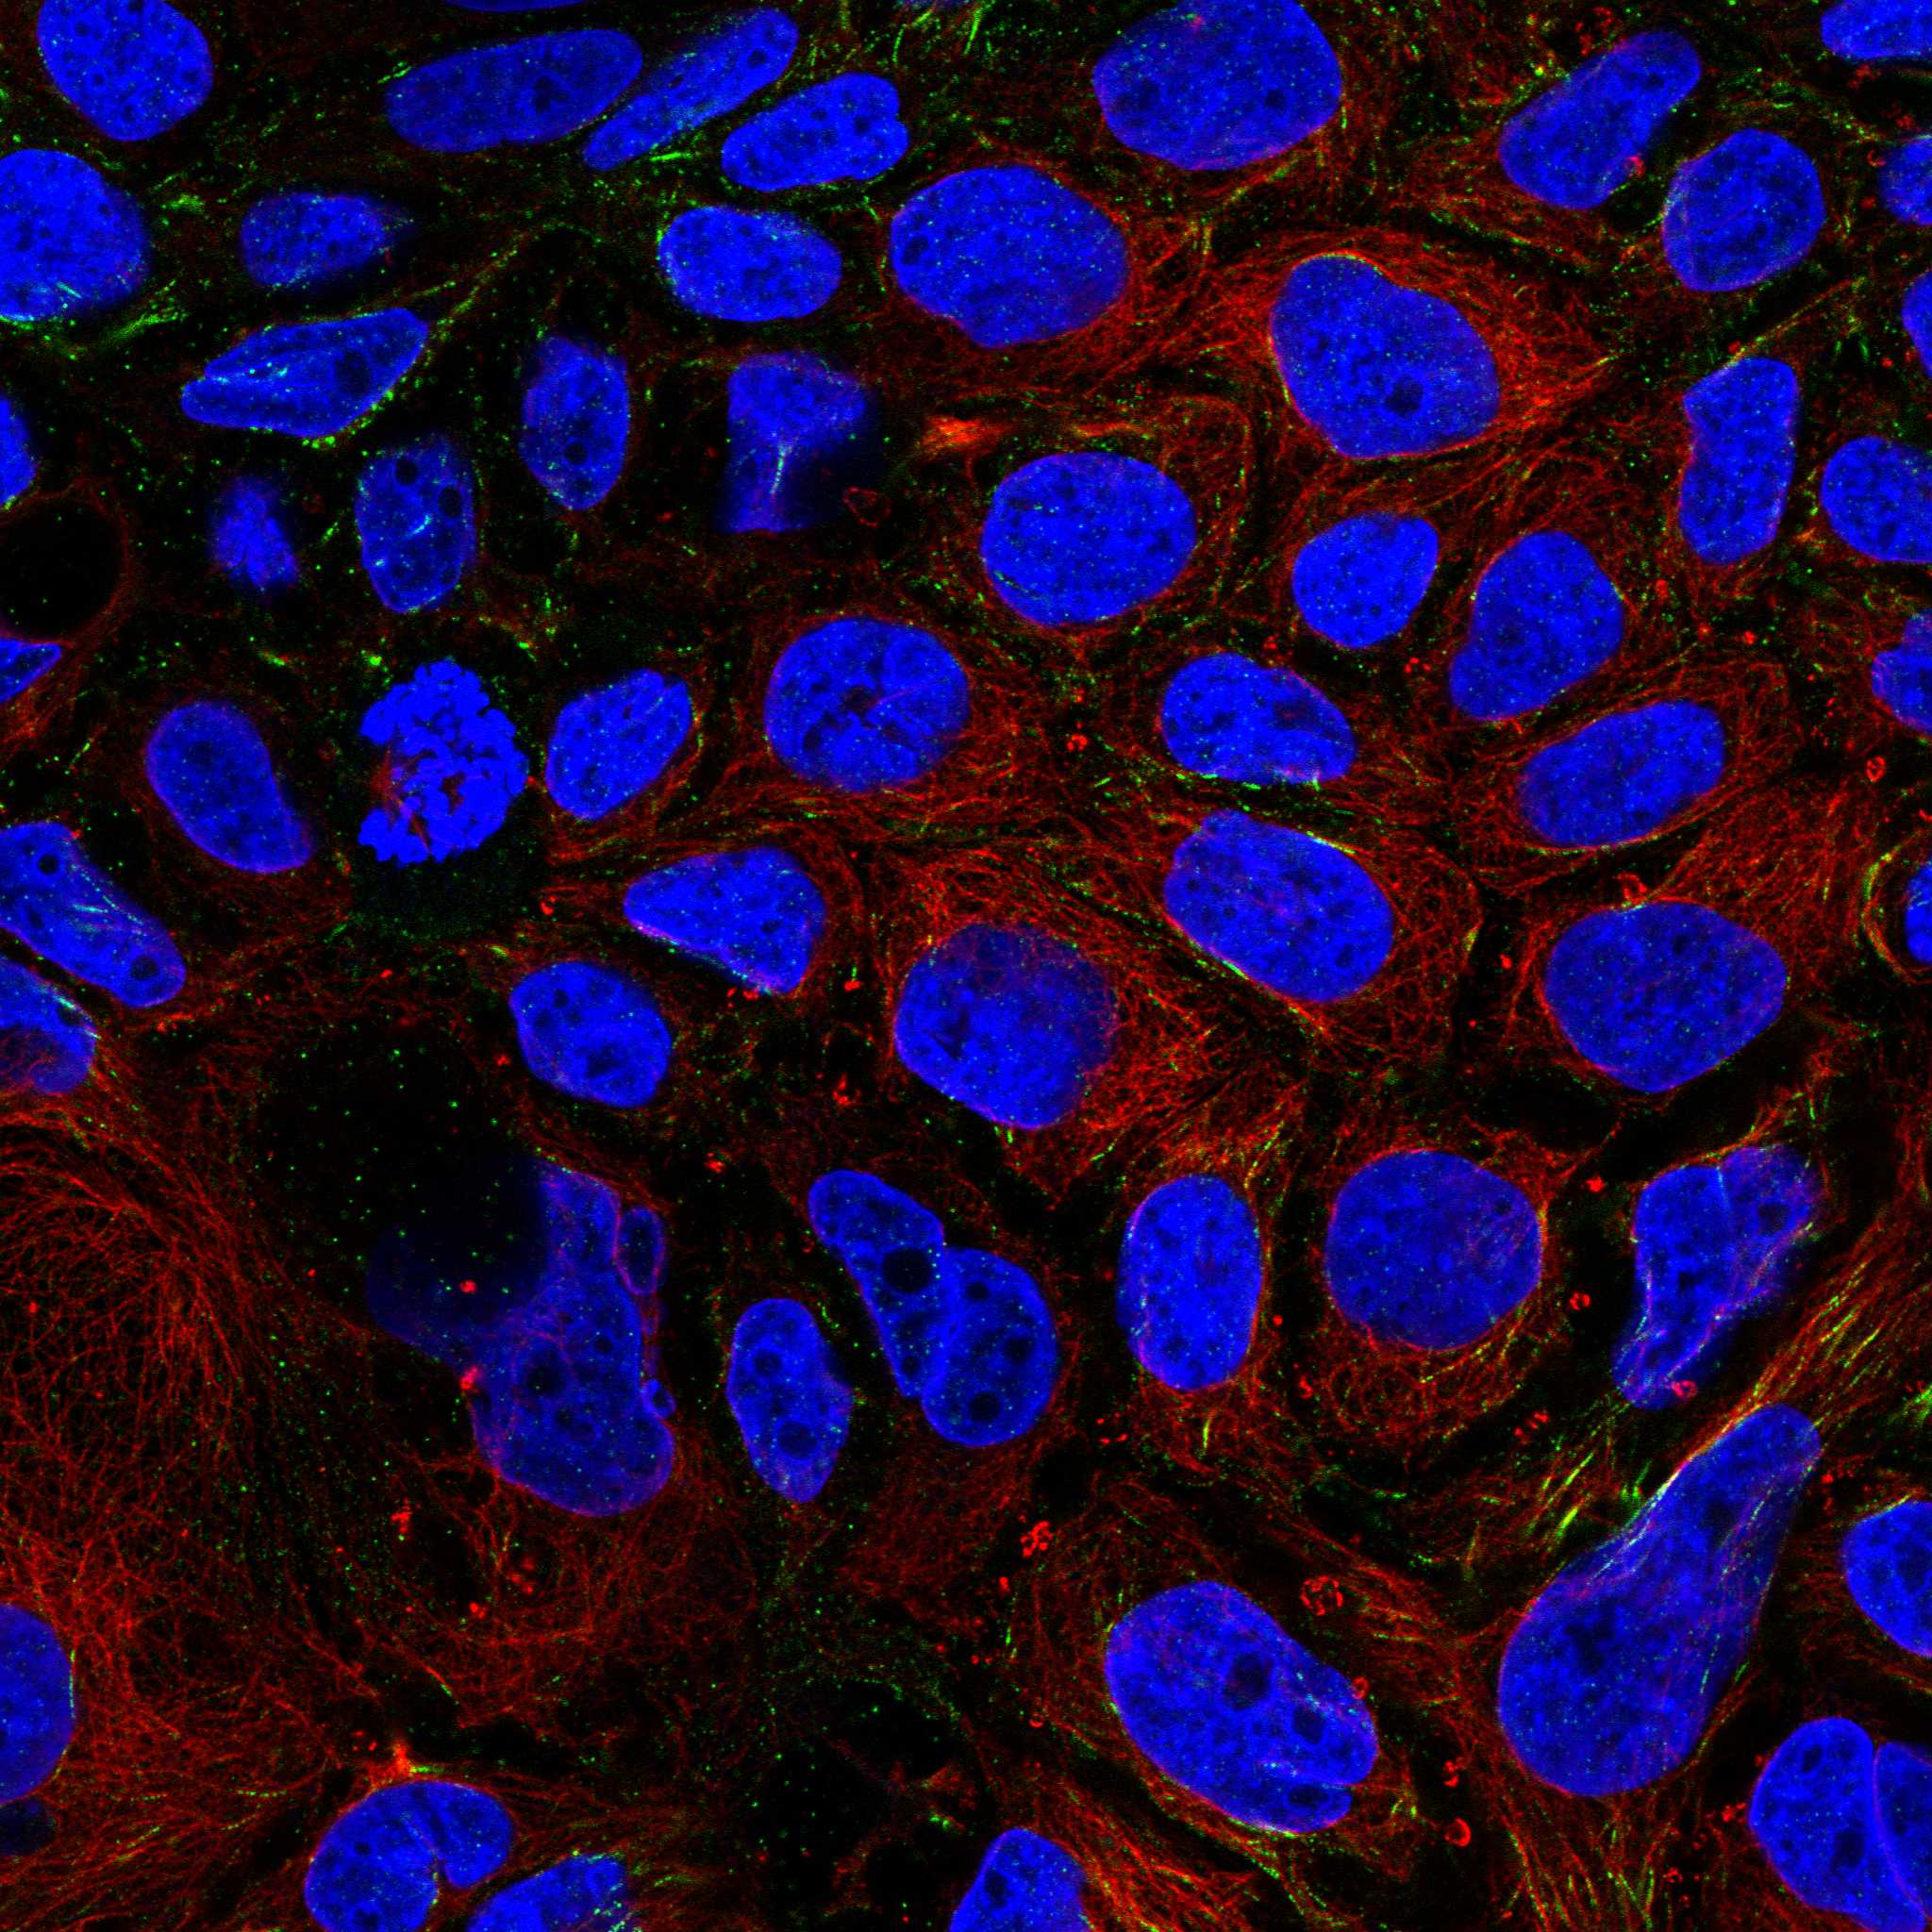
IF/ICC: should its pattern set the IHC-P scoring rule?No. HPA ICC-IF reports approved actin-filament localisation plus a primary-cilium location, whereas HPA tissue IHC describes cytoplasmic staining (HPA subcellular; HPA tissue IHC). Use each assay's own observed pattern; filament or cilium detail is not an IHC-P requirement.
Chromogenic detection chemistryEndogenous peroxidase or pigment can complicate a brown chromogenic readout; a no-primary control and appropriate blocking help distinguish detection background from antibody-dependent signal (general IHC practice). This is a general workflow consideration, not a reported DDC-specific effect.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Kidney positive control lacks proximal tubule signal.The target cell population may be absent from the field, or staining and detection conditions may have failed (HPA tissue IHC: high in proximal tubules; general IHC practice).Confirm proximal tubule morphology, then check the catalog antibody's IHC-P instructions, retrieval conditions and detection controls (general IHC practice). The supplied evidence does not establish DDC-specific retrieval sensitivity.
Diffuse brown haze obscures cell boundaries.Background may arise from detection chemistry, residual endogenous peroxidase or nonspecific antibody binding (general IHC practice); HPA also notes presumed off-target binding in its tissue assessment (HPA tissue IHC).Inspect a no-primary control, review peroxidase blocking and washing, and compare signal with clearly defined renal tubule cells (general IHC practice; HPA tissue IHC: high in proximal tubules).
Most intestinal epithelial cells stain uniformly.That distribution exceeds the endocrine-cell pattern reported for intestinal sites and may indicate nonspecific staining (HPA tissue IHC: high in endocrine cells; general IHC practice).Identify endocrine cells on the section and compare antibody staining with a no-primary control; reassess the result if colour follows broad epithelium instead (HPA tissue IHC; general IHC practice).
Signal appears mainly nuclear or as a membrane rim.The compartment conflicts with HPA's cytoplasmic tissue profile; UniProt supplies no transmembrane segment (HPA tissue IHC; UniProt P20711 topology).Check focus, counterstain and control sections, then score DDC only where staining matches the expected cell and cytoplasmic pattern (general IHC practice; HPA tissue IHC).
Adipocytes or marrow hematopoietic cells show strong staining.HPA reports these particular cells as not detected and acknowledges presumed off-target binding (HPA tissue IHC). The staining alone cannot identify whether antibody binding or detection chemistry caused it.Compare a no-primary control and the kidney proximal tubule benchmark; treat persistent antibody-dependent staining in those cells as a specificity concern (general IHC practice; HPA tissue IHC).
An IF/ICC image looks filamentous while the IHC section looks cytoplasmic.The two HPA records report different assay observations: actin filaments and primary cilium in ICC-IF, cytoplasmic tissue staining in IHC (HPA subcellular; HPA tissue IHC).Interpret the paraffin section against the HPA tissue cell pattern and the IF/ICC image against its own localisation record; do not require visible filaments in chromogenic IHC-P (HPA tissue IHC; HPA subcellular).

Sample controls for DDC IHC & IF

🧪Run kidney first: proximal tubules (cell body) must stain (HPA: High). Use adipose tissue as the negative, where adipocytes are not detected (HPA: Not detected); cells without specific staining on the kidney slide should show counterstain only, with no DAB signal above background.
Positive control tissue: Appendix (Endocrine cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DDC in CACO-2, SH-SY5Y, U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Actin filaments (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and host- and clonality-matched rabbit IgG isotype controls, plus DDC knockout tissue where available or a validated peptide-block control (standard IHC practice; caption: rabbit primary antibody). Block endogenous peroxidase and check kidney sections for residual DAB background (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact A01374-2 kidney caption does not state a fixative (selected tissue-IHC caption). That paraffin-section example used heat-mediated EDTA retrieval at pH 8.0, but does not establish that retrieval is required (selected tissue-IHC caption). The supplied evidence does not establish whether frozen sections or IF are easier; assess kidney background from endogenous peroxidase when interpreting chromogenic staining (standard IHC practice).

HPA tissue IHC evidence for DDC

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Endocrine cells High Protein (IHC) HPA →
Cerebellum Molecular layer - neuropil High Protein (IHC) HPA →
Colon Endocrine cells High Protein (IHC) HPA →
Duodenum Endocrine cells High Protein (IHC) HPA →
Kidney Proximal tubules (cell body) High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced DDC IHC Tips

Troubleshoot DDC staining in paraffin sections by checking retrieval, cell type, compartment, controls, and scoring against the documented kidney example.

Which retrieval conditions should I start with for DDC in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01374-2). The documented kidney image used that retrieval before 10% goat-serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A01374-2). If staining is weak, compare retrieval duration on adjacent sections while holding antibody concentration, detection, and imaging conditions constant (standard IHC practice). Check whether signal appears in renal proximal tubule cell bodies, where staining is reported as high (HPA tissue IHC). Excessive heating can damage morphology, so inspect tissue integrity alongside signal before increasing retrieval further (standard IHC practice).
How should I troubleshoot variable DDC staining between differently fixed sections?
The selected tissue image identifies a paraffin-embedded kidney section but does not state its fixative (datasheet A01374-2). DDC-specific sensitivity to fixation is therefore unknown from the supplied evidence; do not infer a preferred fixative from its expression pattern or protein features. Record each specimen’s fixative, fixation duration, processing history, and section age before comparing staining (standard IHC practice). Process a known positive kidney section alongside each batch, using the documented EDTA pH 8.0 retrieval and 2 μg/ml primary concentration (datasheet A01374-2). Compare morphology, background, and proximal tubule staining before attributing differences to fixation (HPA tissue IHC; standard IHC practice).
Where should convincing DDC staining appear in kidney sections?
Expect predominantly cytoplasmic staining in renal proximal tubule cell bodies; this is the strongest tissue pattern in the supplied atlas profile (HPA tissue IHC). The selected paraffin-section example also detects DDC in human kidney, providing a matched tissue reference for the catalog antibody (datasheet A01374-2). UniProt lists no transmembrane segment or signal peptide for DDC, but does not annotate a subcellular location (UniProt P20711). Its approved actin-filament and additional primary-cilium locations come from cellular imaging and should not be required as resolvable chromogenic patterns (HPA subcellular). Treat isolated nuclear or luminal staining cautiously and compare it with morphology and controls (standard IHC practice).
Could an antibody epitope explain discordant DDC staining across samples?
DDC has four annotated isoforms, so establish which sequence the antibody recognizes before interpreting discordant staining as biological absence (UniProt P20711). The supplied catalog image documents kidney staining but does not map the antibody epitope or demonstrate recognition of each isoform (datasheet A01374-2). Request epitope information or compare with an independently validated antibody against a different region when isoform coverage matters (standard IHC practice). DDC also carries an annotated pyridoxal-phosphate lysine at residue 303; its effect on this antibody’s binding is unknown (UniProt P20711). Keep retrieval and detection conditions matched while comparing antibodies so technical differences do not mimic isoform-specific staining (standard IHC practice).
How can I adapt the DDC question to multiplex immunofluorescence?
Use a marker that identifies the expected cell type, such as proximal tubule cells in kidney, and score DDC signal within those cells (HPA tissue IHC; standard IF practice). Choose fluorophores in channels with low tissue autofluorescence, and inspect single-stain controls for bleed-through before interpreting colocalization (standard IF practice). DDC has no annotated transmembrane segment or signal peptide, while tissue staining is cytoplasmic, so permeabilize cells sufficiently to access an intracellular epitope (UniProt P20711; HPA tissue IHC; standard IF practice). The cellular atlas reports actin-filament and additional primary-cilium localization, which can guide image inspection (HPA subcellular). Optimize IF fixation and permeabilization with IF controls; the paraffin IHC caption supplies no IF fixation evidence (datasheet A01374-2).
What should I change when DDC chromogenic staining has high background?
First separate diffuse reagent background from cell-associated signal by reviewing a no-primary control beside the stained section (standard IHC practice). The documented workflow used 10% goat-serum block, 2 μg/ml rabbit primary overnight at 4°C, and peroxidase-linked detection with DAB (datasheet A01374-2). If background persists, check peroxidase blocking, antibody concentration, wash stringency, and DAB development using adjacent sections (standard IHC practice). Compare proximal tubules with nearby structures because the expected strong kidney signal is in proximal tubule cell bodies (HPA tissue IHC). Interpret staining in damaged edges or necrotic areas cautiously, where nonspecific reagent retention can obscure cellular patterns (standard IHC practice).
How should I quantify DDC staining without confusing tissue composition with expression? ⚠ ANSWER MARKED FOR VERIFICATION
Define the region and cell population before scoring, using proximal tubule cell bodies for the documented strong kidney pattern (HPA tissue IHC). Record the percentage of positive target cells and staining intensity, then calculate an H-score from intensity categories if graded chromogenic staining is reproducible (standard IHC practice). For spatial analysis, report positive-cell density per mm² of viable target tissue rather than total section area (standard IHC practice). Normalize comparisons to the number or area of eligible proximal tubules, and keep retrieval, DAB development, and image thresholds consistent (standard IHC practice). Exclude folds, necrosis, and section edges using predefined morphology rules (standard IHC practice).
How can I distinguish genuine DDC staining from artefact?
A credible kidney result shows cell-associated cytoplasmic staining in proximal tubules, matching the reported high signal in their cell bodies (HPA tissue IHC). DDC lacks an annotated transmembrane segment, so a membrane-only pattern warrants closer scrutiny, although UniProt does not assign a definitive compartment (UniProt P20711). Compare suspect staining with a no-primary control and a known positive kidney section to assess reagent background and assay performance (standard IHC practice; datasheet A01374-2). Edge-only signal, necrotic deposits, or broadly uniform DAB may reflect processing artefact or residual endogenous peroxidase (standard IHC practice). The atlas notes presumed off-target staining, so confirm unexpected cell populations with an independent antibody or orthogonal evidence (HPA tissue IHC).
Boster reagents

Best DDC / Aromatic-L-amino-acid decarboxylase IHC Antibodies

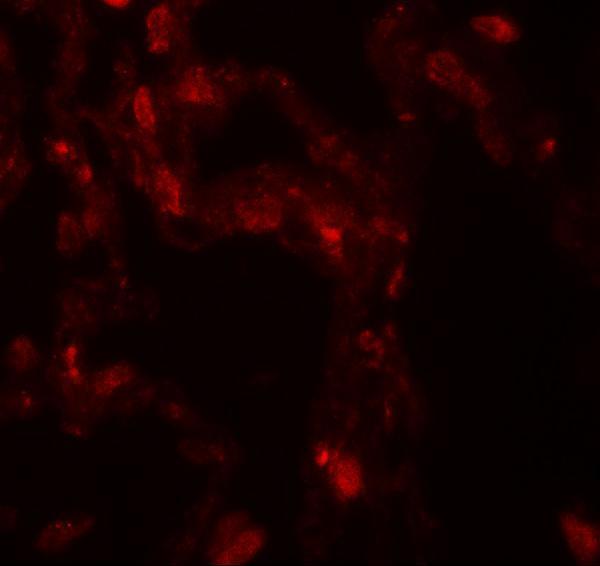
Two anti-DDC antibodies have human IHC images: kidney for A01374-2 and lung for A01374 (catalog IHC captions). A01374 also has a human lung IF image (catalog IF caption).

Real IHC data IHC analysis of DOPA decarboxylase/DDC using anti-DOPA decarboxylase/DDC antibody (A01374-2). DOPA decarboxylase/DDC was detected in a paraffin-embedded section of human kidney tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-DOPA decarboxylase/DDC Antibody (A01374-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-DOPA decarboxylase/DDC Antibody ®
Cat # A01374-2
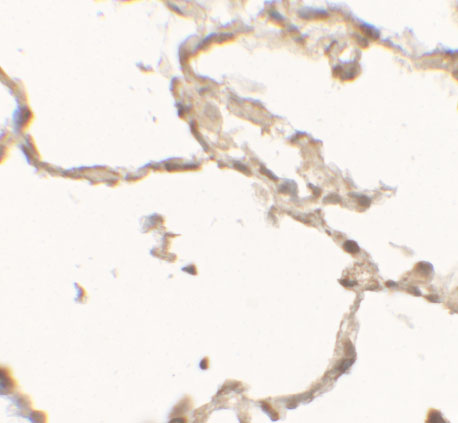
Real IHC data Immunohistochemistry of DDC in human lung tissue with DDC antibody at 2.5 μg/mL.
Anti-DDC Antibody
Cat # A01374

A01374-2 shows IHC staining in a paraffin-embedded human kidney section (A01374-2 IHC caption). A01374 shows IHC staining in human lung tissue and IF staining in human lung tissue (A01374 IHC and IF captions).

Which to pick: For paraffin-section IHC, choose A01374-2: its kidney image documents antigen retrieval and chromogenic detection, with a listed IHC concentration of 2–5 μg/ml (A01374-2 IHC caption; catalog dilution). For IF, choose A01374 based on its human lung IF image; ICC validation is unreported (A01374 IF caption; catalog applications). Both list human, mouse, and rat reactivity, but the supplied IHC and IF images show human tissue only; neither IHC caption reports the fixative (catalog reactivity; A01374-2 and A01374 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P20711 (DDC_HUMAN, Aromatic-L-amino-acid decarboxylase).
  2. Human Protein Atlas. DDC tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. DDC subcellular location (ICC-IF): Mainly localized to the actin filaments. In addition localized to the primary cilium..
  4. Human Protein Atlas. DDC antibody validation summary (1 antibodies).
  5. The role of osteopontin and tumor necrosis factor alpha receptor-1 in xenobiotic-induced cholangitis and biliary fibrosis in mice. Laboratory investigation; a journal of technical methods and pathology 2010 — PMC4285781.
  6. RNA modification regulator DDC in endometrial cancer affects the tumor microenvironment and patient prognosis. Scientific reports 2023 — PMC10593861.
  7. L-DOPA in the hu man ovarian follicular fluid acts as an antioxidant factor on granulosa cells. Journal of ovarian research 2016 — PMC5043631.
  8. Analysis of Expression and Functional Activity of Aromatic L-Amino Acid Decarboxylase (DDC) and Serotonin Transporter (SERT) as Potential Sources of Serotonin in Mouse Ovary. International journal of molecular sciences 2019 — PMC6627913.
  9. PubMed PMID:2590185 — UniProt-cited evidence.
  10. PubMed PMID:1612608 — UniProt-cited evidence.
  11. PubMed PMID:1540578 — UniProt-cited evidence.