DDIT4 / DNA damage-inducible transcript 4 protein · IHC design guide

Design Immunohistochemistry for DDIT4

Plan DDIT4 IHC in paraffin sections using reported cytoplasmic tissue staining as a reference (HPA tissue IHC). Compare matched sections under consistent fixation and score staining by cell type and intensity (standard IHC practice).

Evidence assembled Nov 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DDIT4 (IHC for DDIT4): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A02019, validated IHC image, and IHC protocol steps
Printable DDIT4 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A02019, controls and protocol steps. Open the full DDIT4 IHC guide →

DDIT4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Glandular-cell cytoplasmic staining; texture unreported (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show only medium consistency (HPA tissue IHC)
Regulation Responds to hypoxia and DNA damage (UniProt)
Isoform / epitope No annotated isoforms or processing changes (UniProt)
Section 1

Recommended DDIT4 IHC & IF Protocols

The catalog antibody’s IHC-P protocol accompanies published DDIT4 methods for lung adenocarcinoma (PMC8489140) and gastric cancer tissue microarrays (PMC11929655).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A02019); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-DDIT4, 5 μg/mL (datasheet A02019)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDDIT4-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval); the gastric study used an autoclave for 10 min (PMC11929655).
Section 2

What Is the Expected DDIT4 Staining Pattern?

DDIT4 should show predominantly cytoplasmic staining in paraffin sections (HPA: general cytoplasmic expression), consistent with its cytosolic and mitochondrial annotations (UniProt Q9NX09). Expect strong staining in selected glandular and hematopoietic cells, and colonic endothelial cells (HPA: High). Interpret intensity by cell type: HPA rates the tissue IHC evidence Approved, with medium consistency between antibody staining and RNA expression (HPA: reliability summary). DDIT4 has no transmembrane segment (UniProt Q9NX09 topology).

What am I looking at on my slide?
Cytoplasmic staining is prominent in adrenal or breast glandular cells, or bone marrow hematopoietic cells (HPA: High).This matches reported high-staining cell types and the general cytoplasmic profile (HPA: tissue IHC). Compare cells within the same section; high staining is not expected in every cell (HPA: tissue IHC).
Staining is predominantly nuclear or outlines cell membranes, with little cytoplasmic signal.That distribution conflicts with HPA's cytoplasmic profile and UniProt's cytosolic and mitochondrial annotations (HPA: tissue IHC; UniProt Q9NX09). Review staining specificity and detection conditions using general IHC controls.
Adipocytes stain strongly, while an adjacent expected positive cell population is weak or unstained.HPA reports DDIT4 as not detected in adipocytes (HPA: adipose tissue). The reversal raises concern for nonspecific antibody binding or endogenous detection activity; assess appropriate controls before assigning a DDIT4-positive result.
Most structures show a uniform haze that obscures cell boundaries.Diffuse, non-cell-resolved color does not establish the reported cytoplasmic distribution (HPA: tissue IHC). In general IHC practice, background can arise from detection reagents, insufficient blocking or overly strong staining.
A control section from a reported high-staining tissue has no visible cytoplasmic signal.Check that the section contains the relevant cell type: HPA's High call is cell-specific (HPA: tissue IHC). If it does, review the antibody and general IHC workflow before interpreting the test section as negative.
💡Expected DDIT4 appearanceCall a result positive when the relevant glandular, hematopoietic or endothelial cells show clear cytoplasmic staining at the reported High level (HPA: tissue IHC); predominant nuclear or membranous staining conflicts with the expected distribution (HPA: cytoplasmic profile; UniProt Q9NX09).
How each factor affects the staining
Which cells provide a useful positive comparison?HPA reports High staining in adrenal, appendix, breast, cervix, duodenal and endometrial glandular cells; bone marrow hematopoietic cells; and colonic endothelial cells (HPA: tissue IHC). Select a section containing the specified cells.
How should a weak or absent cell population be judged?Adipocytes are reported not detected, whereas liver cholangiocytes are listed as low (HPA: tissue IHC). These are cell-specific observations, not guarantees for every section; HPA rates overall staining/RNA consistency as medium (HPA: reliability summary).
Does DDIT4 topology predict membrane staining?DDIT4 has no transmembrane segment or signal peptide, and its annotated chain spans residues 1–232 (UniProt Q9NX09). These annotations support checking a membrane-only pattern carefully; they do not establish antigen retrieval or fixation sensitivity.
How strong is the antibody validation evidence?Two listed antibodies have IHC status Approved (HPA: HPA034507, HPA034508). Treat this as the stated validation level; the supplied antibody summary does not label either IHC result Enhanced (HPA: antibody validation).
What should IF/ICC show?HPA reports supported cytosolic localization and ICC support for HPA034508 (HPA: subcellular atlas; antibody validation). Use that localization as a cross-check of compartment, while consulting the separate IF/ICC guide for experimental design.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in the selected positive control cells.The sampled cells may differ from HPA's specified High population (HPA: tissue IHC), or a general IHC workflow step may have failed.Confirm cell identity and control quality first. Then check primary-antibody application, detection reagents and counterstain; optimize general IHC conditions with the control section before scoring unknown sections.
Nuclear staining dominates the section.Predominantly nuclear signal conflicts with cytoplasmic tissue staining and supported cytosolic IF localization (HPA: tissue IHC; subcellular atlas). Its cause cannot be assigned from localization data alone.Inspect a reported high-staining cell population and an appropriate negative reagent control. Reassess antibody specificity and detection background before counting nuclear color as DDIT4.
Adipocytes show stronger staining than the expected positive cells.That contrast reverses the supplied adipocyte observation, which is not detected (HPA: adipose tissue), and may reflect nonspecific or endogenous detection signal.Check reagent controls and examine whether color follows the expected cytoplasmic, cell-specific distribution (HPA: tissue IHC). Do not use adipocyte staining alone to validate a positive call.
The entire section has diffuse brown background.Diffuse color prevents assessment of HPA's general cytoplasmic pattern (HPA: tissue IHC). General IHC causes include inadequate blocking, endogenous detection activity or excessive reagent concentration.Use general IHC controls to locate the background source; adjust blocking, washes, antibody concentration or detection conditions as indicated. Re-evaluate the section for cell-resolved cytoplasmic staining.
Only membranes appear sharply stained.A membrane-only pattern disagrees with HPA's cytoplasmic profile and DDIT4's lack of a transmembrane segment (HPA: tissue IHC; UniProt Q9NX09 topology).Compare the same cell type with a reported positive tissue and review reagent controls. Resolve the compartment discrepancy before treating the membrane outline as target staining.
Staining varies across specimens of the same tissue.HPA's levels describe particular cell types, and antibody staining has medium consistency with RNA data (HPA: tissue IHC; reliability summary). The supplied sources do not identify a DDIT4-specific fixation effect.Score comparable cell populations and include a positive control in each run. Review general section preparation and detection consistency; avoid assigning a target-specific fixation cause without supporting evidence.

Sample controls for DDIT4 IHC & IF

🧪Run breast first and assess its glandular cells, which show high DDIT4 staining (HPA: High in breast glandular cells). Use adipose tissue as the negative tissue (HPA: Not detected in adipose-tissue adipocytes); if adipocytes are present on the breast slide, use them as an internal background comparator, without assuming that every other cell is negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DDIT4 in A-431, U2OS, hTCEpi, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an irrelevant primary matched to the antibody’s host species and immunoglobulin class; and, where available, a DDIT4-knockout biological negative. For chromogenic IHC, quench endogenous peroxidase and inspect adipocyte-rich breast sections for background staining before scoring glandular cells.
⚠️Feasibility: No target-specific fixation window or retrieval dependency is reported in the supplied evidence; optimize retrieval empirically. The selected A02019 mouse-kidney IHC caption reports 5 µg/mL but does not report a fixative (selected-SKU tissue-IHC caption: fixative not stated). The evidence does not establish whether frozen sections or IF are easier; for breast IHC, distinguish glandular-cell staining from signal along adipocyte edges (HPA: High in breast glandular cells; HPA: Not detected in adipose-tissue adipocytes).

HPA tissue IHC evidence for DDIT4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced DDIT4 IHC Tips

Troubleshoot DDIT4 staining by checking cytoplasmic localisation, tissue controls and processing conditions before interpreting chromogenic signal (HPA tissue IHC; HPA subcellular).

How should I adjust retrieval when DDIT4 staining is weak or uneven?
Begin with citrate pH 6.0 heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval setting). Compare sections processed in the same run so that heating, cooling and staining differences do not masquerade as biological variation (standard IHC practice). If staining remains weak, check tissue preservation and antibody concentration before testing another retrieval buffer on matched sections (standard IHC practice). Score the resulting cytoplasmic signal alongside tissue morphology, because the supported subcellular location is cytosol and harsh retrieval can damage sections (HPA subcellular; standard IHC practice).
Can fixation explain variable DDIT4 staining between paraffin sections?
Target-specific fixation sensitivity is unknown from the supplied evidence; the mouse kidney image caption reports 5 µg/mL antibody but does not state its fixative (A02019 caption). Record the fixative and fixation duration for each specimen, then compare sections with similar processing histories and morphology (standard IHC practice). Keep the citrate pH 6.0, 20 min retrieval setting constant while evaluating fixation as a possible source of variation (page retrieval setting; standard IHC practice). Do not infer a DDIT4-specific fixation effect from its localisation, phosphorylation sites or tissue staining pattern (UniProt Q9NX09; HPA tissue IHC).
What staining pattern should I expect, and how should I assess mitochondrial-looking signal?
Expect predominantly cytoplasmic staining in interpretable paraffin sections: tissue IHC describes general cytoplasmic expression, while cell imaging supports cytosol (HPA tissue IHC; HPA subcellular). UniProt also lists mitochondrion, so punctate staining warrants comparison with the surrounding cytoplasmic signal rather than automatic rejection (UniProt Q9NX09 subcellular). DDIT4 has no annotated transmembrane segment, making a crisp cell-border-only pattern a reason to investigate antibody specificity or detection artefact (UniProt Q9NX09 topology; standard IHC practice). Compare the same cell types across sections retrieved in citrate pH 6.0 for 20 min, and check whether unusual signal tracks damaged tissue (page retrieval setting; standard IHC practice).
Could an isoform or modified epitope explain discordant DDIT4 IHC results?
The supplied record annotates 0 isoforms and one 1–232 chain, so an isoform-specific explanation lacks support here (UniProt Q9NX09 processing and isoforms). It does list phosphorylated residues at positions 19, 23, 25 and 121, but the antibody epitope is unspecified (UniProt Q9NX09 modified residues; supplied antibody evidence). Consequently, do not attribute staining changes to phosphorylation without an epitope map or independent validation (standard IHC practice). Compare matched sections at the same citrate pH 6.0 retrieval setting and inspect cytoplasmic localisation before interpreting differences as biological (page retrieval setting; HPA tissue IHC; standard IHC practice).
How can IF help examine DDIT4 localisation alongside a cell-type marker?
For a separate IF experiment, pair DDIT4 with a marker identifying the cell type being assessed; glandular cells are one supported tissue-IHC context (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and consider a far-red channel when tissue autofluorescence obscures shorter wavelengths, using single-stain controls to assess bleed-through (standard IF practice). Because supported DDIT4 signal is cytosolic and no transmembrane segment is annotated, use controlled permeabilisation to access an intracellular epitope; its precise antibody epitope is unspecified (HPA subcellular; UniProt Q9NX09 topology; supplied antibody evidence). Evaluate IF localisation separately from chromogenic IHC scoring, since the supplied 5 µg/mL tissue caption documents IHC rather than IF (A02019 caption).
How do I distinguish diffuse DDIT4 staining from chromogenic background?
Include a section processed without primary antibody to reveal detection-system background, and inspect pigment or precipitate before scoring DAB (standard IHC practice). A peroxidase block followed by thorough washing is a general chromogenic IHC step, particularly when endogenous enzyme activity could contribute colour (standard IHC practice). Check whether staining follows cell cytoplasm rather than section edges, folds or damaged regions; tissue IHC describes general cytoplasmic DDIT4 expression (HPA tissue IHC; standard IHC practice). Compare the candidate signal with a matched control section under the same citrate pH 6.0, 20 min retrieval and detection conditions (page retrieval setting; standard IHC practice).
What should I score when comparing DDIT4 across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score cytoplasmic staining within a defined cell population, recording both the percentage of positive cells and intensity so an H-score can range from 0–300 (HPA tissue IHC; standard IHC scoring practice). Alternatively, count positive cells per mm² when tissue architecture makes cell counting reliable (standard IHC scoring practice). Normalise to the number of evaluable cells or intact tissue area in the same compartment, excluding folds, edges and necrotic regions (standard IHC practice). Apply one staining threshold and the same citrate pH 6.0, 20 min retrieval conditions across comparison sections, then report the scored cell population (page retrieval setting; standard IHC practice).
When is a DDIT4-positive result convincing rather than artefactual?
A convincing result shows reproducible cytoplasmic staining in intact cells, consistent with general tissue IHC and supported cytosolic localisation (HPA tissue IHC; HPA subcellular; standard IHC practice). High staining is reported in several glandular cell populations, while adipocytes are reported as not detected; use those observations as context rather than absolute controls (HPA tissue IHC). Reassess signal limited to cell borders, section edges or necrotic areas, and investigate colour that persists without primary antibody as possible endogenous enzyme or detection background (UniProt Q9NX09 topology; standard IHC practice). Interpret modest differences cautiously because the tissue-IHC reliability is approved with medium consistency between staining and RNA expression (HPA tissue IHC).
Boster reagents

Best DDIT4 / DNA damage-inducible transcript 4 protein IHC Antibodies

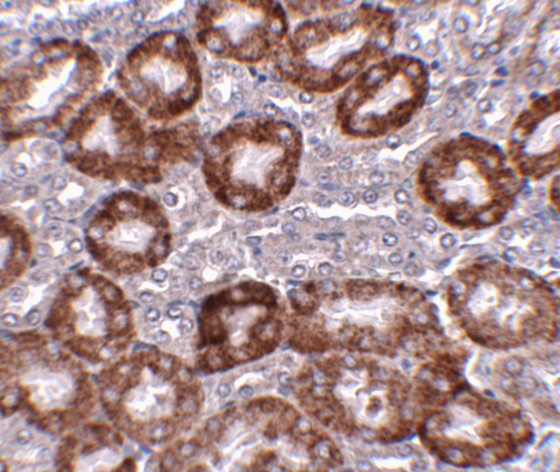
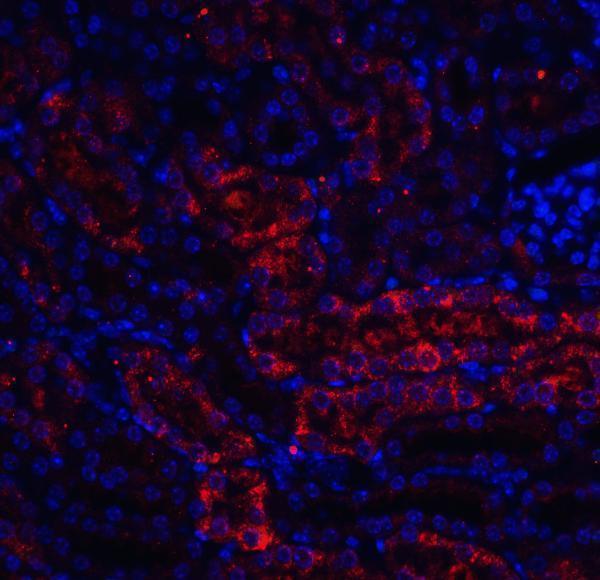
A02019 has mouse kidney IHC and IF images (catalog image captions) and lists Human, Mouse, and Rat reactivity (catalog). The IHC application is IHC-P (catalog).

Real IHC data Immunohistochemistry of RTP801 in mouse kidney tissue with RTP801 antibody at 5 μg/mL.
Anti-RTP801 DDIT4 Antibody
Cat # A02019

A02019 has a mouse kidney IHC image at 5 μg/mL (IHC image caption) and lists IHC-P (catalog). A02019 also has a mouse kidney IF image at 20 μg/mL (IF image caption) and lists Human, Mouse, and Rat reactivity (catalog).

Which to pick: For paraffin-section tissue IHC, choose A02019 because it lists IHC-P (catalog); its IHC image shows mouse kidney (IHC image caption), and the fixative is unreported (IHC image caption). For IF, choose A02019 based on its mouse kidney IF image (IF image caption); ICC validation is unreported (catalog). For work across species, A02019 lists Human, Mouse, and Rat reactivity (catalog), while the supplied IHC and IF images show mouse tissue (image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NX09 (DDIT4_HUMAN, DNA damage-inducible transcript 4 protein).
  2. Human Protein Atlas. DDIT4 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. DDIT4 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. DDIT4 antibody validation summary (2 antibodies).
  5. DDIT4 overexpression associates with poor prognosis in lung adenocarcinoma. Journal of Cancer 2021 — PMC8489140.
  6. DDIT4 promotes gastric cancer proliferation and tumorigenesis through the p53 and MAPK pathways. Cancer communications (London, England) 2018 — PMC6034313.
  7. Pan-cancer analysis of DDIT4 identifying its prognostic value and function in acute myeloid leukemia. Journal of cancer research and clinical oncology 2024 — PMC10954950.
  8. Lower cytoplasmic expression of DDIT4 is associated with poor prognosis in gastric cancer patients. Discover oncology 2025 — PMC11929655.
  9. PubMed PMID:12453409 — UniProt-cited evidence.
  10. PubMed PMID:11884613 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.