DHCR24 / Delta(24)-sterol reductase · IHC design guide

Design Immunohistochemistry for DHCR24

Plan chromogenic IHC for DHCR24 in paraffin sections using the catalog antibody’s documented conditions (datasheet A02125-1). Assess cytoplasmic staining in adrenal glandular cells, testis Leydig cells and hepatocytes, and interpret it alongside the HPA’s medium staining–RNA consistency (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DHCR24 (IHC for DHCR24): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER and Golgi membrane localization (UniProt), antibody A02125-1, validated IHC image, and IHC protocol steps
Printable DHCR24 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER and Golgi membrane localization (UniProt), antibody A02125-1, controls and protocol steps. Open the full DHCR24 IHC guide →

DHCR24 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER and Golgi membrane localization (UniProt)
Staining pattern Cytoplasmic signal in adrenal glandular cells, Leydig cells and hepatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02125-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA expression; verify controls (HPA tissue IHC)
Regulation Expression varies by tissue, with adrenal enrichment (UniProt)
Isoform / epitope Two isoforms; map the epitope to the lumenal or cytoplasmic region (UniProt)
Section 1

Recommended DHCR24 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with two published DHCR24 methods using paraffin tissue sections (PMC5256103; PMC10225231).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A02125-1)
FixationImage fixative and duration unreported (datasheet A02125-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02125-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02125-1)
Primary antibodyRabbit anti-DHCR24, 1:50 recommended; image 1:100 (datasheet A02125-1)
Primary incubationOvernight at 4 °C (datasheet A02125-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02125-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDHCR24-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in a subset of tissues including liver, adrenal gland and testis. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: EDTA pH 8.0 HIER); the published excerpts do not specify retrieval conditions.
Section 2

What Is the Expected DHCR24 Staining Pattern?

DHCR24 should show cytoplasmic staining, consistent with its ER and Golgi membrane localisation and single membrane-spanning segment (HPA tissue IHC; UniProt Q15392 topology). The clearest IHC examples are adrenal glandular cells and testicular Leydig cells, both scored High; hepatocytes and cortical neurons are scored Medium (HPA tissue IHC). HPA rates the tissue profile Enhanced, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in adrenal glandular cells or testicular Leydig cells.This matches the High cell-specific staining reported in both tissues (HPA tissue IHC). Judge the positive cells against neighbouring cells and the section's background; High is an HPA category, not a required chromogen intensity for every preparation (HPA tissue IHC; general IHC practice).
Cytoplasmic staining in hepatocytes, cortical neurons, distal tubules or sebaceous glands.Each cell population is scored Medium in its respective tissue (HPA tissue IHC). A weaker result than the High adrenal or testis examples can therefore still fit the reported pattern; compare like-for-like cells and staining runs before treating intensity differences as biological (HPA tissue IHC; general IHC practice).
Predominantly nuclear signal, with little convincing cytoplasmic signal.A nuclear-dominant pattern conflicts with the reported cytoplasmic IHC profile and ER/Golgi membrane localisation (HPA tissue IHC; UniProt Q15392). Treat it as suspect and review morphology, counterstain and controls; compartment mismatch alone does not identify the source of the artefact (general IHC practice).
Strong staining in cells reported as undetected, such as adipocytes or bone-marrow hematopoietic cells.Those cell populations are scored Not detected (HPA tissue IHC). Consider antibody cross-reactivity or endogenous detection activity, especially if the signal also appears in a no-primary control; biological variation and specimen differences remain possible (general IHC practice).
Diffuse colour across tissue, or no signal in an adrenal glandular-cell positive control.Diffuse staining without cellular definition limits interpretation (general IHC practice). Absent adrenal signal disagrees with the High HPA example but cannot by itself prove DHCR24 absence; first check run controls, tissue preservation and the validated IHC workflow (HPA tissue IHC; general IHC practice).
💡Expected DHCR24 appearanceCall a result convincing when cytoplasmic staining is cell-defined in High-scored adrenal glandular cells or Leydig cells, with Medium-scored populations potentially less intense; nuclear-dominant signal or staining throughout reported negative cells is suspect (HPA tissue IHC; UniProt Q15392; general IHC practice).
How each factor affects the staining
Membrane topology and epitope locationDHCR24 has a signal segment at residues 1–22, one transmembrane segment at 32–52, and a cytoplasmic region at 53–516 (UniProt Q15392 topology). Antibody epitope location is not supplied, so topology cannot establish a target-specific retrieval or permeabilisation requirement.
Tissue and cell selectionAdrenal glandular cells and Leydig cells provide High-scored examples; hepatocytes, cortical neurons, distal tubules and sebaceous glands are Medium (HPA tissue IHC). Adipocytes and bone-marrow hematopoietic cells are reported Not detected and can help assess unexpected staining (HPA tissue IHC).
Antibody validation and interpretation limitThree listed rabbit polyclonal antibodies have IHC Enhanced status (HPA antibodies). The tissue profile also has medium staining/RNA consistency and awaits external verification (HPA tissue IHC); these ratings support comparison with the reported pattern but do not verify every specimen or antibody.
IF/ICC: what localisation should be expected?The HPA subcellular summary says Membrane, but provides no main location or cell-line ICC-IF images (HPA subcellular). ER/Golgi localisation is reported by UniProt Q15392. Those records offer a localisation expectation, not a demonstrated IF/ICC image pattern or protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No cytoplasmic staining in adrenal glandular cells.The expected High-scored population is absent from the readout (HPA tissue IHC); the slide alone cannot distinguish assay failure from specimen variation.Confirm that glandular cells are present and review the run's positive and no-primary controls, detection steps and the antibody's validated IHC conditions (general IHC practice).
Only nuclei appear positive.Nuclear-dominant staining conflicts with cytoplasmic IHC and ER/Golgi membrane localisation (HPA tissue IHC; UniProt Q15392).Check whether counterstain or precipitate is being read as target signal; compare the no-primary control and repeat interpretation in cells with intact morphology (general IHC practice).
Adipocytes or bone-marrow hematopoietic cells stain strongly.These populations are scored Not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible (general IHC practice).Compare a no-primary control and a reported positive cell population in the same run; investigate detection background before calling the unexpected cells DHCR24-positive (general IHC practice).
Chromogen covers broad tissue areas without distinct positive cells.Diffuse deposition can reflect nonspecific binding or detection background (general IHC practice); it obscures the cell-specific HPA pattern (HPA tissue IHC).Inspect no-primary and reagent controls, then review blocking, washes and detection timing against the established IHC workflow (general IHC practice).
Medium-scored cells look weak beside adrenal or Leydig cells.HPA assigns different categories to these cell populations: Medium versus High (HPA tissue IHC).Assess localisation and background before changing conditions; compare equivalent cell types across specimens stained in the same run (HPA tissue IHC; general IHC practice).
An IF/ICC image is being used to judge the IHC slide.HPA supplies a Membrane summary but no ICC-IF image-bearing cell lines or main subcellular location (HPA subcellular).Judge the paraffin IHC result against HPA tissue cell patterns and cytoplasmic localisation; treat any IF/ICC comparison as provisional (HPA tissue IHC; HPA subcellular).

Sample controls for DHCR24 IHC & IF

🧪Run adrenal gland first: glandular cells should stain strongly (HPA: High in adrenal gland glandular cells). Use adipose tissue as the negative, where adipocytes are not detected (HPA: Not detected in adipose tissue adipocytes); on the adrenal slide, assess non-glandular stromal cells for minimal staining as an internal background check (standard IHC practice).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for DHCR24; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only), a rabbit isotype-matched control appropriate to the primary antibody’s clonality, and a DHCR24-knockout section if available or a peptide-block control if the immunizing peptide is available (standard IHC practice). Quench endogenous peroxidase and inspect adrenal sections for intrinsic pigment before interpreting DAB staining (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected A02125-1 tissue-IHC caption does not state the fixative (selected-SKU caption). Heat retrieval in EDTA at pH 8.0 preceded staining of a paraffin-embedded human liver cancer section at 1:100; this demonstrates one workable condition, not a general retrieval dependency (selected-SKU caption). The supplied evidence does not establish that frozen sections or IF are easier; adrenal pigment may complicate chromogenic interpretation (HPA: no ICC-IF image cell lines; standard chromogenic IHC practice).

HPA tissue IHC evidence for DHCR24

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Testis Leydig cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Kidney Distal tubules Medium Protein (IHC) HPA →
Liver Hepatocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced DHCR24 IHC Tips

Troubleshoot DHCR24 staining in paraffin section IHC by checking retrieval, compartment, cell type and controls before comparing staining scores.

How should I retrieve DHCR24 when staining paraffin sections?
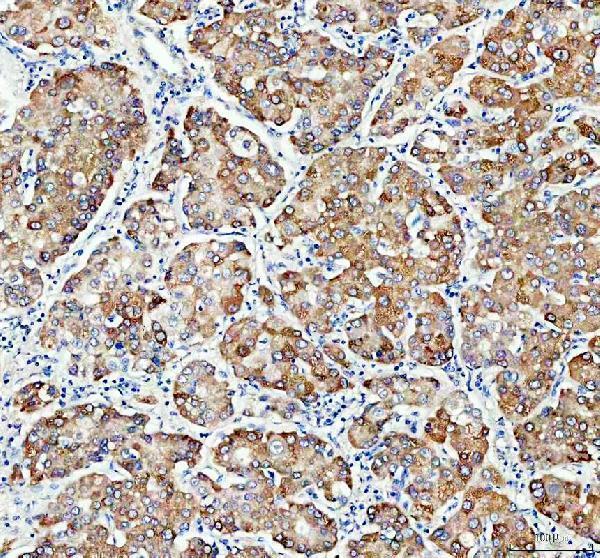
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin-section DHCR24 IHC (datasheet A02125-1). The selected tissue image used this retrieval before an overnight incubation at 4°C with the catalog antibody at 1:100 (datasheet A02125-1); use that image as a processing reference, while recognizing that its fixative was not reported (datasheet A02125-1). If staining is weak, compare retrieval heating and cooling conditions on matched sections while holding antibody concentration and detection constant (standard IHC practice). Include a known positive cell population in each comparison, such as liver hepatocytes with medium reported staining (HPA: liver hepatocytes, Medium), and check whether stronger signal also raises background (standard IHC practice).
Could fixation explain weak or uneven DHCR24 staining?
The selected paraffin-section caption does not state a fixative, so target-specific DHCR24 sensitivity to fixation is unknown (datasheet A02125-1). Record the actual fixative and fixation interval for each specimen, and compare sections with similar processing before attributing an intensity difference to biology (standard IHC practice). On a representative section, first check morphology, retrieval consistency and whether hepatocytes retain an interpretable cytoplasmic signal (standard IHC practice; HPA: liver hepatocytes, Medium). If processing varies across samples, run them in balanced staining batches with the same pH 8.0 EDTA retrieval and 1:100 primary dilution used in the selected image (datasheet A02125-1; standard IHC practice).
Where should a convincing DHCR24 signal appear in tissue?
Expect a cytoplasmic staining pattern in relevant cells, consistent with reported tissue IHC and DHCR24 localisation to endoplasmic reticulum and Golgi membranes (HPA: cytoplasmic expression; UniProt Q15392: subcellular location). DHCR24 has a transmembrane segment at residues 32–52, with residues 53–516 on the cytoplasmic side (UniProt Q15392: topology). Compare the pattern within hepatocytes, which show medium reported staining, and adrenal glandular cells, which show high reported staining (HPA: liver hepatocytes, Medium; HPA: adrenal glandular cells, High). Treat a predominantly nuclear or extracellular pattern as a specificity question and inspect morphology, secondary-only staining and adjacent cells before scoring it as DHCR24 (UniProt Q15392: subcellular location; standard IHC practice).
How can an unknown epitope complicate DHCR24 IHC?
DHCR24 has 2 listed isoforms, but the supplied caption does not identify the catalog antibody’s epitope or establish which isoforms it recognizes (UniProt Q15392: isoforms; datasheet A02125-1). Its processed chain spans residues 23–516; the lumenal segment is 23–31, while residues 53–516 face the cytoplasm (UniProt Q15392: processing and topology). Check the antibody’s documented immunogen against the isoforms before interpreting a negative cell population as absence of all DHCR24 protein (standard IHC practice; UniProt Q15392: isoforms). If epitope information remains unavailable, compare the staining with an independently characterized antibody and appropriate positive tissue controls, keeping retrieval and detection conditions documented (standard IHC practice).
How should I assess DHCR24 in a multiplex IF experiment?
Treat IF/ICC as a separate application: the supplied catalog image establishes paraffin-section chromogenic IHC conditions, while the HPA subcellular payload lists no ICC/IF images (datasheet A02125-1; HPA: subcellular data). For a multiplex IF design, pair DHCR24 with a marker identifying the expected cell population, such as hepatocytes or adrenal glandular cells, and validate each channel separately (HPA: liver hepatocytes, Medium; HPA: adrenal glandular cells, High; standard IF practice). Choose a fluorophore in a channel with low measured tissue autofluorescence and include single-label controls (standard IF practice). Because the catalog antibody’s epitope is unspecified, assess permeabilisation experimentally: most of residues 53–516 are cytoplasmic, whereas 23–31 are lumenal (UniProt Q15392: topology; datasheet A02125-1).
What should I check when DHCR24 DAB staining is widespread?
First compare the suspected signal with a no-primary control and examine whether it follows cell boundaries, tissue damage or section edges (standard IHC practice). The selected image used a 10% goat-serum block, a 1:100 rabbit primary overnight at 4°C, and a peroxidase-based DAB detection workflow (datasheet A02125-1). Check the peroxidase block and secondary-only control when diffuse brown color persists; endogenous enzyme activity and nonspecific detection can contribute to chromogenic background (standard IHC practice). Adjust blocking, washing or primary concentration on matched sections while preserving a positive-cell reference, such as adrenal glandular cells with high reported staining (standard IHC practice; HPA: adrenal glandular cells, High).
How can I compare DHCR24 staining across sections reliably? ⚠ ANSWER MARKED FOR VERIFICATION
Choose an H-score or percent-positive-cell measure for comparable cell populations, and document the threshold before scoring (standard IHC practice). An H-score combines the percentage of cells at each intensity with intensity grades, whereas a density per mm² measure can describe positive cells in a defined region (standard IHC practice). Normalize the result to the number of evaluable target cells or the measured viable tissue area, and exclude folds and necrotic regions by the same rules in every section (standard IHC practice). Keep retrieval, primary dilution, DAB development, imaging and cell-type annotation consistent; HPA reports different DHCR24 levels in adrenal glandular cells and liver hepatocytes (standard IHC practice; HPA: adrenal glandular cells, High; HPA: liver hepatocytes, Medium).
Which patterns would make a DHCR24 positive call doubtful?
A plausible positive call is cytoplasmic staining in an expected cell population, such as adrenal glandular cells or hepatocytes, interpreted against tissue morphology (HPA: cytoplasmic expression; HPA: adrenal glandular cells, High; HPA: liver hepatocytes, Medium). Predominantly nuclear or extracellular color conflicts with the reported endoplasmic reticulum and Golgi membrane localisation and warrants a specificity check (UniProt Q15392: subcellular location; standard IHC practice). Edge-restricted staining, necrotic areas or similar color in a no-primary control suggest artefact rather than a cell-specific result (standard IHC practice). Also inspect the peroxidase control when DAB color is widespread, and avoid treating a single tissue pattern as definitive: HPA rates its tissue IHC evidence Enhanced but pending external verification (standard IHC practice; HPA: reliability description).
Boster reagents

Best DHCR24 / Delta(24)-sterol reductase IHC Antibodies

A02125-1 has real IHC data from a paraffin-embedded human liver cancer section (catalog image caption); listed reactivity covers human, mouse, and rat (catalog reactivity).

Real IHC data IHC analysis of DHCR24 using anti-DHCR24 antibody (A02125-1). DHCR24 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:100 rabbit anti-DHCR24 Antibody (A02125-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-DHCR24 Antibody
Cat # A02125-1

A02125-1 is listed for IHC (catalog applications), with a figure showing a paraffin-embedded human liver cancer section (catalog image caption). It is listed as reactive with human, mouse, and rat (catalog reactivity); no IF figure or IF application is supplied (catalog payload).

Which to pick: Choose A02125-1 for tissue IHC: it is a rabbit polyclonal listed for IHC (catalog host, clonality, and applications), and its own figure documents a paraffin-embedded human liver cancer section (catalog image caption); the fixative is unreported (catalog image caption). Its listed human, mouse, and rat reactivity supports considering it for cross-species work, though the supplied IHC figure shows only human tissue (catalog reactivity; catalog image caption). There is no payload-supported IF/ICC pick because A02125-1 has no listed IF application or IF figure (catalog applications and image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q15392 (DHC24_HUMAN, Delta(24)-sterol reductase).
  2. Human Protein Atlas. DHCR24 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. DHCR24 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. DHCR24 antibody validation summary (3 antibodies).
  5. Cholesterol Synthetase DHCR24 Induced by Insulin Aggravates Cancer Invasion and Progesterone Resistance in Endometrial Carcinoma. Scientific reports 2017 — PMC5256103.
  6. Pan-cancer analysis reveals the potential role of DHCR24 in bladder cancer via interactions with HRAS to facilitate cholesterol synthesis. Oncology letters 2025 — PMC12174751.
  7. In-depth proteomics reveals the characteristic developmental profiles of early lung adenocarcinoma with epidermal growth factor receptor mutation. Cancer medicine 2023 — PMC10225231.
  8. Human umbilical cord mesenchymal stem cells small extracellular vesicles-derived miR-370-3p inhibits cervical precancerous lesions by targeting DHCR24. Stem cells translational medicine 2025 — PMC11825698.
  9. PubMed PMID:11007892 — UniProt-cited evidence.
  10. PubMed PMID:11519011 — UniProt-cited evidence.
  11. PubMed PMID:7584026 — UniProt-cited evidence.