DLST / Dihydrolipoyllysine-residue succinyltransferase component of 2-oxoglutarate dehydrogenase complex, mitochondrial · IHC design guide

Design Immunohistochemistry for DLST

Plan DLST staining in paraffin sections using liver hepatocytes as a strong reference (HPA tissue IHC). Assess granular cytoplasmic staining and start the catalog antibody at 2–5 μg/ml (HPA tissue IHC; datasheet A05097-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DLST (IHC for DLST): expected localisation Granular cytoplasm in most tissues (HPA tissue IHC), antibody A05097-1, validated IHC image, and IHC protocol steps
Printable DLST IHC protocol sheet — expected localisation Granular cytoplasm in most tissues (HPA tissue IHC), antibody A05097-1, controls and protocol steps. Open the full DLST IHC guide →

DLST Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm in most tissues (HPA tissue IHC)
Staining pattern Granular cytoplasmic staining in many cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05097-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Salivary and prostate glandular cells show low staining (HPA tissue IHC)
Regulation Low tissue specificity (HPA tissue RNA)
Isoform / epitope 2 isoforms; mature chain starts at residue 68; check epitope coverage (UniProt)
Section 1

Recommended DLST IHC & IF Protocols

Compare the catalog antibody’s EDTA pH 8.0 IHC-P protocol (datasheet A05097-1) with three published DLST tissue protocols (PMC9905101; PMC11219760; PMC12604326).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A05097-1)
FixationImage fixative and duration unreported (datasheet A05097-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05097-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05097-1)
Primary antibodyRabbit anti-DLST, 2-5 μg/ml (datasheet A05097-1)
Primary incubationOvernight at 4 °C (datasheet A05097-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A05097-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDLST-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous granular cytoplasmic expression in a majority of tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A05097-1); citrate pH 6.0 is a published alternative for mouse brain sections (PMC12604326).
Section 2

What Is the Expected DLST Staining Pattern?

DLST is mainly mitochondrial, with a small nuclear fraction and no transmembrane segment (UniProt P36957 localization and topology). In paraffin tissue sections, expect granular cytoplasmic staining across many cell types, including hepatocytes and cerebellar Purkinje cells (HPA: ubiquitous granular cytoplasmic expression; High in both cell types). HPA rates the tissue staining profile Supported, citing consistency with RNA expression (HPA: IHC reliability Supported).

What am I looking at on my slide?
Distinct granular cytoplasmic staining in hepatocytes or Purkinje cells.This matches the reported tissue pattern and provides a useful positive reference (HPA: granular cytoplasmic profile; High in hepatocytes and Purkinje cells). Judge the granules within intact cells, alongside section morphology, rather than treating any brown deposit as cellular staining (general IHC practice).
Predominantly nuclear, membranous, or extracellular chromogen in an IHC section.Predominantly nuclear or noncellular staining departs from HPA’s granular cytoplasmic tissue profile and warrants an artifact check (HPA: tissue IHC profile). A small nuclear DLST fraction is biologically plausible (UniProt P36957 localization), so isolated nuclear signal is not, by itself, proof of cross-reactivity. A membranous pattern has no support from the supplied topology (UniProt P36957 topology).
Strong staining confined to a cell population outside the reported high-expression examples.Compare its location and morphology with neighboring cells before assigning specificity: HPA reports broad expression, including High staining in germinal center cells and several glandular cell populations (HPA: tissue IHC profile). Unexpected, cell-restricted deposits can reflect cross-reactivity or endogenous detection activity; a no-primary control helps distinguish the latter (general IHC practice).
Uniform haze, widespread chromogen deposits, or staining without clear cell boundaries.This is less consistent with discrete granular cytoplasmic DLST staining (HPA: tissue IHC profile). Assess the no-primary control, blocking, washes, and chromogen development for nonspecific or detection-derived background (general IHC practice). HPA’s Supported reliability describes the reported profile; it does not validate every new staining run (HPA: IHC reliability Supported).
No discernible signal in a section expected to provide a positive reference.Absence of staining in hepatocytes or Purkinje cells conflicts with their reported High levels (HPA: High in hepatocytes and Purkinje cells). Check tissue preservation, antigen retrieval, antibody application, detection reagents, and controls as general IHC troubleshooting steps (general IHC practice). The supplied sources do not establish a DLST-specific fixation or retrieval failure mechanism.
💡Expected DLST appearanceA convincing positive is discrete granular cytoplasmic staining in intact cells, readily seen in reported High populations such as hepatocytes (HPA: tissue IHC profile; High in hepatocytes); diffuse deposits or a dominant membranous pattern require artifact assessment (HPA: tissue IHC profile; UniProt P36957 topology).
How each factor affects the staining
Cellular compartment and readoutTissue IHC shows mainly granular cytoplasmic staining (HPA: tissue IHC profile), while ICC-IF reports supported nucleoplasmic localization and uncertain mitochondrial and cytosolic localization (HPA: subcellular ICC-IF). Interpret these as assay-specific observations; UniProt also records mainly mitochondrial DLST with a small nuclear fraction (UniProt P36957 localization).
Choice of tissue referenceHPA reports High staining in hepatocytes, Purkinje cells, and several other listed populations, but Low staining in salivary glandular cells, prostate glandular cells, smooth muscle cells, and fibroblasts in soft tissue (HPA: tissue IHC levels). Low is a weaker comparator, not a validated negative control; HPA lists no negative tissue here (HPA: negative tissue list empty).
Antibody and isoform coverageThe listed antibody HPA003010 has Supported IHC status (HPA: antibody validation). UniProt records two isoforms and a mature chain spanning residues 68–453 (UniProt P36957 isoforms and processing). The payload gives no epitope position or isoform coverage, so staining cannot be assigned to a particular isoform or processing state.
Detection chemistryEndogenous enzyme activity or nonspecific chromogen deposition can imitate cellular staining in chromogenic IHC (general IHC practice). A matched no-primary control tests detection-derived signal in the same tissue (general IHC practice). This is a general assay consideration, not evidence that DLST itself has a particular endogenous detection artifact.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Granular staining is faint in an HPA High reference tissue.A weak run signal is possible, but HPA’s reported intensity does not specify a cause in your section (HPA: High in hepatocytes or Purkinje cells).Review section quality, retrieval and detection controls, then adjust antibody dilution or development within the applicable IHC workflow (general IHC practice). Do not infer DLST-specific fixation sensitivity from the HPA intensity rating.
Chromogen is strongest at tissue edges or across empty spaces.Edge effects or nonspecific deposits can occur during section staining (general IHC practice); they do not match the reported cellular granules (HPA: tissue IHC profile).Inspect section adhesion and reagent coverage, repeat with even incubation and washing, and compare with a no-primary control (general IHC practice).
Nuclei dominate an otherwise weak IHC stain.This differs from the reported granular cytoplasmic IHC profile (HPA: tissue IHC profile), although UniProt recognizes a small nuclear fraction (UniProt P36957 localization).Check chromogen distribution, counterstain, and control sections before calling nuclear DLST; report a reproducible nuclear component separately from the expected cytoplasmic pattern (general IHC practice).
Unexpected cells stain strongly while the reference population is weak.Broad DLST expression is reported, but this combination may also reflect nonspecific binding or detection activity (HPA: ubiquitous tissue IHC profile; general IHC practice).Compare cellular granularity, use a no-primary control, and reassess the IHC-validated antibody’s staining against an HPA High reference tissue (HPA: antibody IHC Supported; HPA: tissue IHC levels).
All cells are negative, including the positive reference.A failed staining or detection step is plausible when an HPA High population is blank (HPA: High in hepatocytes or Purkinje cells; general IHC practice).Verify reagent order, retrieval execution, antibody application, and positive-control detection in the same run (general IHC practice). The evidence supplied does not identify a DLST-specific retrieval condition.
IF/ICC Q: Why does nucleoplasmic staining appear?HPA reports the nucleoplasm as the main supported ICC-IF location, with mitochondrial and cytosolic locations uncertain (HPA: subcellular ICC-IF). UniProt describes a small nuclear fraction (UniProt P36957 localization).Interpret that image within its ICC-IF assay context; use the granular cytoplasmic tissue profile when judging paraffin IHC (HPA: tissue IHC profile).

Sample controls for DLST IHC & IF

🧪Run cerebellum first and look for staining in Purkinje cells (HPA: High in Purkinje cells). HPA lists no negative tissue and detects DLST in all 44 scored tissues, so use no-primary and isotype controls for the negative comparison; any unstained cells on the positive slide provide a background reference, not a validated DLST-negative cell population (HPA: no negative rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: DLST is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DLST in SiHa, U-251MG, U2OS, Sperm, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a concentration-matched rabbit isotype control for the rabbit catalog antibody, and a DLST-knockout or validated peptide-block control (caption: rabbit anti-DLST antibody). Quench endogenous peroxidase and assess endogenous biotin background when using the caption’s streptavidin–biotin/DAB detection (caption: SABC/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A05097-1 paraffin-section caption does not state a fixative (caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used in that caption, but retrieval dependency and whether frozen sections or IF are easier are unreported (caption: EDTA retrieval). In cerebellum, neuronal lipofuscin can complicate fluorescence interpretation, so assess unstained tissue autofluorescence if using IF (HPA: High in Purkinje cells; standard IF practice).

HPA tissue IHC evidence for DLST

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →
Fallopian tube Glandular cells High Protein (IHC) HPA →
Kidney Bowman's capsule High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: DLST is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced DLST IHC Tips

Troubleshoot DLST staining in paraffin sections by checking retrieval, signal location, controls, and scoring before interpreting biological differences.

Which antigen retrieval conditions should I try first for DLST IHC?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A05097-1). The selected paraffin-section example used this condition before staining human liver cancer tissue with 2 μg/ml antibody overnight at 4°C (datasheet A05097-1). If signal is weak, compare a small retrieval-time series while holding antibody concentration and detection conditions constant (standard IHC practice). Excess heating can damage section morphology or increase diffuse staining, so inspect both the tissue and the expected granular cytoplasmic pattern (standard IHC practice; HPA tissue IHC). Record the retrieval conditions for every run so that staining comparisons remain interpretable (standard IHC practice).
Could fixation explain weak or uneven DLST staining?
The selected paraffin-section caption does not state a fixative, so DLST sensitivity to fixation in this assay is unknown (datasheet A05097-1). Compare sections with documented fixation histories using the same EDTA pH 8.0 retrieval and staining run (datasheet A05097-1; standard IHC practice). Review whether weak staining follows fixation duration or affects only poorly preserved regions, and check morphology before changing antibody concentration (standard IHC practice). A well-preserved reference section stained alongside the test sections helps separate specimen variation from run variation (standard IHC practice). Do not infer a fixation effect from DLST localization or modification annotations alone (UniProt P36957; standard IHC practice).
Where should convincing DLST signal appear in paraffin sections?
Expect predominantly granular cytoplasmic staining in tissue IHC, consistent with the reported widespread pattern and DLST’s principal mitochondrial-matrix location (HPA tissue IHC; UniProt P36957). A small nuclear fraction is described for the protein, whereas HPA cell imaging reports supported nucleoplasmic localization; assess a nuclear IHC signal cautiously against cytoplasmic staining and controls (UniProt P36957; HPA subcellular). Inspect hepatocytes or Purkinje cells as reported high-staining reference populations when those tissues are available (HPA tissue IHC). Uniform staining across extracellular spaces, section folds, or damaged edges is less persuasive than a reproducible cellular pattern (standard IHC practice). Compare compartments at the same magnification and exposure to the chromogen (standard IHC practice).
Can isoforms or modifications alter what this antibody detects?
DLST has 2 annotated isoforms, but the supplied evidence does not map the catalog antibody’s epitope to either one (UniProt P36957; datasheet A05097-1). The processed chain spans residues 68–453, and the lipoyl-binding region spans 70–144 (UniProt P36957). Lipoylation at Lys110 and other annotated modifications could matter if they overlap an antibody epitope, but that overlap is unreported (UniProt P36957; datasheet A05097-1). Interpret different staining patterns as assay observations until epitope mapping or independent antibody validation establishes an isoform-specific explanation (standard IHC practice). Compare staining with a second, documented epitope where isoform assignment matters (standard IHC practice).
How should I check DLST localization by IF alongside tissue IHC?
For IF, pair DLST with a marker for the expected cell population, such as a hepatocyte marker when examining liver, and evaluate signal within the marked cells (HPA tissue IHC; standard IF practice). Choose fluorophores in channels with low specimen autofluorescence, and include unstained and secondary-only controls to identify background (standard IF practice). DLST is principally in the mitochondrial matrix and has no transmembrane segment, so permeabilization must allow antibody access beyond cellular and mitochondrial membranes (UniProt P36957; standard IF practice). Optimize permeabilization empirically while checking morphology and background; the paraffin-section IHC caption supplies no IF fixation or permeabilization conditions (datasheet A05097-1; standard IF practice). Compare compartment patterns cautiously because HPA cell imaging reports supported nucleoplasmic localization (HPA subcellular).
What should I change when DLST IHC has diffuse background?
First inspect a section processed without primary antibody to assess detection-system and tissue background (standard IHC practice). For the selected paraffin-section example, the primary was 2 μg/ml overnight at 4°C, followed by a biotinylated secondary and DAB detection (datasheet A05097-1). If background persists, titrate primary concentration, review washing and blocking, and verify that endogenous peroxidase activity is adequately quenched before chromogen development (standard IHC practice). Because the demonstrated method uses a biotin-based detection system, assess endogenous biotin background where relevant (datasheet A05097-1; standard IHC practice). Preserve the expected granular cytoplasmic signal while reducing diffuse staining (HPA tissue IHC; standard IHC practice).
How can I quantify DLST staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score staining in a defined cell population using an H-score, or report the percentage of positive cells with a prespecified intensity threshold (standard IHC practice). For spatial analysis, count positive cells per mm² of viable tissue and normalize to the measured viable area (standard IHC practice). Keep retrieval, antibody concentration, chromogen development, imaging, and threshold rules consistent across compared sections (standard IHC practice). Record cytoplasmic and nuclear staining separately because tissue IHC is described as granular cytoplasmic while a minor nuclear fraction is reported (HPA tissue IHC; UniProt P36957). Include cell composition in the interpretation when comparing tissues with different proportions of high-staining populations (HPA tissue IHC; standard IHC practice).
How do I distinguish meaningful DLST staining from artefact?
A reproducible granular cytoplasmic pattern in appropriate cells supports DLST staining, particularly where hepatocytes or Purkinje cells show the reported high expression (HPA tissue IHC). Nuclear signal requires separate scrutiny because UniProt describes a small nuclear fraction, while HPA cell imaging identifies nucleoplasm as its supported main location (UniProt P36957; HPA subcellular). Check whether apparent positivity instead tracks section edges, folds, necrotic regions, or endogenous enzyme activity in a no-primary control (standard IHC practice). Compare the suspect region with intact neighboring tissue and repeat staining under the same EDTA pH 8.0 retrieval conditions (datasheet A05097-1; standard IHC practice). Assign biological meaning only to patterns that remain consistent across suitable controls and sections (standard IHC practice).
Boster reagents

Best DLST / Dihydrolipoyllysine-residue succinyltransferase component of 2-oxoglutarate dehydrogenase complex, mitochondrial IHC Antibodies

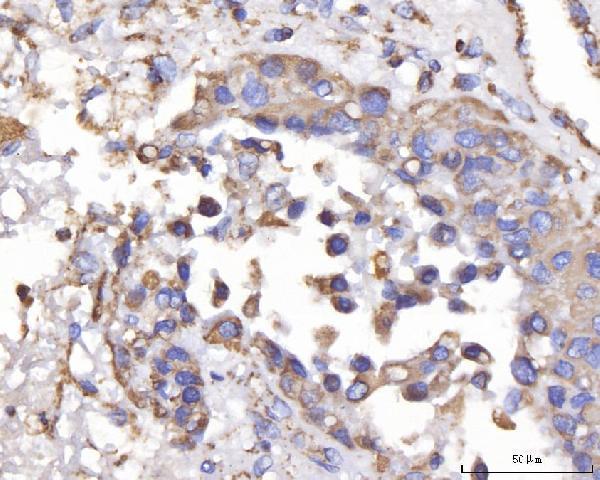
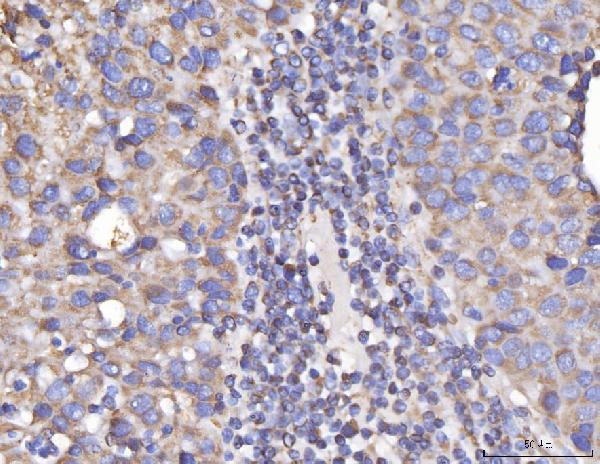
A05097-1 has human paraffin-section IHC images from liver, breast, and lung cancer tissue (IHC image captions). Human IF/ICC is listed, but no IF image is supplied (catalog applications; IF image data).

Real IHC data IHC analysis of DLST using anti-DLST antibody (A05097-1). DLST was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-DLST Antibody (A05097-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-DLST Antibody ®
Cat # A05097-1

A05097-1’s rendered IHC figure shows a human liver cancer paraffin section (rendered IHC caption). Additional IHC captions show human breast and lung cancer paraffin sections; the catalog lists IF/ICC for human samples and reactivity with human, mouse, and rat (IHC image captions; catalog applications and reactivity).

Which to pick: For tissue IHC, choose A05097-1: its paraffin-section caption reports EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (IHC image caption). For IF/ICC, A05097-1 is listed at 5 μg/ml for human samples, though no IF image is supplied (catalog dilution and applications; IF image data). For work across species, A05097-1 lists human, mouse, and rat reactivity, while the supplied IHC images show human tissue only; clonality is unreported (catalog reactivity; IHC image captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P36957 (ODO2_HUMAN, Dihydrolipoyllysine-residue succinyltransferase component of 2-oxoglutarate dehydrogenase complex, mitochondrial).
  2. Human Protein Atlas. DLST tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. DLST subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol and mitochondria..
  4. Human Protein Atlas. DLST antibody validation summary (1 antibodies).
  5. Identification of cuproptosis-related subtypes and the development of a prognostic model in glioma. Frontiers in genetics 2023 — PMC10014798.
  6. Co-occurrence of mutations in NF1 and other susceptibility genes in pheochromocytoma and paraganglioma. Frontiers in endocrinology 2022 — PMC9905101.
  7. Disulfiram downregulates ferredoxin 1 to maintain copper homeostasis and inhibit inflammation in cerebral ischemia/reperfusion injury. Scientific reports 2024 — PMC11219760.
  8. Cuproptosis-driven astrocyte reactivity exacerbates experimental cerebral malaria pathogenesis. Parasites & vectors 2025 — PMC12604326.
  9. PubMed PMID:8268217 — UniProt-cited evidence.
  10. PubMed PMID:8076640 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.