DNAJB6 / DnaJ homolog subfamily B member 6 · IHC design guide

Design Immunohistochemistry for DNAJB6

Plan chromogenic IHC on paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A03290-1). Use nuclear and cytoplasmic staining in myocytes, cardiomyocytes and spermatogonia as reference patterns (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DNAJB6 (IHC for DNAJB6): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A03290-1, validated IHC image, and IHC protocol steps
Printable DNAJB6 IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A03290-1, controls and protocol steps. Open the full DNAJB6 IHC guide →

DNAJB6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Nuclear and cytoplasmic staining in myocytes and cardiomyocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03290-1)
Positive control ⓘ Heart muscle+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across tissue sections. (standard IHC practice; not target-specific)
Caveat Adipocytes may lack signal despite broad tissue expression (HPA tissue IHC)
Regulation Staining is strongest in skeletal and heart muscle (HPA tissue IHC)
Isoform / epitope 4 isoforms; check epitope coverage across variants (UniProt)
Section 1

Recommended DNAJB6 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by two published DNAJB6 protocols using paraffin sections (datasheet A03290-1; PMC10607153; PMC11429285).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A03290-1)
FixationImage fixative and duration unreported (datasheet A03290-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03290-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03290-1)
Primary antibodyRabbit anti-DNAJB6, 2-5 μg/ml (datasheet A03290-1)
Primary incubationOvernight at 4 °C (datasheet A03290-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03290-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDNAJB6-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear and cytoplasmic expression, most abundant in skeletal and heart muscle. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A03290-1); the lung tissue microarray study used Tris-EDTA pH 9.0 (PMC11429285).
Section 2

What Is the Expected DNAJB6 Staining Pattern?

DNAJB6 should show nuclear and cytoplasmic staining in IHC, with prominent signal in cardiomyocytes, skeletal myocytes and testicular spermatogonia (HPA tissue IHC: High in each cell type). Perinuclear and muscle Z-line localization are also reported (UniProt O75190: subcellular location). DNAJB6 has no transmembrane segment (UniProt O75190: topology). Treat this as a supported pattern with medium agreement between antibody staining and RNA data, rather than an absolute rule for every cell (HPA tissue IHC: Supported).

What am I looking at on my slide?
Cardiomyocytes or skeletal myocytes show clear nuclear and cytoplasmic staining.This fits the strongest reported muscle cell staining (HPA tissue IHC: High in both). Cytoplasmic detail may include myofibrillar or Z-line localization (UniProt O75190: subcellular location); visible striations are not required for a positive IHC call.
Testicular spermatogonia stain, while adjacent cells vary in intensity.High staining in spermatogonia supports the positive call (HPA tissue IHC: High in spermatogonia). UniProt also reports expression in earlier germ cells and spermatids (UniProt O75190: tissue specificity). Score identifiable cell types separately rather than assigning one intensity to the entire testis.
Signal is confined to a crisp plasma membrane outline or an extracellular deposit.That distribution conflicts with the reported nuclear and cytoplasmic pattern (HPA tissue IHC: profile) and the absence of a transmembrane segment (UniProt O75190: topology). Treat it as suspect until antibody specificity and the detection system are checked; morphology alone cannot prove its cause.
A cell type reported as unstained shows strong chromogen, or nearly all structures stain alike.Adipocytes and cholangiocytes are reported as not detected in the sampled tissues (HPA tissue IHC: adipose tissue; liver). Unexpected signal could reflect cross-reactivity or endogenous detection activity, but these HPA examples are cell-specific comparators, not proof that the entire tissue is negative.
Broad, low-contrast chromogen obscures nuclei and cell boundaries.Diffuse background cannot be scored reliably as DNAJB6 localization. Compare the no-primary control and inspect whether signal follows tissue structures; background from detection reagents, insufficient blocking or inadequate washing is a general IHC possibility, not a DNAJB6-specific finding.
💡Expected DNAJB6 appearanceCall a result positive when identifiable cardiomyocytes, skeletal myocytes or spermatogonia show convincing nuclear and cytoplasmic staining, often strong in these cells (HPA tissue IHC: High; nuclear and cytoplasmic profile); isolated membrane outlines or indiscriminate extracellular color are suspect (UniProt O75190: topology; HPA tissue IHC: profile).
How each factor affects the staining
Cell type and tissue contextDNAJB6 is widely expressed (UniProt O75190: tissue specificity), but HPA records High muscle and spermatogonial staining alongside Not detected adipocytes and cholangiocytes (HPA tissue IHC). Interpret mixed fields by cell type; a weak or unstained neighbor does not invalidate a positive cell.
Compartment and tissue resolutionNuclear and cytoplasmic IHC is the broad tissue expectation (HPA tissue IHC: profile). UniProt additionally lists perinuclear and muscle Z-line locations (UniProt O75190: subcellular location). Section quality and chromogenic resolution can limit whether those finer patterns are distinguishable; do not require them for scoring.
Antibody validationThree listed antibodies have Supported IHC status (HPA antibodies: HPA024258, HPA058593, CAB004670). The overall tissue profile has medium consistency with RNA expression (HPA tissue IHC: reliability description). Use the chosen antibody's validation context when judging an unexpected pattern; Supported does not make every isolated stained structure specific.
Isoforms and processingUniProt lists four isoforms, A–D, and no signal peptide or propeptide (UniProt O75190: isoforms; processing). The supplied evidence does not map antibody epitopes to isoforms, so it cannot explain a compartment difference by isoform or establish an epitope-specific retrieval condition.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in cardiomyocytes, skeletal myocytes or spermatogonia.These are High IHC cell types (HPA tissue IHC); an empty field may indicate a failed staining run or unsuitable specimen, but the supplied sources do not identify a DNAJB6-specific fixation sensitivity.Confirm the expected cells are present, check a known-positive section from the same run, and review the antibody's IHC validation and the run's general detection controls.
Only membrane or extracellular material is strongly colored.The pattern conflicts with nuclear and cytoplasmic localization (HPA tissue IHC: profile) and no transmembrane segment (UniProt O75190: topology). Nonspecific antibody binding or detection artifact is possible.Review morphology and a no-primary control; if the pattern persists, compare with a separately validated IHC antibody (HPA antibodies: Supported IHC entries).
Strong signal appears in adipocytes or cholangiocytes.Those cell types are Not detected in the cited HPA tissue examples (HPA tissue IHC: adipose tissue; liver). Cross-reactivity or endogenous detection activity is possible; HPA does not establish universal absence.Verify cell identity, compare nearby expected-positive cells and the no-primary control, and assess whether the unexpected color persists with an independently validated antibody.
Diffuse color makes nuclear versus cytoplasmic scoring uncertain.Background can arise from general IHC workflow conditions such as insufficient blocking, washing or chromogen control; the payload gives no DNAJB6-specific cause.Inspect the no-primary control, review blocking and wash steps, and adjust development so identifiable cells and compartments can be scored without broad background.
Muscle stains, but no visible Z-line pattern appears.UniProt reports Z-line localization (UniProt O75190: subcellular location), while HPA summarizes tissue IHC as nuclear and cytoplasmic (HPA tissue IHC: profile). Chromogenic sections may not resolve fine sarcomeric detail.Score the nuclear and cytoplasmic signal in identifiable myocytes against the HPA High reference; do not reject a positive solely because striations are unresolved.
What localization should an IF/ICC image show?HPA reports mainly nucleoplasmic signal with additional cytosolic signal in ICC-IF (HPA subcellular: supported main and additional locations). This is cell imaging evidence, separate from the tissue IHC profile.Use that compartment pattern to interpret IF/ICC images, with cell morphology and appropriate channel controls. Consult the separate IF/ICC guide for its workflow; this IHC section provides no IF/ICC protocol option.

Sample controls for DNAJB6 IHC & IF

🧪Run heart muscle first: cardiomyocytes should stain (HPA: High in cardiomyocytes). Use adipose tissue as the negative comparator (HPA: Not detected in adipocytes); on the heart slide, score any cells without specific DAB staining as internal negatives without assuming a cell identity from the cardiomyocyte result.
Positive control tissue: Heart muscle (Cardiomyocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DNAJB6 in A-431, U-251MG, U2OS, hTERT-RPE1 (serum starved), with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and matched rabbit IgG isotype controls (selected-SKU tissue-IHC caption: rabbit primary antibody), plus DNAJB6-knockout tissue if available or an immunizing-peptide competition control if the peptide is available. Block endogenous peroxidase for chromogenic detection, particularly in blood-containing areas of heart tissue (selected-SKU tissue-IHC caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the fixative in the selected-SKU tissue-IHC caption is unreported. The demonstrated paraffin-section workflow uses heat retrieval in EDTA at pH 8.0 (selected-SKU tissue-IHC caption); that example does not establish whether retrieval is essential. The supplied evidence does not establish that frozen sections or IF are easier; cardiac autofluorescence should be checked if IF is attempted (standard IF practice).

HPA tissue IHC evidence for DNAJB6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Skeletal muscle Myocytes High Protein (IHC) HPA →
Testis Spermatogonia cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced DNAJB6 IHC Tips

Troubleshoot DNAJB6 staining in paraffin sections by checking retrieval, controls, cellular localisation and scoring before interpreting differences between specimens.

Which retrieval conditions should I try first for weak DNAJB6 staining?
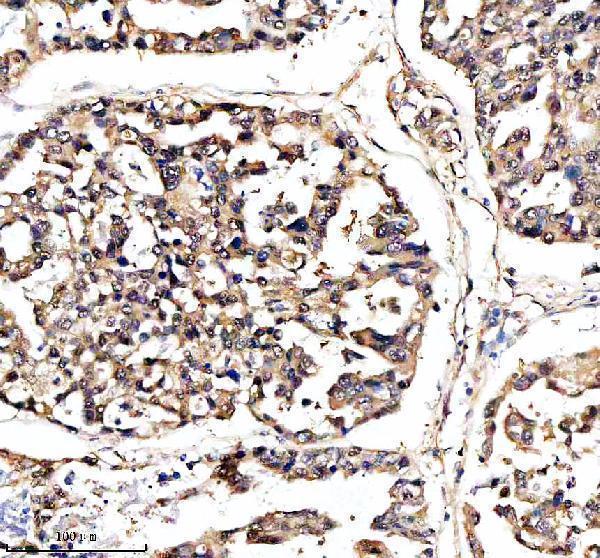
Start with heat-mediated EDTA at pH 8.0 for paraffin-section antigen retrieval (datasheet A03290-1). The selected image used human lung cancer tissue, followed by 10% goat serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A03290-1). If signal remains weak, compare heating durations on adjacent sections while holding antibody concentration and DAB development constant (standard IHC practice). Check section morphology and a no-primary control before accepting an apparent gain in signal (standard IHC practice). Assess both nuclear and cytoplasmic staining when judging improvement (HPA tissue IHC; UniProt O75190 subcellular localisation).
How should I investigate fixation as a cause of uneven DNAJB6 staining?
DNAJB6 sensitivity to fixative type or fixation duration is unknown because no target-specific fixation comparison is supplied (provided evidence). The selected paraffin-section image does not state its fixative, so its staining cannot establish an optimal fixation condition (datasheet A03290-1). For prospective specimens, record time to fixation, fixative and fixation duration, then process comparison sections identically (standard IHC practice). For archival sections, compare similarly processed specimens and include a known-positive tissue in each run (standard IHC practice; HPA tissue IHC). Check retrieval, section integrity and detection before assigning a staining difference to fixation (standard IHC practice).
Should DNAJB6 appear in nuclei, cytoplasm or muscle structures?
Evaluate nuclear and cytoplasmic staining: tissue IHC reports ubiquitous expression in both compartments, and cell imaging places DNAJB6 mainly in the nucleoplasm with additional cytosolic signal (HPA tissue IHC; HPA subcellular). UniProt also annotates perinuclear localisation and association with the sarcomere Z line (UniProt O75190 subcellular localisation). Compare compartments within morphologically intact cells rather than treating every isolated DAB deposit as localisation (standard IHC practice). Heart cardiomyocytes and skeletal myocytes are reported as high-staining cells and can help anchor the expected pattern (HPA tissue IHC). Record nuclear and cytoplasmic signal separately if a condition appears to shift their balance (standard IHC practice).
Can a DNAJB6 staining change identify a particular isoform or modified epitope?
DNAJB6 has 4 annotated isoforms, A through D, but the supplied antibody caption does not identify its epitope (UniProt O75190 isoforms; datasheet A03290-1). Consequently, this chromogenic stain alone cannot assign a signal to one isoform without separate epitope and isoform validation (standard IHC interpretation). The protein contains a J domain at residues 2–69 and annotated modified residues at 135 and 277 (UniProt O75190 domains and modified residues). Do not infer that either modification alters retrieval or antibody binding without a mapped epitope and direct comparison (standard IHC practice). Compare matched sections under identical retrieval and detection conditions before interpreting a compartment-specific loss (standard IHC practice).
How can IF help check the cellular source of an IHC signal?
Use IF as a separate localisation check, pairing DNAJB6 with a marker for the expected cell type in the specimen (standard IF practice). For muscle-rich material, cardiomyocytes and skeletal myocytes provide relevant high-expression expectations (HPA tissue IHC). Select fluorophores outside the strongest tissue autofluorescence where possible, and inspect single-stain and no-primary controls before interpreting overlap (standard IF practice). Because DNAJB6 is annotated in nuclear and cytoplasmic compartments and has no transmembrane segment, permeabilisation should allow access to intracellular epitopes (UniProt O75190 subcellular localisation and topology; standard IF practice). The selected antibody caption documents paraffin-section chromogenic IHC, so IF staining requires its own validation (datasheet A03290-1).
What should I adjust when DAB obscures DNAJB6 staining?
Compare a no-primary section with the stained section to identify signal arising from detection reagents or tissue rather than primary-antibody binding (standard IHC practice). Include a peroxidase-blocking step and check whether diffuse brown signal persists before adjusting the primary antibody (standard chromogenic IHC practice). The selected image used 2 μg/ml primary antibody overnight at 4°C, followed by a peroxidase-conjugated secondary and DAB development (datasheet A03290-1). If background remains high, compare shorter DAB development or a lower primary concentration on matched sections (standard IHC practice). Preserve recognisable nuclear and cytoplasmic patterns while making adjustments, since both are reported for DNAJB6 (HPA tissue IHC).
How should I score DNAJB6 when nuclear and cytoplasmic staining differ? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then record nuclear and cytoplasmic DNAJB6 separately (standard IHC quantification; HPA tissue IHC). An H-score combines staining intensity with the percentage of positive cells; report the scoring scale and denominator used (standard IHC quantification). Alternatively, report percentage-positive cells or positive-cell density per mm² when intensity is unreliable (standard IHC quantification). Normalise each measure to viable cells or viable tissue area in the same annotated compartment, excluding folds and necrosis (standard IHC quantification). Compare sections processed with matched retrieval, antibody incubation and DAB development, because these steps can shift measured signal (standard IHC practice).
How can I distinguish a true DNAJB6-positive cell from artefact?
Prioritise staining within intact nuclei or cytoplasm, the reported DNAJB6 compartments, and check whether it follows identifiable cells (HPA tissue IHC; standard IHC interpretation). Cardiomyocytes, skeletal myocytes and spermatogonia are reported as high-staining populations, while adipocytes were not detected in the cited tissue profile (HPA tissue IHC). Brown deposits confined to section edges, folds or necrotic areas warrant comparison with adjacent intact tissue (standard IHC practice). Test suspicious diffuse staining against a no-primary control and confirm adequate peroxidase blocking to assess detection-related signal (standard chromogenic IHC practice). Interpret unexpected compartment or cell-type staining cautiously because the HPA tissue IHC reliability is rated Supported with medium RNA–staining consistency (HPA tissue IHC).
Boster reagents

Best DNAJB6 / DnaJ homolog subfamily B member 6 IHC Antibodies

A03290-1 has real IHC data from a human lung cancer paraffin section (A03290-1 image caption). Its listed reactivity covers Human, Mouse and Rat; no IF data are supplied (A03290-1 catalog).

Real IHC data IHC analysis of DNAJB6 using anti-DNAJB6 antibody (A03290-1). DNAJB6 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-DNAJB6 Antibody (A03290-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-DNAJB6 Antibody ®
Cat # A03290-1

A03290-1 was used for chromogenic IHC on a paraffin-embedded human lung cancer section at 2 μg/ml (A03290-1 image caption). The catalog lists IHC and Human, Mouse and Rat reactivity, but provides no IF application or image (A03290-1 catalog).

Which to pick: Choose A03290-1 for paraffin-section tissue IHC because its own image documents that preparation; the fixative is unreported (A03290-1 image caption). No listed SKU has IF/ICC validation (A03290-1 catalog). For cross-species planning, A03290-1 is rabbit polyclonal and lists Human, Mouse and Rat reactivity, while its pictured IHC result covers human tissue only (A03290-1 catalog; A03290-1 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75190 (DNJB6_HUMAN, DnaJ homolog subfamily B member 6).
  2. Human Protein Atlas. DNAJB6 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. DNAJB6 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. DNAJB6 antibody validation summary (3 antibodies).
  5. miR-632 Induces DNAJB6 Inhibition Stimulating Endothelial-to-Mesenchymal Transition and Fibrosis in Marfan Syndrome Aortopathy. International journal of molecular sciences 2023 — PMC10607153.
  6. Exome sequencing reveals DNAJB6 mutations in dominantly-inherited myopathy. Annals of neurology 2012 — PMC3314127.
  7. DNAJB6 Promotes Ferroptosis in Esophageal Squamous Cell Carcinoma. Digestive diseases and sciences 2020 — PMC7297805.
  8. Abnormally High Expression of DNAJB6 Accelerates Malignant Progression of Lung Adenocarcinoma. Biomedicines 2024 — PMC11429285.
  9. PubMed PMID:9915854 — UniProt-cited evidence.
  10. PubMed PMID:11896048 — UniProt-cited evidence.
  11. PubMed PMID:12974469 — UniProt-cited evidence.