DUSP9 / Dual specificity protein phosphatase 9 · IHC design guide

Design Immunohistochemistry for DUSP9

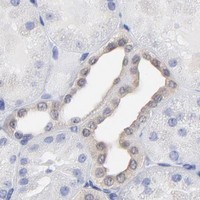
Plan chromogenic paraffin IHC for DUSP9 using the cytoplasmic tissue pattern reported in placenta and kidney (HPA tissue IHC). Use cytotrophoblasts as a positive reference and expect weaker distal tubule staining (HPA tissue IHC); optimize catalog antibody A07919 within 1:100–1:300 (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DUSP9 (IHC for DUSP9): expected localisation Cytoplasmic staining in placenta and kidney (HPA tissue IHC), antibody A07919, validated IHC image, and IHC protocol steps
Printable DUSP9 IHC protocol sheet — expected localisation Cytoplasmic staining in placenta and kidney (HPA tissue IHC), antibody A07919, controls and protocol steps. Open the full DUSP9 IHC guide →

DUSP9 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in placenta and kidney (HPA tissue IHC)
Staining pattern Cytoplasmic cytotrophoblasts; low distal tubule staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Placenta+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across samples (standard IHC practice; not target-specific)
Caveat Medium RNA–staining consistency; verify with controls (HPA tissue IHC)
Regulation Kidney/placenta RNA group enriched (HPA tissue RNA)
Isoform / epitope No isoforms annotated; one 1–384 chain (UniProt)
Section 1

Recommended DUSP9 IHC & IF Protocols

The catalog antibody's IHC-P protocol is accompanied by published DUSP9 workflows for hepatocytes, colorectal cancer tissue, and placenta (PMC6590435; PMC7538709; PMC6854249).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver carcinoma tissue; fixative not specified (datasheet A07919)
FixationImage fixative and duration unreported (datasheet A07919); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-DUSP9, 1:100-1:300 (datasheet A07919)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDUSP9-positive staining in cytotrophoblasts of placenta (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in placenta and kidney. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen-retrieval rule); the placental study used citrate at 98 °C for 15 min (PMC6854249).
Section 2

What Is the Expected DUSP9 Staining Pattern?

DUSP9 is cytoplasmic, with no transmembrane segment (UniProt Q99956). In paraffin IHC, expect cytoplasmic staining in placental cytotrophoblasts at medium intensity; kidney distal tubules show low staining, and elongated or late spermatids in testis show medium staining (HPA tissue IHC). HPA rates tissue staining “Enhanced,” while reporting medium agreement with RNA data and pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in placental cytotrophoblasts; weaker signal in kidney distal tubules.This fits HPA's medium placental and low kidney observations (HPA tissue IHC). Record cell type and compartment before comparing slide intensity: the supplied HPA levels describe different populations, not a single intensity expected throughout either tissue.
Predominantly nuclear or sharply cell-surface signal in placental cytotrophoblasts.Treat that pattern as suspect: UniProt places DUSP9 in the cytoplasm and reports no transmembrane segment (UniProt Q99956). Check whether the signal follows tissue edges, counterstain, or nonspecific detection before assigning it to DUSP9.
Strong staining in adipocytes or adrenal glandular cells.HPA reports DUSP9 as not detected in those respective cell populations (HPA tissue IHC). Review staining specificity and possible endogenous detection activity. A single unexpected positive field cannot establish a new DUSP9 tissue distribution.
Even chromogen across cells, stroma, and empty spaces.Diffuse signal that ignores cell boundaries is difficult to score as cytoplasmic DUSP9. Check background in a detection-only control and review blocking, washing, chromogen development, and section condition as general IHC troubleshooting steps.
No signal in placental cytotrophoblasts, including on a control section.HPA reports medium staining in this population (HPA tissue IHC). First check tissue identity and whether the cells are present; then review antibody and detection performance. One negative run does not overturn the reported tissue pattern.
💡Expected DUSP9 appearanceCall a positive IHC result when placental cytotrophoblast cytoplasm shows medium staining (HPA tissue IHC); isolated nuclear, cell-surface, or cell-independent chromogen is suspect given cytoplasmic DUSP9 localization (UniProt Q99956).
How each factor affects the staining
Cell population chosen for the positive controlPlacental cytotrophoblasts and elongated or late spermatids show medium staining, while kidney distal tubules show low staining (HPA tissue IHC). A faint kidney result needs a different interpretation from absent signal in placenta.
Antibody evidence and interpretation limitHPA lists HPA003336 as IHC “Enhanced” (HPA antibodies). The tissue profile has medium staining–RNA agreement and awaits external verification (HPA tissue IHC); compare morphology and controls before calling an unexpected pattern specific.
Compartment expected in paraffin IHCUniProt assigns DUSP9 to the cytoplasm and reports no transmembrane segment (UniProt Q99956). HPA describes cytoplasmic expression in placenta and kidney (HPA tissue IHC); these sources do not define a required membrane outline.
IF/ICC Q: Should an endoplasmic-reticulum pattern be expected?A: HPA reports mainly endoplasmic-reticulum localization in ICC-IF, with that location approved (HPA subcellular). Its tissue IHC profile describes cytoplasmic staining (HPA tissue IHC). Apply each observation to its own assay.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Placental control has no visible cytoplasmic signal.The expected cell population may be absent, or the IHC run may have failed; HPA reports medium cytotrophoblast staining (HPA tissue IHC).Confirm cytotrophoblasts on the section. Check a known working control and review antigen retrieval, primary antibody use, and detection steps as general IHC workflow checks.
Kidney distal tubules appear faint.Low staining is the reported level for this population (HPA tissue IHC); a faint signal alone does not show assay failure.Assess compartment and morphology, then compare with a placental positive control. Avoid increasing development solely to make kidney match medium-intensity placenta.
Signal appears mostly nuclear or at the cell surface.That distribution conflicts with cytoplasmic DUSP9 and its lack of a transmembrane segment (UniProt Q99956).Review the counterstain and section morphology, then compare with a detection-only control. Report persistent discordant signal separately from the expected cytoplasmic pattern.
Adipocytes or adrenal glandular cells stain strongly.Those cells are listed as not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible.Compare a detection-only control and inspect whether signal tracks the expected cells. Recheck specificity before interpreting the unexpected staining as DUSP9.
Chromogen coats the section without clear cell boundaries.Broad background can obscure cell-specific staining; the HPA tissue profile describes a cytoplasmic distribution (HPA tissue IHC).Inspect a detection-only control, then review blocking, washes, and chromogen development as general IHC workflow steps. Score only interpretable cellular signal.
The IF/ICC image looks more reticular than the paraffin IHC slide.HPA reports mainly endoplasmic-reticulum localization by ICC-IF, while its tissue IHC profile calls the pattern cytoplasmic (HPA subcellular; HPA tissue IHC).Interpret each image against its assay-specific HPA description. Do not require a resolved reticular pattern to call cytoplasmic paraffin IHC staining.

Sample controls for DUSP9 IHC & IF

🧪Run placenta first: cytotrophoblasts should stain at the HPA Medium level (HPA: placenta cytotrophoblasts, Medium). Use adipose tissue adipocytes as the negative comparator (HPA: adipocytes, Not detected); on the placenta slide, compare neighboring non-cytotrophoblast cells with the stained compartment, without assuming those other cells are DUSP9-negative (HPA: placental result specifies cytotrophoblasts only).
Positive control tissue: Placenta (Cytotrophoblasts, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DUSP9 in Hep-G2, PC-3, U2OS, with annotated localisation: Endoplasmic reticulum (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host-species- and immunoglobulin-class-matched isotype control for a monoclonal primary, or matched nonimmune IgG for a polyclonal primary (standard IHC practice); peptide blocking is a biological specificity check shown for the selected antibody in paraffin-embedded human liver carcinoma tissue (A07919 caption). For chromogenic detection in placenta, quench endogenous peroxidase and check endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the exact A07919 paraffin-section caption leaves the fixative unreported (A07919 caption). Antigen-retrieval dependence is unreported; optimize retrieval on the paraffin sections during IHC setup (standard IHC practice). The evidence does not establish that frozen sections or IF are easier; for placental chromogenic IHC, control blood-associated endogenous peroxidase background (HPA: placenta cytotrophoblasts, Medium; standard IHC practice).

HPA tissue IHC evidence for DUSP9

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Placenta Cytotrophoblasts Medium Protein (IHC) HPA →
Testis Elongated or late spermatids Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced DUSP9 IHC Tips

Troubleshoot DUSP9 staining in paraffin sections using compartment, tissue pattern, and peptide-block controls (UniProt Q99956; HPA tissue IHC; catalog caption A07919).

How should I retrieve DUSP9 antigen when cytoplasmic staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page antigen-retrieval rule). Allow sections to cool in buffer before washing, and keep heating and cooling consistent across comparison slides (standard IHC practice). If staining remains weak, compare a shorter retrieval time with the page setting on adjacent sections, changing only that variable (standard IHC practice). Use placenta cytotrophoblast staining as a positive tissue reference, while recognizing its reported signal is medium rather than uniformly strong (HPA tissue IHC). Evaluate cytoplasmic signal and tissue preservation together; excessive heating can make apparent gains in staining difficult to interpret (standard IHC practice; UniProt Q99956 localization).
Could fixation explain weak or patchy DUSP9 staining in paraffin sections?
Target-specific DUSP9 sensitivity to fixation is unknown because the selected antibody caption identifies paraffin-embedded tissue but does not state a fixative (catalog caption A07919). Record the actual fixative, fixation duration, section thickness, and time between cutting and staining for each specimen (standard IHC practice). For a suspected fixation effect, compare similarly processed adjacent sections using the same citrate pH 6.0, 95–98 °C, 20 min retrieval and identical detection conditions (page antigen-retrieval rule; standard IHC practice). Include a reference section with medium cytotrophoblast staining to help distinguish a run-wide failure from specimen variation (HPA tissue IHC; standard IHC practice). Avoid assigning a DUSP9-specific fixation mechanism from staining differences alone (catalog caption A07919).
Where should convincing DUSP9 staining appear within cells?
Expect predominantly cytoplasmic chromogenic staining when judging tissue sections (UniProt Q99956 localization; HPA tissue IHC). An endoplasmic reticulum-associated pattern is also biologically plausible, although that finer localization comes from subcellular IF evidence rather than this paraffin-section assay (HPA subcellular). DUSP9 has no transmembrane segment or signal peptide, so crisp cell-surface-only staining warrants closer control review (UniProt Q99956 topology and processing). Compare the suspect pattern with cytotrophoblasts in placenta, which show medium tissue staining, and with adipocytes in adipose tissue, where staining was not detected (HPA tissue IHC). Judge compartment and cell identity before increasing chromogen development time, since longer development can obscure a diffuse cytoplasmic pattern (standard IHC practice).
Can an isoform or epitope effect explain discrepant DUSP9 staining?
The supplied record lists 0 isoforms and a single 1–384 chain, so an annotated alternative isoform does not explain discordant staining (UniProt Q99956 isoforms and processing). DUSP9 contains a rhodanese domain at residues 18–139 and a phosphatase domain at 203–346; its listed phosphoserines include positions 16, 262, and 351 (UniProt Q99956 domains and modified residues). The catalog caption does not identify the antibody epitope, so none of those positions establishes epitope accessibility or phosphorylation sensitivity (catalog caption A07919). Compare staining with and without the synthesized-peptide block shown for this exact antibody, using matching paraffin sections and detection settings (catalog caption A07919; standard IHC practice). Interpret peptide competition alongside cell localization and tissue controls rather than as proof of a particular epitope (standard IHC practice).
How can IF help assess ambiguous chromogenic DUSP9 staining?
Use IF as a separate localization check, pairing DUSP9 with a validated marker for the cell type under study; placental cytotrophoblasts are a supported positive tissue reference (HPA tissue IHC; standard IF practice). Select a fluorophore channel with low tissue autofluorescence and acquire an unstained control in every channel before setting exposure (standard IF practice). Because DUSP9 lacks a transmembrane segment and is reported as cytoplasmic, choose permeabilisation appropriate for an intracellular epitope, then verify that the antibody and marker patterns remain intact (UniProt Q99956 topology and localization; standard IF practice). HPA reports an approved endoplasmic reticulum localization from subcellular imaging, which can guide pattern review without establishing performance of the catalog antibody in IF (HPA subcellular; catalog caption A07919). Keep IF conclusions separate from chromogenic intensity scores (standard IF and IHC practice).
What controls distinguish DUSP9 signal from chromogenic background?
Run a no-primary section to reveal detection-system and tissue-associated background, and include the synthesized-peptide-block condition documented for the selected antibody (standard IHC practice; catalog caption A07919). Quench endogenous peroxidase before HRP-based chromogenic detection, for example with 3% hydrogen peroxide for 10 min, then check a no-primary control (standard IHC practice). Block nonspecific binding with a compatible protein block and keep wash times, antibody incubation, and DAB development matched across slides (standard IHC practice). Adipocytes in adipose tissue provide a reported not-detected comparison, while placental cytotrophoblasts provide a medium-signal comparison (HPA tissue IHC). Treat diffuse edge staining or signal confined to damaged regions as suspect until controls and intact tissue agree (standard IHC practice).
How should I quantify DUSP9 across paraffin tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score cytoplasmic DUSP9 within a prespecified cell population and tissue region, using an H-score based on intensity and percentage of positive cells (UniProt Q99956 localization; standard IHC practice). For an H-score, record percentages at intensities 0–3 and sum each percentage multiplied by its intensity, yielding 0–300 (standard IHC practice). Alternatively, report percentage positive cells, or positive-cell density per mm² when comparing regions with different cellularity (standard IHC practice). Normalize to eligible intact cells or measured viable tissue area, and use the same positivity threshold and DAB development across slides (standard IHC practice). Keep placental cytotrophoblast and not-detected adipocyte reference sections in the scoring review (HPA tissue IHC; standard IHC practice).
When is a DUSP9-positive IHC result credible?
A credible result shows cellular cytoplasmic signal in intact tissue and behaves consistently across positive, negative, and peptide-block controls (UniProt Q99956 localization; HPA tissue IHC; catalog caption A07919; standard IHC practice). Placental cytotrophoblasts have reported medium staining, whereas adipocytes in adipose tissue were not detected; kidney distal tubules have low reported signal (HPA tissue IHC). Predominantly nuclear or cell-surface-only staining deserves scrutiny because the supplied protein record places DUSP9 in the cytoplasm and lists no transmembrane segment (UniProt Q99956 localization and topology). Exclude section edges, necrotic areas, and endogenous peroxidase signal before assigning positivity (standard IHC practice). Interpret any liver carcinoma staining in light of the selected antibody's paraffin-tissue image and peptide-block control, without assuming its unstated fixative (catalog caption A07919).
Boster reagents

Best DUSP9 / Dual specificity protein phosphatase 9 IHC Antibodies

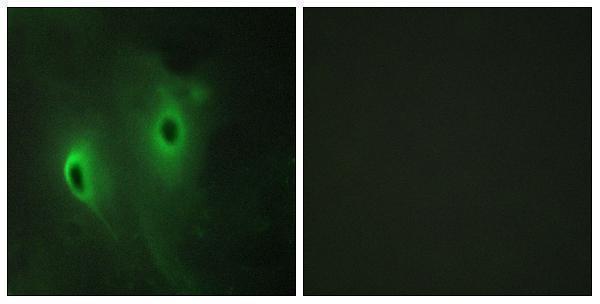
Both anti-DUSP9 antibodies have paraffin-embedded tissue IHC images (catalog IHC image captions). A07919 also has a HeLa-cell IF image (catalog IF image caption); both list human, mouse and rat reactivity (catalog reactivity).

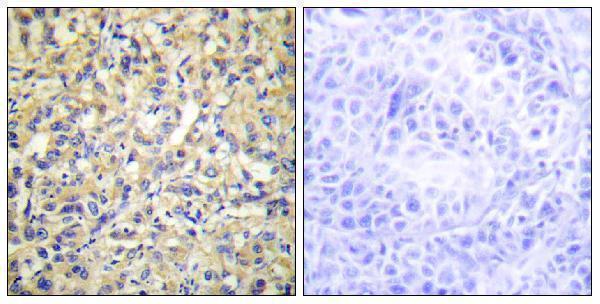
Real IHC data Immunohistochemistry analysis of paraffin-embedded human liver carcinoma tissue, using DUSP9 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-MKP-4 DUSP9 Antibody
Cat # A07919
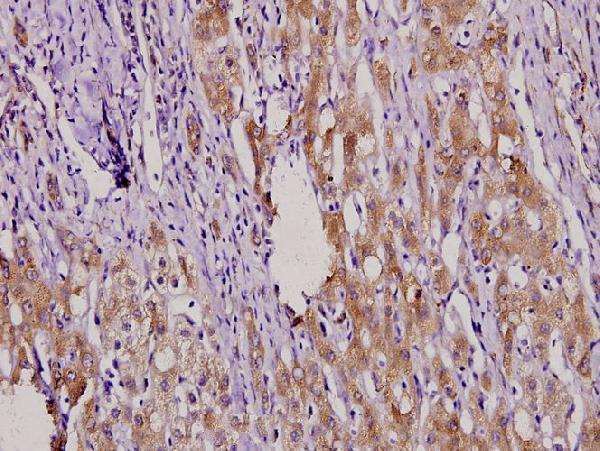
Real IHC data Immunohistochemistry (IHC) analyzes of MKP-4 (A174) pAb in paraffin-embedded liver cancer tissue at 1:100.
Anti-MKP-4 (A174) DUSP9 Antibody
Cat # A07919-1

A07919 shows IHC in paraffin-embedded human liver carcinoma tissue and IF in HeLa cells, each with a peptide-blocked comparator (catalog IHC/IF image captions). A07919-1 shows IHC in paraffin-embedded liver cancer tissue at 1:100; it lists IF as an application but has no IF image (catalog IHC image caption; catalog applications and IF image alts).

Which to pick: For tissue IHC, choose A07919 if the peptide-blocked comparator is useful; A07919-1 provides a paraffin-embedded tissue example at 1:100 (each SKU’s IHC image caption). For IF/ICC, choose A07919 for its HeLa-cell IF image; A07919-1 lists IF without an IF image (catalog IF image alts; catalog applications). Both are rabbit antibodies (catalog host), A07919 is listed as polyclonal (catalog dilution data), and both list human, mouse and rat reactivity (catalog reactivity); either is a cross-species candidate, but neither IHC caption establishes mouse or rat tissue performance or reports the fixative (catalog IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q99956 (DUS9_HUMAN, Dual specificity protein phosphatase 9).
  2. Human Protein Atlas. DUSP9 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. DUSP9 subcellular location (ICC-IF): Mainly localized to the endoplasmic reticulum..
  4. Human Protein Atlas. DUSP9 antibody validation summary (1 antibodies).
  5. Identifying specific TLS-associated genes as potential biomarkers for predicting prognosis and evaluating the efficacy of immunotherapy in soft tissue sarcoma. Frontiers in immunology 2024 — PMC11076739.
  6. Dual-Specificity Phosphatase 9 Protects Against Nonalcoholic Fatty Liver Disease in Mice Through ASK1 Suppression. Hepatology (Baltimore, Md.) 2019 — PMC6590435.
  7. Downregulation of DUSP9 Promotes Tumor Progression and Contributes to Poor Prognosis in Human Colorectal Cancer. Frontiers in oncology 2020 — PMC7538709.
  8. Expression of Dual-Specificity Phosphatase 9 in Placenta and Its Relationship with Gestational Diabetes Mellitus. Journal of diabetes research 2019 — PMC6854249.
  9. PubMed PMID:9030581 — UniProt-cited evidence.
  10. PubMed PMID:15772651 — UniProt-cited evidence.
  11. PubMed PMID:18669648 — UniProt-cited evidence.