E2F1 / Transcription factor E2F1 · IHC design guide

Design Immunohistochemistry for E2F1

Plan E2F1 chromogenic IHC around the nuclear staining reported in most tissues (HPA tissue IHC). Bone marrow hematopoietic cells show high staining, while kidney glomerular cells are reported as not detected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for E2F1 (IHC for E2F1): expected localisation Nuclear in most tissues (HPA tissue IHC), antibody M00257-1, validated IHC image, and IHC protocol steps
Printable E2F1 IHC protocol sheet — expected localisation Nuclear in most tissues (HPA tissue IHC), antibody M00257-1, controls and protocol steps. Open the full E2F1 IHC guide →

E2F1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear in most tissues (HPA tissue IHC)
Staining pattern Nuclear staining across most tissues (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Kidney+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat IHC staining and RNA show medium consistency (HPA tissue IHC)
Regulation Cell-cycle RB1 binding; abundance unknown (UniProt)
Isoform / epitope No annotated isoforms or processing; epitope unknown (UniProt)
Section 1

Recommended E2F1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by two published E2F1 immunohistochemistry protocols (PMC5362443; PMC11136682).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet M00257-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-E2F1, 1:200-1:1000 (datasheet M00257-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultE2F1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 retrieval at 95–98 °C for 20 min because E2F1 is nuclear (page retrieval rule; UniProt Q01094).
Section 2

What Is the Expected E2F1 Staining Pattern?

E2F1 is a nuclear transcription factor with no transmembrane segment (UniProt Q01094). In paraffin-section IHC, expect nuclear staining in most tissues (HPA: tissue IHC, Enhanced reliability; medium consistency with RNA). Interpret staining by cell type: HPA reports High staining in bone-marrow hematopoietic cells, colon glandular cells and esophageal squamous epithelial cells, but Not detected in kidney glomerular cells, pancreatic exocrine glandular cells and skeletal-muscle myocytes (HPA: tissue IHC).

What am I looking at on my slide?
Distinct chromogenic signal is concentrated in nuclei of bone-marrow hematopoietic cells or colon glandular cells (HPA: High in both cell types).This fits the expected E2F1 compartment and a documented positive cell population (UniProt Q01094: nucleus; HPA: nuclear expression in most tissues). Compare nuclei with the counterstain, and assess the named cells rather than assigning one score to the entire section (general IHC practice).
Signal is mainly cytoplasmic, membranous or extracellular, with little nuclear staining.That distribution conflicts with E2F1's nuclear annotation and the HPA tissue pattern (UniProt Q01094: nucleus, no transmembrane segment; HPA: nuclear expression in most tissues). Treat it as suspect; review morphology, antibody specificity and detection background before counting it as E2F1 (general IHC practice).
Strong staining appears in glomerular cells, pancreatic exocrine glandular cells or skeletal-muscle myocytes (HPA: Not detected in these cells).The result conflicts with the named HPA cell-level observations, though it does not establish that the whole tissue must be negative (HPA: tissue IHC). Consider nonspecific antibody binding or endogenous chromogenic activity; inspect the appropriate negative controls and adjacent cell types (general IHC practice).
Broad haze or precipitate covers nuclei and surrounding tissue, obscuring cell boundaries.A diffuse deposit cannot be scored confidently as nuclear E2F1 (UniProt Q01094: nucleus; HPA: nuclear tissue pattern). Uneven reagent coverage, insufficient washing or detection background can produce this appearance; compare the negative control and review the staining workflow (general IHC practice).
No nuclear signal is visible in a documented positive population, such as appendix lymphoid tissue (HPA: High).A blank expected-positive population leaves the assay result uninterpretable for that run (HPA: High in appendix lymphoid tissue; general IHC practice). Check that the named cells are present, then assess control staining and the primary-antibody and detection steps before interpreting other cells as negative (general IHC practice).
💡Expected E2F1 appearanceCall a positive result when distinct nuclear chromogen marks the relevant cells, with strong staining plausible in HPA High populations such as bone-marrow hematopoietic cells; predominantly cytoplasmic staining or diffuse deposit alone is suspect (HPA: tissue IHC; UniProt Q01094: nucleus).
How each factor affects the staining
Cell-level reference pattern (HPA: tissue IHC)HPA's High and Not detected labels apply to specified cells: colon glandular cells are High, while kidney glomerular cells are Not detected (HPA: tissue IHC). Select and score reference populations by cell identity; do not convert either observation into a claim about every cell in that organ (general IHC practice).
Evidence and antibody validation (HPA: tissue IHC; HPA: antibodies)The overall tissue profile has Enhanced reliability with medium staining–RNA consistency (HPA: tissue IHC). Antibody CAB000329 is IHC Enhanced; HPA008003 and CAB019308 are IHC Approved (HPA: antibodies). Validation status informs confidence but does not verify an individual laboratory run (general IHC practice).
Expected compartment (UniProt Q01094; HPA: subcellular ICC-IF)UniProt annotates E2F1 in the nucleus; HPA ICC-IF supports nucleoplasm as the main location and lists centrosome as uncertain (UniProt Q01094; HPA: subcellular ICC-IF). For the separate IF/ICC guide, ask: where should signal localize? Mainly nucleoplasm; do not require a centrosome signal (HPA: subcellular ICC-IF).
Molecular context (UniProt Q01094)E2F1 is a 437-residue chain with no annotated signal peptide, propeptide or transmembrane segment (UniProt Q01094). Its annotated acetylation, methylation and phosphorylation sites establish modification, but the supplied record does not show how they affect paraffin-section staining or antigen retrieval (UniProt Q01094).
Cell-cycle context (UniProt Q01094)E2F1 functions with DP proteins in G1-to-S control and interacts with RB1 in a cell-cycle-dependent manner (UniProt Q01094). Nuclear stain identifies an observed pattern; intensity alone does not establish transcriptional activity or cell-cycle phase from the supplied evidence (UniProt Q01094; general IHC interpretation).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected-positive nuclei are blank, including bone-marrow hematopoietic cells (HPA: High).The intended cells may be absent from the examined area, or a primary-antibody or detection step may have failed (general IHC practice).Confirm the cells on the counterstain, inspect the positive control, and check the recorded antibody dilution, retrieval and detection steps against the validated IHC workflow (general IHC practice).
Only cytoplasm or cell borders stain.That pattern conflicts with nuclear E2F1 and may reflect nonspecific staining (UniProt Q01094: nucleus; HPA: nuclear tissue pattern; general IHC practice).Recheck nuclear morphology and the negative control; reassess primary-antibody dilution, blocking and washing within the validated IHC workflow (general IHC practice).
Pancreatic exocrine glandular cells stain strongly (HPA: Not detected).Possible explanations include nonspecific antibody binding or endogenous detection activity; the HPA observation alone cannot identify which occurred (HPA: tissue IHC; general IHC practice).Compare a no-primary control, inspect background in neighboring structures, and verify the detection system's endogenous-activity blocking step (general IHC practice).
Diffuse chromogen makes nuclei hard to distinguish.Excess detection background or incomplete washing can obscure the nuclear pattern (general IHC practice; UniProt Q01094: nucleus).Examine the negative control and review washing, blocking and chromogen development; score E2F1 only where nuclear boundaries remain clear (general IHC practice).
A reference tissue seems wholly negative despite an HPA High entry.The HPA entry may concern a cell population missing from the sampled area; for example, appendix High refers to lymphoid tissue (HPA: tissue IHC).Locate the specified population on the section before comparing staining; record cell-level findings and check the positive control if that population is present but blank (HPA: tissue IHC; general IHC practice).
ICC-IF shows nucleoplasmic signal but no centrosome spot.Nucleoplasm is HPA supported, whereas the additional centrosome location is uncertain (HPA: subcellular ICC-IF).Interpret nucleoplasmic localization in the separate IF/ICC guide; do not mark the result as failed solely because a centrosome spot is absent (HPA: subcellular ICC-IF).

Sample controls for E2F1 IHC & IF

🧪Run adrenal gland first; its glandular cells must show E2F1 staining (HPA: High in adrenal gland glandular cells). Use skeletal muscle myocytes as the negative tissue (HPA: Not detected in skeletal muscle myocytes); on the positive slide, unstained neighboring nuclei provide an internal background reference, without assuming a specific neighboring cell type is E2F1-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Kidney (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show E2F1 in CACO-2, Rh30, U2OS, A-431, U-251MG, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a nonimmune IgG control matched to the primary antibody’s host species and immunoglobulin class; use an E2F1 knockout sample as a biological specificity control. For chromogenic staining, block endogenous peroxidase and assess residual background on the adrenal section.
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected M00257-1 mouse-pancreas caption does not state its fixative (selected-SKU tissue-IHC caption). Antigen-retrieval dependence is unreported, so optimize retrieval empirically for paraffin sections; the supplied evidence does not establish whether frozen sections or IF would be easier. Score nuclear staining (UniProt Q01094: Nucleus), and check adrenal sections for residual endogenous-peroxidase staining.

HPA tissue IHC evidence for E2F1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Lymphoid tissue High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Kidney Cells in glomeruli Not detected Protein (IHC) HPA →
Pancreas Exocrine glandular cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced E2F1 IHC Tips

Troubleshoot E2F1 chromogenic IHC by checking nuclear localisation, tissue context and controls before changing the staining workflow.

How should I retrieve E2F1 in paraffin sections when nuclear staining is weak?
Use Tris-EDTA at pH 9.0 for heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval setting). Allow sections to cool in retrieval buffer, then compare a stained section with a primary-antibody omission control processed through the same heating and detection steps (standard IHC practice). Score nuclear signal in a suitable reference compartment, such as bone marrow hematopoietic cells, rather than judging retrieval from diffuse tissue colour (HPA: high in bone marrow hematopoietic cells; UniProt Q01094: nucleus). If signal remains weak, adjust heating within the validated tissue workflow and inspect morphology before considering a different retrieval buffer (standard IHC practice).
Could fixation explain weak or uneven E2F1 nuclear staining?
Target-specific fixation sensitivity is unknown from the supplied evidence; the selected M00257-1 mouse-pancreas IHC caption does not state a fixative (selected IHC caption: fixative not stated). Record fixation conditions and compare sections processed together before assigning a weak signal to E2F1 epitope loss (standard IHC practice). Check whether nuclear morphology is preserved and whether staining varies with section thickness or tissue edges, which can affect interpretation of chromogenic IHC (standard IHC practice). Do not infer fixation tolerance from the reported tissue staining pattern or E2F1 modifications, since neither is a direct fixation experiment (HPA: tissue IHC profile; UniProt Q01094: modified residues).
What localisation should count as convincing E2F1 staining?
Prioritise a nuclear chromogenic signal with identifiable nuclei, because E2F1 is annotated as nuclear and tissue IHC shows nuclear expression in most tissues (UniProt Q01094: nucleus; HPA: tissue IHC profile). Nucleoplasmic localisation has supporting subcellular evidence, while an additional centrosome location is uncertain and should not define a positive IHC score (HPA: subcellular localisation). Compare nuclear staining with the counterstain and score cells within their anatomical compartment, rather than treating diffuse cytoplasmic colour as equivalent target signal (standard IHC practice). If colour obscures nuclear boundaries, reduce detection development or antibody concentration using paired sections and unchanged controls (standard chromogenic IHC practice).
How can epitope selection affect an unexpected E2F1 IHC pattern?
Check the catalog antibody's stated immunogen or epitope against the 1–437 E2F1 chain before interpreting a changed staining pattern (UniProt Q01094: chain 1–437). The supplied record annotates 0 isoforms, so it provides no basis for assigning separate nuclear patterns to documented E2F1 isoforms (UniProt Q01094: isoforms 0). Acetylation at residues 117, 120 and 125, methylation at 185, and phosphorylation at 364 are annotated modifications; their effect on this antibody's binding is untested here (UniProt Q01094: modified residues). Compare retrieval conditions and an appropriate nuclear reference while keeping detection settings matched, and avoid attributing a staining change to any one modification without epitope-specific evidence (standard IHC practice).
How should I check E2F1 localisation in a parallel IF experiment?
Use IF as a parallel localisation check, with E2F1 evaluated against a nuclear counterstain because its principal localisation is nucleoplasmic (HPA: supported nucleoplasm). In bone marrow, multiplex with a validated hematopoietic-cell marker to identify the expected cell population; hematopoietic cells show high tissue IHC staining (HPA: bone marrow hematopoietic cells, high). Choose a spectrally separated fluorophore, preferably a far-red channel if the specimen has strong shorter-wavelength autofluorescence, and include single-colour controls (standard IF practice). Because E2F1 is nuclear and has no transmembrane segment, permeabilise the cell and nuclear barriers for antibody access, then optimise detergent exposure against preserved nuclear morphology (UniProt Q01094: nucleus and topology; standard IF practice).
What causes diffuse brown staining when E2F1 nuclei are unclear?
First compare the stained section with primary-antibody omission and detection-only controls to locate signal arising from the chromogenic workflow (standard IHC practice). Quench endogenous peroxidase before HRP and DAB detection, and assess whether excess DAB development or concentrated antibody masks the expected nuclear pattern (standard chromogenic IHC practice; UniProt Q01094: nucleus). Examine a weak-expression compartment, such as pancreatic exocrine glandular cells, alongside a high-expression reference under matched settings (HPA: pancreatic exocrine cells not detected; bone marrow hematopoietic cells high). Treat staining that follows tissue edges, damaged areas or the omission control as background until nuclear, compartment-specific signal survives those comparisons (standard IHC practice).
How should I quantify E2F1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical compartment and count only evaluable nuclei before calculating the percentage of E2F1-positive cells or a nuclear H-score (standard IHC scoring practice; UniProt Q01094: nucleus). For an H-score, multiply the percentage of nuclei at each intensity 0–3 by that intensity and sum the products, giving a 0–300 range (standard IHC scoring practice). Normalise positive counts to the number of evaluable cells in each compartment, or report positive nuclei per mm² when area is the denominator (standard IHC scoring practice). Keep retrieval, counterstain, imaging and scoring thresholds consistent across sections, and report compartments separately because HPA staining levels vary by cell population (standard IHC practice; HPA: tissue IHC profile).
When is an apparent E2F1-positive cell likely to be artefactual?
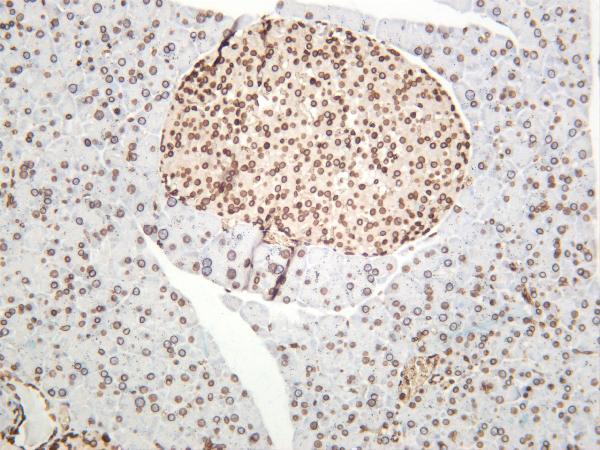
A credible positive has colour confined mainly to an intact nucleus in an identified cell, consistent with E2F1's nuclear annotation and the tissue IHC profile (UniProt Q01094: nucleus; HPA: nuclear expression in most tissues). Recheck apparent staining in pancreatic exocrine glandular cells against controls, since HPA reports that population as not detected despite a separate mouse-pancreas antibody image (HPA: pancreatic exocrine cells not detected; selected IHC caption: mouse pancreas). Exclude necrotic areas, section edges and diffuse cytoplasmic colour from positive-cell scoring when morphology or controls indicate artefact (standard IHC practice). Signal persisting in an omission control may reflect endogenous enzyme activity or detection background, so resolve that source before drawing a biological conclusion (standard chromogenic IHC practice).
Boster reagents

Best E2F1 / Transcription factor E2F1 IHC Antibodies

Anti-E2F1 antibodies list human, mouse and rat reactivity (catalog entries). IHC images show pancreas and paraffin-embedded ovary carcinoma; IF images show HeLa cells (catalog image captions).

Real IHC data Mouse pancreas was stained with anti-E2F-1 rabbit antibody
Anti-E2F-1 Rabbit Monoclonal Antibody
Cat # M00257-1

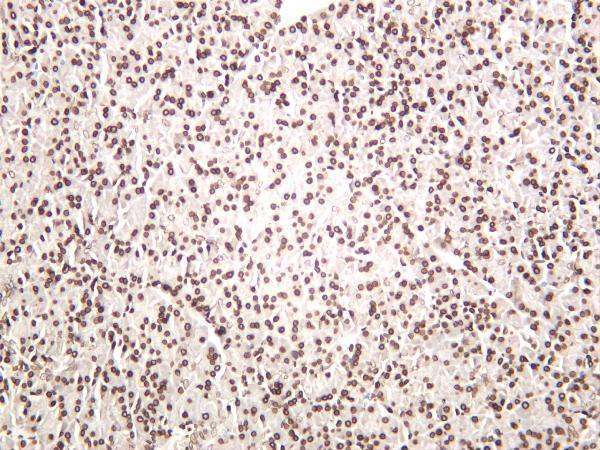
The rendered card is M00257-1, whose IHC images show mouse and rat pancreas (M00257-1 IHC image captions). M00257 is a separate catalog option with an IHC image of paraffin-embedded human ovary carcinoma and an IF image of HeLa cells (M00257 image captions; cards payload).

Which to pick: For tissue IHC, choose M00257-1 when the mouse or rat pancreas images match your sample (M00257-1 IHC image captions); M00257 has image evidence for paraffin-embedded human ovary carcinoma (M00257 IHC image caption). For IF/ICC, M00257 lists both applications and shows HeLa-cell IF, while M00257-1 lists IF but has no IF image in the payload (catalog applications and IF image captions). Both are rabbit monoclonals listed as reactive with human, mouse and rat (catalog entries); neither IHC caption reports a fixative (IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q01094 (E2F1_HUMAN, Transcription factor E2F1).
  2. Human Protein Atlas. E2F1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. E2F1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the centrosome..
  4. Human Protein Atlas. E2F1 antibody validation summary (4 antibodies).
  5. U2 small nuclear RNA auxiliary factor 2, transcriptionally activated by the transcription factor Dp-1/E2F transcription factor 1 complex, enhances the growth and aerobic glycolysis of leiomyosarcoma cells. Bioengineered 2022 — PMC9278431.
  6. Adenovirus E2F1 overexpression sensitizes LNCaP and PC3 prostate tumor cells to radiation in vivo. International journal of radiation oncology, biology, physics 2011 — PMC4299462.
  7. E2F-1 targets miR-519d to regulate the expression of the ras homolog gene family member C. Oncotarget 2017 — PMC5362443.
  8. CircMYBL2 facilitates hepatocellular carcinoma progression by regulating E2F1 expression. Oncology research 2024 — PMC11136682.
  9. PubMed PMID:1638634 — UniProt-cited evidence.
  10. PubMed PMID:1638635 — UniProt-cited evidence.
  11. PubMed PMID:1448092 — UniProt-cited evidence.