EDIL3 / EGF-like repeat and discoidin I-like domain-containing protein 3 · IHC design guide

Design Immunohistochemistry for EDIL3

Plan chromogenic EDIL3 IHC on paraffin sections with a 1:50 antibody starting dilution (datasheet A06273-1). Compare cytoplasmic and extracellular staining across tissues, including high staining in glial cells and kidney tubules (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EDIL3 (IHC for EDIL3): expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC), antibody A06273-1, validated IHC image, and IHC protocol steps
Printable EDIL3 IHC protocol sheet — expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC), antibody A06273-1, controls and protocol steps. Open the full EDIL3 IHC guide →

EDIL3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC)
Staining pattern Most tissues show cytoplasmic and extracellular staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06273-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Skeletal muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06273-1)
Caveat Secreted EDIL3 may stain away from its RNA source (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended EDIL3 IHC & IF Protocols

Use the catalog antibody’s IHC protocol alongside published paraffin-section protocols for endometrial cancer, breast and prostate cancer, and newborn mouse calvaria (PMC6806535; PMC7494865; PMC5705136).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human stomach cancer tissue; fixative not specified (datasheet A06273-1)
FixationImage fixative and duration unreported (datasheet A06273-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06273-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06273-1)
Primary antibodyRabbit anti-EDIL3, 1:50 recommended; image 2 μg/ml (datasheet A06273-1)
Primary incubationOvernight at 4 °C (datasheet A06273-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06273-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEDIL3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and extracellular expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A06273-1); the published protocols used different conditions where stated (PMC6806535; PMC7494865).
Section 2

What Is the Expected EDIL3 Staining Pattern?

EDIL3 is secreted and has no transmembrane segment (UniProt O43854 topology). In paraffin tissue, expect cytoplasmic and extracellular staining, including in glial cells, kidney tubular cells, and selected glandular or respiratory epithelial cells (HPA: tissue IHC). HPA rates the tissue staining Approved, with medium consistency between staining and RNA data; for a secreted protein, RNA and protein locations may differ (HPA: reliability description).

What am I looking at on my slide?
Cytoplasmic signal with adjacent extracellular staining in a documented positive cell population.This fits the broad tissue pattern (HPA: cytoplasmic and extracellular expression in most tissues). Assess the cell type and tissue together: HPA reports high staining in kidney tubular cells and glial cells in the caudate, cortex, and hippocampus (HPA: tissue IHC).
A sharply nuclear-only pattern or uniform membrane-only staining in paraffin tissue.Neither is the reported tissue IHC pattern (HPA: tissue profile). Treat it as a localization discrepancy and review controls and detection conditions (standard IHC practice). HPA's uncertain plasma-membrane assignment comes from ICC-IF and should not override the tissue IHC pattern (HPA: subcellular ICC-IF).
Strong staining in skeletal-muscle myocytes or another cell population outside the documented pattern.HPA reports skeletal-muscle myocytes as not detected (HPA: tissue IHC). Unexpected signal can reflect cross-reactivity or endogenous detection activity (standard IHC practice); it is not, by itself, proof of either. Compare staining with omission and detection controls (standard IHC practice).
A diffuse deposit across most of the section that obscures cell and extracellular boundaries.This is difficult to score against HPA's cytoplasmic and extracellular pattern (HPA: tissue profile). Check background in a no-primary control and review blocking, detection, and wash conditions (standard IHC practice) before calling the diffuse signal EDIL3.
No visible stain in a documented high-staining tissue after chromogenic detection.An absent signal in kidney tubular cells, adrenal glandular cells, or cerebral-cortex glial cells conflicts with the reported high tissue staining (HPA: tissue IHC). Check the positive control and assay steps first (standard IHC practice); one negative section cannot establish EDIL3 absence.
💡Expected EDIL3 appearanceCall positive a discernible cytoplasmic and extracellular signal in a documented positive cell population, potentially strong where HPA reports high staining (HPA: tissue IHC); isolated nuclear stain, indiscriminate deposit, or strong skeletal-myocyte staining warrants control review (HPA: tissue profile; standard IHC practice).
How each factor affects the staining
Compartment and secretionEDIL3 is secreted, with a signal peptide at residues 1–23 and a mature chain at 24–480 (UniProt O43854). Extracellular staining can therefore fit the tissue pattern (HPA: tissue profile); do not require every positive deposit to sit inside the producing cell.
Choice of comparison tissueHPA reports high staining in kidney tubular cells, adrenal and epididymal glandular cells, nasopharyngeal respiratory epithelium, and several brain cell populations; skeletal-muscle myocytes are not detected (HPA: tissue IHC). These are interpretation references, not universal assay guarantees.
Strength of validationHPA labels tissue IHC Approved and describes medium agreement between staining and RNA data (HPA: reliability). Its listed tissue-IHC antibody, HPA020415, is Approved; no Enhanced status is supplied (HPA: antibody validation). Interpret an unexpected pattern with controls rather than treating approval as absolute specificity.
Isoforms and epitope coverageUniProt lists two EDIL3 isoforms and extracellular EGF-like and F5/8 type C domains (UniProt O43854). The supplied record gives no antibody epitope or isoform-specific tissue pattern, so it cannot predict whether a given antibody distinguishes isoforms.
Antigen retrieval in paraffin sectionsNo EDIL3-specific retrieval condition or fixation sensitivity is supplied (UniProt O43854; HPA: supplied records). If optimizing retrieval, compare conditions with the same documented positive tissue and a no-primary control (standard IHC practice); do not infer a target-specific fixation effect.
IF/ICC Q&A: should a membrane signal match tissue IHC?HPA assigns plasma-membrane localization with uncertainty in ICC-IF images from U2OS and hTERT-RPE1 (HPA: subcellular ICC-IF). Tissue IHC instead reports cytoplasmic and extracellular staining (HPA: tissue profile). Use the separate IF/ICC guide for that application.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive tissue is blank.The section may have failed to produce detectable signal; a blank result alone does not identify which assay step failed (standard IHC practice).Confirm that a documented high-staining cell population is present (HPA: tissue IHC), then check primary application, retrieval, detection reagents, and a positive control (standard IHC practice).
The whole section has brown haze.Background from blocking, detection chemistry, or incomplete washing can obscure a localized pattern (standard IHC practice).Run a no-primary control, review blocking and washes, and reduce detection background before scoring (standard IHC practice). Compare any remaining signal with HPA's cytoplasmic/extracellular pattern (HPA: tissue profile).
Skeletal-muscle myocytes stain strongly.They are reported as not detected (HPA: skeletal-muscle tissue IHC); cross-reactivity or endogenous detection activity is possible (standard IHC practice).Check no-primary and detection controls and repeat with appropriate background control (standard IHC practice). Treat persistent staining as discrepant with the HPA reference, not automatic confirmation of EDIL3 (HPA: tissue IHC).
Only nuclei are stained.Nuclear-only staining does not match the reported cytoplasmic and extracellular tissue distribution (HPA: tissue profile).Review the no-primary control and chromogen background, then reassess localization in a documented positive tissue (standard IHC practice; HPA: tissue IHC).
Extracellular stain appears away from cells with high RNA expression.EDIL3 is secreted (UniProt O43854), and HPA cautions that RNA and protein locations may differ for secreted proteins (HPA: reliability description).Score extracellular signal with tissue structure and controls rather than requiring RNA and protein to coincide cell by cell (HPA: tissue profile; standard IHC practice).
A membrane-only result is used to call paraffin IHC positive.The membrane assignment is uncertain and comes from ICC-IF, while tissue IHC describes cytoplasmic and extracellular expression (HPA: subcellular ICC-IF; tissue profile).Recheck the tissue IHC compartment and positive-cell pattern against the HPA tissue reference; evaluate IF/ICC observations under the separate guide (HPA: tissue IHC; subcellular ICC-IF).

Sample controls for EDIL3 IHC & IF

🧪Run adrenal gland first; its glandular cells should stain for EDIL3 (HPA: High in adrenal gland glandular cells). Use skeletal muscle myocytes as the negative tissue (HPA: Not detected in skeletal muscle myocytes), and assess cells outside the annotated glandular compartment on the positive slide for background rather than assuming they are EDIL3-negative (HPA: High in glandular cells).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Skeletal muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EDIL3 in U2OS, hTERT-RPE1, with annotated localisation: Plasma membrane (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a rabbit IgG control matched to the primary antibody’s class and clonality where applicable; and EDIL3 knockout tissue if available (caption: rabbit anti-EDIL3 primary; standard IHC practice). Block endogenous peroxidase and compare any brown adrenal pigment with the no-primary slide before scoring DAB staining (HPA: adrenal gland positive; standard IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected A06273-1 paraffin-section caption does not report a fixative (selected-SKU tissue-IHC caption). Heat retrieval in EDTA at pH 8.0 is documented for a stomach cancer section, but a retrieval requirement for adrenal gland is unreported (selected-SKU tissue-IHC caption). Paraffin IHC has a documented example, while the supplied evidence does not establish that frozen sections or IF are easier; brown adrenal pigment may complicate DAB scoring (selected-SKU tissue-IHC caption; standard IHC practice).

HPA tissue IHC evidence for EDIL3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Secreted protein, tissue location of RNA and protein is expected to differ.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced EDIL3 IHC Tips

Troubleshoot EDIL3 staining in paraffin sections by checking retrieval, compartment, controls and scoring before interpreting chromogenic signal.

Which retrieval condition should I start with for EDIL3 IHC?
Start with heat-mediated EDTA retrieval at pH 8.0 for paraffin-section EDIL3 IHC (datasheet A06273-1). The selected human stomach cancer image used this condition, but its caption does not report heating time or temperature (datasheet A06273-1). Establish those settings with a short retrieval-time series on adjacent sections, keeping antibody concentration and detection conditions constant. Include a kidney tubule reference section, where staining is reported as high, to distinguish weak retrieval from a low-expressing specimen (HPA: High in kidney tubule cells). If signal remains weak, assess another retrieval buffer only as a documented fallback, and compare morphology and background alongside staining.
How should I troubleshoot fixation-related loss of EDIL3 staining?
Target-specific fixation sensitivity is unknown: the selected EDIL3 tissue image identifies a paraffin section but does not state its fixative (datasheet A06273-1). Record fixative, fixation duration, tissue thickness and processing history for each block before attributing a negative result to EDIL3 biology. For new specimens, use a consistent routine fixation and processing workflow, then compare adjacent sections under the same retrieval and detection conditions. If an older block stains poorly, compare it with a recently processed reference section that stains strongly in the same run. Do not infer a preferred fixative from tissue staining patterns or EDIL3 sequence features.
Where should EDIL3 signal appear in tissue sections?
Assess both cellular and extracellular compartments: EDIL3 is annotated as secreted, and tissue staining is described as cytoplasmic and extracellular in most tissues (UniProt O43854: secreted; HPA: tissue IHC profile). A rim near cells can be plausible, but plasma-membrane localisation remains uncertain in subcellular imaging (HPA: plasma membrane, uncertain). Annotate vessel-associated matrix, glandular cells and other structures separately rather than treating all brown pixels as equivalent. Compare the pattern across serial sections and with a no-primary control to identify tissue pigment or detection background. A purely nuclear pattern needs independent confirmation before it is called EDIL3, given the reported localisation (UniProt O43854: secreted; HPA: tissue IHC profile).
Could isoforms or epitope masking explain inconsistent EDIL3 staining?
EDIL3 has 2 annotated isoforms, but the supplied antibody caption does not identify its immunogen or establish isoform recognition (UniProt O43854: isoforms 1 and 2; datasheet A06273-1). The precursor contains a signal peptide at residues 1–23 and a mature chain at 24–480 (UniProt O43854: processing). It also has annotated glycosylation sites at 73, 88 and 140, so epitope accessibility is worth testing empirically (UniProt O43854: glycosylation). Compare retrieval conditions on adjacent sections and, if available, use an antibody with a documented nonoverlapping epitope. Do not assign an isoform from staining alone without epitope mapping and an orthogonal measurement.
How should I adapt the EDIL3 localisation check for tissue immunofluorescence?
Use a separate IF optimisation, since the selected A06273-1 image documents chromogenic staining in a paraffin section, with no tissue IF conditions supplied (datasheet A06273-1). Multiplex EDIL3 with a validated marker for the cell population under study; glial cells or kidney tubule cells are reported high-staining examples (HPA: High in glial cells and kidney tubule cells). Select a fluorophore channel with low tissue autofluorescence and image unstained and single-label controls before interpreting overlap. If the mapped epitope is extracellular, first assess staining without permeabilisation; for an intracellular epitope, optimise mild permeabilisation on matched sections. Report extracellular deposits separately from cellular overlap because EDIL3 is secreted (UniProt O43854: secreted).
How can I reduce diffuse brown background without erasing EDIL3 signal?
The selected tissue image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and peroxidase-based DAB detection (datasheet A06273-1). Use those as documented starting conditions, then titrate primary antibody and wash stringency on adjacent sections if diffuse signal persists. Include a no-primary section and a routine endogenous-peroxidase block to separate reagent background from true chromogen deposition. Check section edges, folds and necrotic regions before changing antibody concentration, since those areas can trap reagents or stain unevenly. Preserve extracellular staining during optimisation because EDIL3 is secreted and HPA reports extracellular tissue expression (UniProt O43854: secreted; HPA: tissue IHC profile).
What scoring method captures both cellular and extracellular EDIL3 staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the analysis compartment before scoring, because EDIL3 is secreted and tissue staining is reported in cytoplasmic and extracellular locations (UniProt O43854: secreted; HPA: tissue IHC profile). For a defined cell population, record percent positive cells and an H-score using prespecified intensity categories of 0–3. For extracellular deposits, report positive area or signal density per mm² of viable tissue rather than forcing deposits into a cell-based score. Normalise cellular counts to the number of eligible cells and extracellular measurements to annotated viable area, excluding folds and necrosis. Apply one threshold and one compartment mask across the batch, with reference sections and background controls reviewed together.
How do I distinguish convincing EDIL3 staining from artefact?
A convincing result shows reproducible cellular or extracellular staining with appropriate negative controls; EDIL3 is secreted and HPA reports cytoplasmic and extracellular tissue expression (UniProt O43854: secreted; HPA: tissue IHC profile). Use reported high-staining kidney tubule cells or glial cells as reference patterns, while recognising that HPA calls myocytes in skeletal muscle not detected (HPA: tissue IHC). Treat isolated nuclear signal, abrupt section-edge staining and staining confined to necrosis as reasons to investigate artefact, not as proof of expression. A no-primary control helps reveal endogenous enzyme or detection-system signal. Interpret apparent membrane rims cautiously because the reported plasma-membrane assignment is uncertain (HPA: plasma membrane, uncertain).
Boster reagents

Best EDIL3 / EGF-like repeat and discoidin I-like domain-containing protein 3 IHC Antibodies

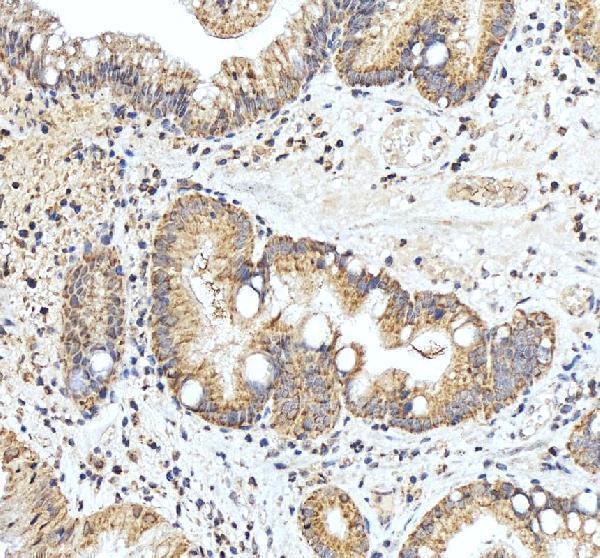
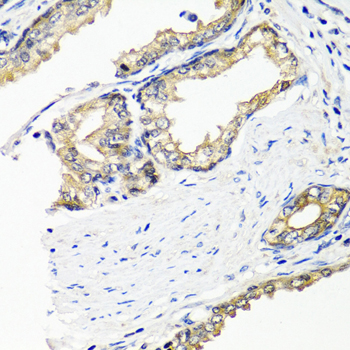
Real IHC images show EDIL3 staining in paraffin-embedded human stomach and stomach cancer sections (A06273 and A06273-1 image captions); both antibodies list human and mouse reactivity, and A06273-1 also lists rat reactivity and IF/ICC applications (catalog).

Real IHC data IHC analysis of EDIL3 using anti-EDIL3 antibody (A06273-1). EDIL3 was detected in a paraffin-embedded section of human stomach cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-EDIL3 Antibody (A06273-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-EDIL3 Antibody
Cat # A06273-1
Real IHC data Immunohistochemistry of paraffin-embedded human stomach using EDIL3 antibody at dilution of 1:100 .Perform microwave antigen retrieval with 10 mM PBS buffer pH 7.2 before commencing with IHC staining protocol.
Anti-EDIL3 Antibody
Cat # A06273

A06273 will render with IHC of paraffin-embedded human stomach at 1:100 after microwave retrieval in PBS, pH 7.2 (A06273 image caption). A06273-1 will render with IHC of a paraffin-embedded human stomach cancer section after heat retrieval in EDTA, pH 8.0 (A06273-1 image caption).

Which to pick: For tissue IHC, either SKU has its own paraffin-section image; choose A06273 for the depicted human stomach protocol or A06273-1 for the depicted human stomach cancer protocol (A06273 and A06273-1 image captions). Choose A06273-1 for IF/ICC or planned rat samples because it is listed as polyclonal, includes IF/ICC applications, and lists human, mouse and rat reactivity; A06273 lists IHC and human/mouse reactivity (catalog). The fixative is unreported for both depicted sections (A06273 and A06273-1 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O43854 (EDIL3_HUMAN, EGF-like repeat and discoidin I-like domain-containing protein 3).
  2. Human Protein Atlas. EDIL3 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. EDIL3 subcellular location (ICC-IF): Localized to the plasma membrane..
  4. Human Protein Atlas. EDIL3 antibody validation summary (2 antibodies).
  5. Prognostic Significance of EDIL3 Expression and Correlation with Mesenchymal Phenotype and Microvessel Density in Lung Adenocarcinoma. Scientific reports 2017 — PMC5561239.
  6. Evaluation of Changes in the Expression Pattern of EDIL3 in Different Grades of Endometrial Cancer. Current pharmaceutical biotechnology 2019 — PMC6806535.
  7. EDIL3 promotes epithelial-mesenchymal transition and paclitaxel resistance through its interaction with integrin α(V)β(3) in cancer cells. Cell death discovery 2020 — PMC7494865.
  8. The extracellular matrix protein Edil3 stimulates osteoblast differentiation through the integrin α5β1/ERK/Runx2 pathway. PloS one 2017 — PMC5705136.
  9. PubMed PMID:9420328 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.