This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic EFNA5 IHC in paraffin sections using the IHC-validated antibody at 1:50–1:200 as a starting range (datasheet: A06229). Compare staining in neuronal or glandular cells with HPA tissues where EFNA5 was not detected (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Membranous and cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Neuronal and glandular cells show membranous and cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Caudate+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep formalin fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | ADAM10 can shed the extracellular domain, altering surface signal (UniProt) | |
| Regulation | Expression regulation is not annotated (UniProt) | |
| Isoform / epitope | No isoforms annotated; mature chain excludes propeptide 204–228 (UniProt) |
The catalog antibody’s IHC protocol is accompanied by published EFNA5 protocols for mouse retina, hepatoma tissue arrays, and renal carcinoma arrays (PMC7569469; PMC11489415; PMC8870418).
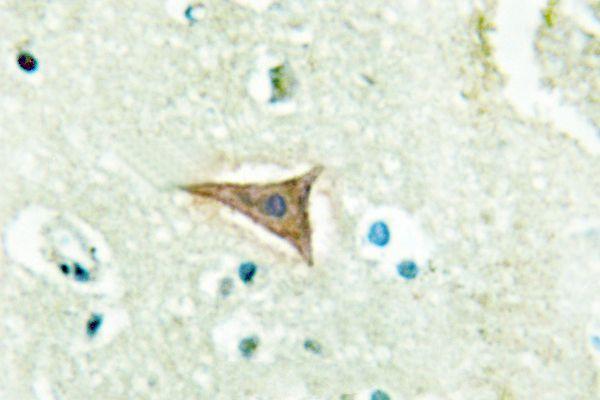
| Sample | Paraffin-embedded human brain tissue; fixative not specified (datasheet A06229) |
| Fixation | Image fixative and duration unreported (datasheet A06229); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-EFNA5, 1:50-1:200 (datasheet A06229) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | EFNA5-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Membranous and cytoplasmic expression in several tissues. No signal in the no-primary control. |
EFNA5 is a GPI-anchored cell-surface ligand with no transmembrane segment and can occupy caveolae-like membrane microdomains (UniProt P52803 topology). Expect membranous and cytoplasmic staining in several tissues, including neuronal and glandular cells (HPA tissue IHC). HPA rates its tissue staining Approved but reports low consistency with RNA expression; interpret tissue intensity with that caveat (HPA tissue IHC).
| Membranous staining, with some cytoplasmic staining, in caudate or cerebral cortex neuronal cells. | This matches the reported compartments and High neuronal staining (HPA tissue IHC). Cell-surface signal is consistent with GPI-anchored EFNA5 (UniProt P52803 topology). Assess the named cells rather than treating all tissue elements as equivalent (HPA tissue IHC). |
| Predominantly nuclear staining, with little signal at the membrane or in the cytoplasm. | A nuclear-dominant pattern does not match HPA tissue IHC or the reported cell-membrane location (HPA tissue IHC; UniProt P52803 topology). Treat it as a possible staining artefact and compare it with the expected compartments and controls (general IHC practice). |
| Strong staining in adipocytes or skeletal-muscle myocytes instead of the expected positive cells. | HPA reports those cell types as Not detected (HPA tissue IHC). Consider cross-reactivity or endogenous chromogenic activity and review detection controls (general IHC practice). An unexpected positive alone does not establish EFNA5 expression, particularly given HPA's low staining–RNA consistency (HPA tissue IHC). |
| Diffuse color coats the section without clear cellular or compartment boundaries. | That appearance cannot support a cell-specific EFNA5 call (general IHC practice). Check background in a no-primary control, then assess blocking, washes, detection chemistry and chromogen development as general IHC variables (general IHC practice). |
| No staining appears in caudate neuronal cells or duodenal glandular cells. | Both are listed as High in HPA tissue IHC, so a blank positive-control section calls for a workflow check (HPA tissue IHC; general IHC practice). HPA's Approved rating and low staining–RNA consistency mean one negative section cannot, by itself, settle EFNA5 absence (HPA tissue IHC). |
| Membrane topology | EFNA5 is a cell-surface GPI-bound ligand, lacks a transmembrane segment and occupies discrete caveolae-like microdomains (UniProt P52803 topology and function). Judge membrane localization at cell borders; an entirely nuclear pattern conflicts with that annotation (UniProt P52803 topology). |
| Processing and shedding | UniProt lists a signal peptide at residues 1–20, a mature chain at 21–203, and ADAM10-mediated extracellular-domain shedding (UniProt P52803 processing and subunit). These features make epitope location relevant to interpretation, but the payload does not locate the IHC antibody's epitope or establish a specific staining change. |
| Tissue choice and evidence strength | HPA lists High staining in hippocampal neuronal cells, gallbladder glandular cells and cardiomyocytes, among others; adipocytes and bone-marrow hematopoietic cells are Not detected (HPA tissue IHC). HPA also reports low tissue RNA specificity and low staining–RNA consistency, so compare the named cell populations rather than assuming whole-tissue uniformity (HPA tissue IHC). |
| Antibody validation | The HPA antibody CAB013282 has an Approved IHC rating, while HPA054047 has no IHC rating in the supplied record (HPA antibodies). HPA's tissue profile is also Approved with low staining–RNA consistency (HPA tissue IHC). Neither rating establishes that every observed chromogenic signal is EFNA5. |
| IF/ICC Q: Should its image match the IHC slide? | A: HPA reports approved vesicle and cytosol localization in ICC-IF, whereas tissue IHC is described as membranous and cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). The modalities and rated antibodies differ (HPA antibodies); use the separate IF/ICC guide for that application. |
| Situation | Likely cause | Next action |
|---|---|---|
| A known-positive cell population is blank. | A weak or failed IHC run is possible; HPA lists caudate neuronal cells and duodenal glandular cells as High (HPA tissue IHC; general IHC practice). | Confirm the positive-control section, primary-antibody step and detection reagents; review antigen-retrieval conditions as a general IHC workflow check (general IHC practice). No EFNA5-specific retrieval or fixation sensitivity is established by these sources. |
| Color is uniform across cells and empty spaces. | Diffuse background can arise from nonspecific detection or excess chromogen development (general IHC practice). It does not reproduce HPA's cell-associated membranous and cytoplasmic profile (HPA tissue IHC). | Inspect a no-primary control and reassess blocking, washing and development time (general IHC practice). Score EFNA5 only where cellular localization remains interpretable (HPA tissue IHC; general IHC practice). |
| The strongest signal is nuclear. | EFNA5 is annotated at the cell membrane, including caveolae-like microdomains, while HPA tissue staining is membranous and cytoplasmic (UniProt P52803 topology; HPA tissue IHC). | Flag the nuclear pattern as suspect; compare it with a positive tissue and detection controls before interpreting it as EFNA5 (HPA tissue IHC; general IHC practice). |
| An HPA Not detected cell type stains strongly. | For adipocytes, skeletal-muscle myocytes or bone-marrow hematopoietic cells, the result conflicts with the listed HPA cell-type pattern (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice). | Check the no-primary control and the identity of the stained cells; compare with an HPA High population before calling the signal specific (HPA tissue IHC; general IHC practice). |
| Membrane and cytoplasmic signals vary within an otherwise positive tissue. | HPA describes both compartments, while UniProt places EFNA5 at the surface and reports extracellular-domain shedding (HPA tissue IHC; UniProt P52803 topology and subunit). The supplied evidence does not assign a mechanism to each stained cell. | Record the two compartments separately and compare the same named cell type across sections; avoid inferring shedding from the IHC pattern alone (HPA tissue IHC; UniProt P52803 subunit; general IHC practice). |
| An IF/ICC image appears more vesicular than the IHC section. | HPA's approved ICC-IF localization is vesicles and cytosol; its tissue IHC description is membranous and cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). | Interpret each image against its own application-specific reference and antibody rating (HPA antibodies; HPA tissue IHC; HPA subcellular ICC-IF). Use the separate IF/ICC guide for IF/ICC decisions. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in molecular layer | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
These questions address EFNA5 staining in paraffin sections with chromogenic detection; the immunofluorescence entry covers the secondary application.
A06229 has an IHC image from paraffin-embedded human brain tissue (A06229 image caption), lists IF as an application, and lists human, mouse and rat reactivity (A06229 catalog applications/reactivity).
Only A06229 will render; its own figure shows IHC on paraffin-embedded human brain tissue (A06229 image caption). It lists IHC and IF applications and human, mouse and rat reactivity (A06229 catalog applications/reactivity); no IF figure is supplied (A06229 IF image alts).
Which to pick: Choose A06229 for paraffin-section tissue IHC because its own figure shows human brain tissue processed as paraffin sections (A06229 image caption); the fixative is unreported (A06229 image caption). For IF, A06229 is listed at 1:50–1:200 (A06229 catalog applications/dilution), but no IF image or ICC application is supplied (A06229 catalog IF image alts/applications). For cross-species work, A06229 lists human, mouse and rat reactivity (A06229 catalog reactivity); its IHC figure documents human tissue only (A06229 image caption).