EHD1 / EH domain-containing protein 1 · IHC design guide

Design Immunohistochemistry for EHD1

Plan paraffin-section EHD1 IHC using cytoplasmic staining in selected cell populations as a reference (HPA tissue IHC). Placental trophoblasts and lymph node germinal center cells offer comparison tissue (HPA tissue IHC); interpret staining with specificity controls because the HPA reagent may recognize more than one gene product (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EHD1 (IHC for EHD1): expected localisation Tissue: cytoplasmic (HPA tissue IHC); molecular: endosome membranes (UniProt), antibody A02168-1, validated IHC image, and IHC protocol steps
Printable EHD1 IHC protocol sheet — expected localisation Tissue: cytoplasmic (HPA tissue IHC); molecular: endosome membranes (UniProt), antibody A02168-1, controls and protocol steps. Open the full EHD1 IHC guide →

EHD1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Tissue: cytoplasmic (HPA tissue IHC); molecular: endosome membranes (UniProt)
Staining pattern Cytoplasmic in endothelium, trophoblasts, some germinal center cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A02168-1)
Positive control ⓘ Kidney+4 more · see all
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A02168-1); verify before use.
Caveat HPA staining may include another gene product (HPA tissue IHC)
Regulation No expression regulator reported (UniProt)
Isoform / epitope 0 listed isoforms; one 1–534 chain (UniProt)
Section 1

Recommended EHD1 IHC & IF Protocols

The catalog antibody has a citrate pH 6 IHC protocol (datasheet: A02168-1); the published options below cover human lung specimens (PMC5410234) and mouse testis (PMC2856533).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human testis cancer tissues; fixative not specified (datasheet A02168-1)
FixationImage fixative and duration unreported (datasheet A02168-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A02168-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02168-1)
Primary antibodyRabbit anti-EHD1, 0.5-1μg/ml (datasheet A02168-1)
Primary incubationOvernight at 4 °C (datasheet A02168-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02168-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEHD1-positive staining in cells in glomeruli of kidney (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in endothelial, trophoblastic and a subset of germinal center cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate pH 6 retrieval (datasheet: A02168-1); the lung protocol reports this pH (PMC5410234), while the testis protocol does not specify one (PMC2856533).
Section 2

What Is the Expected EHD1 Staining Pattern?

EHD1 is associated with recycling and early endosome membranes and the cell membrane; it has no transmembrane segment (UniProt Q9H4M9). In tissue IHC, expect cytoplasmic staining in endothelial and trophoblastic cells and a subset of germinal center cells (HPA tissue IHC). HPA rates the tissue staining Approved, while cautioning that the antibody may target protein from more than one gene and awaits external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in glomerular cells, with signal following cellular outlines or appearing punctate.This fits the High glomerular staining reported in kidney (HPA tissue IHC). Membrane-associated or vesicular detail is plausible from EHD1 localisation (UniProt Q9H4M9), but a chromogenic section need not resolve individual endosomes (general IHC practice).
Staining is confined to nuclei, without the expected cytoplasmic signal.A nuclear-only pattern conflicts with HPA's cytoplasmic tissue profile and UniProt's membrane and endosome localisation (HPA tissue IHC; UniProt Q9H4M9). Check the counterstain and detection controls before scoring it as EHD1.
Strong staining appears in adrenal glandular cells or bronchial respiratory epithelium.Those cell populations are reported as Not detected (HPA tissue IHC). Review the cell identity and controls; cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA's multi-gene-target caution limits attribution to EHD1 (HPA tissue IHC).
Brown deposit spreads across cells and surrounding tissue without a clear cellular pattern.This is difficult to reconcile with HPA's cell-specific cytoplasmic profile (HPA tissue IHC). Nonspecific binding or endogenous detection activity can produce diffuse background; compare a matched detection control before interpreting intensity (general IHC practice).
Glomerular cells show no signal in a kidney section used as a positive reference.HPA reports High staining in glomerular cells (HPA tissue IHC). First confirm that glomeruli are present and the IHC run worked; a blank section alone cannot distinguish a failed assay from biological variation (general IHC practice).
💡Expected EHD1 appearanceCall a result consistent when glomerular cells show High cytoplasmic staining, with suitable localisation around membranes or vesicles (HPA tissue IHC; UniProt Q9H4M9); widespread nuclear-only or cell-independent deposit is suspect (general IHC practice).
How each factor affects the staining
Cell compartmentEHD1 has no transmembrane segment yet associates with recycling endosome, early endosome and cell membranes (UniProt Q9H4M9). Score cytoplasmic signal in its cellular context; do not require a continuous surface rim (general IHC practice).
Tissue and cell selectionKidney glomerular cells are High; placental trophoblastic and lymph-node germinal center cells are Medium (HPA tissue IHC). Compare the specified cells, since whole-section intensity can obscure a subset pattern (general IHC practice).
Antibody evidenceHPA049890 and HPA049986 have Approved IHC status, while the tissue profile cautions that the signal may represent protein from more than one gene (HPA antibodies; HPA tissue IHC). Treat agreement with the pattern as supportive, not definitive identity.
Expression evidenceUniProt reports high testis expression, whereas HPA reports tissue-enhanced RNA in testis and bone marrow but Not detected protein staining in bone-marrow hematopoietic cells (UniProt Q9H4M9; HPA tissue IHC). RNA or tissue-level expression alone does not specify an IHC-positive cell.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected kidney reference is blank.The sampled field may lack glomeruli, or the IHC run may have failed (general IHC practice); HPA's High designation applies specifically to glomerular cells (HPA tissue IHC).Locate glomeruli on the counterstained section and check the run control before changing assay conditions (general IHC practice).
Signal is mainly nuclear.Nuclear-only staining does not match the cytoplasmic tissue profile or membrane and endosome localisation (HPA tissue IHC; UniProt Q9H4M9).Recheck compartment assignment against the counterstain and inspect a matched detection control; withhold an EHD1-positive score if the nuclear-only pattern persists (general IHC practice).
Adrenal glandular cells stain strongly.HPA lists these cells as Not detected and cautions that its antibody may target protein from more than one gene (HPA tissue IHC).Verify the cell type, compare detection controls and assess whether the same staining follows the expected positive-cell pattern elsewhere (general IHC practice).
Diffuse chromogen obscures cell boundaries.Nonspecific binding or endogenous detection activity can obscure a cell-specific result (general IHC practice).Compare a matched detection control and review blocking, detection and wash conditions before scoring the tissue (general IHC practice).
Bone marrow is expected to be IHC positive because its RNA is tissue enhanced.HPA reports tissue-enhanced RNA yet Not detected staining in hematopoietic cells (HPA tissue IHC); the measures answer different questions.Judge the observed hematopoietic cells against the protein IHC record, and use a glomerulus-containing kidney section for a stronger positive reference (HPA tissue IHC).
IF/ICC Q: Should a plasma-membrane or cilium signal be accepted?HPA supports plasma-membrane localisation and additional primary-cilium and transition-zone localisation in ICC-IF (HPA subcellular).A: Interpret those as IF/ICC localisation evidence; assess paraffin-section chromogenic staining against the separate tissue IHC pattern (HPA subcellular; HPA tissue IHC).

Sample controls for EHD1 IHC & IF

🧪Run kidney first: cells in glomeruli should stain (HPA: High in kidney glomerular cells). Use adrenal gland glandular cells as the negative tissue (HPA: Not detected); on the kidney slide, assess adjacent non-glomerular cells for background without assuming they are EHD1-negative.
Positive control tissue: Kidney (Cells in glomeruli, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
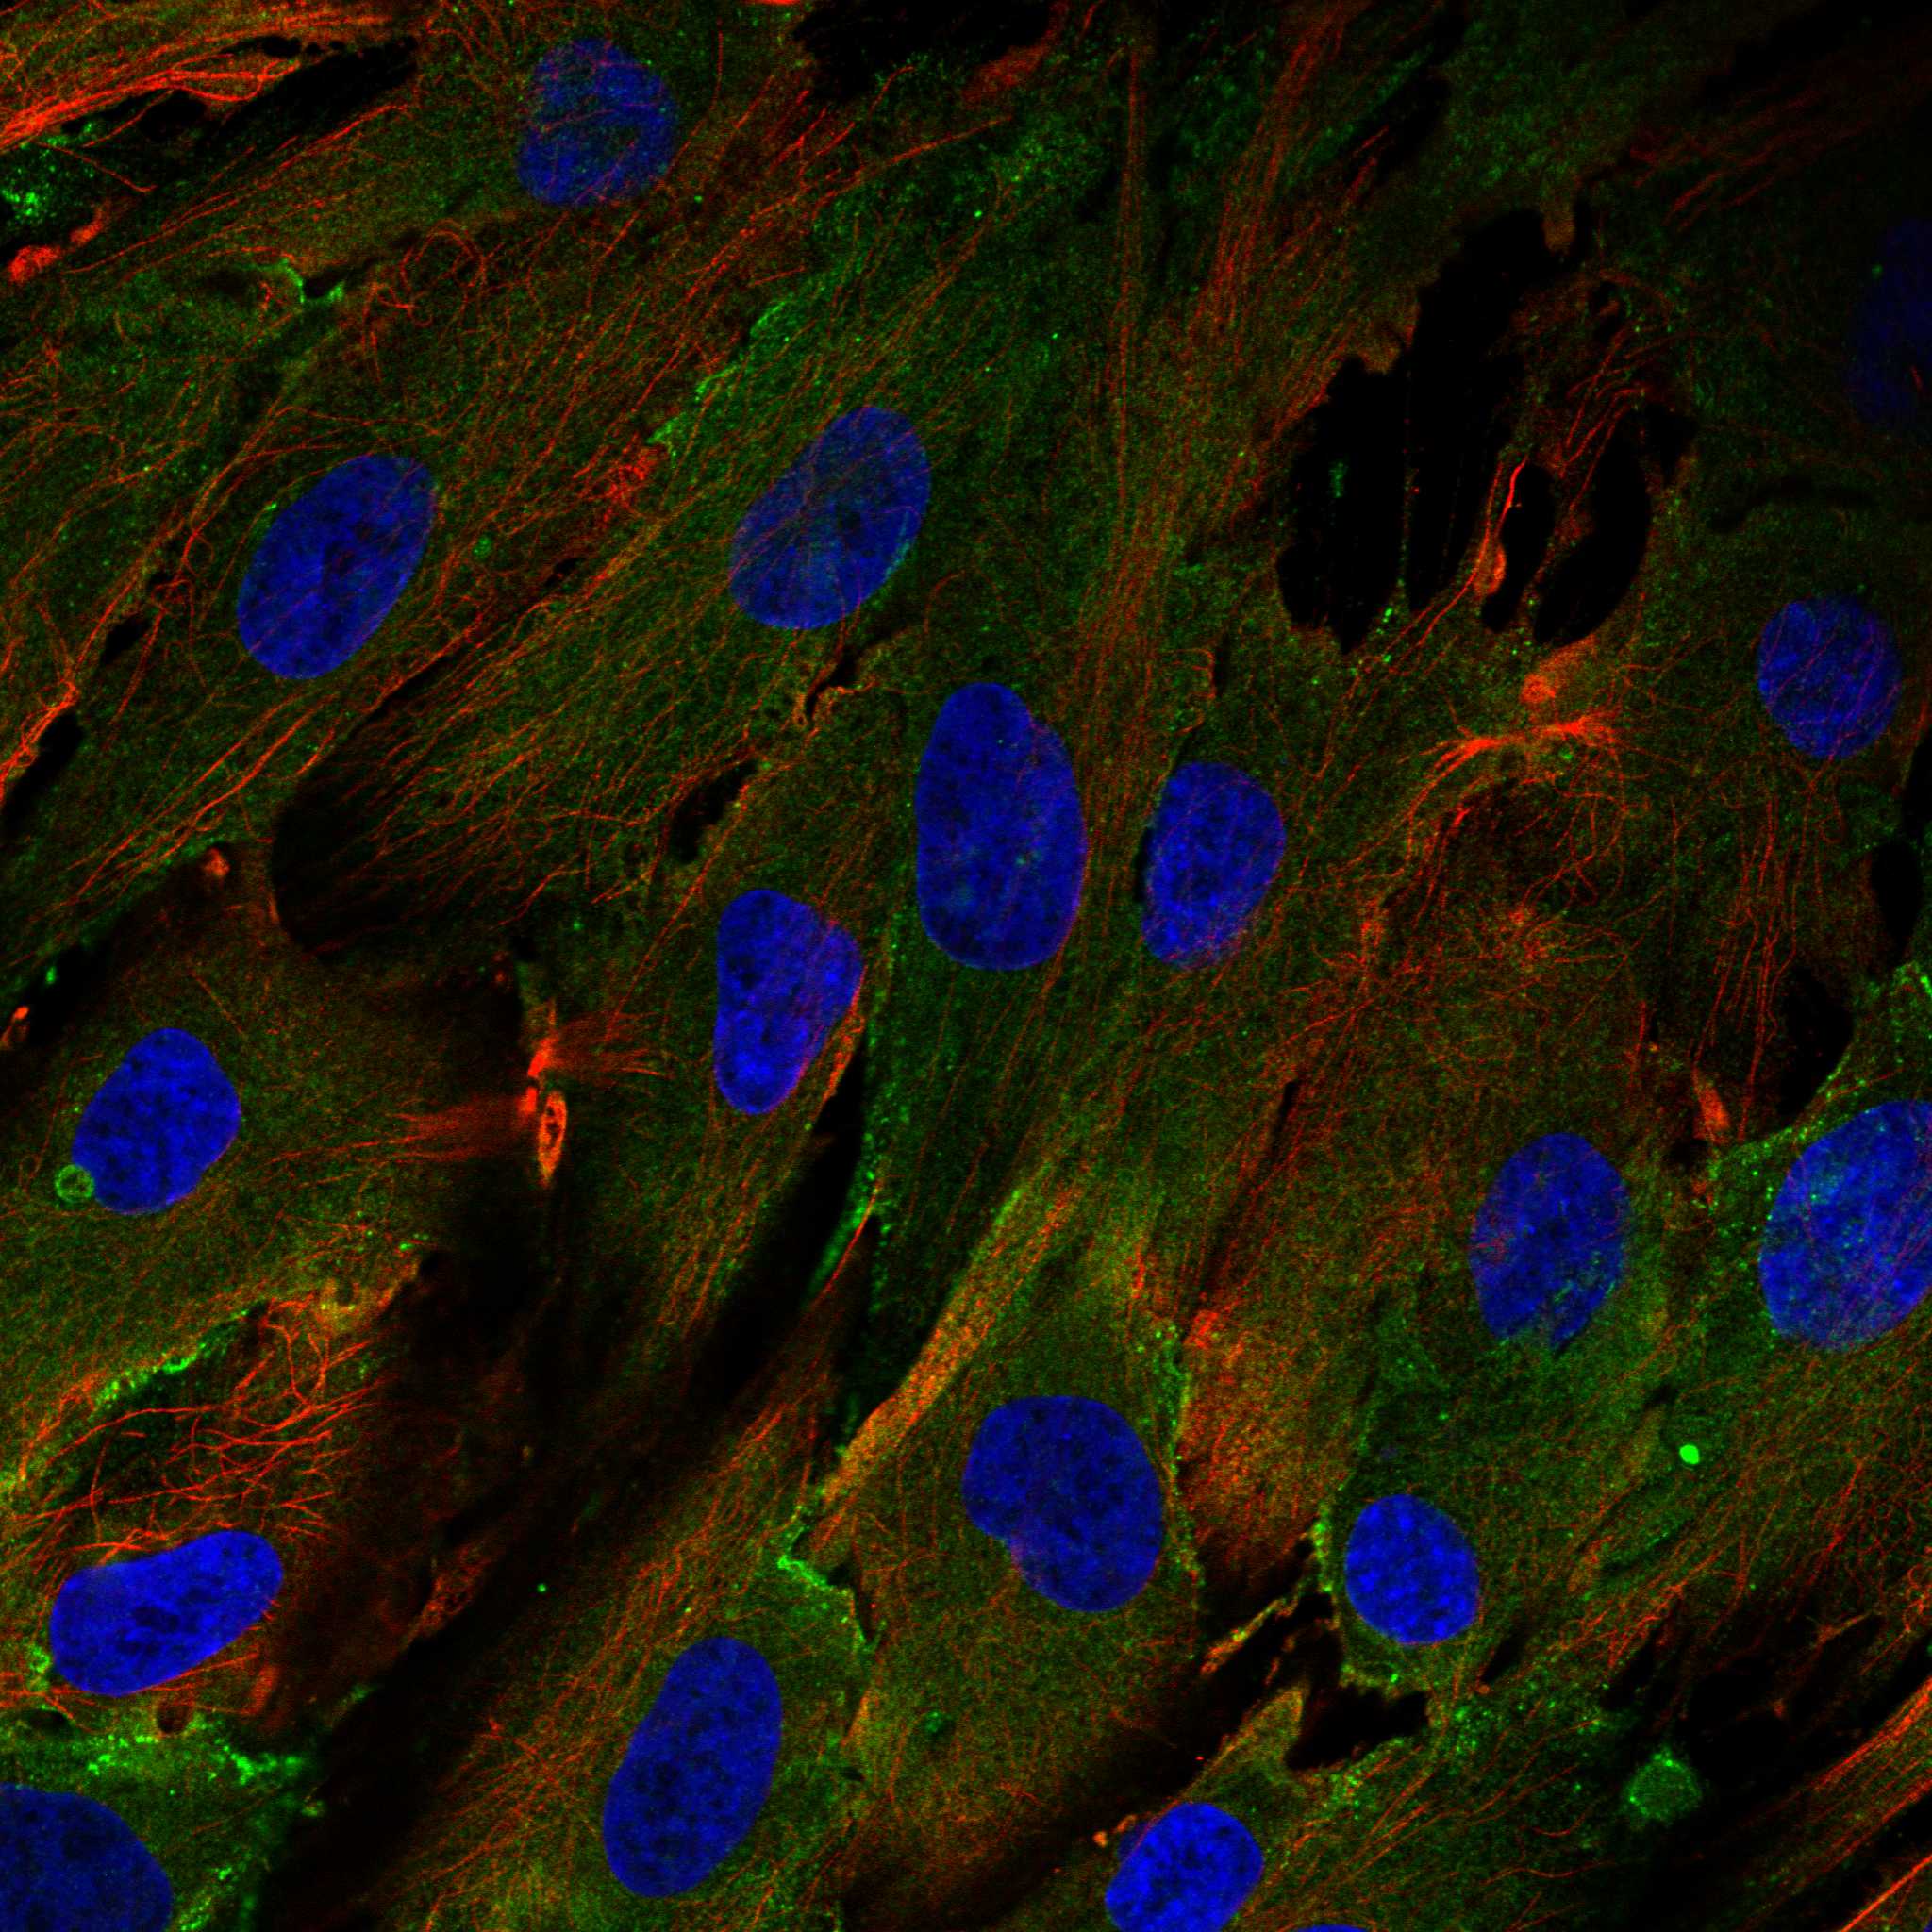
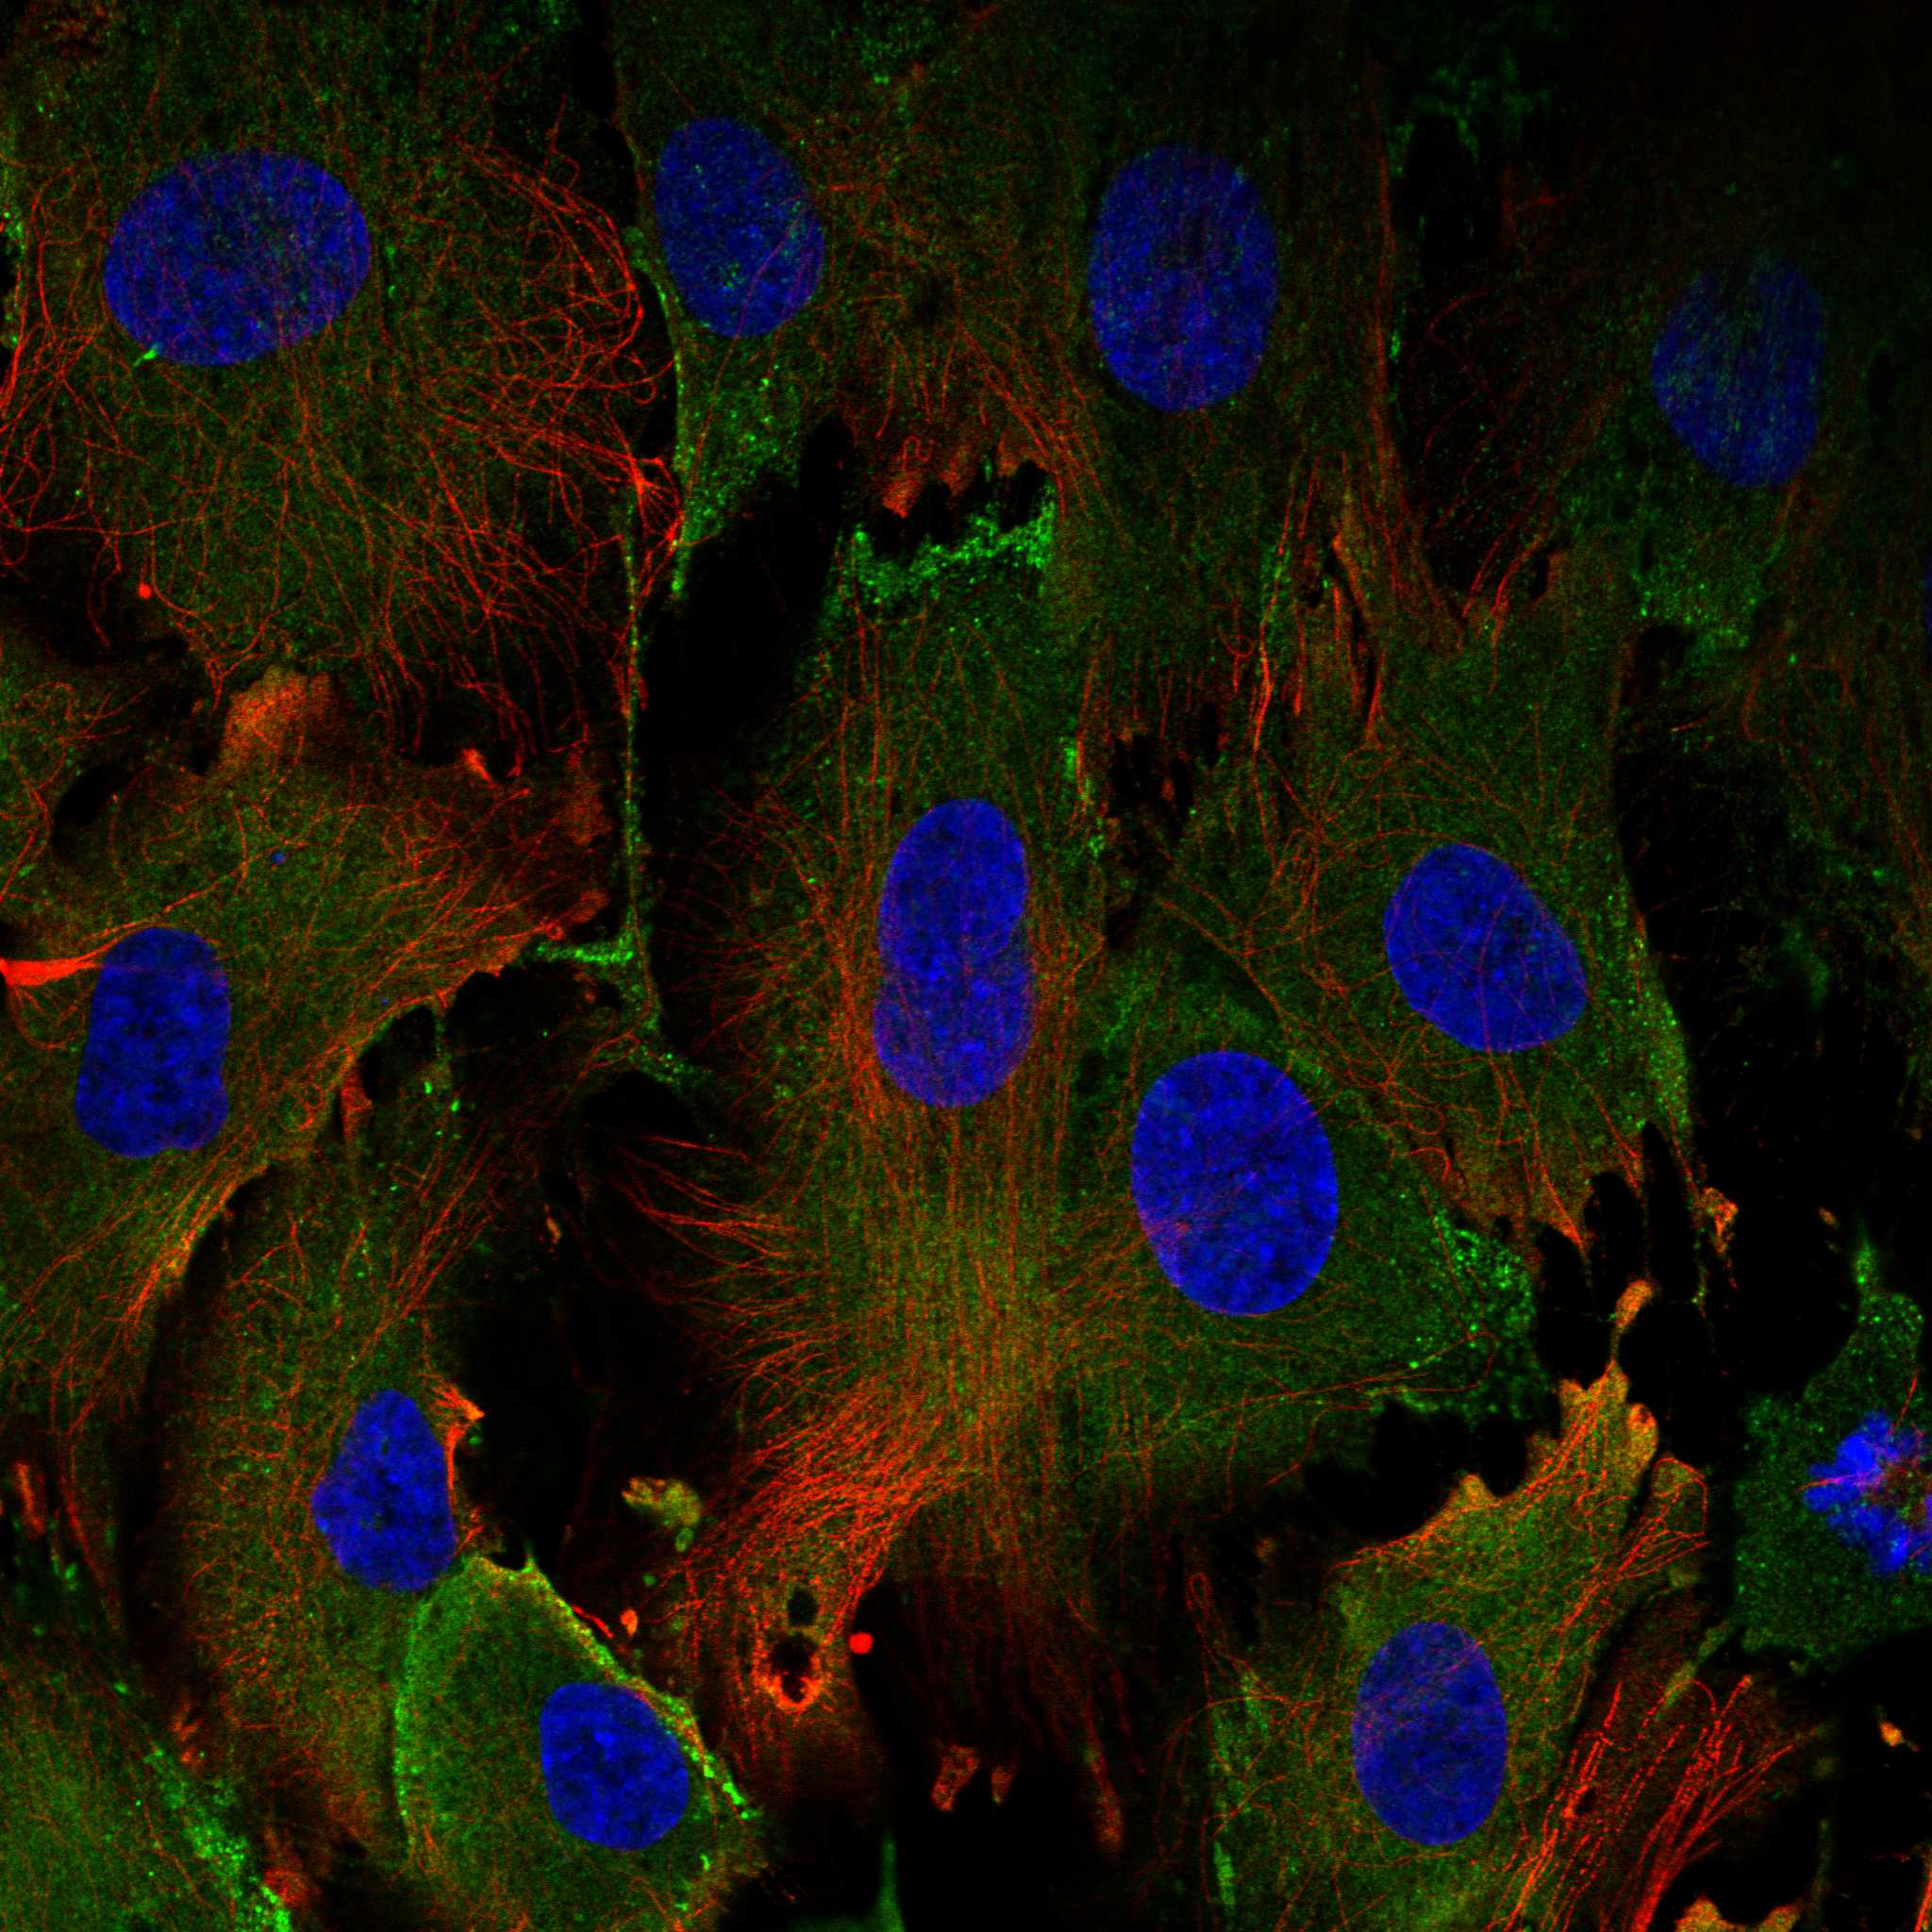
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EHD1 in BJ [Human fibroblast], SiHa, U2OS, A-431, A-549, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, KOLF2.1J, with annotated localisation: Plasma membrane (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched rabbit IgG isotype control (caption: rabbit anti-EHD1 antibody), and an EHD1 knockout biological control where available. For chromogenic kidney IHC, block endogenous peroxidase and check for endogenous biotin background if using the caption’s biotin-based detection (caption: biotinylated secondary and SABC–DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A02168-1 paraffin-section caption does not state the fixative. The caption uses citrate retrieval at pH 6 for 20 minutes, but does not establish that retrieval is required for kidney sections. HPA supports plasma membrane and ciliary IF localization (HPA: subcellular), but the supplied evidence does not establish whether frozen sections or IF are easier; evaluate kidney background from endogenous peroxidase or biotin during chromogenic detection.

HPA tissue IHC evidence for EHD1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Caution, targets protein from more than one gene. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Cells in glomeruli High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Lung Alveolar cells Medium Protein (IHC) HPA →
Lymph node Germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced EHD1 IHC Tips

Troubleshoot EHD1 staining in paraffin sections by checking retrieval, cellular pattern and controls before comparing chromogenic signal across samples.

What retrieval conditions should I try first when EHD1 staining is weak?
Start with heat-mediated citrate buffer at pH 6 for 20 minutes on paraffin sections (datasheet A02168-1). The illustrated testis cancer section used that retrieval before staining with 1 μg/ml antibody overnight at 4°C (datasheet A02168-1). If signal is weak, compare retrieved and unretrieved sections from the same block while holding antibody concentration and detection constant (standard IHC practice). Inspect tissue integrity and nonspecific staining alongside signal, because stronger retrieval can also damage morphology or increase background (standard IHC practice). Score cytoplasmic and membrane-associated patterns in the expected cells, rather than treating stronger diffuse colour as improved EHD1 detection (HPA tissue IHC; UniProt Q9H4M9 localisation).
Could fixation explain variable EHD1 staining between paraffin blocks?
The selected paraffin-section caption does not state a fixative, so target-specific EHD1 fixation sensitivity is unknown (datasheet A02168-1). Record fixative, fixation duration, block age and processing history for each specimen before comparing staining intensity (standard IHC practice). When material permits, stain matched blocks together using the documented citrate pH 6, 20-minute retrieval and 1 μg/ml primary concentration (datasheet A02168-1). Compare morphology and staining in the same cell population, since differences in cellular composition can mimic a fixation effect (standard IHC practice; HPA tissue IHC). Treat any improvement after a processing change as a local optimisation result until it is reproduced across comparable specimens (standard IHC practice).
Which EHD1 staining pattern is plausible in tissue sections?
Expect cellular staining compatible with EHD1 at recycling and early endosome membranes and the cell membrane (UniProt Q9H4M9 localisation). HPA describes cytoplasmic staining in endothelial, trophoblastic and a subset of germinal center cells, providing tissue-level patterns to inspect (HPA tissue IHC). Because EHD1 lacks a transmembrane segment, do not require a continuous membrane outline for a positive call (UniProt Q9H4M9 topology). Evaluate the pattern at high magnification alongside cell morphology and an adjacent negative-control section (standard IHC practice). Predominantly nuclear staining or uniform colour over every cell type warrants investigation before attribution to EHD1 (UniProt Q9H4M9 localisation; standard IHC practice).
How should I assess possible epitope-related staining differences?
The supplied EHD1 record lists 0 isoforms and a 534-amino-acid chain, but the catalog antibody epitope is unspecified (UniProt Q9H4M9; datasheet A02168-1). EHD1 contains a dynamin-type G domain and a C-terminal EH domain, information useful when an epitope map becomes available (UniProt Q9H4M9 domains). Its annotated phosphoserines at positions 355 and 456 do not establish that this antibody is modification-sensitive (UniProt Q9H4M9 modified residues). Compare staining after the documented citrate retrieval under otherwise identical conditions before assigning a biological cause to intensity differences (datasheet A02168-1; standard IHC practice). Seek antibody epitope or independent specificity evidence before interpreting a changed pattern as an EHD1 variant (standard IHC practice).
How can I check an EHD1 pattern with multiplex immunofluorescence?
Pair EHD1 with a validated marker for the cell population being assessed, such as endothelial cells, and include single-label controls (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores after checking tissue autofluorescence in an unstained section, particularly before assigning weak puncta to EHD1 (standard IF practice). EHD1 associates with endosomal membranes and has no transmembrane segment, but the catalog antibody epitope and its accessibility are unspecified (UniProt Q9H4M9 localisation and topology; datasheet A02168-1). Optimise permeabilisation for an intracellular epitope using matched sections, while checking that membrane and ciliary detail remains intact (standard IF practice). Interpret overlap at the appropriate optical resolution and retain the chromogenic IHC controls as separate evidence (standard IF practice).
What should I change when EHD1 DAB staining looks diffuse?
First inspect a no-primary control for secondary-reagent binding and endogenous enzyme signal before attributing diffuse DAB colour to EHD1 (standard IHC practice). The illustrated protocol used 10% goat serum block, 1 μg/ml primary overnight at 4°C, and a biotinylated secondary for 30 minutes at 37°C (datasheet A02168-1). Check peroxidase blocking and assess endogenous biotin when using the illustrated biotin-based detection system (datasheet A02168-1; standard IHC practice). Compare background in expected positive and negative cell populations on the same section, while inspecting edges and damaged tissue separately (HPA tissue IHC; standard IHC practice). Adjust one workflow variable at a time and keep DAB development consistent across comparisons (standard IHC practice).
How should I score EHD1 expression across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, using the cytoplasmic patterns reported for endothelial, trophoblastic or selected germinal center cells as context (HPA tissue IHC). Record the percentage of positive viable cells and stain intensity to calculate an H-score from 0–300, or report positive-cell density per mm² (standard IHC practice). Normalise counts to viable tissue area or the number of eligible cells, and analyse comparable regions across specimens (standard IHC practice). Keep retrieval, primary concentration, DAB development and image settings consistent during a comparison (datasheet A02168-1; standard IHC practice). Report background thresholds and excluded damaged or necrotic regions so that changes in cell composition are not mistaken for altered EHD1 staining (standard IHC practice).
How can I distinguish credible EHD1 positivity from staining artefact?
A credible signal should match identifiable cells and a cytoplasmic or membrane-associated distribution consistent with EHD1 localisation (HPA tissue IHC; UniProt Q9H4M9 localisation). HPA reports high signal in glomerular cells and no detection in adrenal glandular cells, useful reference patterns rather than absolute controls for every specimen (HPA tissue IHC). Reconsider isolated nuclear colour, section-edge accentuation, necrotic deposits or staining reproduced in the no-primary control (UniProt Q9H4M9 localisation; standard IHC practice). Check endogenous peroxidase and, with biotin-based detection, endogenous biotin before calling diffuse DAB signal positive (datasheet A02168-1; standard IHC practice). Interpret ambiguous staining cautiously because HPA flags possible recognition of protein from more than one gene (HPA tissue IHC reliability).
Boster reagents

Best EHD1 / EH domain-containing protein 1 IHC Antibodies

EHD1 IHC images cover human testis cancer, tonsil and placenta, and mouse testis paraffin sections (A02168-1 image captions). IF/ICC images cover A431 and SiHa cells (A02168-1/2 image captions).

Real IHC data IHC analysis of EHD1 using anti-EHD1 antibody (A02168-1). EHD1 was detected in paraffin-embedded section of human testis cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-EHD1 Antibody (A02168-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-EHD1 Antibody ®
Cat # A02168-1
Real IF data IF analysis of EHD1 using anti-EHD1 antibody (A02168-2). EHD1 was detected in an immunocytochemical section of SiHa cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-EHD1 Antibody (A02168-2) overnight at 4°C. DyLight®594 Conjugated Goat Anti-Rabbit IgG (BA1142) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-EHD1 Antibody ®
Cat # A02168-2

A02168-1 has IHC images from human and mouse paraffin sections and an IF/ICC image from A431 cells (catalog image captions). A02168-2 has an IF/ICC image from SiHa cells and lists human, mouse and monkey reactivity; IHC is absent from its application list (catalog image caption; application and reactivity lists).

Which to pick: Choose A02168-1 for paraffin tissue IHC: its own captions document citrate retrieval at pH 6 for 20 minutes, 1 μg/ml primary antibody and DAB detection; the fixative is unreported (A02168-1 IHC image captions). For IF/ICC, A02168-1 is shown in A431 cells at 2 μg/ml and A02168-2 in SiHa cells at 5 μg/ml; neither has a specified clone (catalog IF image captions; clone fields). For cross-species planning, A02168-1 lists human, mouse and rat reactivity with IHC and IF, while A02168-2 lists human, mouse and monkey reactivity with IF/ICC; the tissue IHC images document human and mouse samples for A02168-1 (catalog application and reactivity lists; A02168-1 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H4M9 (EHD1_HUMAN, EH domain-containing protein 1).
  2. Human Protein Atlas. EHD1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. EHD1 subcellular location (ICC-IF): Mainly localized to the plasma membrane. In addition localized to the primary cilium and primary cilium transition zone..
  4. Human Protein Atlas. EHD1 antibody validation summary (4 antibodies).
  5. Increased Expression of Eps15 Homology Domain 1 is Associated with Poor Prognosis in Resected Small Cell Lung Cancer. Journal of Cancer 2015 — PMC4565848.
  6. Mammalian Eps15 homology domain 1 promotes metastasis in non-small cell lung cancer by inducing epithelial-mesenchymal transition. Oncotarget 2017 — PMC5410234.
  7. The expression of Eps15 homology domain 1 is negatively correlated with disease-free survival and overall survival of osteosarcoma patients. Journal of orthopaedic surgery and research 2019 — PMC6460645.
  8. The endocytic recycling regulator EHD1 is essential for spermatogenesis and male fertility in mice. BMC developmental biology 2010 — PMC2856533.
  9. PubMed PMID:9253601 — UniProt-cited evidence.
  10. PubMed PMID:10395801 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.