EIF3A / Eukaryotic translation initiation factor 3 subunit A · IHC design guide

Design Immunohistochemistry for EIF3A

Plan EIF3A staining in paraffin sections around its broadly observed cytoplasmic pattern (HPA tissue IHC). Start with the catalog antibody at 2–5 μg/ml and score signal by cell type, noting that smooth muscle cells were not detected (datasheet A02339-3; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EIF3A (IHC for EIF3A): expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody A02339-3, validated IHC image, and IHC protocol steps
Printable EIF3A IHC protocol sheet — expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody A02339-3, controls and protocol steps. Open the full EIF3A IHC guide →

EIF3A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC)
Staining pattern Broad cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02339-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Smooth muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Smooth muscle cells may show no staining (HPA tissue IHC)
Regulation Abundance regulation is unreported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended EIF3A IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02339-3) is followed by four published EIF3A immunohistochemistry protocols (PMC8684683; PMC4999401; PMC12065328; PMC4005749).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colorectal adenocarcinoma tissue; fixative not specified (datasheet A02339-3)
FixationImage fixative and duration unreported (datasheet A02339-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02339-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02339-3)
Primary antibodyRabbit anti-EIF3A, 2-5 μg/ml (datasheet A02339-3)
Primary incubationOvernight at 4 °C (datasheet A02339-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02339-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEIF3A-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A02339-3); citrate retrieval is a published alternative for tissue arrays (PMC8684683).
Section 2

What Is the Expected EIF3A Staining Pattern?

EIF3A should show predominantly cytoplasmic staining in many cell types: HPA describes a ubiquitous cytoplasmic IHC pattern with Enhanced reliability and medium agreement with RNA data (HPA: tissue IHC). This fits its cytoplasmic location and lack of a transmembrane segment (UniProt Q14152: subcellular location and topology). Expect medium staining in several glandular and other listed cell populations, while intensity varies by tissue (HPA: tissue IHC).

What am I looking at on my slide?
Cytoplasmic stain in appendix or breast glandular cells.This matches the expected compartment and the medium staining reported in those cells (HPA: tissue IHC; UniProt Q14152: cytoplasm). Judge the cells against adjacent background and a counterstain before scoring intensity; a cytoplasmic tint alone is insufficient if the whole section is similarly colored (standard IHC practice).
Predominantly nuclear stain, with little cytoplasmic signal.This is discordant with the tissue IHC profile and UniProt location (HPA: ubiquitous cytoplasmic expression; UniProt Q14152: cytoplasm). Check staining specificity and detection background before assigning a nuclear IHC pattern. HPA reports uncertain nucleoplasmic localization by ICC-IF, which does not establish nuclear staining as the expected paraffin IHC result (HPA: subcellular ICC-IF).
Strong stain in smooth muscle cells while listed positive cells are weak.Smooth muscle cells are reported as not detected, so that reversal warrants scrutiny (HPA: tissue IHC). Possible explanations include nonspecific antibody binding or endogenous detection activity (standard IHC practice); the image alone cannot distinguish them. Compare the cell type, compartment and controls before calling the stain EIF3A.
Uniform haze across cells, stroma and empty areas.A diffuse, cell-independent deposit is less convincing than a cytoplasmic cell pattern (HPA: tissue IHC; standard IHC interpretation). Consider incomplete blocking, excessive antibody or detection reagent, or inadequate washing as general workflow causes (standard IHC practice). Do not score the haze as EIF3A-positive cells.
No visible stain in appendix glandular cells or bone marrow hematopoietic cells.Both are reported at medium intensity, so an entirely blank result should prompt a technical check before a biological conclusion (HPA: tissue IHC). Assess section quality, retrieval, antibody and detection steps with appropriate controls (standard IHC practice). HPA does not establish a target-specific fixation effect.
💡Expected EIF3A appearanceCall positive when distinct cytoplasmic stain reaches about the reported medium level in a listed positive cell population (HPA: tissue IHC; UniProt Q14152: cytoplasm); dominant nuclear staining or uniform, cell-independent deposit calls for review rather than an EIF3A-positive score (HPA: subcellular ICC-IF; standard IHC interpretation).
How each factor affects the staining
Compartment and topologyUniProt places EIF3A in the cytoplasm and lists no transmembrane segment (UniProt Q14152: subcellular location and topology). HPA describes ubiquitous cytoplasmic tissue staining (HPA: tissue IHC). Evaluate intracellular cytoplasmic distribution; a membrane-only pattern has no support from these sources.
Tissue context and validationHPA lists medium stain in appendix glandular, bone marrow hematopoietic and cerebellar Purkinje cells, low stain in several other cells, and no detection in smooth muscle cells (HPA: tissue IHC). Its Enhanced IHC assessment reflects antibody-pattern support, while the tissue profile reports medium agreement with RNA data (HPA: tissue IHC; HPA: antibodies).
Antibody evidenceBoth listed antibodies have Enhanced IHC validation; only HPA038316 has Supported ICC validation (HPA: antibodies). These ratings help select evidence for interpreting a pattern, but they do not specify a dilution, retrieval condition or guaranteed result for another IHC-validated antibody (HPA: antibodies).
Isoforms and epitopeUniProt lists 2 EIF3A isoforms and a chain spanning residues 2–1382 (UniProt Q14152: isoforms and processing). No antibody epitope is supplied here, so isoform recognition or an epitope-specific staining difference cannot be predicted from this record.
What should IF/ICC show?HPA reports supported cytosolic and uncertain nucleoplasmic localization, with ICC-IF images in A-431, U-251MG and U2OS (HPA: subcellular ICC-IF). Treat the nucleoplasmic observation as uncertain; it does not override the cytoplasmic expectation for this paraffin IHC guide (HPA: tissue IHC; UniProt Q14152: cytoplasm).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A listed medium-staining tissue is blank.The result conflicts with the reported cell pattern (HPA: tissue IHC); section, retrieval or detection failure is possible (standard IHC practice).Check section preservation and the run's positive and detection controls, then review retrieval and the antibody's IHC instructions (standard IHC practice). Do not infer EIF3A-specific fixation sensitivity from this result.
The expected cytoplasmic stain is very weak.Signal may be weak from general IHC workflow conditions; tissue intensity also varies, with some populations reported low (standard IHC practice; HPA: tissue IHC).Confirm the sampled cell type and compare a listed medium-staining tissue in the same run (HPA: tissue IHC). Review antibody concentration, retrieval and detection using the applicable IHC instructions (standard IHC practice).
The whole section has a brown haze.Cell-independent chromogen may reflect nonspecific binding, endogenous enzyme activity or incomplete washing (standard chromogenic IHC practice).Inspect the appropriate negative and detection controls; review blocking, washing and detection conditions (standard IHC practice). Score only cell-associated cytoplasmic stain that remains distinguishable from background (HPA: tissue IHC; standard IHC interpretation).
Nuclei stain more strongly than cytoplasm.This differs from the expected IHC compartment (HPA: tissue IHC; UniProt Q14152: cytoplasm). The uncertain ICC-IF nucleoplasmic observation does not explain a dominant nuclear paraffin IHC result (HPA: subcellular ICC-IF).Compare antibody and detection controls, inspect counterstain and reassess cellular localization (standard IHC practice). Report the nuclear pattern as discordant unless independently supported.
Smooth muscle cells stain prominently.HPA reports smooth muscle cells as not detected (HPA: tissue IHC). Nonspecific binding or endogenous detection activity is possible, but the stain alone cannot establish which (standard IHC practice).Check the tissue cell identity, cytoplasmic distribution and detection controls; compare with a listed medium-staining population in the run (HPA: tissue IHC; standard IHC practice).
Staining differs between fields or sections.Uneven reagent coverage or section handling can produce spatial differences (standard IHC practice); cell composition and reported tissue intensity also vary (HPA: tissue IHC).Compare like cell types across fields, inspect section integrity and review staining uniformity (standard IHC practice). Base the interpretation on identifiable cells and controls, rather than assigning every field the same EIF3A score.

Sample controls for EIF3A IHC & IF

🧪Run bone marrow first: hematopoietic cells should show EIF3A staining at the HPA Medium level; use smooth muscle as the negative tissue because EIF3A is Not detected in smooth muscle cells (HPA: bone marrow, hematopoietic cells, Medium; HPA: smooth muscle, smooth muscle cells, Not detected). On the positive slide, cells without specific signal should remain at background, but the supplied HPA row does not identify a particular internal-negative cell type (HPA: bone marrow row).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Smooth muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EIF3A in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control for the catalog rabbit primary; where feasible, confirm specificity with EIF3A knockout material or competition with the matching immunizing peptide (caption: rabbit anti-EIF3A antibody; standard IHC controls). For bone marrow chromogenic staining, quench endogenous peroxidase and inspect the no-primary slide for background DAB signal (HPA: bone marrow, hematopoietic cells; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A02339-3 paraffin-section caption does not state a fixative (selected tissue-IHC caption). The caption demonstrates heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required; frozen-section staining is not documented as easier, while HPA provides ICC-IF images with supported cytosolic localization and uncertain nucleoplasmic localization (selected tissue-IHC caption; HPA: subcellular). In bone marrow, endogenous peroxidase in hematopoietic cells can create misleading chromogenic signal (HPA: bone marrow, hematopoietic cells; standard IHC practice).

HPA tissue IHC evidence for EIF3A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced EIF3A IHC Tips

Troubleshoot EIF3A staining in paraffin sections by checking retrieval, cytoplasmic localisation, controls and scoring before interpreting differences between samples.

What retrieval should I try first if EIF3A staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02339-3). The selected image used this retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C, so reproduce those conditions when assessing weak staining (datasheet A02339-3). Compare a known positive section processed alongside the sample, and check whether tissue morphology remains intact after heating (standard IHC practice). If staining remains weak, test a different retrieval buffer on adjacent sections while holding antibody concentration and detection conditions constant (standard IHC practice). Score the gain in cytoplasmic signal against any rise in background (UniProt Q14152 localisation; standard IHC practice).
Could fixation explain inconsistent EIF3A staining between paraffin blocks?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not report a fixative (datasheet A02339-3). Record the fixative, fixation duration and processing history for each block before comparing EIF3A intensity (standard IHC practice). Run sections from the blocks together with the same EDTA pH 8.0 retrieval and primary incubation, keeping section thickness and detection conditions consistent (datasheet A02339-3; standard IHC practice). If one block stains poorly, compare its morphology and an appropriate control antigen to assess general processing effects (standard IHC practice). A staining difference alone cannot establish a specific fixation effect on EIF3A (standard IHC interpretation).
Where should EIF3A signal appear in a convincing IHC section?
Expect predominantly cytoplasmic staining: UniProt places EIF3A in the cytoplasm, and HPA reports ubiquitous cytoplasmic tissue expression (UniProt Q14152 localisation; HPA tissue IHC). HPA subcellular images support cytosolic localisation and mark nucleoplasmic localisation as uncertain, so score a nuclear-only DAB pattern cautiously (HPA subcellular). Compare staining within identifiable cells against the counterstain, avoiding extracellular pigment or precipitate when assigning a compartment (standard IHC practice). Medium staining in glandular cells from several tissues provides examples of expected positive cell populations, while smooth muscle cells were not detected in the cited tissue profile (HPA tissue IHC). Use matched sections and the same detection settings for compartment comparisons (standard IHC practice).
How should I interpret staining if the antibody epitope is unspecified?
EIF3A has 2 annotated isoforms, but the supplied antibody caption does not map its epitope or establish isoform selectivity (UniProt Q14152 isoforms; datasheet A02339-3). Do not assign a paraffin-section signal to one isoform without antibody epitope information and a suitable orthogonal control (standard IHC interpretation). The protein has a PCI domain at residues 315–498 and annotated modified residues, including phosphoserines at 492 and 584 (UniProt Q14152 domains and modified residues). These annotations alone do not establish whether retrieval or phosphorylation changes antibody binding (standard IHC interpretation). If staining varies unexpectedly, compare an independently validated epitope or genetic control where available (standard IHC practice).
How can IF help check an ambiguous chromogenic EIF3A pattern?
Use IF as a separate localisation check: HPA supports cytosolic signal and labels nucleoplasmic signal uncertain (HPA subcellular). Multiplex EIF3A with a marker for the expected cell population, such as a glandular-cell marker in a glandular section, and inspect both channels at the single-cell level (HPA tissue IHC; standard IF practice). Choose fluorophores and exposure settings after checking tissue autofluorescence in an unstained section, particularly when faint signal overlaps background (standard IF practice). EIF3A has no annotated transmembrane segment, so use permeabilisation appropriate for access to its intracellular epitope and verify that cell structure remains intact (UniProt Q14152 topology and localisation; standard IF practice). Keep IF conclusions distinct from chromogenic intensity scores (standard assay interpretation).
How do I distinguish weak EIF3A staining from diffuse DAB background?
Run a no-primary control beside the test section to reveal signal from the detection system and tissue itself (standard IHC practice). In the selected procedure, sections received 10% goat serum blocking and peroxidase-linked secondary detection with DAB; these are documented conditions, not proof that every background source was removed (datasheet A02339-3). Include a peroxidase block, rinse thoroughly and inspect whether brown signal persists in the no-primary section (standard chromogenic IHC practice). Compare candidate staining with the expected cytoplasmic pattern and check whether it follows tissue folds or damaged edges (UniProt Q14152 localisation; standard IHC practice). Adjust blocking or primary concentration only after identifying the likely source (standard IHC practice).
What should I measure when comparing EIF3A across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score cytoplasmic signal in a predefined cell population because the tissue profile describes EIF3A as ubiquitously cytoplasmic (HPA tissue IHC). An H-score combines the percentage of cells at each intensity grade; alternatively report percent positive cells or positive-cell density per mm², with the scoring rule stated in advance (standard IHC quantification). Normalise counts to the number of eligible cells or evaluable tissue area, and compare matched regions rather than whole sections with different cellular composition (standard IHC practice). Apply one threshold and imaging setup across groups, with observers blinded where feasible (standard IHC practice). Report staining controls and excluded necrotic or folded areas with the scores (standard IHC practice).
When is an unusual EIF3A-positive area likely to be artefactual?
A convincing result should show signal within intact cell cytoplasm, consistent with UniProt localisation and the HPA tissue profile (UniProt Q14152 localisation; HPA tissue IHC). Check the cell identity before calling an unexpected compartment or cell population positive; smooth muscle cells were not detected in the cited HPA tissue profile (HPA tissue IHC). Staining confined to section edges, folds or necrotic areas warrants review on adjacent sections because those regions can distort chromogenic interpretation (standard IHC practice). Brown signal persisting without primary antibody may reflect endogenous enzyme activity or detection background rather than EIF3A (standard IHC practice). Resolve discrepancies with matched controls and morphology before comparing biological groups (standard IHC practice).
Boster reagents

Best EIF3A / Eukaryotic translation initiation factor 3 subunit A IHC Antibodies

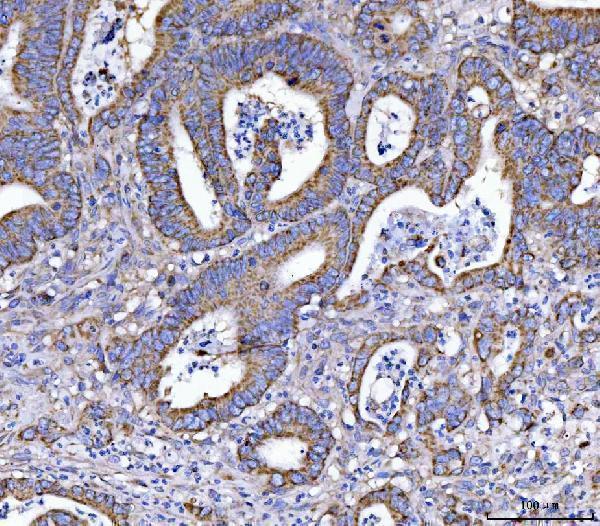
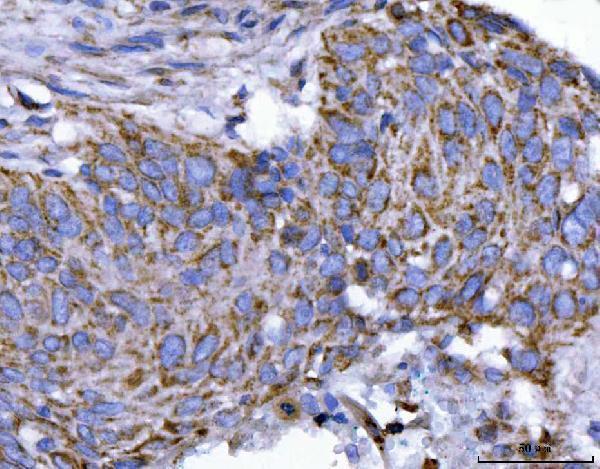
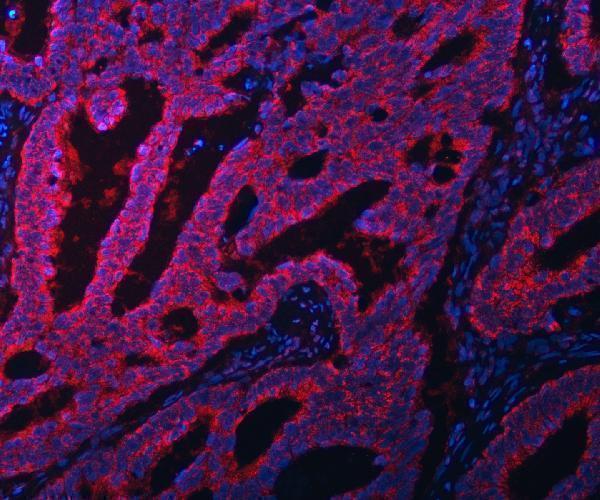
Anti-EIF3A antibodies have IHC images from paraffin-embedded human colorectal and esophageal cancers and mouse and rat brain (A02339-3 IHC captions); IF images cover human intestinal cancer (A02339-3 IF caption).

Real IHC data IHC analysis of EIF3A using anti-EIF3A antibody (A02339-3). EIF3A was detected in a paraffin-embedded section of human colorectal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-EIF3A Antibody (A02339-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-EIF3A Antibody ®
Cat # A02339-3
Real IF data Immunofluorescent analysis using the Antibody at 1:50 dilution.
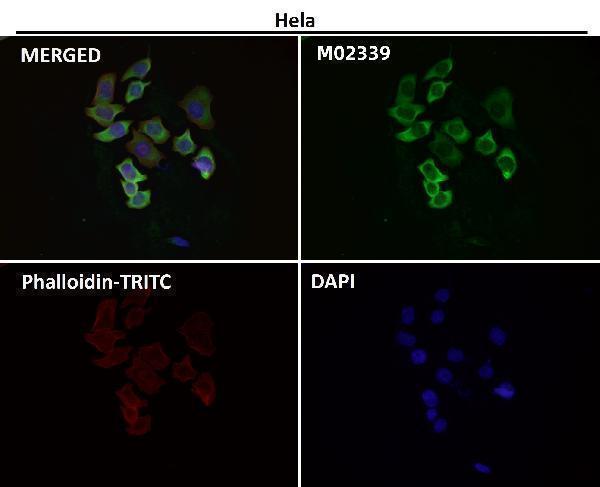
Anti-eIF3A Rabbit Monoclonal Antibody
Cat # M02339

A02339-3 has IHC images of paraffin-embedded human colorectal adenocarcinoma, esophageal squamous carcinoma, mouse brain and rat brain, plus an IF image of paraffin-embedded human intestinal cancer (A02339-3 image captions). M02339 lists human, mouse and rat reactivity and IHC/ICC/IF applications; its IF captions report dilutions but do not identify samples (M02339 catalog; M02339 IF captions).

Which to pick: For tissue IHC, choose A02339-3: its paraffin-section captions document EDTA pH 8 retrieval and 2 μg/ml primary antibody; the fixative is unreported (A02339-3 IHC captions). For IF/ICC, consider M02339 when a rabbit monoclonal is preferred: ICC/IF is listed and IF figures are provided, though their samples are unidentified (M02339 catalog; M02339 IF captions). For cross-species IHC, A02339-3 has human, mouse and rat tissue images; M02339 lists reactivity with all three species but has no IHC image in the supplied catalog (A02339-3 IHC captions; M02339 catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14152 (EIF3A_HUMAN, Eukaryotic translation initiation factor 3 subunit A).
  2. Human Protein Atlas. EIF3A tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. EIF3A subcellular location (ICC-IF): Mainly localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. EIF3A antibody validation summary (2 antibodies).
  5. Systematic analyses of the role of prognostic and immunological EIF3A, a reader protein, in clear cell renal cell carcinoma. Cancer cell international 2021 — PMC8684683.
  6. Eukaryotic Translation Initiation Factor 3a (eIF3a) Promotes Cell Proliferation and Motility in Pancreatic Cancer. Journal of Korean medical science 2016 — PMC4999401.
  7. Knockdown of eIF3a alleviates pulmonary arterial hypertension by inhibiting endothelial-to-mesenchymal transition via TGFβ1/SMAD pathway. Journal of translational medicine 2025 — PMC12065328.
  8. The prognostic value of altered eIF3a and its association with p27 in non-small cell lung cancers. PloS one 2014 — PMC4005749.
  9. PubMed PMID:9150439 — UniProt-cited evidence.
  10. PubMed PMID:9054404 — UniProt-cited evidence.
  11. PubMed PMID:8590280 — UniProt-cited evidence.