EIF4G1 / Eukaryotic translation initiation factor 4 gamma 1 · IHC design guide

Design Immunohistochemistry for EIF4G1

Plan chromogenic EIF4G1 IHC in paraffin sections using the catalog antibody at 0.5–1 μg/mL (datasheet A01351-2). Assess mainly cytoplasmic staining against documented tissue patterns (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
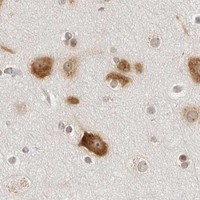
Immunohistochemistry protocol sheet for EIF4G1 (IHC for EIF4G1): expected localisation Mainly cytoplasmic in most tissues (HPA tissue IHC), antibody A01351-2, validated IHC image, and IHC protocol steps
Printable EIF4G1 IHC protocol sheet — expected localisation Mainly cytoplasmic in most tissues (HPA tissue IHC), antibody A01351-2, controls and protocol steps. Open the full EIF4G1 IHC guide →

EIF4G1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic in most tissues (HPA tissue IHC)
Staining pattern Glandular cells: mainly cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01351-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Antibody staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Low tissue specificity at RNA level (HPA tissue RNA)
Isoform / epitope 8 isoforms; confirm epitope coverage (UniProt)
Section 1

Recommended EIF4G1 IHC & IF Protocols

The catalog antibody protocol uses citrate pH 6 heat retrieval (datasheet A01351-2). The four published EIF4G1 IHC protocols below provide tissue-specific starting points (PMC3580022; PMC7957198; PMC5036801; PMC2873436).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human intestinal cancer tissues; fixative not specified (datasheet A01351-2)
FixationImage fixative and duration unreported (datasheet A01351-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01351-2)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01351-2)
Primary antibodyRabbit anti-EIF4G1, 0.5-1μg/ml (datasheet A01351-2)
Primary incubationOvernight at 4 °C (datasheet A01351-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01351-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEIF4G1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval for the catalog antibody (datasheet A01351-2). Assess pH 9 steam retrieval separately when following the brain-tissue study (PMC3580022).
Section 2

What Is the Expected EIF4G1 Staining Pattern?

EIF4G1 staining should be mainly cytoplasmic across many tissues, including glandular cells, neurons and hematopoietic cells (HPA: mainly cytoplasmic in most tissues; HPA: High in these cell types). UniProt also lists nuclear and stress granule localisation, so assess those patterns in context rather than treating them as the routine IHC result (UniProt Q04637: subcellular location). EIF4G1 has no transmembrane segment (UniProt Q04637: topology). Tissue IHC reliability is Approved, with medium consistency against RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Clear cytoplasmic staining in colon or appendix glandular cells, with cell outlines and tissue structure intact.This fits the reported compartment and high staining in these cells (HPA: mainly cytoplasmic in most tissues; HPA: High in colon and appendix glandular cells). Judge staining within the relevant cells, rather than from the overall darkness of a section (standard IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal, across the section.This differs from the main tissue IHC pattern and warrants checking specificity and counterstain interpretation (HPA: mainly cytoplasmic in most tissues; standard IHC practice). Nuclear localisation is listed by UniProt, so a nuclear component alone does not establish an artefact (UniProt Q04637: subcellular location).
Strong staining in cells where the expected cell population is absent, or staining that ignores tissue boundaries.Consider cross-reactivity or endogenous detection activity, then compare with a no-primary control (standard IHC practice). EIF4G1 is broadly expressed, and HPA supplies low-staining examples rather than confirmed negative tissues; staining outside one listed high-staining cell type is not, by itself, a false positive (HPA: low tissue specificity; HPA: tissue IHC levels).
Diffuse colour covers stroma, lumina or the whole section without a discernible cellular pattern.Treat this as background until controls show otherwise; excess detection signal or inadequate blocking can obscure cellular localisation (standard IHC practice). It does not match HPA's mainly cytoplasmic tissue pattern (HPA: tissue IHC profile).
Little or no staining in an intact section containing colon glandular cells or cerebellar Purkinje cells.These are reported high-staining populations, so check the staining run and whether the intended cells are present (HPA: High in colon glandular cells and cerebellar Purkinje cells; standard IHC practice). A single blank section cannot establish absence of EIF4G1 expression (standard IHC practice).
💡Expected EIF4G1 appearanceA convincing positive shows discernible, predominantly cytoplasmic signal in an HPA high-staining population such as colon glandular cells; widespread structure-free colour or staining confined to an unexpected compartment calls for controls before interpretation (HPA: tissue IHC profile; HPA: High in colon glandular cells; standard IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA reports high staining in several glandular, neuronal and hematopoietic populations, but low staining in cardiomyocytes and adipocytes (HPA: tissue IHC levels). Low is not a validated negative control, and RNA specificity is low across tissues (HPA: tissue IHC levels; HPA: RNA specificity).
Compartment and protein topologyThe routine tissue pattern is mainly cytoplasmic; UniProt also lists nucleus and stress granules (HPA: tissue IHC profile; UniProt Q04637: subcellular location). No transmembrane segment or signal peptide is annotated, so a membrane-only or secretory pattern needs scrutiny (UniProt Q04637: topology and processing).
Isoforms and antibody epitopeUniProt lists eight EIF4G1 isoforms and multiple modified residues (UniProt Q04637: isoforms and modified residues). The supplied record gives no epitope for the antibody being used, so isoform recognition and modification-dependent staining cannot be predicted from these annotations alone (UniProt Q04637: isoforms and modified residues; supplied antibody data: epitope unreported).
Strength of tissue evidenceHPA rates its tissue IHC profile Approved but reports medium consistency with RNA expression (HPA: tissue IHC reliability). HPA028487 and CAB014774 are IHC Approved; that status does not establish that every unusual pattern is specific (HPA: antibody validation; standard IHC practice).
IF/ICC Q: What localisation should be expected?A: Mainly cytosolic staining; HPA calls the cytosol location Supported (HPA: ICC-IF subcellular summary). This is supporting context for localisation, while the primary interpretation here concerns chromogenic tissue IHC (HPA: tissue IHC profile).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in an HPA high-staining cell population.The relevant cells may be missing, or a staining-run step may have failed (HPA: tissue IHC levels; standard IHC practice).Confirm cell identity and section integrity, then review antibody dilution, detection and an appropriate run control (standard IHC practice). No EIF4G1-specific retrieval or fixation sensitivity is supplied (HPA: tissue IHC record; UniProt Q04637: record).
Signal is faint but remains cytoplasmic.A faint result alone cannot distinguish weak staining from a run issue; HPA reports different staining levels by cell type (HPA: tissue IHC levels; standard IHC practice).Compare the same cell population with a high-staining reference section processed in the run, and assess signal against background (HPA: tissue IHC levels; standard IHC practice).
Brown deposit appears in a no-primary control.Endogenous detection activity or nonspecific detection reagents can produce chromogenic signal (standard IHC practice).Review the detection system and its blocking steps before assigning the deposit to EIF4G1 (standard IHC practice).
Background obscures cellular detail.Nonspecific binding or overly strong detection can mask localisation (standard IHC practice).Review blocking, washing, antibody dilution and detection conditions using controls; score only distinguishable cellular signal (standard IHC practice).
A section looks predominantly nuclear or membrane-localised.The pattern differs from HPA's mainly cytoplasmic tissue profile; nuclear localisation is nevertheless listed by UniProt (HPA: tissue IHC profile; UniProt Q04637: subcellular location).Check counterstain and control sections, then compare the same cell type's cytoplasmic staining before calling the pattern specific (standard IHC practice).
A low-staining cell population gives measurable colour.HPA labels some populations Low, not negative; background can also make weak colour difficult to interpret (HPA: tissue IHC levels; standard IHC practice).Compare cellular localisation and intensity with controls and a reported high-staining population; do not use Low as a zero-signal threshold (HPA: tissue IHC levels; standard IHC practice).

Sample controls for EIF4G1 IHC & IF

🧪Run bone marrow first and expect staining in hematopoietic cells (HPA: High in bone marrow hematopoietic cells). HPA detects EIF4G1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and regard cells with counterstain alone as background rather than a validated EIF4G1-negative cell type (HPA: no negative rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: EIF4G1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EIF4G1 in A-431, U-251MG, U2OS, KOLF2.1J, U2OS, siRNA 1 (10x), U2OS, siRNA 2 (10x), U2OS, scrambled (10x), NIH 3T3, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section, a concentration-matched rabbit IgG isotype section, and identically processed EIF4G1 knockout material if available (caption: rabbit primary; standard IHC practice). Quench endogenous peroxidase in bone marrow before DAB detection and assess endogenous biotin when using the caption’s avidin–biotin detection method (selected tissue-IHC caption; standard IHC practice).
⚠️Feasibility: No EIF4G1-specific fixation window or fixation effect is reported, and the selected A01351-2 paraffin-section caption does not state the fixative (selected tissue-IHC caption). That caption provides a starting retrieval condition of citrate buffer at pH 6 for 20 minutes; it does not establish that retrieval is required under every condition (selected tissue-IHC caption). HPA ICC-IF images support a cytosolic localization check, but the supplied evidence does not establish whether frozen sections or IF are easier than paraffin IHC; endogenous peroxidase in marrow myeloid cells can complicate DAB interpretation (HPA: supported cytosol and ICC-IF images; standard IHC practice).

HPA tissue IHC evidence for EIF4G1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: EIF4G1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced EIF4G1 IHC Tips

Troubleshoot EIF4G1 staining in paraffin section IHC using the catalog antibody’s tissue image and reference localization data.

What retrieval should I try first if EIF4G1 staining is weak?
Start with heat mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A01351-2). The catalog antibody produced staining in a paraffin section of human intestinal cancer tissue with this retrieval, followed by 1 µg/mL primary antibody overnight at 4°C (A01351-2 image caption). If staining is weak, first verify heating, buffer pH, and section coverage across the run (standard IHC practice). Compare any stronger retrieval condition on adjacent sections because increased signal can also increase background or damage tissue architecture (standard IHC practice).
Could fixation explain weak or uneven EIF4G1 staining?
Target specific sensitivity to fixation is unknown from the supplied evidence; the catalog image identifies a paraffin section but does not state its fixative (A01351-2 image caption). Record the fixative, fixation duration, and processing history for each block before comparing staining intensity (standard IHC practice). On adjacent sections, repeat citrate retrieval at pH 6 for 20 minutes and hold antibody concentration and detection constant while checking whether the uneven pattern persists (datasheet A01351-2; standard IHC practice). Interpret a difference between blocks cautiously until a control section processed alongside them shows that the staining run worked (standard IHC practice).
Should EIF4G1 staining appear in nuclei or cytoplasm?
Expect mainly cytoplasmic staining in tissue sections (HPA tissue IHC: mainly cytoplasmic expression in most tissues). Cytosol is the supported main location in cell imaging, while UniProt also lists nucleus and stress granules (HPA subcellular: cytosol supported; UniProt Q04637 subcellular). Score cytoplasmic and nuclear signal separately, and inspect the same cells at higher magnification before accepting an apparent nuclear pattern (standard IHC practice). If nuclear staining dominates without convincing cytoplasmic signal, compare a matched control section and assess counterstain overlap and detection background before assigning it to EIF4G1 (standard IHC practice; HPA tissue IHC: mainly cytoplasmic).
Could EIF4G1 isoforms or epitope changes affect staining?
EIF4G1 has 8 annotated isoforms, so an antibody may not recognize every form equally if its epitope varies among them (UniProt Q04637 isoforms; standard immunostaining principle). The supplied catalog image does not identify the recognized epitope, so its isoform coverage cannot be inferred from tissue staining (A01351-2 image caption). UniProt lists multiple modified residues, including phosphorylation and methylation, but their effects on this antibody’s binding are unreported (UniProt Q04637 modified residues; A01351-2 image caption). For a discrepant specimen, compare antibodies with documented, distinct epitopes on adjacent sections while keeping retrieval and scoring consistent (standard IHC practice).
How should I adapt EIF4G1 localization checks for multiplex IF?
Use the separate IF/ICC workflow to examine EIF4G1 alongside a marker identifying the expected cell population, such as an epithelial marker when assessing glandular cells (HPA tissue IHC: high in colon glandular cells; standard IF practice). Choose a fluorophore whose signal is distinguishable from the specimen’s autofluorescence, and include single stain and unstained controls (standard IF practice). EIF4G1 is intracellular and has no transmembrane segment, so permeabilize the plasma membrane sufficiently for antibody access to its cytosolic epitope while checking preservation of cellular structure (UniProt Q04637 topology; HPA subcellular: cytosol supported; standard IF practice). IF fixation conditions and this antibody’s IF performance are not established by the supplied IHC caption (A01351-2 image caption).
How can I reduce diffuse or misleading DAB background?
The catalog image used 10% goat serum blocking, a biotinylated goat anti rabbit secondary, streptavidin biotin detection, and DAB (A01351-2 image caption). If background is widespread, inspect a no primary control and check whether secondary antibody binding or the detection system contributes signal (standard IHC practice). Include a peroxidase block before DAB development and assess whether endogenous biotin contributes to staining with the chosen detection chemistry (standard chromogenic IHC practice). Maintain the documented 1 µg/mL primary incubation as a reference while optimizing washes and detection exposure on adjacent sections (A01351-2 image caption; standard IHC practice).
How should I quantify EIF4G1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring because tissue IHC is mainly cytoplasmic and expression varies among cell types (HPA tissue IHC: mainly cytoplasmic expression; HPA tissue IHC cell profiles). For cytoplasmic DAB, report the percentage of positive cells and an intensity weighted H-score using the same thresholds across specimens (standard IHC practice). If cell counts differ substantially, report positive cells per mm² of viable tissue or the fraction of positive cells within the annotated population (standard IHC practice). Normalize comparisons to the same tissue area definition, staining batch controls, and image acquisition settings; exclude folds and necrotic regions (standard IHC practice).
When is EIF4G1 staining credible rather than an artefact?
A credible pattern is predominantly cytoplasmic and occurs in identifiable viable cells, consistent with tissue IHC and supported cytosolic localization (HPA tissue IHC: mainly cytoplasmic; HPA subcellular: cytosol supported). High staining in glandular cells of colon or appendix can serve as a reference pattern, while low staining in adipocytes should not be treated as assay failure by itself (HPA tissue IHC: colon and appendix glandular cells High; adipocytes Low). Be cautious with isolated nuclear staining, section edges, necrotic regions, or pigment that appears in a no primary control (standard IHC practice; HPA tissue IHC: mainly cytoplasmic). Check endogenous peroxidase and detection controls before interpreting DAB deposits as EIF4G1 (standard chromogenic IHC practice).
Boster reagents

Best EIF4G1 / Eukaryotic translation initiation factor 4 gamma 1 IHC Antibodies

A01351-2 has IHC images from human cancer tissues and mouse intestine, plus an IF/ICC image from U20S cells (catalog image captions).

Real IHC data IHC analysis of EIF4G1 using anti-EIF4G1 antibody (A01351-2). EIF4G1 was detected in paraffin-embedded section of human intestinal cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-EIF4G1 Antibody (A01351-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-EIF4G1 Antibody ®
Cat # A01351-2

A01351-2 is listed for IHC in human, mouse and rat, with paraffin section images from human intestinal, mammary and lung cancers and mouse intestine (catalog applications, reactivity and IHC captions). Its IF/ICC image shows U20S cells (catalog IF caption).

Which to pick: Choose A01351-2 for paraffin section IHC; its tissue captions use citrate retrieval at pH 6 for 20 minutes and 1 μg/ml primary antibody, but do not report the fixative (catalog IHC captions). For IF/ICC, the same SKU has a U20S cell image using 2 μg/ml primary antibody (catalog IF caption). For work across species, the catalog lists human, mouse and rat reactivity, while the supplied IHC images document human and mouse samples (catalog reactivity and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q04637 (IF4G1_HUMAN, Eukaryotic translation initiation factor 4 gamma 1).
  2. Human Protein Atlas. EIF4G1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. EIF4G1 subcellular location (ICC-IF): Mainly localized to the cytosol..
  4. Human Protein Atlas. EIF4G1 antibody validation summary (3 antibodies).
  5. Sequence variants in eukaryotic translation initiation factor 4-gamma (eIF4G1) are associated with Lewy body dementia. Acta neuropathologica 2013 — PMC3580022.
  6. Elevation of EIF4G1 promotes non-small cell lung cancer progression by activating mTOR signalling. Journal of cellular and molecular medicine 2021 — PMC7957198.
  7. Characterization of the Expression of the RNA Binding Protein eIF4G1 and Its Clinicopathological Correlation with Serous Ovarian Cancer. PloS one 2016 — PMC5036801.
  8. Over-expression of eukaryotic translation initiation factor 4 gamma 1 correlates with tumor progression and poor prognosis in nasopharyngeal carcinoma. Molecular cancer 2010 — PMC2873436.
  9. PubMed PMID:1429670 — UniProt-cited evidence.
  10. PubMed PMID:9857202 — UniProt-cited evidence.
  11. PubMed PMID:9418880 — UniProt-cited evidence.