ELOA / Elongin-A · IHC design guide

Design Immunohistochemistry for ELOA

Plan chromogenic IHC for ELOA in paraffin sections using its observed nuclear and nucleolar tissue pattern (HPA tissue IHC). Purkinje cells, placental trophoblastic cells and stomach glandular cells show high staining and can guide tissue selection (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ELOA (IHC for ELOA): expected localisation Nuclear and nucleolar tissue staining (HPA tissue IHC), antibody A31715, validated IHC image, and IHC protocol steps
Printable ELOA IHC protocol sheet — expected localisation Nuclear and nucleolar tissue staining (HPA tissue IHC), antibody A31715, controls and protocol steps. Open the full ELOA IHC guide →

ELOA Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and nucleolar tissue staining (HPA tissue IHC)
Staining pattern Widespread nuclear and nucleolar staining (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Ovary+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope Two isoforms; epitope impact is undetermined (UniProt)
Section 1

Recommended ELOA IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet) with three published ELOA tissue IHC protocols (PMC9664729; PMC8368010; PMC10557880).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A31715)
FixationImage fixative and duration unreported (datasheet A31715); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ELOA, 1:50-1:200 (datasheet A31715)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultELOA-positive staining in purkinje cells of cerebellum (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear and nucleolar expression. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 retrieval at 95–98 °C for 20 min for nuclear ELOA (page retrieval rule; UniProt Q14241).
Section 2

What Is the Expected ELOA Staining Pattern?

ELOA is a nuclear transcription elongation factor with no transmembrane segment (UniProt Q14241). In paraffin sections, expect widespread nuclear and nucleolar staining, including strong staining in cerebellar Purkinje cells, placental trophoblastic cells, and stomach glandular cells (HPA tissue IHC: High). HPA rates its tissue IHC profile Approved, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Clear nuclear and nucleolar staining in Purkinje cells, trophoblastic cells, or stomach glandular cells.This matches the reported ELOA tissue pattern: each listed cell population has High staining (HPA tissue IHC). Evaluate the signal within identified cells; a strong nucleus elsewhere does not establish that the expected positive cell population stained.
Predominantly cytoplasmic, membranous, or extracellular staining, with little nuclear signal.Treat this as a compartment mismatch requiring a specificity check: UniProt places ELOA in the nucleus and reports no transmembrane segment (UniProt Q14241). Cytosolic signal is listed as uncertain in ICC-IF and does not establish a cytoplasmic IHC pattern (HPA subcellular).
Strong signal in ovarian stroma, smooth muscle cells, or splenic red pulp cells.These cell populations are listed as Not detected (HPA tissue IHC). Check cell identification and compare a reagent control before interpreting the signal as ELOA; cross-reactivity or endogenous detection activity is possible (general IHC practice).
Diffuse colour across nuclei, cytoplasm, and surrounding tissue, obscuring cell boundaries.This does not resolve the reported nuclear and nucleolar distribution (HPA tissue IHC). Background from antibody binding, detection reagents, or residual chromogen should be assessed with controls and reagent optimisation (general IHC practice).
No nuclear signal in an otherwise evaluable Purkinje cell, trophoblastic cell, or stomach glandular cell area.That conflicts with the High staining reported for those cells (HPA tissue IHC). First check the run and tissue identification; the Approved profile has only medium consistency with RNA data, so an individual negative result needs confirmation (HPA tissue IHC).
💡Expected ELOA appearanceCall a result positive when identifiable Purkinje, trophoblastic, or stomach glandular cells show strong nuclear and nucleolar staining (HPA tissue IHC: High); isolated cytoplasmic or membranous colour is a specificity concern given ELOA's nuclear location (UniProt Q14241).
How each factor affects the staining
Tissue and cell choice (HPA tissue IHC).Purkinje cells, trophoblastic cells, and stomach glandular cells are High; ovarian stroma, smooth muscle cells, and splenic red pulp cells are Not detected (HPA tissue IHC). Compare the named cells, rather than treating every cell in a tissue as equivalent.
Antibody evidence (HPA antibodies; HPA tissue IHC).HPA005910 is Approved for IHC, and the overall tissue profile is Approved with medium staining–RNA consistency (HPA antibodies; HPA tissue IHC). These labels support use of the pattern as a reference but do not establish that every tissue section will agree.
Isoforms and unmapped epitope (UniProt Q14241; HPA antibodies).UniProt lists two ELOA isoforms, while the supplied antibody record gives no epitope position (UniProt Q14241; HPA antibodies). These data cannot establish whether the antibody detects both isoforms or predict an isoform-specific IHC pattern.
Processing and post-translational modifications (UniProt Q14241).UniProt lists one chain spanning residues 1–772, no signal peptide or propeptide, and several modified residues (UniProt Q14241). With no supplied epitope map, neither cleavage-dependent staining nor a modification-dependent loss of staining can be predicted.
Antigen retrieval and fixation (general IHC practice).Record the retrieval conditions and compare them within a controlled run when troubleshooting weak staining (general IHC practice). The supplied UniProt and HPA records give no ELOA-specific fixation sensitivity or retrieval condition.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No stain in an identified High-staining cell population (HPA tissue IHC).The staining run may have failed, or the expected cells may be absent from the examined area (general IHC practice). HPA's Approved profile has medium staining–RNA consistency (HPA tissue IHC).Confirm cell identity and tissue quality, then review primary antibody, retrieval, detection, and counterstain steps against the run record; repeat with controls (general IHC practice).
Colour is stronger in cytoplasm than in nuclei.The pattern conflicts with nuclear ELOA localisation (UniProt Q14241). Excess background or nonspecific binding can create a misleading compartment pattern (general IHC practice).Compare a primary-antibody omission control, reduce excessive staining where indicated, and judge whether identifiable nuclei retain the expected signal (general IHC practice; HPA tissue IHC: nuclear and nucleolar).
Ovarian stroma, smooth muscle, or splenic red pulp cells stain strongly.HPA lists these cells as Not detected (HPA tissue IHC). Misidentified cells, cross-reactivity, or endogenous detection activity are possible explanations (general IHC practice).Verify cell identity and compare primary-antibody omission and detection controls; review blocking appropriate to the detection chemistry (general IHC practice).
A diffuse deposit obscures nuclei throughout the section.Diffuse colour cannot establish the nuclear and nucleolar pattern (HPA tissue IHC). Excess primary antibody, incomplete washing, or detection background are general possibilities (general IHC practice).Check control sections, washing, reagent exposure, and primary antibody concentration; optimise one variable at a time while preserving a known-positive comparison (general IHC practice; HPA tissue IHC: High populations).
The slide shows nuclear signal, but cell populations differ in intensity.Variation is plausible: HPA reports High, Medium, Low, and Not detected categories across named cell populations, despite a ubiquitous nuclear and nucleolar profile (HPA tissue IHC).Score identified cell populations separately and compare each with its HPA category; avoid using the overall tissue appearance to assign a category to every cell (HPA tissue IHC).
Q: Should an ICC-IF speckled or cytosolic image determine the IHC call?A: HPA supports nuclear speckles in ICC-IF but labels cytosol uncertain; tissue IHC reports nuclear and nucleolar expression (HPA subcellular; HPA tissue IHC).Interpret the paraffin-section result against the tissue IHC compartment and named cell populations; use the ICC-IF observation only as context for that separate assay (HPA tissue IHC; HPA subcellular).

Sample controls for ELOA IHC & IF

🧪Run cerebellum first and assess Purkinje cells for ELOA staining (HPA: High in Purkinje cells); use smooth muscle as the negative tissue (HPA: Not detected in smooth muscle cells). On the cerebellum slide, any nuclei without specific staining should show counterstain and background only; these provide an internal background reference, not a proven ELOA-negative cell population (standard IHC practice).
Positive control tissue: Cerebellum (Purkinje cells, HPA High)
Negative control tissue: Ovary (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ELOA in A-431, U-251MG, U2OS, with annotated localisation: Nuclear speckles (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and clonality; confirm specificity with ELOA knockout material or a validated peptide-blocking control (standard IHC practice). Block endogenous peroxidase and check the cerebellum section for residual chromogen background (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A31715 paraffin-section caption does not state a fixative (A31715 caption). Retrieval dependence is unreported, so optimize antigen retrieval empirically for the paraffin IHC assay; the supplied evidence does not establish that frozen sections or IF are easier (A31715 caption; standard IHC practice). If evaluating IF in cerebellum, distinguish neuronal autofluorescence from nuclear signal (standard IF practice; HPA: nuclear speckles supported).

HPA tissue IHC evidence for ELOA

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced ELOA IHC Tips

Troubleshoot ELOA staining by checking nuclear localisation, processing conditions and cell specific controls before comparing chromogenic IHC results (UniProt Q14241; HPA tissue IHC).

How should I retrieve ELOA in paraffin sections when nuclear staining is weak?
Use Tris-EDTA at pH 9.0 for heat-induced epitope retrieval at 95–98 °C for 20 min (this page’s antigen-retrieval protocol). Let sections cool in retrieval buffer, then compare staining with a matched section processed in the same run (standard IHC practice). Because ELOA is nuclear and HPA reports nuclear and nucleolar tissue staining, assess nuclei before judging diffuse colour as rescue (UniProt Q14241 subcellular location; HPA tissue IHC). If nuclei remain weak, check primary incubation and detection controls before changing retrieval conditions (standard IHC practice). Record any changed retrieval condition alongside the original protocol when comparing sections (standard IHC practice).
Can I change fixation to recover weak ELOA staining?
ELOA-specific fixation sensitivity is unknown from the supplied evidence, so treat fixation changes as an experiment rather than an established rescue (supplied ELOA evidence). The A31715 image shows staining in paraffin-embedded human breast carcinoma at 1:100, but its caption does not state the fixative (A31715 tissue-IHC caption). For new specimens, keep fixative and fixation duration consistent across comparison groups and document both with processing times (standard IHC practice). If staining varies between blocks, compare an established positive section in the same staining run before attributing the difference to fixation (standard IHC practice). HPA staining patterns cannot establish a fixation requirement for this antibody (HPA tissue IHC).
Where should I expect ELOA staining within cells?
Prioritise nuclear signal when reading chromogenic sections, since ELOA is annotated in the nucleus and at sites of DNA damage (UniProt Q14241 subcellular location). HPA describes ubiquitous nuclear and nucleolar tissue staining, with high signal in cerebellar Purkinje cells and placental trophoblastic cells (HPA tissue IHC). HPA cell imaging places ELOA mainly in nuclear speckles and lists cytosolic localisation as uncertain, so diffuse cytoplasmic colour warrants a control review (HPA subcellular). Compare nuclei and cytoplasm within the same cell population at the same exposure and chromogen development conditions (standard IHC practice). A nuclear pattern supports localisation but does not alone prove antibody specificity (standard IHC practice).
Could ELOA isoforms or modifications explain discordant nuclear staining?
ELOA has 2 annotated isoforms, so check the antibody’s stated immunogen or epitope before assuming it recognises both (UniProt Q14241 isoforms; standard IHC practice). The protein contains a TFIIS N-terminal region at residues 4–79 and an F-box at 566–610, which can help place a disclosed epitope (UniProt Q14241 domains). Annotated phosphorylation and acetylation sites mean an epitope near a modified residue deserves separate validation; the supplied evidence does not establish an effect on IHC staining (UniProt Q14241 modified residues). ELOA has no transmembrane segment, signal peptide or propeptide, so interpret a membrane-only pattern cautiously (UniProt Q14241 topology and processing). Compare any alternative antibody against the same sections and scoring rules (standard IHC practice).
How can IF help assess an ambiguous ELOA IHC pattern?
For IF on matched material, pair ELOA with an epithelial marker such as cytokeratin when assessing breast glandular cells, and score marker-positive cells separately (HPA tissue IHC: breast glandular cells show medium ELOA; standard IF practice). Choose a fluorophore channel with low tissue autofluorescence and include an unstained section to measure background (standard IF practice). Permeabilise sufficiently for antibody access to the nuclear epitope, since ELOA has no transmembrane segment and is predominantly nuclear (UniProt Q14241 topology and subcellular location; standard IF practice). HPA reports mainly nuclear speckles in cell imaging, with cytosolic localisation uncertain (HPA subcellular). Optimise IF fixation and permeabilisation independently; the A31715 paraffin IHC caption gives no IF conditions (A31715 tissue-IHC caption).
What should I check when ELOA chromogenic staining looks diffuse or patchy?
Inspect a no-primary control for secondary reagent or chromogen background, and verify that endogenous peroxidase was blocked before DAB development (standard chromogenic IHC practice). Compare nuclear signal with adjacent cytoplasmic colour, since ELOA is annotated as nuclear and HPA tissue staining is nuclear and nucleolar (UniProt Q14241 subcellular location; HPA tissue IHC). Uneven colour at folds, section edges or poorly preserved areas should be assessed against morphology rather than counted as positive cells (standard IHC practice). Titrate antibody concentration and shorten chromogen development if background obscures nuclei, documenting each change (standard IHC practice). The 1:100 value belongs specifically to the A31715 breast carcinoma image (A31715 tissue-IHC caption).
How should I score ELOA across specimens with different cell compositions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and score nuclear staining within that population, because HPA reports different intensities across named tissue cell types (HPA tissue IHC). An H-score combines the percentage of cells at intensity grades 0–3 into a 0–300 score; also report the percentage of nuclear-positive cells (standard IHC practice). If spatial abundance matters, report positive nuclei per mm² of viable analysed tissue and state how regions were selected (standard IHC practice). Normalise counts to the number of eligible nuclei or analysed viable area, and use identical thresholds and chromogen development across specimens (standard IHC practice). No ELOA-specific positivity cutoff is supplied by the evidence (supplied ELOA evidence).
How do I distinguish ELOA-positive cells from staining artefacts?
A plausible positive cell shows nuclear staining in intact morphology, consistent with ELOA’s nuclear annotation and HPA’s nuclear and nucleolar tissue pattern (UniProt Q14241 subcellular location; HPA tissue IHC). Compare the same cell type across sections: HPA reports high staining in placental trophoblastic cells, while ovarian stromal cells are listed as not detected (HPA tissue IHC). Predominantly membranous colour is discordant with ELOA’s lack of a transmembrane segment, and cytosolic localisation has uncertain support (UniProt Q14241 topology; HPA subcellular). Exclude edge staining, necrotic areas and endogenous peroxidase colour using morphology and a no-primary control (standard chromogenic IHC practice). Treat a discordant pattern as provisional until independent antibody or orthogonal evidence supports it (standard IHC practice).
Boster reagents

Best ELOA / Elongin-A IHC Antibodies

The catalog includes an ELOA antibody with an IHC image from paraffin-embedded human breast carcinoma and another with an IF image from MCF7 cells (catalog image captions).

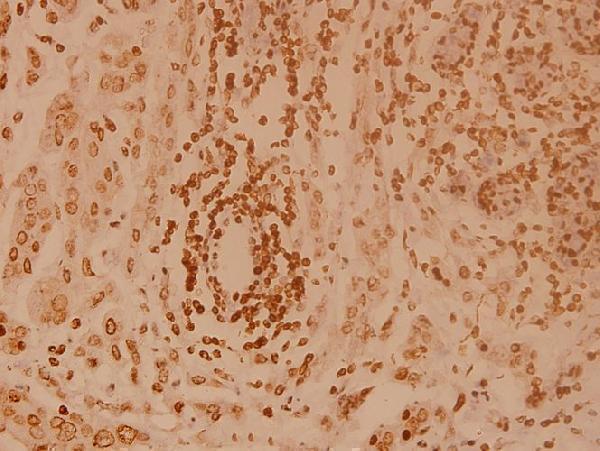
Real IHC data Immunohistochemistry (IHC) analyzes of Elongin A1 (R129) pAb in paraffin-embedded human breast carcinoma tissue at 1:100.
Anti-Elongin A1 (R129) ELOA Antibody
Cat # A31715
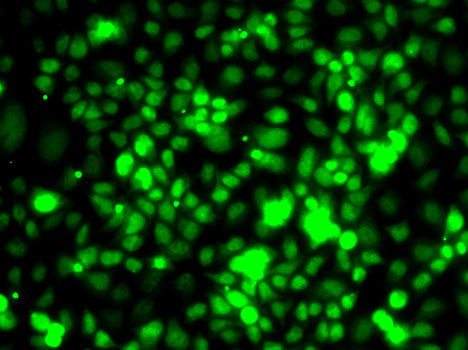
Real IF data Immunofluorescence analysis of MCF7 cells using TCEB3 antibody .
Anti-Elongin A1 ELOA Antibody
Cat # A31715-1

A31715 is listed for human IHC, with an image from paraffin-embedded human breast carcinoma at 1:100 (catalog applications, reactivity and IHC image caption). A31715-1 is listed for IF/ICC in human, mouse and rat, with an IF image from MCF7 cells (catalog applications, reactivity and IF image caption).

Which to pick: Choose A31715 for tissue IHC: its own image shows paraffin-embedded human breast carcinoma, and the fixative is unreported (A31715 IHC image caption). Choose A31715-1 for IF/ICC; it is also the option listed as reactive with mouse and rat, although its IF image shows MCF7 cells only (A31715-1 applications, reactivity and IF image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14241 (ELOA1_HUMAN, Elongin-A).
  2. Human Protein Atlas. ELOA tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ELOA subcellular location (ICC-IF): Mainly localized to the nuclear speckles. In addition localized to the cytosol..
  4. Human Protein Atlas. ELOA antibody validation summary (1 antibodies).
  5. Long noncoding RNA DLGAP1-AS2 promotes tumorigenesis and metastasis by regulating the Trim21/ELOA/LHPP axis in colorectal cancer. Molecular cancer 2022 — PMC9664729.
  6. Large-scale and high-resolution mass spectrometry-based proteomics profiling defines molecular subtypes of esophageal cancer for therapeutic targeting. Nature communications 2021 — PMC8368010.
  7. ELOA promotes tumor growth and metastasis by activating RBP1 in gastric cancer. Cancer medicine 2023 — PMC10557880.
  8. PubMed PMID:8654961 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:16710414 — UniProt-cited evidence.