This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan ELOVL6 IHC in paraffin sections using the observed cytoplasmic tissue pattern (HPA tissue IHC). Compare stained cells with appropriate controls because the tissue staining has uncertain reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in several tissues (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in adipocytes and glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | Caudate+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A06004-1); verify before use. | |
| Caveat | Tissue staining has uncertain reliability (HPA tissue IHC) | |
| Regulation | No expression regulator reported (UniProt) | |
| Isoform / epitope | No isoforms; 1–265 chain, epitope side unassigned (UniProt) |
The catalog antibody’s IHC-P protocol is followed by published ELOVL6 IHC methods for normal, polyp, and COAD tissues (PMC9755665) and paraffin-embedded patient tissues (PMC9937776).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A06004-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ELOVL6, 5 μg/mL (datasheet A06004-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ELOVL6-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control. |
ELOVL6 is a 7-pass endoplasmic reticulum membrane protein (UniProt Q9H5J4 topology and subcellular location). In paraffin-section IHC, expect cytoplasmic staining in selected cell populations, including adipocytes and glandular cells in several tissues (HPA tissue IHC: Medium). Interpret this as a provisional pattern: HPA rates tissue staining reliability Uncertain, with only medium agreement between antibody staining and RNA expression (HPA tissue IHC reliability).
| Cytoplasmic chromogen in adipocytes or glandular cells, with little dominant nuclear staining (HPA tissue IHC: Medium in selected populations). | This fits the reported cytoplasmic profile and the ER membrane location (HPA tissue IHC profile; UniProt Q9H5J4 subcellular location). A fine granular or reticular appearance is plausible for an ER protein, but ordinary chromogenic IHC cannot establish precise organelle colocalisation (standard IHC interpretation). Judge the cell population as well as the compartment. |
| Predominantly nuclear, extracellular, or sharply cell-surface staining instead of cytoplasmic signal (HPA tissue IHC profile). | This conflicts with the reported cytoplasmic staining and ER membrane assignment (HPA tissue IHC profile; UniProt Q9H5J4 subcellular location). Review tissue morphology, chromogen deposits, and controls before assigning ELOVL6 identity (standard IHC practice). A surface-like edge alone does not prove membrane localisation at the organelle level (standard IHC interpretation). |
| Strong staining in a population reported as not detected, such as esophageal squamous epithelium or splenic red-pulp cells (HPA tissue IHC). | Treat unexpected signal as a specificity question, including possible cross-reactivity or endogenous detection activity (standard IHC practice). HPA's 'Not detected' calls describe those sampled cell populations; they do not establish an absolute biological absence (HPA tissue IHC). Compare a reported Medium population and appropriate detection controls on the same run (HPA tissue IHC; standard IHC practice). |
| Uniform haze across tissue, stroma, and empty spaces, obscuring cell boundaries (standard IHC interpretation). | This is a background pattern, not the cell-restricted cytoplasmic profile reported for ELOVL6 (HPA tissue IHC profile). Nonspecific reagent binding, endogenous enzyme activity, or excessive chromogen development can produce broad staining (standard chromogenic IHC practice). Assess the no-primary control and slide morphology before scoring intensity (standard IHC practice). |
| No convincing cytoplasmic signal in adipocytes despite an intact section (HPA tissue IHC: Medium in adipocytes). | A failed positive reference is a run-level warning, although HPA's Uncertain reliability prevents treating any one specimen as guaranteed positive (HPA tissue IHC reliability and adipose-tissue result). Check control-slide performance, reagent delivery, retrieval conditions, and detection before calling the study tissue negative (standard IHC practice). |
| Membrane topology and visual resolution (UniProt Q9H5J4 topology). | ELOVL6 has 7 transmembrane segments and an ER membrane assignment (UniProt Q9H5J4). Cytoplasmic chromogen is compatible with that location, but light-microscope IHC cannot demonstrate that the colored material lies in the ER membrane (standard IHC interpretation). |
| Cell-population differences (HPA tissue IHC). | HPA reports Medium staining in adipocytes, several glandular populations, Purkinje cells, and colon endothelial cells; it reports Low or Not detected staining in other listed populations (HPA tissue IHC). UniProt's 'ubiquitous' tissue-specificity annotation does not imply equal detectable IHC signal in every cell (UniProt Q9H5J4 tissue specificity; HPA tissue IHC). |
| Evidence strength for the staining pattern (HPA tissue IHC; HPA antibody HPA042355). | HPA calls the tissue pattern Uncertain, notes medium staining–RNA consistency, and lists HPA042355 IHC validation as Uncertain (HPA tissue IHC reliability; HPA antibody HPA042355). Use reported positive and negative populations as comparisons, with controls, rather than as definitive proof of antibody specificity (standard IHC interpretation). |
| Processing and fixation evidence (UniProt Q9H5J4 processing; supplied source scope). | UniProt annotates a full-length 1–265 chain, with no signal peptide or propeptide and no annotated isoforms (UniProt Q9H5J4 processing and isoforms). The supplied sources do not establish ELOVL6-specific sensitivity to fixation or retrieval; choose and assess those conditions as general IHC workflow variables (standard IHC practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| Adipocyte reference is blank, and study sections are also blank (HPA tissue IHC: adipocytes Medium). | The run may have failed at staining, retrieval, reagent delivery, or detection; the reference itself is not guaranteed positive in every specimen (standard IHC practice; HPA tissue IHC reliability: Uncertain). | Inspect section integrity and a positive-reference slide; verify the documented IHC-P procedure and reagent steps, then repeat with an appropriate detection control before interpreting biological absence (standard IHC practice). |
| Expected cytoplasmic signal is weak beside heavy counterstain (HPA tissue IHC profile). | Counterstain or chromogen development can make a weak cytoplasmic reaction hard to resolve (standard chromogenic IHC practice). HPA reports Low staining in some populations, including lung macrophages and cardiomyocytes (HPA tissue IHC). | Compare the same cell type across control and study slides; adjust counterstain or development within the validated IHC workflow, then score only clearly resolved cellular signal (standard IHC practice). |
| Nuclei dominate the stain in an otherwise interpretable section (HPA tissue IHC profile). | That compartment disagrees with cytoplasmic HPA staining and UniProt's ER membrane assignment; nonspecific staining or a slide artifact is possible (HPA tissue IHC; UniProt Q9H5J4; standard IHC interpretation). | Check the no-primary control, chromogen deposits, and cell boundaries. Reassess antibody specificity before recording nuclear ELOVL6 localisation (standard IHC practice). |
| A reported Not detected population stains strongly (HPA tissue IHC). | Cross-reactivity or endogenous detection activity is possible, while biological variation cannot be excluded from HPA's limited, Uncertain IHC evidence (standard IHC practice; HPA tissue IHC reliability). | Compare it with a reported Medium population and no-primary control in the same run. Record the exact cell type and compartment rather than treating whole-tissue staining as one result (HPA tissue IHC; standard IHC practice). |
| Diffuse brown haze makes nearly every cell look positive (standard IHC interpretation). | Nonspecific binding, endogenous enzyme activity, or overdevelopment may obscure the cell-restricted pattern (standard chromogenic IHC practice; HPA tissue IHC profile). | Review background in the no-primary control, blocking and wash steps, and chromogen development; repeat scoring only when cellular staining separates from background (standard IHC practice). |
| Can IF/ICC confirm the precise ELOVL6 compartment? (HPA subcellular ICC-IF). | HPA gives only a broad 'Membrane' summary, no main location, and no cell-line ICC-IF images; it cannot verify an ER pattern by imaging here (HPA subcellular ICC-IF). | Use UniProt's ER membrane assignment as the localisation hypothesis and consult the separate IF/ICC guide for that application; do not infer an IF protocol or validated colocalisation from this IHC evidence (UniProt Q9H5J4; HPA subcellular ICC-IF). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot ELOVL6 chromogenic IHC in paraffin sections by checking retrieval, compartmental staining, controls and scoring (UniProt Q9H5J4; HPA tissue IHC).
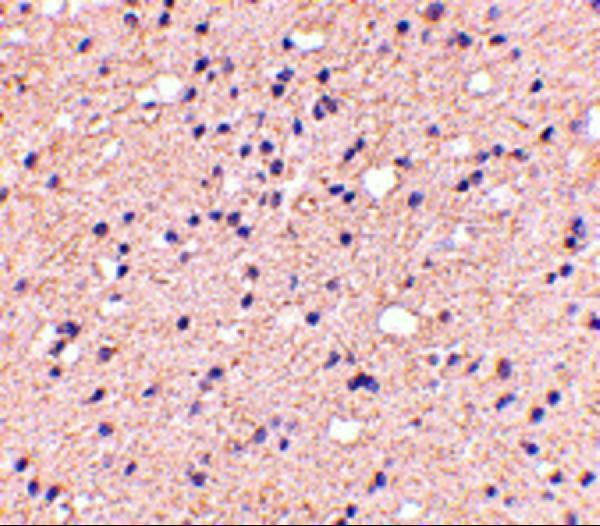
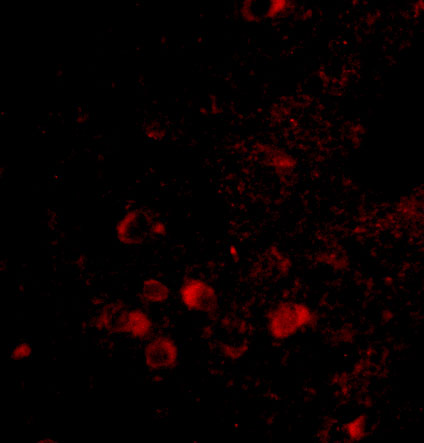
A06004-1 has IHC and IF images from human brain tissue (catalog: image captions) and lists Human, Mouse, and Rat reactivity (catalog: reactivity).
A06004-1 will render with a human brain tissue IHC image at 5 μg/mL (IHC image caption). It also lists IHC-P and IF, with a human brain tissue IF image at 20 μg/mL (catalog: applications; IF image caption).
Which to pick: Choose A06004-1 for paraffin-section IHC: IHC-P is listed, and its own image caption documents human brain tissue staining at 5 μg/mL; the fixative is unreported (catalog: applications; IHC image caption). For IF, its human brain tissue image uses 20 μg/mL; ICC validation and clonality are unreported (IF image caption; catalog: applications, clone). For Mouse or Rat samples, A06004-1 lists reactivity with both species, while the supplied IHC and IF images show Human brain tissue (catalog: reactivity; image captions).