EPHB3 / Ephrin type-B receptor 3 · IHC design guide

Design Immunohistochemistry for EPHB3

Plan EPHB3 staining in paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A04659). Compare staining with high expression in oral mucosa squamous cells and undetected expression in bronchial respiratory epithelial cells (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EPHB3 (IHC for EPHB3): expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC), antibody A04659, validated IHC image, and IHC protocol steps
Printable EPHB3 IHC protocol sheet — expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC), antibody A04659, controls and protocol steps. Open the full EPHB3 IHC guide →

EPHB3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Variable membrane/cytoplasmic staining in squamous and GI epithelia (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04659)
Positive control ⓘ Oral mucosa+4 more · see all
Negative control ⓘ Bronchus+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA expression show medium consistency (HPA tissue IHC)
Regulation Expression regulation not reported (UniProt)
Isoform / epitope No isoforms listed; extracellular versus cytoplasmic epitope matters (UniProt)
Section 1

Recommended EPHB3 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A04659) with four published EPHB3 IHC methods (PMC7226026; PMC8841496; PMC6959498; PMC4917863).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human glioma tissue; fixative not specified (datasheet A04659)
FixationImage fixative and duration unreported (datasheet A04659); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04659); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04659)
Primary antibodyRabbit anti-EPHB3, 2-5 μg/ml (datasheet A04659)
Primary incubationOvernight at 4 °C (datasheet A04659)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04659)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEPHB3-positive staining in squamous epithelial cells of oral mucosa (HPA tissue IHC: High). HPA tissue profile: Membranous and cytoplasmic expression at variable levels in most tissues, including squamous epithelia and the gastrointestinal tract. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A04659); the cited excerpts do not specify retrieval conditions.
Section 2

What Is the Expected EPHB3 Staining Pattern?

EPHB3 is a single-pass receptor with an extracellular region and a cytoplasmic kinase region, so membrane staining is expected (UniProt P54753 topology). In tissue IHC, HPA reports membranous and cytoplasmic staining at variable levels, including high staining in oral squamous epithelium and medium staining in colon glands (HPA tissue IHC). HPA rates the tissue pattern Enhanced, with medium consistency between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Distinct membrane staining, with some cytoplasmic staining, in oral squamous epithelial cells or colon glandular cells (HPA tissue IHC).This fits the reported distribution. Oral squamous epithelial staining is High; colon glandular staining is Medium (HPA tissue IHC). Assess the named cell population and its compartment before scoring the whole section.
Predominantly nuclear staining with little membrane or cytoplasmic signal.A nuclear-only pattern conflicts with the reported membrane location and tissue IHC pattern (UniProt P54753 subcellular location; HPA tissue IHC). Treat it as suspect; check morphology and staining controls before assigning it to EPHB3.
Strong staining in bronchial respiratory epithelial cells or skeletal myocytes.HPA reports EPHB3 as Not detected in those cell populations (HPA tissue IHC). Unexpected signal raises cross-reactivity or endogenous detection activity as possibilities; compare an omission control and a known-positive section before interpreting it.
Diffuse chromogen across cells and surrounding tissue, without a discernible cellular pattern.This obscures the reported membranous and cytoplasmic pattern (HPA tissue IHC). Uneven blocking, detection background or excessive development can produce diffuse staining (general IHC practice); use controls to locate the source.
No discernible staining in oral squamous epithelial cells despite visible, intact epithelium.HPA reports High staining in this population (HPA tissue IHC). A negative result warrants a technical check of retrieval, primary antibody and detection controls (general IHC practice); the reference level does not guarantee every specimen will stain.
💡Expected EPHB3 appearanceCall a positive result when staining is discernible at the membrane, with possible cytoplasmic signal, in oral squamous epithelium at High or colon glands at Medium levels (UniProt P54753 subcellular location; HPA tissue IHC); isolated nuclear staining or uniform background is suspect against that pattern (HPA tissue IHC).
How each factor affects the staining
Receptor topology (UniProt P54753 topology).EPHB3 spans the membrane at residues 560–580; residues 34–559 are extracellular and 581–998 are cytoplasmic (UniProt P54753 topology). The supplied record does not identify the antibody epitope, so topology cannot predict its exact staining accessibility.
Cell population and reference intensity (HPA tissue IHC).Oral squamous epithelial cells stain High, while colon and duodenal glandular cells stain Medium (HPA tissue IHC). Bronchial respiratory epithelial cells and skeletal myocytes are reported Not detected; compare like cell populations when judging a result (HPA tissue IHC).
Tissue IHC validation (HPA antibodies; HPA tissue IHC).HPA008184 is IHC Enhanced; HPA007698 and CAB034350 are IHC Approved (HPA antibodies). The tissue profile has Enhanced reliability with medium staining–RNA consistency (HPA tissue IHC). These labels support a reference pattern, not certainty for each specimen.
Processing and epitope limits (UniProt P54753 processing and glycosylation).The signal peptide covers residues 1–33, and the annotated chain begins at residue 34; glycosylation sites are listed at 351 and 445 (UniProt P54753). Without a supplied epitope or assay comparison, do not infer a retrieval requirement or a staining change from these annotations.
IF/ICC: what pattern is supported? (HPA subcellular ICC-IF; UniProt P54753).The HPA subcellular summary says Membrane, but supplies no ICC-IF image cell lines or main-location detail (HPA subcellular ICC-IF). Membrane localisation is also annotated by UniProt (UniProt P54753 subcellular location); these data do not establish an IF/ICC protocol or image-verified cell pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An oral mucosa section is blank where squamous epithelium is present.That differs from the reported High signal in oral squamous epithelial cells (HPA tissue IHC); a failed assay step is possible (general IHC practice).Check a known-positive section, then verify the recorded retrieval, primary antibody incubation and detection steps (general IHC practice). Do not infer an EPHB3-specific fixation effect from this result.
Colon glands stain less intensely than oral squamous epithelium.HPA reports Medium staining in colon glands and High staining in oral squamous epithelial cells (HPA tissue IHC).Score each specified cell population against its own reference level and compare sections processed in the same run (HPA tissue IHC; general IHC practice).
Signal is confined chiefly to nuclei.That location conflicts with the membrane annotation and the membranous/cytoplasmic tissue profile (UniProt P54753 subcellular location; HPA tissue IHC).Inspect the no-primary control and tissue morphology; repeat with an independently validated IHC antibody if the nuclear pattern persists (general IHC practice; HPA antibodies).
Chromogen appears broadly across cells and tissue spaces.Diffuse background may arise from nonspecific detection or endogenous peroxidase activity in chromogenic IHC (general IHC practice).Run a no-primary control, check endogenous activity blocking and review chromogen development before scoring cell-specific signal (general IHC practice).
Bronchial respiratory epithelial cells stain strongly.HPA reports this cell population as Not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice).Compare a no-primary control and a known-positive tissue, then check whether a second IHC-validated antibody reproduces the cellular pattern (general IHC practice; HPA antibodies).
Glandular cells show cytoplasmic signal with an indistinct membrane edge.Cytoplasmic staining is part of the reported tissue profile, so this finding alone does not establish an artefact (HPA tissue IHC).Confirm that signal follows the glandular cells, examine an appropriately controlled section and record membrane and cytoplasmic staining separately (HPA tissue IHC; general IHC practice).

Sample controls for EPHB3 IHC & IF

🧪Run oral mucosa first; its squamous epithelial cells should stain (HPA: High in oral mucosa squamous epithelial cells). Use bronchus respiratory epithelial cells as the negative tissue (HPA: Not detected); any cells used as internal negatives on the oral mucosa slide should be independently verified as EPHB3-negative and show only background staining (standard IHC practice).
Positive control tissue: Oral mucosa (Squamous epithelial cells, HPA High)
Negative control tissue: Bronchus (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for EPHB3; derive a cell-line control from the positive tissue's cell type (Squamous epithelial cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and an irrelevant primary matched to the test antibody’s host, isotype, clonality, and concentration (standard IHC practice; caption: rabbit primary). Use EPHB3-knockout tissue as a biological negative where available, and block endogenous peroxidase before chromogenic detection, especially if inflammatory cells are present in oral mucosa (standard IHC practice; caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04659 tissue-IHC caption does not state the fixative (caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used for the paraffin-section example, but the caption does not establish that retrieval is required (caption: heat-mediated EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF are easier; assess possible inflammatory-cell peroxidase background when interpreting oral mucosa staining (standard IHC practice).

HPA tissue IHC evidence for EPHB3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Oral mucosa Squamous epithelial cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Colon Glandular cells Medium Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →
Endometrium Glandular cells Low Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced EPHB3 IHC Tips

Use membrane centred staining, matched tissue controls, and the catalog antibody’s paraffin section conditions to troubleshoot EPHB3 chromogenic IHC.

How should I adjust retrieval when EPHB3 staining is weak in paraffin sections?
Start with heat mediated retrieval in EDTA at pH 8.0 (datasheet A04659). The demonstrated paraffin section workflow then used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and DAB detection (caption A04659). If staining remains weak, compare retrieval heating and cooling conditions on adjacent sections while keeping antibody concentration, incubation, and development constant (standard IHC practice). Score both signal and tissue damage: apparent gains at torn edges or in disrupted cells should not outweigh coherent membranous and cytoplasmic staining (HPA: tissue IHC profile; standard IHC practice).
Can fixation explain variable EPHB3 staining between paraffin blocks?
The EPHB3 paraffin section caption does not state a fixative, so target specific sensitivity to fixation is unknown (caption A04659). Record each block’s fixative and processing history, then compare sections using the same EDTA pH 8.0 retrieval, 2 μg/ml primary antibody, and DAB workflow (datasheet A04659; caption A04659). Uneven fixation or processing can alter tissue morphology and antigen accessibility in routine IHC, so inspect preservation before attributing intensity differences to EPHB3 (standard IHC practice). Include comparable control tissue on each run and report any block dependent differences without assigning EPHB3 a specific fixation effect (standard IHC practice).
Which staining compartments are plausible for EPHB3 in tissue sections?
Prioritise cell border staining, with possible cytoplasmic staining, when assessing EPHB3 in chromogenic sections (UniProt P54753: cell membrane localisation; HPA: tissue IHC profile). Its extracellular residues 34–559, transmembrane segment 560–580, and cytoplasmic residues 581–998 support a membrane centred interpretation (UniProt P54753 topology). In tissue, compare the distribution within morphologically identified cells rather than treating every brown deposit as receptor signal (standard IHC practice). HPA reports high staining in oral mucosal squamous epithelial cells and medium staining in colon glandular and cerebral cortical neuronal cells, useful patterns for comparison rather than universal intensity thresholds (HPA: tissue IHC).
How does an unknown antibody epitope affect EPHB3 IHC interpretation?
The supplied antibody caption does not identify its epitope, so staining cannot be assigned to a particular EPHB3 domain (caption A04659). EPHB3 spans an extracellular region at residues 34–559 and a cytoplasmic region at 581–998, with glycosylation sites at 351 and 445 (UniProt P54753 topology and glycosylation). UniProt lists 0 alternative isoforms in this record; that does not establish whether this antibody distinguishes EPHB3 from related receptors (UniProt P54753 isoforms; standard antibody validation practice). For ambiguous staining, seek documented epitope and specificity evidence, then evaluate controls and localisation before making domain specific claims (standard IHC practice).
What should I check before comparing EPHB3 IHC with multiplex IF?
Use the chromogenic paraffin section result as the IHC reference; the supplied A04659 caption provides tissue IHC conditions but no IF validation (caption A04659). In a separate IF optimisation, pair EPHB3 with a marker identifying the expected cell population, such as a neuronal marker when examining cerebral cortical neuronal cells (HPA: cerebral cortex neuronal staining; standard IF practice). Choose fluorophores and channels after checking tissue autofluorescence, and include single stain controls to assess bleed through (standard IF practice). Match permeabilisation to the antibody’s documented epitope: access to residues 581–998 requires intracellular access, while residues 34–559 are extracellular; this antibody’s epitope is unspecified (UniProt P54753 topology; caption A04659).
How can I distinguish EPHB3 signal from chromogenic background?
Begin with the demonstrated 10% goat serum block and 2 μg/ml primary antibody, then compare a no primary control on a matched section (caption A04659; standard IHC practice). The documented detection uses a peroxidase linked secondary and DAB; a peroxidase block is a general precaution for that chemistry, not EPHB3 specific evidence (caption A04659; standard IHC practice). If diffuse brown staining persists, review secondary binding, wash stringency, and DAB development time while holding retrieval at EDTA pH 8.0 (datasheet A04659; standard IHC practice). Interpret residual colour against cell borders and morphology because HPA reports membranous and cytoplasmic EPHB3 staining (HPA: tissue IHC profile).
How should I score EPHB3 staining across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring because EPHB3 tissue staining varies by cell type and includes membranous and cytoplasmic patterns (HPA: tissue IHC profile). Report the percentage of positive cells and intensity separately, or calculate an H-score from percentages at intensity grades 0–3 (standard IHC scoring practice). Normalise counts to the number of evaluable cells in the same defined compartment; for spatial counts, report positive cells per mm² of viable tissue (standard IHC quantification practice). Keep retrieval, antibody incubation, DAB development, and image thresholds consistent, and exclude folds, necrosis, and section edges by prespecified rules (standard IHC practice).
When is brown staining convincing evidence of EPHB3 expression?
Favour reproducible staining at cell borders, with compatible cytoplasmic staining, in intact cells of an identified tissue compartment (UniProt P54753: cell membrane localisation; HPA: tissue IHC profile). Compare likely positive patterns with high oral mucosal squamous epithelial staining or medium colon glandular staining; skeletal muscle myocytes were not detected in the supplied HPA observations (HPA: tissue IHC). Treat isolated nuclear colour, section edge enhancement, and staining in necrotic areas cautiously because they do not establish the reported distribution (HPA: tissue IHC profile; standard IHC practice). Check a no primary control for endogenous enzyme or detection background, and resolve unexpected cell staining with independent validation before assigning it to EPHB3 (standard IHC practice).
Boster reagents

Best EPHB3 / Ephrin type-B receptor 3 IHC Antibodies

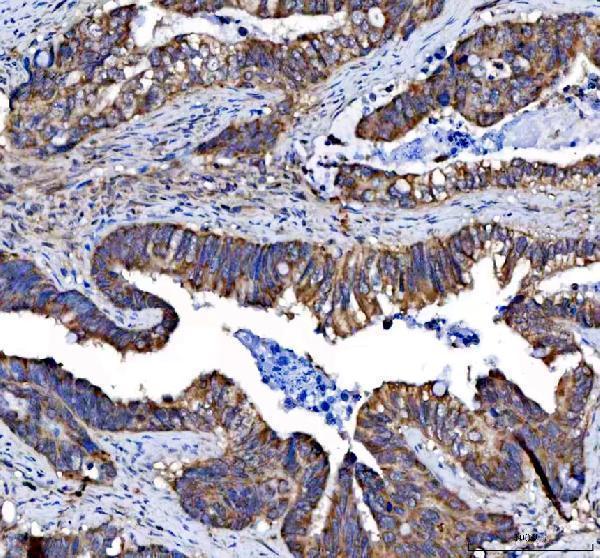
A04659 has human paraffin-section IHC images from glioma and colon cancer tissue (catalog image captions); M04659-1 lists human, mouse and rat ICC/IF reactivity but has no IF image (catalog applications and reactivity).

Real IHC data IHC analysis of EPHB3 using anti-EPHB3 antibody (A04659). EPHB3 was detected in a paraffin-embedded section of human glioma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-EPHB3 Antibody (A04659) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-EPHB3 Antibody ®
Cat # A04659

A04659 will render with IHC images from human glioma and colon cancer paraffin sections (A04659 image captions). M04659-1 will render with a listed ICC/IF application and human, mouse and rat reactivity, but no IF image (M04659-1 applications, reactivity and image alts).

Which to pick: Choose A04659 for chromogenic tissue IHC: its own captions document EDTA pH 8.0 retrieval and DAB detection in human paraffin sections; the fixative is unreported (A04659 image captions). Choose rabbit monoclonal M04659-1 for IF/ICC because that application is listed, though no IF image is supplied (M04659-1 catalog applications, clone and image alts). Both list human, mouse and rat reactivity, but the documented IHC images for A04659 are human only (catalog reactivity; A04659 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P54753 (EPHB3_HUMAN, Ephrin type-B receptor 3).
  2. Human Protein Atlas. EPHB3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. EPHB3 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. EPHB3 antibody validation summary (3 antibodies).
  5. Expression Profile and Prognostic Significance of EPHB3 in Colorectal Cancer. Biomolecules 2020 — PMC7226026.
  6. Knockdown of EphB3 inhibits cell proliferation partly through the AKT signaling pathway and represses epithelial-mesenchymal transition in esophageal squamous cell carcinoma. Translational cancer research 2022 — PMC8841496.
  7. Prognostic and Clinicopathological Significance of EphB3 and Dysadherin Expression in Extrahepatic Cholangiocarcinoma. Cancer management and research 2020 — PMC6959498.
  8. TCF7L1 Modulates Colorectal Cancer Growth by Inhibiting Expression of the Tumor-Suppressor Gene EPHB3. Scientific reports 2016 — PMC4917863.
  9. PubMed PMID:8397371 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:9267020 — UniProt-cited evidence.