EPRS1 / Bifunctional glutamate/proline--tRNA ligase · IHC design guide

Design Immunohistochemistry for EPRS1

Plan EPRS1 IHC on paraffin sections using the catalog antibody at 2–5 μg/mL (datasheet A02967-2). Use lung endothelial cells as a high-staining reference (HPA tissue IHC), and score endothelial and other cell populations separately.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for EPRS1 (IHC for EPRS1): expected localisation Predominantly cytoplasmic in tissue (HPA tissue IHC), antibody A02967-2, validated IHC image, and IHC protocol steps
Printable EPRS1 IHC protocol sheet — expected localisation Predominantly cytoplasmic in tissue (HPA tissue IHC), antibody A02967-2, controls and protocol steps. Open the full EPRS1 IHC guide →

EPRS1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly cytoplasmic in tissue (HPA tissue IHC)
Staining pattern Cytoplasmic in most tissues; prominent in endothelial cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02967-2)
Positive control ⓘ Lung+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across compared paraffin sections. (selected-SKU IHC image A02967-2)
Caveat Endothelial staining may dominate tissue scores (HPA tissue IHC)
Regulation Low tissue specificity (HPA tissue RNA)
Isoform / epitope No annotated isoforms; one full-length chain (UniProt)
Section 1

Recommended EPRS1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02967-2) is followed by published EPRS1 staining protocols for liver cancer (PMC10155449) and kidney biopsies (PMC11671583).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A02967-2)
FixationImage fixative and duration unreported (datasheet A02967-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02967-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02967-2)
Primary antibodyRabbit anti-EPRS1, 2-5μg/ml (datasheet A02967-2)
Primary incubationOvernight at 4 °C (datasheet A02967-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02967-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultEPRS1-positive staining in endothelial cells of lung (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues, highly abundant in endothelial cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A02967-2); neither published excerpt specifies retrieval chemistry (PMC10155449; PMC11671583).
Section 2

What Is the Expected EPRS1 Staining Pattern?

EPRS1 should show predominantly cytoplasmic staining in paraffin sections, with strong signal in lung endothelial cells and elongated or late spermatids (HPA tissue IHC: High). Endothelial cells in cerebral cortex and colon show medium staining (HPA tissue IHC: Medium). HPA rates the tissue profile Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA tissue IHC). A cytosolic pattern fits EPRS1's lack of a transmembrane segment (UniProt P07814).

What am I looking at on my slide?
Cytoplasmic staining is strong in lung endothelial cells or elongated or late spermatids.This matches the reported high staining in those cells (HPA tissue IHC: High). Judge the cellular compartment and cell identity together; intensity alone cannot establish specificity (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal, appears in otherwise positive cells.A nuclear dominant pattern differs from the reported cytoplasmic tissue profile and cytosolic location (HPA tissue IHC; UniProt P07814). Consider localisation or detection artefact and compare with appropriate controls (general IHC practice).
Strong staining appears in adipocytes, cardiomyocytes, or skeletal myocytes.Those cell types were reported as not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible; compare primary omitted and detection controls before interpreting a new biological pattern (general IHC practice).
Broad, diffuse chromogen obscures cell boundaries and the expected endothelial pattern.The distribution cannot be scored reliably when background masks cells (general IHC practice). Reassess blocking, washing, detection background, and antibody concentration before comparing it with HPA's cell resolved tissue profile (HPA tissue IHC).
No staining is visible in lung endothelial cells on the test section.This conflicts with the reported high lung endothelial signal (HPA tissue IHC: High). First check that endothelial cells are present and the positive control worked; a failed run does not establish EPRS1 absence (general IHC practice).
💡Expected EPRS1 appearanceCall the result positive when cytoplasmic chromogen is strongest in lung endothelial cells or elongated or late spermatids (HPA tissue IHC: High), while nuclear dominant signal or strong staining in adipocytes warrants control based review (UniProt P07814; HPA tissue IHC: Adipocytes not detected; general IHC practice).
How each factor affects the staining
Cell and tissue choiceLung endothelial cells and elongated or late spermatids offer reported high signal; appendix glandular, bone marrow hematopoietic, and breast myoepithelial cells show medium signal (HPA tissue IHC). Use the named cell population when comparing sections.
Reference reliabilityHPA labels tissue staining Enhanced but describes only medium consistency between staining and RNA expression (HPA tissue IHC). Its antibody summaries list HPA026490 as IHC Enhanced and HPA030052 as IHC Supported (HPA antibodies); these labels do not validate every new staining condition.
Topology and regulated locationEPRS1 has no transmembrane segment and is mainly cytosolic (UniProt P07814). UniProt reports movement from cytosol to membranes after Ser-999 phosphorylation (UniProt P07814); a membrane associated pattern therefore needs context and controls rather than automatic rejection.
Processing and tissue interpretationUniProt lists no signal peptide or propeptide and one chain spanning residues 1–1512 (UniProt P07814). Those annotations support interpreting intracellular staining, but they do not predict an antibody's epitope accessibility or a paraffin section's staining intensity.
IF/ICC: what localisation should a separate IF guide expect?Mainly cytosolic signal is supported; a sperm mid piece location is additionally approved (HPA subcellular ICC-IF). These observations provide a localisation cross-check, while this section's staining decisions concern chromogenic IHC in paraffin sections (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Lung endothelial cells are unstained.The expected high signal is missing (HPA tissue IHC: Lung endothelial cells High); specimen content or the IHC run may need review (general IHC practice).Confirm endothelial cells on the section and compare a known-positive section processed in the same run; then review retrieval and antibody dilution using the applicable IHC protocol (general IHC practice).
Only nuclear staining is prominent.This differs from the cytoplasmic tissue profile and cytosolic annotation (HPA tissue IHC; UniProt P07814); nonspecific staining or localisation artefact is possible (general IHC practice).Check nuclear counterstain and primary omitted controls, then compare the result with the expected cytoplasmic pattern in a known-positive cell population (general IHC practice; HPA tissue IHC).
Strong signal appears in adipocytes or cardiomyocytes.Both populations are listed as not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity could explain discordant chromogen (general IHC practice).Inspect primary omitted and detection controls, confirm cell identity, and repeat with an IHC validated antibody if the discordance persists (general IHC practice; HPA antibodies: IHC validation).
Chromogen covers tissue uniformly or pools at edges.A spatial pattern dominated by background cannot be matched to HPA's cytoplasmic, cell resolved staining profile (HPA tissue IHC; general IHC practice).Review blocking, washing, antibody concentration, and detection controls; rescore only where individual cells and their cytoplasm can be distinguished (general IHC practice).
A membrane associated pattern replaces the usual cytosolic appearance.UniProt reports phosphorylation dependent movement toward membranes, but the section alone cannot establish Ser-999 phosphorylation (UniProt P07814; general IHC practice).Check whether cytoplasmic staining remains, compare controls and cell types, and describe the observed distribution without assigning a phosphorylation state from chromogen alone (general IHC practice).
A tissue appears uniformly negative despite an expected positive compartment.EPRS1 staining varies by cell population: lung endothelial cells are high, whereas some named populations are not detected (HPA tissue IHC). A whole tissue judgment can miss a small positive population.Identify and score the relevant cells separately, then compare with a known-positive section from the same run before calling a technical failure or biological absence (general IHC practice; HPA tissue IHC).

Sample controls for EPRS1 IHC & IF

🧪Run lung first and look for staining in endothelial cells (HPA: High in lung endothelial cells); use adipose tissue adipocytes as the negative comparator (HPA: Not detected in adipocytes). On the lung slide, treat unstained nonendothelial cells as provisional internal negatives only; HPA does not identify a negative lung cell population (HPA: lung endothelial cells High).
Positive control tissue: Lung (Endothelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show EPRS1 in A-431, U-251MG, U2OS, Sperm, U2OS, siRNA 1 (10x), U2OS, siRNA 1 (40x), U2OS, siRNA 2 (10x), U2OS, siRNA 2 (40x), U2OS, scrambled (10x), U2OS, scrambled (40x), with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (caption: rabbit primary antibody). Use EPRS1 knockout material as a biological specificity control; in blood-containing lung sections, quench endogenous peroxidase and assess endogenous biotin background for the biotinylated secondary and SABC-DAB detection system (caption: biotinylated secondary, SABC, DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A02967-2 paraffin-section caption does not state a fixative. The caption uses heat retrieval in EDTA pH 8.0, but does not establish that retrieval is required (caption: heat-mediated EDTA retrieval). Frozen sections and IF/ICC cannot be judged easier from the supplied evidence; blood-associated peroxidase background is a practical concern when scoring lung endothelium with DAB (HPA: High in lung endothelial cells; caption: DAB detection).

HPA tissue IHC evidence for EPRS1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Endothelial cells High Protein (IHC) HPA →
Testis Elongated or late spermatids High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Myoepithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced EPRS1 IHC Tips

Troubleshoot EPRS1 staining in paraffin sections using the catalog antibody’s tissue image, reported localisation, and matched controls.

How should I adjust retrieval when EPRS1 staining is weak or uneven?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A02967-2). The catalog image used this retrieval before staining a paraffin section of human lung cancer tissue (datasheet A02967-2). If staining is weak, check heating uniformity, cooling, and section adhesion before comparing a second retrieval condition on adjacent sections (standard IHC practice). Keep primary concentration, detection, and development time constant during that comparison, using the reported 2 µg/ml primary concentration as a documented starting point (datasheet A02967-2; standard IHC practice). Judge improvement by cytoplasmic signal and preservation of tissue detail, rather than by stronger staining alone (HPA tissue IHC; standard IHC practice).
Could fixation explain weak EPRS1 staining in my paraffin sections?
Target-specific fixation sensitivity is unknown: the selected tissue caption describes a paraffin section but does not state its fixative (datasheet A02967-2). Record fixative, fixation duration, specimen thickness, and processing history for each case before comparing staining intensity (standard IHC practice). If archival samples vary, stain similarly processed sections together and include a consistently positive reference section in each run (standard IHC practice; HPA tissue IHC: high lung endothelial staining). Compare morphology and cytoplasmic staining across those sections while holding EDTA retrieval at pH 8.0 constant (datasheet A02967-2; HPA tissue IHC). Do not assign a fixation effect solely from a weak field without a processing-matched comparison (standard IHC practice).
How should I assess membrane-like EPRS1 staining in chromogenic IHC?
Expect predominantly cytoplasmic staining in tissue, consistent with EPRS1’s supported cytosolic localisation (HPA tissue IHC; HPA subcellular). EPRS1 has no transmembrane segment, although phosphorylation at Ser-999 can accompany movement from cytosol to membranes (UniProt P07814 topology and subcellular annotation). A sharp membrane-like rim in one section therefore needs confirmation across intact cells and replicate sections before biological interpretation (standard IHC practice; UniProt P07814 subcellular annotation). Compare the rim with adjacent cytoplasm, tissue edges, and no-primary controls, and examine whether it tracks cell boundaries rather than chromogen deposits (standard IHC practice). Routine chromogenic staining alone cannot establish Ser-999 phosphorylation or membrane recruitment (standard IHC practice; UniProt P07814 subcellular annotation).
Could an isoform or modified epitope explain inconsistent EPRS1 staining?
The supplied record lists 0 isoforms and one chain spanning residues 1–1512 (UniProt P07814 processing and isoforms). It also lists WHEP-TRS domains at residues 749–805, 822–878, and 900–956, plus multiple modified residues (UniProt P07814 domains and modified residues). The selected caption does not identify the antibody’s epitope, so a specific modification or domain cannot be assigned as the cause of staining differences (datasheet A02967-2). If an epitope sequence becomes available, compare its position with the annotated domains and modifications before designing a targeted control (UniProt P07814; standard IHC practice). Meanwhile, compare adjacent sections under identical retrieval and detection conditions to distinguish technical variation from a reproducible pattern (standard IHC practice).
How can I check EPRS1 localisation by IF alongside the IHC result?
Use a marker for the expected cell population when multiplexing; endothelial cells are a useful comparison in lung because their EPRS1 tissue staining is reported as high (HPA tissue IHC). Place the EPRS1 fluorophore in a channel with low measured tissue autofluorescence, and inspect single-stain and no-primary controls before interpreting overlap (standard IF practice). For an intracellular epitope, optimise gentle permeabilisation after fixation; EPRS1 is mainly cytosolic and has no transmembrane segment, while this antibody’s epitope is unspecified (HPA subcellular; UniProt P07814 topology; datasheet A02967-2). Capture each channel separately and assess cellular overlap against morphology and the cell marker (standard IF practice). The paraffin tissue caption supplies no IF fixation or permeabilisation condition (datasheet A02967-2).
What should I check when EPRS1 DAB staining appears widespread?
First compare a no-primary section with the stained section to identify signal arising from detection reagents or tissue rather than primary antibody binding (standard IHC practice). The documented workflow used 10% goat serum, biotinylated goat anti-rabbit secondary antibody, streptavidin-biotin complex, and DAB (datasheet A02967-2). Include a peroxidase block and assess endogenous biotin or pigment where relevant to this detection system (standard IHC practice). Titrate primary concentration and DAB development against the documented 2 µg/ml starting condition, keeping retrieval at EDTA pH 8.0 (datasheet A02967-2; standard IHC practice). Because EPRS1 has broad cytoplasmic tissue expression, distinguish cell-shaped signal from diffuse haze before reducing sensitivity (HPA tissue IHC; standard IHC practice).
How should I quantify EPRS1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region of interest before scoring, since EPRS1 intensity varies among reported tissue cell types (HPA tissue IHC; standard IHC practice). For chromogenic sections, report the percentage of positive cells and an H-score based on prespecified intensity categories, or positive-cell density per mm² when cellular abundance is the question (standard IHC practice). Normalise counts to viable tissue area or to the number of eligible cells in the same compartment, and exclude folds, necrosis, and section edges consistently (standard IHC practice). Keep retrieval, antibody concentration, DAB development, illumination, and scoring thresholds consistent across compared sections (datasheet A02967-2; standard IHC practice). Report cell type and cytoplasmic localisation with each score so a change in tissue composition is visible (HPA tissue IHC; standard IHC practice).
When is an EPRS1-positive IHC result biologically convincing?
A convincing result shows cell-shaped cytoplasmic signal with preserved morphology and a low-signal no-primary control (HPA tissue IHC; standard IHC practice). High staining in lung endothelial cells and low or absent staining in listed comparison populations can help assess pattern plausibility, without serving as absolute sample controls (HPA tissue IHC). Treat isolated nuclear staining cautiously because the supported main location is cytosol, while membrane recruitment requires evidence beyond a chromogenic pattern (HPA subcellular; UniProt P07814 subcellular annotation; standard IHC practice). Check tissue edges, necrotic areas, pigment, and endogenous peroxidase for misleading DAB signal before calling a field positive (standard IHC practice). The catalog caption documents staining in human lung cancer tissue but does not establish diagnostic specificity (datasheet A02967-2).
Boster reagents

Best EPRS1 / Bifunctional glutamate/proline--tRNA ligase IHC Antibodies

The catalog antibodies have paraffin-section IHC images from human cancer tissues and IF/ICC images from A431 or U20S cells; A02967-2 lists human, mouse and rat reactivity (catalog image captions; catalog reactivity).

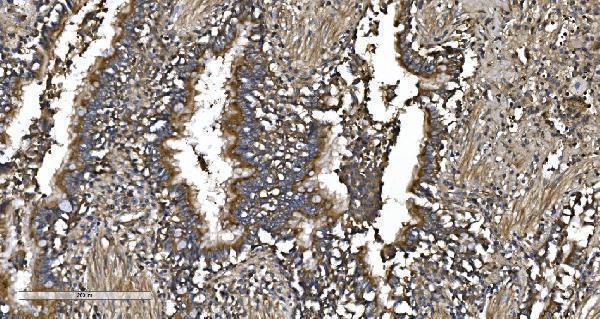
Real IHC data IHC analysis of EPRS1/PARS using anti-EPRS1/PARS antibody (A02967-2). EPRS1/PARS was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-EPRS1/PARS Antibody (A02967-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-EPRS1/PARS Antibody ®
Cat # A02967-2
Real IHC data IHC analysis of EPRS1/PARS using anti-EPRS1/PARS antibody (M02967). EPRS1/PARS was detected in a paraffin-embedded section of human testis cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-EPRS1/PARS Antibody (M02967) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-EPRS1/PARS Antibody ® (monoclonal, 12B5B3)
Cat # M02967

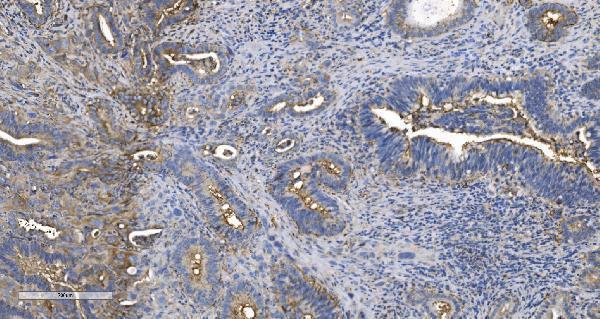
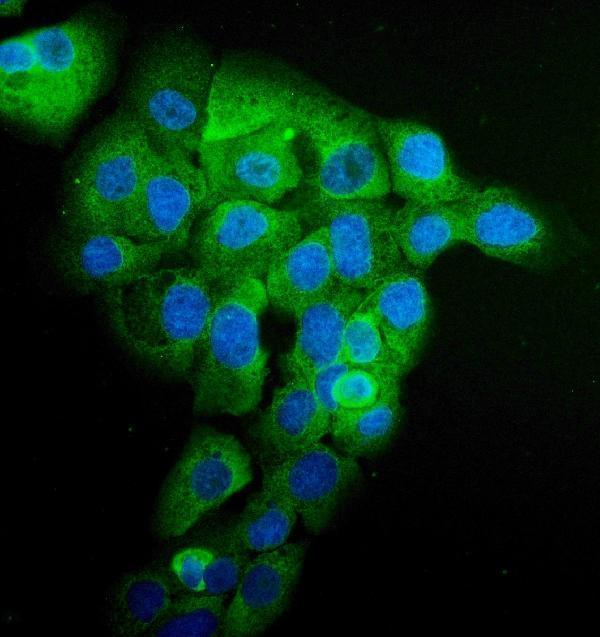
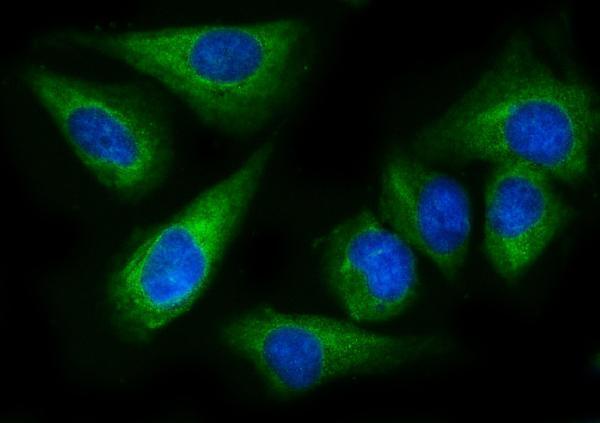
A02967-2 has paraffin-section IHC images from human lung, gallbladder, ovarian and breast cancers, plus IF/ICC data from A431 cells (A02967-2 image captions). M02967 has paraffin-section IHC data from human testis cancer and IF/ICC data from U20S cells (M02967 image captions).

Which to pick: For tissue IHC, choose A02967-2 for its four illustrated human paraffin-section tissues, or monoclonal M02967 for the illustrated human testis cancer section (respective IHC image captions; catalog clone listing). For IF/ICC, both list the application and have cell images: A02967-2 in A431 cells and M02967 in U20S cells (catalog applications; respective IF image captions). Choose A02967-2 when mouse or rat reactivity is required (catalog reactivity); the IHC captions report paraffin sections but do not report the fixative (respective IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.