FABP3 / Fatty acid-binding protein, heart · IHC design guide

Design Immunohistochemistry for FABP3

Plan FABP3 staining in paraffin sections using kidney distal tubules and heart cardiomyocytes as tissue references (HPA tissue IHC). This guide covers fixation, antigen retrieval, antibody dilution, detection and interpretation of cytoplasmic staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
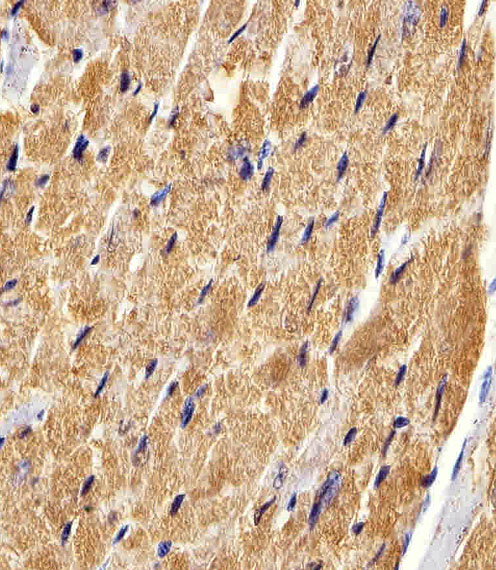
Immunohistochemistry protocol sheet for FABP3 (IHC for FABP3): expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A01734-1, validated IHC image, and IHC protocol steps
Printable FABP3 IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A01734-1, controls and protocol steps. Open the full FABP3 IHC guide →

FABP3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic: distal tubules high, cardiomyocytes medium (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01734-1)
Positive control ⓘ Kidney+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Antibody staining has medium consistency with RNA data (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No isoforms annotated; chain spans residues 2–133 (UniProt)
Section 1

Recommended FABP3 IHC & IF Protocols

The catalog antibody uses heat-mediated citrate retrieval at pH 6 (datasheet A01734-1). Three published FABP3 IHC protocols provide tissue-specific conditions for comparison (PMC12335710; PMC8489205; PMC12134909).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human oesophagus squama cancer tissue; fixative not specified (datasheet A01734-1)
FixationImage fixative and duration unreported (datasheet A01734-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01734-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01734-1)
Primary antibodyRabbit anti-FABP3, 0.5-1μg/ml recommended; image 2μg/ml (datasheet A01734-1)
Primary incubationOvernight at 4 °C (datasheet A01734-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01734-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFABP3-positive staining in distal tubules of kidney (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in heart and skeletal muscle, and kidney. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 for the catalog antibody (datasheet A01734-1); consider Tris-EDTA pH 9 when adapting the published ESCC protocol (PMC12335710).
Section 2

What Is the Expected FABP3 Staining Pattern?

FABP3 should appear mainly in the cytoplasm of kidney distal tubules and cardiomyocytes (HPA tissue IHC; UniProt P05413: cytoplasm). HPA reports high staining in distal tubules, medium staining in cardiomyocytes, and low staining in skeletal myocytes (HPA tissue IHC). Its IHC reliability is Enhanced, although antibody staining and RNA expression show only medium consistency (HPA tissue IHC). FABP3 has no transmembrane segment (UniProt P05413 topology).

What am I looking at on my slide?
Cytoplasmic staining is strong in kidney distal tubules and moderate in cardiomyocytes.This matches the reported cell types, compartment, and relative levels (HPA tissue IHC; UniProt P05413: cytoplasm). Judge intensity against controls processed in the same run; color strength alone cannot establish antibody specificity (general IHC practice).
Signal is predominantly nuclear, or sharply restricted to a membrane instead of cytoplasm.That is unexpected for the IHC tissue pattern (HPA tissue IHC; UniProt P05413: cytoplasm). Check section morphology, counterstain, and the negative control before calling it FABP3. The separate ICC-IF localization record does not validate a membrane-only chromogenic IHC pattern (HPA subcellular ICC-IF).
Strong staining appears in adipocytes or adrenal glandular cells.Those cells were reported as not detected (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity, especially if staining also appears in a no-primary control (general IHC practice). A discordant field is a reason to investigate, not proof of either mechanism.
Weak color covers most tissue structures, including spaces without cells.This is diffuse background rather than the cell-associated pattern reported for FABP3 (HPA tissue IHC). Examine the no-primary control and assess blocking, washes, chromogen development, and section quality (general IHC practice).
A kidney distal-tubule control has no visible signal.The expected level there is high (HPA tissue IHC). Treat a blank control as an uninterpretable run: verify that the control contains distal tubules, then check primary antibody, retrieval settings, detection reagents, and development using the antibody's validated IHC instructions (general IHC practice).
💡Expected FABP3 appearanceCall the stain positive when cytoplasmic color marks kidney distal tubules strongly or cardiomyocytes moderately (HPA tissue IHC; UniProt P05413: cytoplasm); diffuse color, dominant nuclear signal, or strong staining in HPA-negative cell types warrants investigation before scoring.
How each factor affects the staining
Cell type and reference intensityKidney distal tubules are high, cardiomyocytes medium, and skeletal myocytes low in the supplied tissue record (HPA tissue IHC). Compare each cell type with its own reference level; a weak skeletal-muscle result does not carry the same implication as an absent distal-tubule control.
Antibody evidence and its limitTwo listed antibodies have Enhanced IHC validation, HPA055754 and CAB017830 (HPA antibodies). HPA describes medium consistency between tissue staining and RNA expression (HPA tissue IHC). Use this support for the reported pattern while investigating discordant staining.
Cellular compartment and topologyUniProt places FABP3 in the cytoplasm and reports no transmembrane segment (UniProt P05413). A membrane-dominant IHC result therefore needs control review; topology does not by itself identify the cause of unexpected stain.
IF/ICC Q: should focal-adhesion signal define an IHC-positive result?A: No. The ICC-IF record lists focal adhesion sites as uncertain, Golgi as approved, and plasma membrane as uncertain (HPA subcellular ICC-IF). Interpret paraffin-section chromogenic IHC against the cytoplasmic tissue pattern (HPA tissue IHC).
Detection-system backgroundEndogenous peroxidase or nonspecific detection can add color in chromogenic IHC (general IHC practice). A no-primary control helps distinguish detection background from antibody-dependent staining; it cannot by itself establish that antibody-dependent signal is FABP3.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Distal tubules are blank while the rest of the slide is faint.The expected distal-tubule signal is high (HPA tissue IHC); the pattern suggests a run or detection problem, although this image alone cannot identify which step failed.Confirm distal tubules are present. Check antibody use, retrieval settings, detection reagents, and chromogen against the validated IHC instructions (general IHC practice); no FABP3-specific retrieval condition is established here.
Cardiomyocytes stain less strongly than distal tubules.Medium cardiomyocyte and high distal-tubule levels are consistent with the tissue record (HPA tissue IHC).Assess cytoplasmic localization and same-run controls before adjusting staining conditions. Do not require equal intensity in these two tissues to accept the run (HPA tissue IHC).
Adipocytes stain strongly.Adipocytes were not detected in the reported adipose tissue pattern (HPA tissue IHC); cross-reactivity or detection background is possible (general IHC practice).Inspect a no-primary control and compare staining with a positive tissue control. If color remains antibody-dependent, review specificity before scoring it as FABP3 (general IHC practice).
Brown color is widespread, including extracellular areas.Diffuse color is inconsistent with the reported cell-associated cytoplasmic pattern (HPA tissue IHC; UniProt P05413: cytoplasm). Detection background is one possible cause (general IHC practice).Compare the no-primary control, then review blocking, washes, and chromogen development; repeat the run if the controls cannot support interpretation (general IHC practice).
Signal appears mainly in nuclei or at cell borders.The IHC tissue profile is cytoplasmic (HPA tissue IHC; UniProt P05413: cytoplasm). The ICC-IF membrane annotation is uncertain and does not resolve an unexpected IHC pattern (HPA subcellular ICC-IF).Check counterstain and tissue morphology, compare positive and no-primary controls, and withhold a positive call until the compartment pattern is resolved (general IHC practice).
A slide shows faint skeletal-myocyte staining.Low skeletal-myocyte staining is reported (HPA tissue IHC); faint signal there alone does not establish a failed assay.Check that the signal is cytoplasmic, then compare a same-run distal-tubule or cardiomyocyte control with its reported pattern (HPA tissue IHC; general IHC practice).

Sample controls for FABP3 IHC & IF

🧪Run kidney first: distal tubule cells should stain for FABP3 (HPA: High in kidney distal tubules). Use adipose tissue as the negative tissue, with adipocytes showing no specific staining (HPA: Not detected in adipocytes); on the kidney slide, assess neighboring cells without specific cytoplasmic signal against the no-primary control rather than assuming every non-distal-tubule cell is negative (UniProt P05413: Cytoplasm; standard IHC practice).
Positive control tissue: Kidney (Distal tubules, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FABP3 in ASC52telo, Hep-G2, U2OS, with annotated localisation: Focal adhesion sites (uncertain) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a concentration-matched rabbit IgG isotype control, and a FABP3-knockout specimen or validated immunizing-peptide block as a biological specificity control (selected A01734-1 caption: rabbit primary; standard IHC practice). For kidney chromogenic IHC, control endogenous peroxidase and check endogenous biotin background when using the caption’s biotin-based detection (selected A01734-1 caption: biotinylated secondary and SABC/DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A01734-1 paraffin-section caption does not state the fixative (selected A01734-1 caption). That caption used heat retrieval in citrate buffer at pH 6 for 20 minutes, but the evidence does not establish that retrieval is required in every specimen (selected A01734-1 caption). The supplied evidence does not establish whether frozen sections or IF are easier for FABP3; kidney endogenous peroxidase or biotin can complicate chromogenic interpretation (standard IHC practice).

HPA tissue IHC evidence for FABP3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Distal tubules High Protein (IHC) HPA →
Heart muscle Cardiomyocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced FABP3 IHC Tips

Troubleshoot FABP3 staining in paraffin sections by checking retrieval, cytoplasmic localisation, controls and scoring against the supplied tissue evidence.

Which retrieval conditions should I start with for FABP3 paraffin sections?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes (datasheet A01734-1). The selected paraffin-section image used this treatment before overnight incubation with 2 µg/mL primary antibody at 4 °C, so keep those conditions together for the first comparison (datasheet A01734-1). If staining is weak, compare a shorter and a longer heating period on matched sections while keeping detection and exposure to DAB consistent (standard IHC practice). Judge recovery in distal kidney tubules and cardiomyocytes, where staining is reported, alongside a no-primary control for retrieval-related background (HPA tissue IHC; standard IHC practice). Record tissue integrity as well as signal, since damaged sections cannot establish whether a retrieval change improved FABP3 detection (standard IHC practice).
How should I troubleshoot fixation-related loss of FABP3 staining?
Target-specific sensitivity of FABP3 to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not state a fixative (datasheet A01734-1). Record the fixative, fixation duration and processing history for each specimen before comparing staining intensity across blocks (standard IHC practice). If a block stains weakly, run a well-preserved positive-control section in the same batch and first confirm the documented citrate pH 6 retrieval for 20 minutes (datasheet A01734-1; standard IHC practice). Compare sections with different fixation histories only after checking morphology and matched detection conditions, because those variables can affect the interpretation of a weak result (standard IHC practice). Do not infer fixation sensitivity from the protein’s cytoplasmic annotation or tissue staining pattern (UniProt P05413; HPA tissue IHC).
Where should convincing FABP3 staining appear in tissue?
Expect predominantly cytoplasmic chromogenic staining, consistent with the protein annotation and the reported tissue IHC profile (UniProt P05413; HPA tissue IHC). Distal kidney tubules provide a reported high-staining cell population, while cardiomyocytes are reported at medium intensity and skeletal myocytes at low intensity (HPA tissue IHC). Assess signal within intact cell outlines rather than treating DAB in lumina, tissue folds or detached material as cellular staining (standard IHC practice). UniProt annotates no transmembrane segment, so a solely sharp surface rim warrants review of morphology and the no-primary control (UniProt P05413 topology; standard IHC practice). HPA also reports focal-adhesion, Golgi and plasma-membrane signals from cell imaging, with uncertainty attached to some locations; these do not replace the tissue IHC expectation (HPA subcellular; HPA tissue IHC).
Could isoforms or epitope changes explain discordant staining?
No FABP3 isoforms are listed in the supplied record, so an isoform-specific explanation is unsupported here (UniProt P05413). The protein has no annotated transmembrane segment or signal peptide, while several modified residues are reported near its amino terminus (UniProt P05413 topology; UniProt P05413 modified residues). The antibody’s binding epitope is not supplied, so those modifications cannot be assigned a specific effect on staining (UniProt P05413 modified residues; datasheet A01734-1). When sections disagree, first compare retrieval, primary concentration and detection on adjacent sections, including the documented 2 µg/mL incubation condition (datasheet A01734-1; standard IHC practice). If a staining pattern remains discordant, use an independently validated antibody or another orthogonal readout before invoking epitope masking (standard IHC practice).
How can I check FABP3 localisation by IF alongside chromogenic IHC?
Treat IF as a separate assay: the selected antibody evidence documents paraffin-section chromogenic staining, while HPA reports cell-imaging localisations without establishing IF performance for this SKU (datasheet A01734-1; HPA subcellular). Multiplex FABP3 with a validated marker for the expected cell population, such as a cardiomyocyte or distal-tubule marker, and include single-colour controls (HPA tissue IHC; standard IF practice). Choose fluorophores after inspecting tissue autofluorescence in unstained sections, and separate emission channels to limit bleed-through (standard IF practice). Because FABP3 is annotated as cytoplasmic and lacks a transmembrane segment, use permeabilisation appropriate for access to an intracellular epitope, then verify cell morphology (UniProt P05413 topology; standard IF practice). Compare the IF distribution with cytoplasmic tissue IHC, while interpreting focal-adhesion and plasma-membrane HPA annotations with their stated uncertainty (HPA tissue IHC; HPA subcellular).
What should I check when DAB staining is diffuse or widespread?
First inspect no-primary and detection-only controls to identify signal produced by the detection system rather than the primary antibody (standard IHC practice). The selected workflow used 10% goat serum blocking, a biotinylated secondary and a streptavidin–biotin complex with DAB, so check each step when background rises (datasheet A01734-1). Include an endogenous peroxidase block and assess whether a biotin-based detection system contributes tissue background (standard chromogenic IHC practice). Titrate the primary around the documented 2 µg/mL condition and compare equivalent development times on positive and negative tissues (datasheet A01734-1; standard IHC practice). Diffuse nuclear colour or staining concentrated at section edges should prompt a morphology and control review before scoring FABP3 (UniProt P05413 cytoplasm; standard IHC practice).
How should I quantify FABP3 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: FABP3 tissue staining is described as cytoplasmic, with different reported intensities across distal tubules, cardiomyocytes and skeletal myocytes (HPA tissue IHC). For comparable sections, record the percentage of positive cells and an intensity-based H-score, or measure positive area per mm² when discrete cell counting is impractical (standard IHC practice). Normalise each result to the number or area of eligible, intact cells in the prespecified tissue region, excluding folds and necrosis (standard IHC practice). Keep retrieval, primary incubation and DAB development matched across the batch, and set scoring thresholds using appropriate controls (datasheet A01734-1; standard IHC practice). Report cell-type results separately because a change in tissue composition can change a whole-section average without changing staining within a cell type (HPA tissue IHC; standard IHC practice).
How can I distinguish a true FABP3 positive from artefact?
A credible positive has intracellular staining in intact cells of an expected population, such as distal kidney tubules or cardiomyocytes, with an appropriate control pattern (HPA tissue IHC; UniProt P05413 cytoplasm; standard IHC practice). Review staining restricted to nuclei, section edges or necrotic regions before calling it FABP3, since those distributions do not match the reported tissue pattern (HPA tissue IHC; standard IHC practice). A positive no-primary control or signal associated with endogenous enzyme activity points to a detection problem requiring investigation (standard chromogenic IHC practice). Interpret absence in adipocytes or adrenal glandular cells against their reported lack of detection, while recognising that the HPA tissue profile has medium consistency with RNA data (HPA tissue IHC). Resolve surprising cellular or compartment patterns with matched controls and independent evidence before assigning biological meaning (standard IHC practice).
Boster reagents

Best FABP3 / Fatty acid-binding protein, heart IHC Antibodies

Real IHC images show FABP3 in human heart and cancer sections, plus mouse and rat heart sections; all depicted sections are paraffin embedded (catalog image captions).

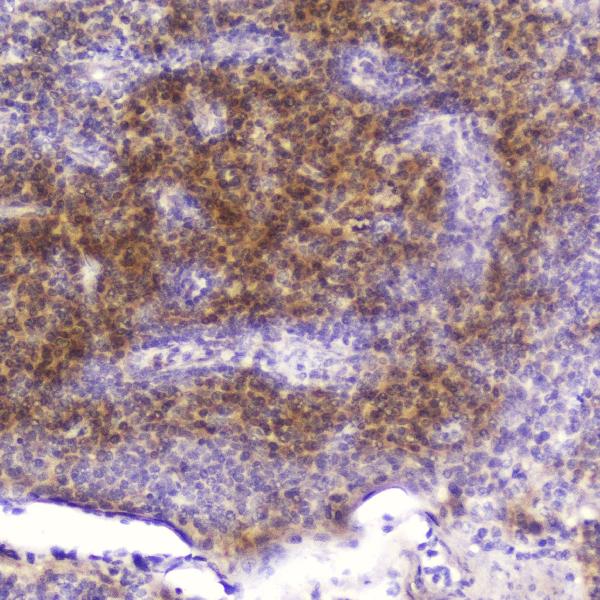
Real IHC data IHC analysis of Cardiac FABP using anti-Cardiac FABP antibody (A01734-1). Cardiac FABP was detected in paraffin-embedded section of human oesophagus squama cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-Cardiac FABP Antibody (A01734-1) overnight at 4℃. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37℃. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Cardiac FABP/FABP3 Antibody ®
Cat # A01734-1
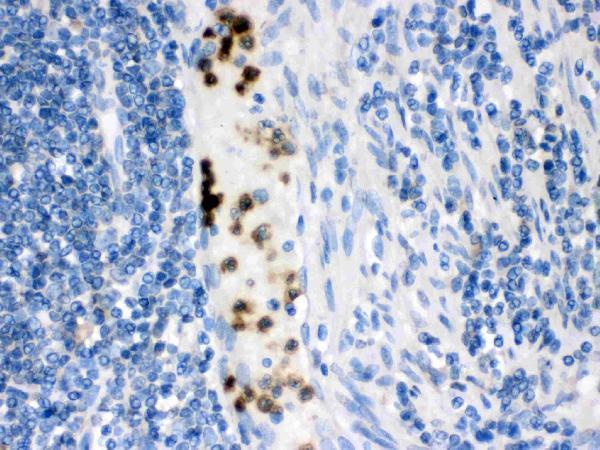
Real IHC data Cardiac FABP was detected in paraffin-embedded sections of human intestinal cancer tissues using rabbit anti-Cardiac FABP Antigen Affinity purified polyclonal antibody (Catalog # PA1336) at 1 μg/mL. The immunohistochemical section was developed using SABC method (Catalog # SA1022).
Anti-Cardiac FABP/FABP3 Antibody ®
Cat # PA1336
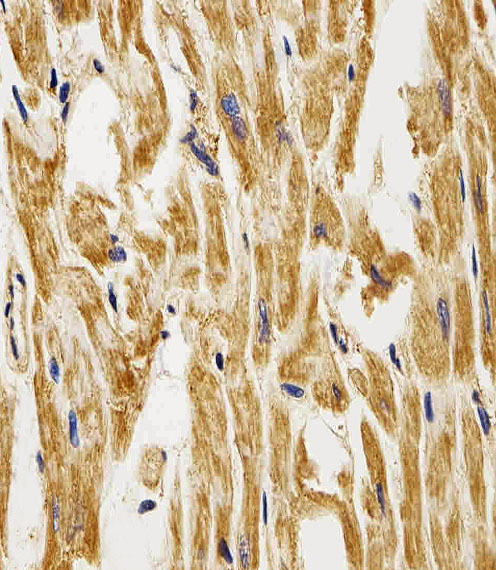
Real IHC data Immunohistochemical analysis of paraffin-embedded H. heart section using FABP3. A01734-2 was diluted at 1:25 dilution. A peroxidase-conjugated goat anti-rabbit IgG at 1:400 dilution was used as the secondary antibody, followed by DAB staining.
Anti-FABP3 Antibody
Cat # A01734-2

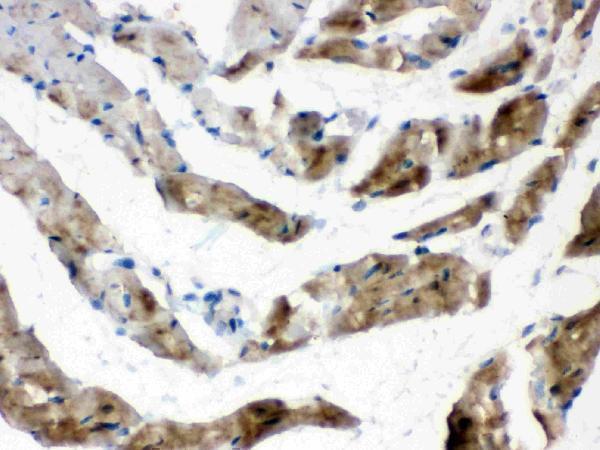
A01734-1 has IHC images from human oesophageal cancer, tonsil, mouse heart and rat heart paraffin sections (A01734-1 image captions). PA1336 has images from human intestinal cancer, rat cardiac muscle and mouse skeletal muscle; A01734-2 has a human heart paraffin-section image (PA1336 and A01734-2 image captions).

Which to pick: For human heart IHC, A01734-2 has a paraffin-section DAB image at 1:25; its caption does not report the fixative (A01734-2 image caption). For cross-species IHC, choose A01734-1: it is rabbit polyclonal with human, mouse and rat reactivity, and its paraffin-section captions document citrate retrieval at pH 6 for 20 minutes (A01734-1 catalog and image captions). None of these SKUs lists IF/ICC validation or an IF dilution, so this evidence does not support an IF/ICC pick (catalog application lists and IF fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P05413 (FABPH_HUMAN, Fatty acid-binding protein, heart).
  2. Human Protein Atlas. FABP3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. FABP3 subcellular location (ICC-IF): Mainly localized to the focal adhesion sites. In addition localized to the plasma membrane and the Golgi apparatus..
  4. Human Protein Atlas. FABP3 antibody validation summary (2 antibodies).
  5. A nine-gene signature with potential targets for predicting the prognosis of patients with esophageal cancer. Translational cancer research 2025 — PMC12335710.
  6. Fatty acid binding protein 3 is associated with peripheral arterial disease. JVS-vascular science 2020 — PMC8489205.
  7. Fatty Acid-Binding Protein 3 Expression in the Brain and Skin in Human Synucleinopathies. Frontiers in aging neuroscience 2021 — PMC8026871.
  8. Oleanolic Acid Restores Drug Sensitivity in Sorafenib-resistant Hepatocellular Carcinoma: Evidence from In Vitro and In Vivo Studies. Journal of clinical and translational hepatology 2025 — PMC12134909.
  9. PubMed PMID:1710107 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.