FHL2 / Four and a half LIM domains protein 2 · IHC design guide

Design Immunohistochemistry for FHL2

Plan FHL2 chromogenic IHC in paraffin sections using cardiomyocytes and ovarian stromal cells as high-staining reference populations (HPA tissue IHC). This guide covers fixation, antibody dilution, detection and interpretation of the predominantly cytoplasmic tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
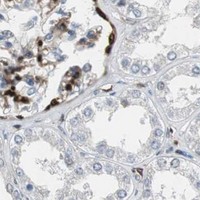
Immunohistochemistry protocol sheet for FHL2 (IHC for FHL2): expected localisation Cytoplasmic tissue staining; nuclear localisation is possible (HPA tissue IHC; UniProt), antibody A02129-2, validated IHC image, and IHC protocol steps
Printable FHL2 IHC protocol sheet — expected localisation Cytoplasmic tissue staining; nuclear localisation is possible (HPA tissue IHC; UniProt), antibody A02129-2, controls and protocol steps. Open the full FHL2 IHC guide →

FHL2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining; nuclear localisation is possible (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic staining in cardiomyocytes and ovarian stromal cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02129-2)
Positive control ⓘ Heart muscle+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA expression show medium consistency (HPA tissue IHC)
Regulation Expression regulation unreported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage unspecified (UniProt)
Section 1

Recommended FHL2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by published FHL2 IHC methods for human liver, colorectal cancer, and visceral adipose tissue (PMC3562203; PMC3708555; PMC10573629).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendiceal adenocarcinoma tissue; fixative not specified (datasheet A02129-2)
FixationImage fixative and duration unreported (datasheet A02129-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02129-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02129-2)
Primary antibodyRabbit anti-FHL2, 2-5 μg/ml (datasheet A02129-2)
Primary incubationOvernight at 4 °C (datasheet A02129-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02129-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFHL2-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression, highest in heart muscle, ovary and endometrium. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A02129-2). Reproduce each article’s stated conditions when comparing results.
Section 2

What Is the Expected FHL2 Staining Pattern?

FHL2 is found in the cytoplasm and nucleus, including the sarcomeric Z line in muscle (UniProt Q14192 localisation). In paraffin IHC, expect cytoplasmic staining in cardiomyocytes, Bowman's capsule cells and ovarian stromal cells, with high staining reported in each (HPA tissue IHC). HPA rates the tissue profile Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA tissue IHC). FHL2 has no transmembrane segment (UniProt Q14192 topology).

What am I looking at on my slide?
Strong cytoplasmic staining in cardiomyocytes, with cellular outlines still readable.This agrees with the high cardiomyocyte signal reported in heart muscle (HPA tissue IHC). FHL2 can associate with the sarcomeric Z line (UniProt Q14192 localisation); assess any fine muscle pattern within the cells rather than treating it as a required feature of every chromogenic section.
A predominantly membrane-rim or gland-lumen signal, with little cellular staining.A membrane or luminal pattern is unsupported by the cytoplasmic tissue profile (HPA tissue IHC) and absence of a transmembrane segment (UniProt Q14192 topology). Check section edges, precipitate and detection background before assigning it to FHL2. Nuclear staining alone is not disqualifying because nuclear localisation is recorded (UniProt Q14192 localisation).
Strong staining in adipocytes while cardiomyocytes stain weakly or not at all.Adipocytes are reported as not detected, whereas cardiomyocytes are high (HPA tissue IHC). This reversal raises concern for nonspecific staining or endogenous detection activity (general IHC practice). Evaluate the cells separately; a tissue-level negative label does not mean every cell in that tissue is negative.
Uniform pale brown haze across cells, stroma and empty spaces.A field-wide haze cannot be scored as the cell-specific pattern reported by HPA (HPA tissue IHC). Review the no-primary control, wash steps and detection background; diffuse colour may obscure a real intracellular signal (general IHC practice).
No staining in an adequately preserved heart muscle section.Cardiomyocytes are a high-signal reference in the HPA profile (HPA tissue IHC). First check the section and detection controls, then review the IHC-validated antibody's specified use and retrieval conditions (general IHC practice). A failed positive reference makes a negative study section uninterpretable.
💡Expected FHL2 appearanceCall a section positive when identifiable cardiomyocytes show strong intracellular, chiefly cytoplasmic chromogen (HPA tissue IHC); isolated luminal colour or widespread background is a suspect positive (general IHC practice).
How each factor affects the staining
Tissue and cell choiceHeart cardiomyocytes, Bowman's capsule cells and ovarian stromal cells are high; breast myoepithelial cells are medium (HPA tissue IHC). Compare the named cell populations, since signal intensity differs within and between tissues.
Compartment and assayCytoplasm, nucleus and muscle Z line are recorded for FHL2 (UniProt Q14192 localisation). ICC-IF images chiefly place it on actin filaments and focal adhesion sites (HPA subcellular ICC-IF); that cell-culture pattern is context, not an IHC-P requirement.
IF/ICC Q: Where should the signal appear?A: HPA reports mainly actin filaments and focal adhesion sites in ICC-IF (HPA subcellular ICC-IF). Interpret those images within the separate IF/ICC guide; they do not specify a chromogenic paraffin protocol.
Antibody validationThree listed antibodies have Enhanced IHC validation; two also have Approved ICC validation (HPA antibody validation). Enhanced supports the reported pattern, while HPA still describes medium consistency with RNA expression for the tissue profile (HPA tissue IHC).
Isoforms and processingTwo isoforms are listed, with no signal peptide, propeptide or cleavage chain beyond residues 1–279 (UniProt Q14192 isoforms and processing). The supplied record gives no antibody epitope, so isoform-specific staining or loss of staining cannot be predicted.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Heart muscle is blank or much weaker than expected.The positive reference may have failed; cardiomyocytes are high in the HPA profile (HPA tissue IHC).Check section integrity and run controls, then review retrieval, antibody dilution and detection against the IHC-validated antibody's instructions (general IHC practice). No FHL2-specific fixation sensitivity is established by the supplied sources.
Every structure, including spaces between cells, looks brown.Diffuse background can arise from nonspecific detection or chromogen deposition (general IHC practice).Compare a no-primary control, inspect reagent and wash performance, and score only signal inside identifiable cells (general IHC practice).
A membrane rim dominates the stain.A dominant membrane pattern conflicts with the absence of a transmembrane segment (UniProt Q14192 topology).Inspect section edges and precipitate, then compare with the intracellular cardiomyocyte reference (HPA tissue IHC; general IHC practice).
An expected negative cell population stains strongly.Adipocytes and liver cholangiocytes are reported as not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible (general IHC practice).Confirm the cell identity, compare the no-primary control and repeat alongside a high cardiomyocyte reference (HPA tissue IHC; general IHC practice).
Some cells show nuclear signal.Nuclear localisation is recorded for FHL2 (UniProt Q14192 localisation), although the tissue IHC profile describes general cytoplasmic expression (HPA tissue IHC).Assess nuclear signal with the cytoplasmic pattern, cell identity and controls; do not reject it solely for its compartment (UniProt Q14192 localisation; general IHC practice).
A weak study section seems negative.FHL2 levels vary by cell population; endometrial glandular cells are low, while cardiomyocytes are high (HPA tissue IHC).Check the high-signal heart reference and controls before calling the study cells negative; report the cell population and staining intensity observed (HPA tissue IHC; general IHC practice).

Sample controls for FHL2 IHC & IF

🧪Run heart muscle first: cardiomyocytes should stain (HPA: High in cardiomyocytes). Use adipose tissue as the negative tissue, with adipocytes expected to lack staining (HPA: Not detected in adipocytes); on the heart slide, cells without specific staining should show counterstain only, but the supplied HPA data do not identify a heart cell type as an established internal negative (HPA: High in cardiomyocytes).
Positive control tissue: Heart muscle (Cardiomyocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FHL2 in A-431, U-251MG, U2OS, U2OS, siRNA 1, U2OS, siRNA 2, U2OS, scrambled, with annotated localisation: Actin filaments (enhanced), Focal adhesion sites (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit IgG isotype control appropriate to the primary antibody; and FHL2-knockout material processed in parallel if available (caption: rabbit primary; standard IHC practice). For the heart positive, block endogenous peroxidase and check for endogenous biotin before interpreting DAB signal from the biotin-based detection system (caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A02129-2 tissue-IHC caption does not state a fixative (caption: fixative not stated). The paraffin-section example uses heat-mediated retrieval in EDTA at pH 8.0, establishing a starting condition without establishing that retrieval is required; frozen sections or IF cannot be judged easier from the supplied evidence (caption: EDTA retrieval; HPA: ICC-IF images available). In heart muscle, endogenous peroxidase or biotin could complicate interpretation of the biotin-based DAB signal (HPA: High in cardiomyocytes; caption: SABC and DAB; standard IHC practice).

HPA tissue IHC evidence for FHL2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Kidney Bowman's capsule High Protein (IHC) HPA →
Ovary Ovarian stroma cells High Protein (IHC) HPA →
Breast Myoepithelial cells Medium Protein (IHC) HPA →
Cervix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced FHL2 IHC Tips

Use matched controls and cell-specific scoring to troubleshoot FHL2 staining in paraffin sections; assess IF separately when spatial resolution is needed.

Which retrieval conditions should I start with for weak FHL2 staining in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A02129-2). The selected image used this retrieval before staining a paraffin section of human appendiceal adenocarcinoma with 2 μg/ml catalog antibody overnight at 4°C (caption A02129-2). Keep section thickness, heating, cooling, antibody concentration, and detection constant while comparing retrieval runs (standard IHC practice). If signal remains weak, compare a separately validated retrieval condition on adjacent sections, with a known positive control in every run (standard IHC practice; HPA: high in heart muscle cardiomyocytes). Record tissue damage alongside staining intensity, because excessive heating can impair morphology and scoring (standard IHC practice).
Could fixation explain weak or inconsistent FHL2 staining?
Target-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not state a fixative, and its staining cannot establish how fixation affects FHL2 (caption A02129-2). Record each specimen's actual fixative, fixation duration, and processing history before comparing staining across cases (standard IHC practice). Run sections with matched processing together and retain a documented positive control, such as heart muscle containing cardiomyocytes (standard IHC practice; HPA: high in heart muscle cardiomyocytes). If a fixation-related problem is suspected, compare available specimens with documented processing under the same EDTA pH 8.0 retrieval and antibody conditions (datasheet A02129-2; standard IHC practice). Do not assign a weak result to fixation until controls and morphology have been reviewed (standard IHC practice).
How should I assess predominantly nuclear FHL2 staining?
Evaluate nuclear staining alongside cytoplasmic staining in the same identifiable cell population, because both compartments are recorded for FHL2 (UniProt Q14192: cytoplasm and nucleus). In muscle, consider the reported myofibrillar sarcomere Z-line location when judging a structured cytoplasmic pattern (UniProt Q14192: Z line). The HPA subcellular profile places FHL2 mainly at actin filaments and focal adhesion sites in its cell imaging data (HPA subcellular: enhanced locations). Compare the nuclear-to-cytoplasmic pattern with a matched positive section and a no-primary control before treating a nuclear-only pattern as biological (standard IHC practice). Document compartment-specific scores separately, since a single whole-cell score can hide a shift in localisation (standard IHC practice).
Can isoforms or epitope masking account for discordant FHL2 staining?
Check the catalog antibody's documented immunogen or epitope before attributing discordant staining to an isoform; the supplied caption does not identify that epitope (caption A02129-2). FHL2 has 2 listed isoforms and four annotated LIM zinc-binding domains spanning residues 40–275 (UniProt Q14192: isoforms and domains). A phosphoserine is annotated at residue 238, but the payload does not establish whether this antibody recognizes that region or whether phosphorylation alters staining (UniProt Q14192: modified residue; caption A02129-2). Compare retrieval and staining on serial sections under controlled conditions before proposing epitope masking (standard IHC practice). Report the antibody identity and any verified epitope information when interpreting isoform-specific claims (standard IHC practice).
How can IF help verify FHL2 localisation in a multiplex experiment?
For a separate IF assay, pair FHL2 with a marker identifying the expected cell population, such as a cardiomyocyte identity marker in heart muscle (HPA: high in heart muscle cardiomyocytes; standard IF practice). Choose spectrally separated fluorophores and place a weaker signal in a longer-wavelength channel after checking tissue autofluorescence and single-color controls (standard IF practice). FHL2 has no transmembrane segment and is annotated in intracellular compartments, so permeabilise cells to expose cytoplasmic and nuclear epitopes, then optimise detergent strength empirically (UniProt Q14192: topology and subcellular location; standard IF practice). Include no-primary and single-color controls when testing colocalisation (standard IF practice). The paraffin-section caption establishes chromogenic IHC conditions, not IF performance (caption A02129-2).
What should I check when DAB background obscures FHL2-positive cells?
Compare the stained slide with a no-primary control and inspect whether pigment follows tissue edges, damaged areas, or the expected cell boundaries (standard IHC practice). Block endogenous peroxidase before DAB development, then check for incomplete blocking if both primary-treated and no-primary sections develop color (standard IHC practice). The selected image used 10% goat serum, biotinylated goat anti-rabbit IgG for 30 minutes at 37°C, and a streptavidin-biotin complex with DAB (caption A02129-2). If diffuse staining persists, titrate the 2 μg/ml primary concentration downward while keeping retrieval and development matched (caption A02129-2; standard IHC practice). Assess endogenous biotin interference when using biotin-based detection (standard IHC practice).
How should I quantify FHL2 when staining varies by cell type and compartment? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and nuclear or cytoplasmic compartment before counting, using morphology or an adjacent identity stain where needed (standard IHC practice; UniProt Q14192: nuclear and cytoplasmic locations). For intensity scoring, report the percentage of cells at 0, 1, 2, and 3 intensity and calculate an H-score from 0–300 (standard IHC practice). Alternatively, report percent-positive cells or positive-cell density per mm² when those measures better match the question (standard IHC practice). Normalise counts to the number of eligible cells or evaluable tissue area, and exclude necrotic or folded regions consistently (standard IHC practice). Keep staining thresholds and image acquisition settings fixed across the comparison set (standard IHC practice).
How can I distinguish true FHL2 staining from artefact?
A plausible result should occur in identifiable cells and a supported compartment: FHL2 is annotated in cytoplasm and nucleus, and HPA reports high staining in heart muscle cardiomyocytes (UniProt Q14192: subcellular location; HPA: heart muscle). Treat isolated staining at section edges, folds, or necrotic regions cautiously and compare it with intact tissue nearby (standard IHC practice). Examine a no-primary control for endogenous enzyme or detection-system signal, especially when interpreting DAB deposits (standard IHC practice). Do not assume every appendiceal tumor cell is positive merely because the selected image shows staining in a human appendiceal adenocarcinoma section (caption A02129-2). HPA rates tissue staining reliability as Enhanced but describes only medium consistency with RNA expression, so confirm unexpected cell patterns independently (HPA: reliability description; standard IHC practice).
Boster reagents

Best FHL2 / Four and a half LIM domains protein 2 IHC Antibodies

A02129-2 has chromogenic IHC images from human paraffin sections (catalog IHC captions). M02129-1 lists ICC/IF for human, mouse and rat, with no supplied IF image (catalog applications, reactivity and IF image alts).

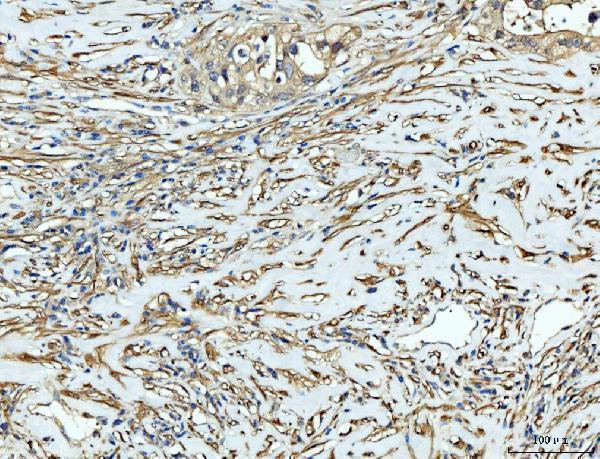
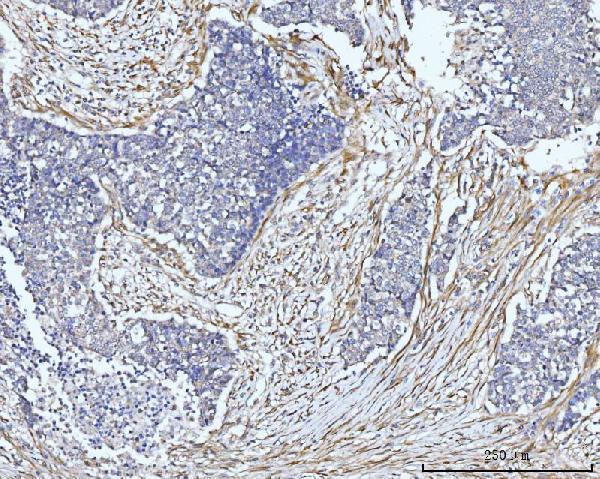
Real IHC data IHC analysis of FHL2 using anti-FHL2 antibody (A02129-2). FHL2 was detected in a paraffin-embedded section of human appendiceal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-FHL2 Antibody (A02129-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-FHL2 Antibody ®
Cat # A02129-2

A02129-2 is the sole figure-backed card: its IHC captions show human appendiceal adenocarcinoma, lung cancer, ruptured spleen and stomach cancer paraffin sections (catalog IHC captions). It lists human, mouse and rat reactivity, but its supplied IHC images show human tissue only (catalog reactivity and IHC captions).

Which to pick: Choose A02129-2 for human paraffin-section chromogenic IHC: its listed dilution is 2–5 μg/ml, and its captions document EDTA retrieval at pH 8.0 with DAB detection; the fixative is unreported (catalog IHC dilution and captions). Choose rabbit monoclonal M02129-1, clone 19F25, for ICC/IF based on its listed application and 1:50 IF dilution; no IF image is supplied (catalog clone, applications, IF dilution and image alts). Both list human, mouse and rat reactivity, but the supplied tissue IHC images support human samples only, and M02129-1 has no listed IHC application (catalog reactivity and applications; A02129-2 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14192 (FHL2_HUMAN, Four and a half LIM domains protein 2).
  2. Human Protein Atlas. FHL2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. FHL2 subcellular location (ICC-IF): Mainly localized to the actin filaments and focal adhesion sites..
  4. Human Protein Atlas. FHL2 antibody validation summary (3 antibodies).
  5. Deficiency in four and one half LIM domain protein 2 (FHL2) aggravates liver fibrosis in mice. BMC gastroenterology 2013 — PMC3562203.
  6. Epithelial expression of FHL2 is negatively associated with metastasis-free and overall survival in colorectal cancer. British journal of cancer 2013 — PMC3708555.
  7. Four-and-a-Half LIM-Domain Protein 2 (FHL2) Induces Neuropeptide Y (NPY) in Macrophages in Visceral Adipose Tissue and Promotes Diet-Induced Obesity. International journal of molecular sciences 2023 — PMC10573629.
  8. FHL2 in arterial medial calcification in chronic kidney disease. Nephrology, dialysis, transplantation : official publication of the European Dialysis and Transplant Association - European Renal Association 2024 — PMC11596093.
  9. PubMed PMID:9150430 — UniProt-cited evidence.
  10. PubMed PMID:9573400 — UniProt-cited evidence.
  11. PubMed PMID:11001931 — UniProt-cited evidence.