FOXL2 / Forkhead box protein L2 · IHC design guide

Design Immunohistochemistry for FOXL2

Plan chromogenic FOXL2 IHC in paraffin sections using nuclear staining in ovarian follicle cells as a reference (HPA tissue IHC). The catalog antibody’s IHC range is 2–5 µg/mL (datasheet A01185-1); compare staining across consistently fixed sections and score each cell type separately.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for FOXL2 (IHC for FOXL2): expected localisation Nuclear staining in ovarian follicle and stromal cells (HPA tissue IHC), antibody A01185-1, validated IHC image, and IHC protocol steps
Printable FOXL2 IHC protocol sheet — expected localisation Nuclear staining in ovarian follicle and stromal cells (HPA tissue IHC), antibody A01185-1, controls and protocol steps. Open the full FOXL2 IHC guide →

FOXL2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in ovarian follicle and stromal cells (HPA tissue IHC)
Staining pattern Nuclear follicle-cell and stromal-cell staining in ovary and endometrium (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01185-1)
Positive control ⓘ Endometrium+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Endometrial smooth muscle also stains; score cell types separately (HPA tissue IHC)
Regulation Expression persists in adult ovarian follicle cells (UniProt)
Isoform / epitope No annotated isoforms; one chain spans residues 1–376 (UniProt)
Section 1

Recommended FOXL2 IHC & IF Protocols

The catalog antibody has an EDTA pH 8.0 IHC protocol (datasheet: A01185-1). The following published FOXL2 protocols describe chromogenic staining of gonadal or ovarian sections (PMC4217102; PMC11731763; PMC13328056).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse ovary tissue; fixative not specified (datasheet A01185-1)
FixationImage fixative and duration unreported (datasheet A01185-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01185-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01185-1)
Primary antibodyRabbit anti-FOXL2, 2 μg/ml (datasheet A01185-1)
Primary incubationOvernight at 4 °C (datasheet A01185-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01185-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFOXL2-positive staining in smooth muscle cells of endometrium (HPA tissue IHC: Medium). HPA tissue profile: Nuclear expression in ovarian follicle cells and stromal cells in ovary and endometrium. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A01185-1). Published alternatives use microwave-heated citrate or Tris-based solution (PMC11731763; PMC13328056).
Section 2

What Is the Expected FOXL2 Staining Pattern?

FOXL2 should appear in nuclei, consistent with its nuclear localization and lack of a transmembrane segment (UniProt P58012). In paraffin tissue sections, expect staining in ovarian follicle cells and in stromal cells of the ovary and endometrium (HPA: tissue IHC profile). HPA reports medium staining in ovarian follicle cells and endometrial smooth muscle cells; its tissue IHC reliability is Enhanced (HPA: tissue IHC).

What am I looking at on my slide?
Distinct nuclear stain in ovarian follicle cells, with little surrounding haze.This matches the expected compartment and a documented positive cell population; HPA scores follicle cell staining as medium (UniProt P58012: nucleus; HPA: ovary IHC). Judge the nuclei against their own section context rather than requiring every ovarian cell to have equal signal (general IHC practice).
Strong cytoplasmic, surface, or extracellular color while nuclei remain pale.Treat this as a compartment mismatch requiring investigation, not a convincing FOXL2 result: FOXL2 is nuclear and has no transmembrane segment (UniProt P58012). Examine counterstained nuclei, staining boundaries, and detection controls for nonspecific deposit or background (general IHC practice).
Color dominates an HPA negative cell population, such as adipocytes or adrenal glandular cells.These populations are reported as not detected in the sampled HPA tissue views (HPA: adipose tissue and adrenal gland IHC). Cross-reactivity or endogenous detection activity are possibilities; a negative tissue result alone does not identify which mechanism produced the color (general IHC practice).
Diffuse color coats nuclei and surrounding tissue with weak cell boundaries.The expected result is localized nuclear staining in the documented cell populations (HPA: tissue IHC profile; UniProt P58012: nucleus). Diffuse haze limits interpretation; review blocking, antibody concentration, washing, and chromogen development as general IHC variables (general IHC practice).
No nuclear signal appears in ovarian follicle cells on an otherwise readable section.A known positive population is missing: HPA reports medium follicle cell staining (HPA: ovary IHC). Check that follicle cells are actually present, then inspect reagent performance, retrieval, and detection using established IHC controls; this observation alone cannot establish FOXL2 absence (general IHC practice).
💡Expected FOXL2 appearanceCall the result positive when ovarian follicle cell nuclei show localized, approximately medium staining (HPA: ovary IHC; UniProt P58012: nucleus); predominant cytoplasmic or widespread staining of HPA negative cell populations is a suspect result (UniProt P58012: nucleus; HPA: tissue IHC).
How each factor affects the staining
Tissue and cell selectionOvarian follicle cells and endometrial smooth muscle cells are documented medium positive populations (HPA: tissue IHC). HPA also describes nuclear staining in ovarian and endometrial stromal cells; select and identify the intended cells before scoring (HPA: tissue IHC profile).
Negative tissue contextHPA reports adipocytes in adipose tissue and glandular cells in adrenal gland, appendix, and bronchus as not detected (HPA: tissue IHC). These are comparison populations, not proof that every cell in an entire organ lacks FOXL2 (HPA: cell-specific tissue entries).
Antibody evidenceThe listed antibody HPA069613 has Enhanced IHC validation, and HPA labels the tissue profile Enhanced based on external characterization (HPA: antibody validation; HPA: tissue IHC reliability). Validation supports the reported pattern; assess each new staining run with appropriate controls (general IHC practice).
Compartment and topologyFOXL2 is nuclear and has no transmembrane segment or signal peptide (UniProt P58012). A membrane rim or secreted-looking deposit is therefore inconsistent with its annotated location; check detection background before assigning such color to FOXL2 (UniProt P58012; general IHC practice).
IF/ICC Q: What pattern should I expect?A: Mainly nucleoplasmic signal; HPA marks that location supported in ICC-IF, while UniProt assigns FOXL2 to the nucleus (HPA: subcellular ICC-IF; UniProt P58012). Interpret IF/ICC with its dedicated guide; the tissue intensity entries here come from IHC (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Follicle cells are present but show no nuclear color.Loss of signal may reflect a run-level IHC issue; HPA expects medium staining in these cells (HPA: ovary IHC; general IHC practice).Confirm cell identity and counterstain, then review retrieval, primary antibody application, and detection alongside a documented positive section (general IHC practice).
Many unrelated cell types stain, including HPA negative populations.Possible antibody cross-reactivity, excess background, or endogenous detection activity (general IHC practice); HPA records those specified cells as not detected (HPA: tissue IHC).Compare with a no-primary control, inspect tissue-specific endogenous activity, and review blocking and detection conditions before scoring the color as FOXL2 (general IHC practice).
Cytoplasm stains more strongly than the nucleus.The pattern conflicts with FOXL2's nuclear assignment and HPA's nuclear tissue profile (UniProt P58012; HPA: tissue IHC profile).Check nuclear boundaries and the control section; review primary concentration, washing, and detection background as general IHC variables (general IHC practice).
Uniform haze obscures follicle cell nuclei.General IHC background can obscure a localized signal (general IHC practice); the expected FOXL2 pattern is nuclear (UniProt P58012; HPA: tissue IHC profile).Review blocking, washes, antibody concentration, and chromogen development; retain a readable counterstain for nuclear localization (general IHC practice).
Ovarian sections differ in apparent staining strength.The HPA entry reports a cell-specific medium level, not a required intensity for every cell or section (HPA: ovary IHC).Compare the same identified cell population across sections and check matched run controls before interpreting intensity differences (general IHC practice).
An endometrial section looks negative despite an expected positive result.HPA's medium entry is specifically for smooth muscle cells, while its profile also describes stromal nuclear staining (HPA: endometrium IHC; HPA: tissue IHC profile).Locate and score the relevant cells first; if they are present and unstained, review the positive control and routine retrieval and detection checks (general IHC practice).

Sample controls for FOXL2 IHC & IF

🧪Run ovary first and score follicle cells for nuclear staining (Medium; HPA: ovary follicle cells; UniProt P58012: nucleus). Use adipose tissue adipocytes as the negative comparator (HPA: not detected); on the ovary slide, treat cells outside the follicle-cell compartment that lack nuclear signal as internal background references, without assuming they are verified FOXL2-negative.
Positive control tissue: Endometrium (Smooth muscle cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FOXL2 in A-431, K-562, SiHa, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and clonality; the caption identifies a rabbit primary but does not state clonality (selected-SKU IHC caption; standard IHC practice). If available, use FOXL2 knockout tissue or a validated peptide-block control to test specificity, and block endogenous peroxidase before HRP/DAB detection in ovary sections (standard IHC practice; selected-SKU IHC caption: HRP/DAB).
⚠️Feasibility: The selected-SKU paraffin-section ovary caption reports EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml overnight at 4°C, but its fixative is unreported; no target-specific fixation window or fixation effect is reported (selected-SKU IHC caption). Retrieval was used in that example, but a retrieval dependency is unreported; the supplied evidence does not establish that frozen sections or IF/ICC are easier (selected-SKU IHC caption; HPA: ICC-IF images). No ovary-specific artefact is reported; check tissue autofluorescence if using IF (standard IF practice).

HPA tissue IHC evidence for FOXL2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — External characterization data supports antibody staining.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Endometrium Smooth muscle cells Medium Protein (IHC) HPA →
Ovary Follicle cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced FOXL2 IHC Tips

Troubleshoot FOXL2 staining in paraffin sections by checking retrieval, nuclear localisation, cell identity and matched controls before comparing signal intensity.

What retrieval conditions should I try first when FOXL2 staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A01185-1). The catalog antibody produced FOXL2 staining in a paraffin-embedded mouse ovary section after that retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A01185-1). If signal is weak, check that sections remained covered by buffer during heating and cool them consistently before blocking (standard IHC practice). Compare any adjusted heating time with the original condition on adjacent sections, since excessive heating can damage tissue morphology (standard IHC practice). Judge improvement by clearer follicle-cell nuclei, rather than stronger diffuse colour (HPA: ovarian follicle-cell nuclear expression; standard IHC practice).
How should I troubleshoot variable FOXL2 staining after fixation?
FOXL2-specific sensitivity to fixation is unknown here; the selected paraffin-section caption does not state its fixative (datasheet A01185-1). Record the fixative, fixation duration, tissue thickness and processing history for each specimen before attributing a signal difference to FOXL2 biology (standard IHC practice). For a controlled comparison, process matched pieces together and stain adjacent sections with the same EDTA pH 8.0 retrieval and 2 μg/ml primary antibody conditions (datasheet A01185-1; standard IHC practice). Compare nuclear signal alongside tissue preservation and a positive-control section, since poor morphology makes cell-level scoring unreliable (standard IHC practice). Do not infer fixation tolerance from FOXL2 tissue-expression patterns or its lack of a transmembrane segment (HPA: tissue IHC; UniProt P58012 topology).
How can I distinguish specific FOXL2 staining from misplaced signal?
Score FOXL2 primarily in nuclei, because UniProt places it in the nucleus and HPA supports a nucleoplasmic location (UniProt P58012 subcellular location; HPA: supported nucleoplasm). In ovary, examine follicle cells as an expected positive population and document stromal staining separately (HPA: nuclear expression in ovarian follicle cells and stromal cells). Use a counterstain that preserves nuclear boundaries, then inspect signal at high magnification before assigning positive cells (standard IHC practice). Predominantly cytoplasmic DAB, widespread extracellular colour or staining detached from intact nuclei warrants review of background and section quality (UniProt P58012 subcellular location; standard IHC practice). Keep the pH 8.0 retrieval condition consistent while resolving localisation discrepancies (datasheet A01185-1).
Could an isoform or epitope issue explain inconsistent nuclear staining?
The supplied FOXL2 record lists 0 isoforms and one chain spanning residues 1–376 (UniProt P58012 isoforms and processing). It also records phosphoserine at position 33, but provides no evidence that this modification changes recognition by the catalog antibody (UniProt P58012 modified residues; datasheet A01185-1). The antibody's epitope is not supplied, so avoid assigning weak staining to a particular residue or modification (datasheet A01185-1). Compare the same tissue across retrieval conditions and include a known staining-control section to test whether accessibility varies with processing (standard IHC practice). Report the clone or catalog identity and observed nuclear pattern when comparing studies, rather than assuming two antibodies recognize the same epitope (standard IHC practice).
How should I adapt the FOXL2 question to multiplex immunofluorescence?
Pair FOXL2 with a separately validated marker that identifies the expected follicle-cell population, and confirm that both signals can be assigned to the same cells (HPA: ovarian follicle-cell nuclear expression; standard IF practice). Choose well-separated fluorophores and inspect unstained tissue in each channel so tissue autofluorescence does not masquerade as FOXL2 signal (standard IF practice). FOXL2 is nuclear and has no transmembrane segment, so use permeabilisation that permits nuclear antibody access while preserving morphology (UniProt P58012 subcellular location and topology; standard IF practice). Check antibody-only and secondary-only controls for channel bleed-through and nonspecific fluorescence (standard IF practice). Validate IF fixation and antibody conditions independently; the paraffin-section caption supplies neither IF conditions nor a fixative (datasheet A01185-1).
What should I change when DAB background obscures FOXL2-positive nuclei?
Inspect a no-primary control to distinguish secondary or detection-system background from primary-antibody staining (standard IHC practice). Include a peroxidase block before HRP detection and control DAB development time, since these are general chromogenic IHC steps (standard IHC practice). The selected paraffin-section example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and an HRP-based DAB readout (datasheet A01185-1). If diffuse colour persists, review washing, antibody concentration and damaged section edges one variable at a time (standard IHC practice). Retain intact follicle-cell nuclei as the reference pattern when deciding whether a change improves specificity (HPA: ovarian follicle-cell nuclear expression; standard IHC practice).
How should I quantify FOXL2-positive cells across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and cell population before scoring, then count only intact nuclei with interpretable counterstain (standard IHC practice). For follicle cells, report the percentage of positive nuclei among all evaluable follicle-cell nuclei; keep stromal cells in a separate category (HPA: ovarian follicle-cell and stromal nuclear expression; standard IHC practice). If intensity matters, use an H-score from 0–300 based on the percentages at defined intensity levels, with thresholds fixed before comparing groups (standard IHC practice). Alternatively, report positive nuclei per mm² of evaluable tissue and state the excluded damaged or necrotic area (standard IHC practice). Apply identical retrieval, detection, imaging and scoring rules across sections (standard IHC practice).
When is an apparent FOXL2-positive cell likely to be an artefact?
Treat crisp nuclear staining in the expected follicle-cell population as stronger evidence than diffuse cytoplasmic colour (HPA: ovarian follicle-cell nuclear expression; UniProt P58012 subcellular location). Check whether staining is concentrated at section edges, folds or necrotic regions before calling those cells positive (standard IHC practice). Compare the suspect area with a no-primary control to identify endogenous enzyme or detection-system colour (standard IHC practice). HPA reports medium FOXL2 staining in ovarian follicle cells and no detection in adipocytes from adipose tissue, which can guide tissue-level control selection (HPA: ovary follicle cells medium; adipose tissue adipocytes not detected). Interpret any positive result alongside compartment, cell identity and tissue integrity, rather than DAB intensity alone (standard IHC practice).
Boster reagents

Best FOXL2 / Forkhead box protein L2 IHC Antibodies

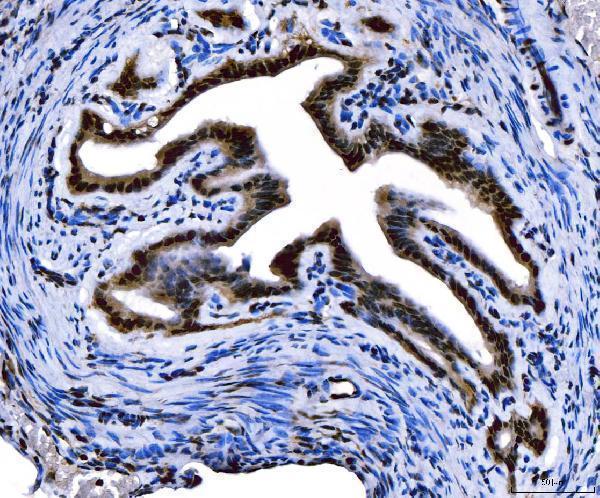
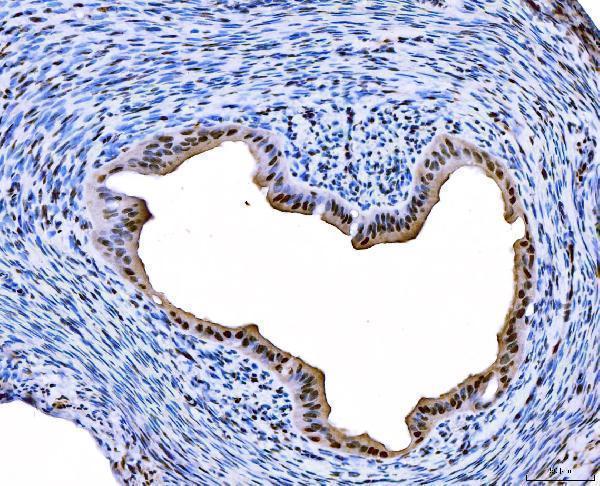
The catalog antibody has real IHC images from paraffin sections of mouse and rat ovary and human lung and ovarian cancer tissue (catalog image captions); no IF data are supplied (catalog payload).

Real IHC data IHC analysis of FOXL2 using anti-FOXL2 antibody (A01185-1). FOXL2 was detected in a paraffin-embedded section of mouse ovary tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-FOXL2 Antibody (A01185-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-FOXL2 Antibody ®
Cat # A01185-1

A01185-1 is listed for IHC in human, mouse, and rat samples (catalog: applications and reactivity). Its IHC captions show paraffin sections of mouse and rat ovary and human lung and ovarian cancer tissue; they do not report the fixative (catalog image captions).

Which to pick: Choose A01185-1 for paraffin-section IHC: its mouse ovary caption documents EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml (A01185-1 IHC image caption). It is the listed cross-species option for human, mouse, and rat IHC (catalog: applications and reactivity); the captions do not report the fixative (A01185-1 IHC image captions). No IF/ICC choice can be recommended because IF/ICC is absent from its application list and no IF image is supplied (catalog payload).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P58012 (FOXL2_HUMAN, Forkhead box protein L2).
  2. Human Protein Atlas. FOXL2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. FOXL2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm..
  4. Human Protein Atlas. FOXL2 antibody validation summary (1 antibodies).
  5. Molecular cloning and analysis of gonadal expression of Foxl2 in the rice-field eel Monopterus albus. Scientific reports 2014 — PMC4217102.
  6. Protective effect of luteinizing hormone on frozen-thawed ovarian follicles and granulosa cells. PloS one 2025 — PMC11731763.
  7. Clinical and genetic analysis of recurrent adult-type granulosa cell tumor of the ovary: Persistent preservation of heterozygous c.402C>G FOXL2 mutation. PloS one 2017 — PMC5464638.
  8. Investigating autoimmunity in the etiology of premature ovarian insufficiency in a mouse model. Journal of reproductive immunology 2026 — PMC13328056.
  9. PubMed PMID:11175783 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:16153597 — UniProt-cited evidence.