This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for FSCN1 using the catalog antibody at 1:50 on paraffin sections (datasheet M02147-1). Use cytoplasmic staining in the documented cell populations to guide interpretation (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in tissue cells (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic in tubules, glia, endothelium, fibroblasts and macrophages (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M02147-1) | |
| Positive control | Breast+4 more · see all | |
| Negative control | Bronchus+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Macrophage and endothelial staining can complicate cell scoring (HPA tissue IHC) | |
| Regulation | Low tissue specificity; staining varies by cell type (HPA tissue IHC) | |
| Isoform / epitope | No isoforms annotated; Fascin chain spans residues 2–493 (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet M02147-1) is paired with four published FSCN1 IHC protocols (PMC2833258; PMC13243165; PMC13461984; PMC6494834).
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet M02147-1) |
| Fixation | Image fixative and duration unreported (datasheet M02147-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M02147-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M02147-1) |
| Primary antibody | Rabbit monoclonal (clone ADOA-6) anti-FSCN1, 1:50 (datasheet M02147-1) |
| Primary incubation | Overnight at 4 °C (datasheet M02147-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet M02147-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | FSCN1-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in cells in seminiferous tubules, glial cells, endothelial cells, fibroblasts and macrophages. No signal in the no-primary control. |
FSCN1 should stain predominantly in the cytoplasm of selected cells, including glial cells, endothelial cells, fibroblasts, macrophages and cells in seminiferous tubules (HPA: tissue IHC profile). Cortical or projection-associated signal is also plausible because FSCN1 is an actin-bundling protein with no transmembrane segment (UniProt Q16658: function, localization and topology). The tissue IHC profile is rated Enhanced (HPA: reliability).
| Cytoplasmic staining is strong in lung endothelial cells, cerebral cortex glial cells or testis Sertoli cells, with adjacent cells showing different intensities (HPA: High in these cell populations). | This fits the cell-specific IHC pattern. Score the identified cells and their compartment rather than treating the whole tissue as uniformly positive; HPA reports staining by cell population (HPA: tissue IHC). |
| The apparent positive signal is confined to nuclei, with no convincing cytoplasmic staining in expected positive cells. | Treat an isolated nuclear pattern as suspect: UniProt places FSCN1 in the cytosol, cortex, cytoskeleton and projections, while HPA describes cytoplasmic tissue staining (UniProt Q16658: localization; HPA: tissue IHC profile). Check morphology and staining controls before scoring it. |
| Strong signal appears in bronchial respiratory epithelium or duodenal glandular cells (HPA: Not detected in these cell populations). | That distribution conflicts with the cited HPA observations, so investigate cross-reactivity or endogenous detection activity (HPA: tissue IHC; general IHC practice). It does not make every cell in the bronchus or duodenum a negative control. |
| A broad, poorly localized chromogenic haze covers positive and expected negative cell populations. | This is difficult to assign to FSCN1 because the reference pattern is cell-selective and mainly cytoplasmic (HPA: tissue IHC profile). Review blocking, antibody concentration and detection controls as general IHC troubleshooting steps (general IHC practice). |
| Known positive cells, such as lung endothelial cells or testis Sertoli cells, show no discernible cytoplasmic signal (HPA: High in these cells). | A failed positive control makes a negative result in the study specimen uninterpretable. Check tissue preservation, antigen retrieval and detection performance as general IHC workflow variables; the supplied sources do not define FSCN1-specific fixation sensitivity (general IHC practice). |
| Cell context and scoring | HPA reports High staining in breast glandular cells but Not detected in duodenal glandular cells; cell identity and tissue context therefore matter when choosing comparison fields (HPA: tissue IHC). Its low tissue RNA specificity is not a claim that every cell stains equally (HPA: RNA specificity and tissue IHC). |
| Target location and topology | FSCN1 has no transmembrane segment or signal peptide, and UniProt lists cytosolic, cortical, cytoskeletal and projection locations (UniProt Q16658: topology, processing and localization). Judge a chromogenic pattern against the identified cell compartment; a crisp surface outline alone is insufficient evidence of the expected tissue IHC pattern (HPA: cytoplasmic profile). |
| Strength of the reference pattern | The HPA tissue profile is Enhanced, with high consistency between staining and RNA data and support from similar staining by paired antibodies (HPA: reliability description). This supports the reference distribution but does not establish the performance of every antibody or preparation in a new laboratory. |
| IF/ICC Q&A: what location should be expected? | Expect mainly cytosol; HPA also lists plasma membrane with uncertain support in ICC-IF images (HPA: subcellular summary and location). UniProt additionally places FSCN1 at the cell cortex and actin-rich projections (UniProt Q16658: localization). This is an interpretation cue for IF/ICC, not an IHC-P protocol option. |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in both study tissue and an HPA-positive control population. | The IHC run may have failed; absence in lung endothelial cells or testis Sertoli cells conflicts with the HPA reference pattern (HPA: High in these cells). | Check the control section, retrieval conditions, antibody dilution and detection reagents before interpreting the study tissue (general IHC practice). The supplied sources give no FSCN1-specific retrieval condition or fixation effect. |
| Background obscures cell boundaries across the section. | Nonspecific antibody binding or detection background can obscure a cell-selective cytoplasmic pattern (general IHC practice; HPA: tissue IHC profile). | Review blocking and antibody concentration, then compare a no-primary control with the stained section (general IHC practice). |
| Signal appears in cells HPA labels Not detected. | For example, strong bronchial respiratory epithelial staining may reflect cross-reactivity or endogenous detection activity (HPA: Not detected in bronchial respiratory epithelial cells; general IHC practice). | Inspect a no-primary control and confirm cell identity and compartment; compare a known positive population on the same run where available (general IHC practice; HPA: tissue IHC). |
| Only nuclei appear positive. | An isolated nuclear pattern does not match the supplied cytoplasmic tissue profile or UniProt localization (HPA: tissue IHC profile; UniProt Q16658: localization). | Check counterstain and chromogen appearance, then repeat interpretation against a known cytoplasmic positive control (general IHC practice; HPA: tissue IHC profile). |
| A peripheral rim is the dominant signal. | FSCN1 can associate with the cell cortex, but HPA's tissue profile emphasizes cytoplasm; its ICC-IF plasma membrane assignment is uncertain (UniProt Q16658: localization; HPA: tissue IHC and subcellular location). | Look for accompanying cytoplasmic signal and compare cell morphology and controls before calling the rim specific (general IHC practice; HPA: tissue IHC profile). |
| A whole organ is called negative despite scattered positive cells. | HPA reports expression in named cell populations, including glial cells in cerebral cortex and cells in kidney glomeruli (HPA: High in these populations). | Re-examine the relevant compartment at suitable magnification and record the positive cell population separately from surrounding tissue (general IHC practice; HPA: tissue IHC). |


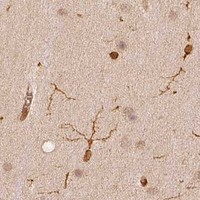

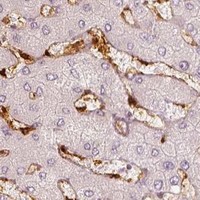


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Antibody staining in cells/structures not annotated, view images. Paired antibodies with high similarity supports the protein expression pattern.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Processes in white matter | High | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in glomeruli | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot FSCN1 staining in paraffin sections by checking retrieval, cell type, subcellular pattern, and controls before changing scoring thresholds.
M02147-1 has IHC images of paraffin sections from human tonsil and mouse and rat spleen (catalog IHC image captions). IF/ICC is listed, but no IF image is supplied (catalog applications; IF image alts).
M02147-1 has IHC images of paraffin sections from human tonsil, mouse spleen, and rat spleen (catalog IHC image captions). It lists IHC and IF/ICC applications and human, mouse, and rat reactivity; no IF image is supplied (catalog applications; catalog reactivity; IF image alts).
Which to pick: For tissue IHC, choose M02147-1: its own captions document paraffin sections, 1:50 primary dilution, EDTA retrieval at pH 8.0, and DAB detection; the fixative is unreported (M02147-1 IHC image captions). For IF/ICC, M02147-1 is the listed option, with a catalog dilution of 1:50, although no IF figure is supplied (catalog applications; catalog IF dilution; IF image alts). For cross-species IHC, this rabbit monoclonal clone ADOA-6 lists human, mouse, and rat reactivity and has an IHC image for each species (catalog host/clone/reactivity; M02147-1 IHC image captions).