This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan FZD5 IHC in paraffin sections using the cytoplasmic tissue pattern reported for gastrointestinal glands, placenta and brain (HPA tissue IHC). Compare that pattern with its annotated membrane and Golgi locations when interpreting staining (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in tissue; membrane and Golgi annotated (HPA tissue IHC; UniProt) | |
| Staining pattern | Cytoplasmic in GI glands, trophoblasts and neurons (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A04292-1) | |
| Positive control | Caudate+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A04292-1) | |
| Caveat | Tissue IHC is cytoplasmic despite membrane annotation (HPA tissue IHC; UniProt) | |
| Regulation | Expression regulation is not annotated (UniProt) | |
| Isoform / epitope | No isoforms listed; epitope location depends on topology (UniProt) |
The catalog antibody has a heat-mediated, pH 9.0 IHC-P protocol (datasheet A04292-1). Four published FZD5 IHC protocols provide tissue-specific starting points (PMC7717951; PMC6487103; PMC6007469; PMC13560161).
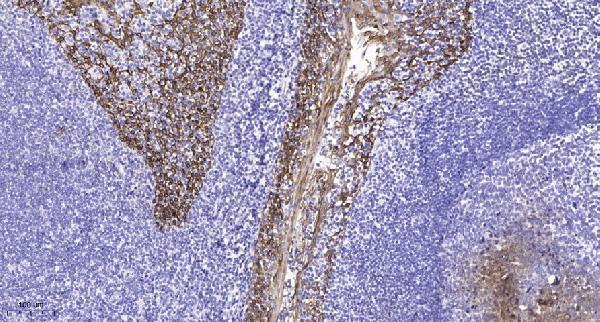
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A04292-1) |
| Fixation | Image fixative and duration unreported (datasheet A04292-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A04292-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-FZD5, 1:100-1:300 (datasheet A04292-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | FZD5-positive staining in neuronal cells of caudate (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression mainly in glandular cells in the gastrointestinal tract, placenta and the brain. No signal in the no-primary control. |
FZD5 is a 7-transmembrane receptor at the plasma membrane and Golgi apparatus (UniProt Q13467 topology; UniProt Q13467 subcellular location). In paraffin-section IHC, expect staining in glandular cells of the gastrointestinal tract, trophoblastic cells of the placenta, and selected brain cells; HPA describes the observed pattern as mainly cytoplasmic (HPA tissue IHC). HPA rates its tissue IHC evidence Approved, pending external verification (HPA tissue IHC).
| Cell-associated chromogenic staining in duodenal or small-intestinal glandular cells, placental trophoblastic cells, or selected neurons (HPA tissue IHC). | This fits HPA's Medium staining in those cell populations (HPA tissue IHC). Membrane-associated and cytoplasmic signal can both be plausible: UniProt places FZD5 at the plasma membrane and Golgi, while HPA describes mainly cytoplasmic tissue staining (UniProt Q13467 subcellular location; HPA tissue IHC). |
| Predominantly nuclear staining, with little convincing membrane-associated or cytoplasmic signal. | A nuclear-dominant pattern does not match the reported FZD5 locations or HPA tissue pattern (UniProt Q13467 subcellular location; HPA tissue IHC). Treat it as a possible staining artefact and compare it with a negative reagent control before scoring it as FZD5 (general IHC practice). |
| Strong staining in adipocytes or cardiomyocytes, while expected positive cells show little signal. | HPA reports FZD5 as Not detected in those specific cell populations (HPA tissue IHC). Consider antibody cross-reactivity or endogenous chromogenic activity; inspect cellular boundaries and control sections before assigning the signal to FZD5 (general IHC practice). |
| Diffuse color across cells, stroma, and empty slide areas, without a consistent cellular pattern. | This does not resemble HPA's cell-restricted observations (HPA tissue IHC). Background from nonspecific antibody binding, detection reagents, or incomplete washing can obscure a real signal; the pattern alone cannot identify which step caused it (general IHC practice). |
| No convincing staining in duodenal glandular cells or placental trophoblastic cells. | Both populations have Medium HPA tissue IHC staining (HPA tissue IHC). A blank result warrants a check of section integrity, retrieval, antibody and detection performance before concluding that the specimen lacks FZD5 (general IHC practice). |
| Compartment and topology | FZD5 has 7 transmembrane segments and is reported at the plasma membrane and Golgi (UniProt Q13467 topology; UniProt Q13467 subcellular location). HPA's paraffin-section profile is mainly cytoplasmic, so a cytoplasmic result is compatible with its observations; topology alone cannot establish the appearance of this antibody's IHC stain (HPA tissue IHC). |
| Choice of comparison cells | HPA reports Medium staining in duodenal and small-intestinal glandular cells and placental trophoblastic cells, but Not detected in adipocytes and cardiomyocytes (HPA tissue IHC). Compare named cell populations, rather than treating an entire organ as uniformly positive or negative (HPA tissue IHC). |
| Strength of pattern evidence | The tissue profile and listed IHC antibody HPA052361 are Approved; the profile is pending external verification, and the antibody is not listed as Enhanced (HPA tissue IHC; HPA antibodies). Use the reported pattern as a reference, while treating an unexpected result as something to investigate rather than an automatic biological finding. |
| Extracellular region and processing | UniProt places an extracellular region at residues 27–238, lists N-glycosylation sites at 47 and 151, and describes a signal peptide at 1–26 (UniProt Q13467 topology; UniProt Q13467 processing; UniProt Q13467 glycosylation). The supplied evidence gives no antibody epitope, so these annotations do not predict retrieval needs or staining loss. |
| Antigen retrieval | Retrieval is a routine variable to check when paraffin-section IHC lacks signal (general IHC practice). The supplied UniProt and HPA records give no FZD5-specific retrieval condition or fixation-sensitivity finding; select and assess conditions using the IHC-validated antibody's instructions and controls. |
| IF/ICC Q&A: should the IHC pattern be expected in cells? | HPA summarizes FZD5's ICC-IF location as Membrane but provides no main location or cell-line images in this payload (HPA subcellular). UniProt also reports plasma membrane and Golgi locations (UniProt Q13467 subcellular location). These records support a location check, not a validated IF/ICC staining appearance or protocol. |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive glandular or trophoblastic cells are blank (HPA tissue IHC). | The staining run may have failed, or the specimen may have inadequate evaluable cells; the image alone cannot distinguish these possibilities (general IHC practice). | Check section morphology, the run's positive control, retrieval record, primary-antibody application, and detection reagents; repeat with a documented working run if a control failed (general IHC practice). |
| Signal is weak in an HPA-positive cell population (HPA tissue IHC). | Low assay sensitivity or an unsuitable retrieval or antibody condition may reduce visible chromogen (general IHC practice). HPA's Medium category does not specify a required intensity for every specimen (HPA tissue IHC). | Compare cells on the same run with a positive control and the documented IHC conditions; adjust one routine assay variable at a time if controls support troubleshooting (general IHC practice). |
| Color appears in adipocytes or cardiomyocytes, where HPA reports Not detected (HPA tissue IHC). | Cross-reactive binding or endogenous detection activity is possible; HPA's observation does not identify which explanation applies (HPA tissue IHC; general IHC practice). | Review a negative reagent control and an expected positive cell population, then check endogenous-enzyme blocking and detection controls for the chromogenic method used (general IHC practice). |
| Predominantly nuclear staining replaces the expected cell-associated pattern. | The location conflicts with UniProt's membrane and Golgi annotation and HPA's mainly cytoplasmic profile (UniProt Q13467 subcellular location; HPA tissue IHC). Nonspecific staining is possible (general IHC practice). | Check whether the color persists in a negative reagent control, inspect counterstain separately, and avoid scoring nuclear-only signal as FZD5 without independent support (general IHC practice). |
| Diffuse chromogen makes individual positive cells hard to identify. | Nonspecific binding, residual detection activity, or insufficient washing can raise background in chromogenic IHC (general IHC practice). | Compare a negative reagent control, confirm the blocking and wash steps used, and assess whether recognizable HPA-positive cells remain above background (general IHC practice; HPA tissue IHC). |
| A section from an HPA-positive tissue disagrees with the reference pattern (HPA tissue IHC). | The sampled cell population, tissue condition, or assay performance may differ; HPA's Approved profile is pending external verification (HPA tissue IHC; general IHC practice). | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Medium | Protein (IHC) | HPA → |
| Hippocampus | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Placenta | Trophoblastic cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot FZD5 staining in paraffin sections by checking retrieval, cell type, and compartment before comparing signal intensity across samples.
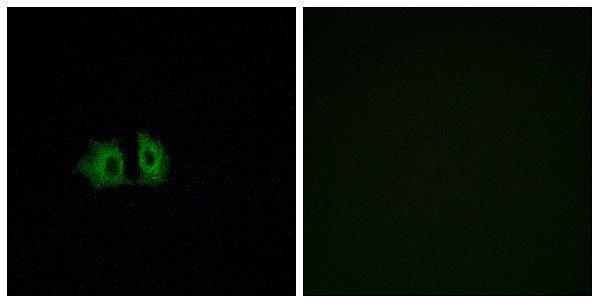
Anti-FZD5 options list human, mouse and rat reactivity (catalog: reactivity); A04292-1 has human tonsil IHC and A549-cell IF images (A04292-1 image captions).
A04292-1 lists IHC and IF, with images of paraffin-embedded human tonsil and A549 cells (A04292-1 applications; image captions). A04292-2 lists IHC, IF and ICC, while A04292Y500 lists IHC and IF; both list human, mouse and rat reactivity, but neither has an IHC image in this payload (catalog: applications, reactivity, IHC image alts).
Which to pick: For tissue IHC, choose A04292-1: its own caption documents paraffin-embedded human tonsil stained at 1:200 after Tris-EDTA retrieval at pH 9.0; the fixative is unreported (A04292-1 IHC caption). For IF/ICC, A04292-2 lists both applications and is polyclonal (A04292-2 applications; dilution_raw); A04292-1 also has an A549-cell IF image (A04292-1 IF caption). For cross-species IHC, start with A04292-1 because it lists human, mouse and rat reactivity, while recognising that its IHC image documents human tissue only (A04292-1 reactivity; IHC caption).